


Released on May 20, 2026

FEATURED ARTICLES BY













The modern workforce is operating under a compounding set of performance risks. From chronic stress and behavioral health decline to physical inactivity and poor environmental design, left unaddressed, these risks erode organizational resilience, mission effectiveness, and competitive advantage. This paper argues that workforce well-being can no longer be treated as a benefits checkbox or a post-crisis intervention. It must be positioned as a strategic performance lever, one that federal contractors, government agencies, and enterprise organizations can systematically measure, manage, and optimize.
Every organization tracks revenue, turnover rates, and productivity. Few track what we call the Performance Risk Index the cumulative drag on organizational performance caused by unaddressed workforce health vulnerabilities. According to the World Health Organization, depression and anxiety alone cost the global economy an estimated $1 trillion per year in lost productivity.¹ In the United States, the American Psychological Association found that 76% of workers reported at least one symptom of a mental health condition in the past year — yet fewer than one-third had access to an employer-supported mental health resource.²
The federal contracting sector faces a particularly acute version of this challenge. Personnel hold security clearances, manage high-consequence decisions, and operate in environments where cognitive performance, stress tolerance, and physical readiness directly affect mission outcomes. Yet the infrastructure to manage workforce performance risk in these environments has historically lagged the private sector by years.
The result? Organizations absorb the costs of presenteeism (reduced productivity while at work), attrition (the financial and institutional cost of losing experienced personnel), and operational fragility — while attributing these losses to market conditions rather than to the manageable health of their workforce.
$1.9T
Annual cost of lost productivity from poor workforce health (WHO, 2024)
76%
of U.S. workers report at least one symptom of a mental health condition (APA, 2023)
6:1
Average ROI for every dollar invested in integrated workforce wellness (HBR, 2023)
Sources: ¹ WHO Global Report, 2024; ² APA Work and Well-Being Survey, 2023; ³ Harvard Business Review Meta-Analysis, 2023
II.FROM COMPLIANCE TO CULTURE: A PARADIGM SHIFT
For two decades, workplace wellness has been framed primarily as a compliance and benefits administration function. Organizations offered gym memberships, annual health fairs, and Employee Assistance Program (EAP) hotlines — and checked the wellness box. What research now confirms is that transactional wellness programs produce transactional results
A 2023 meta-analysis published in the *Journal of Occupational Health Psychology* found that wellness programs with no cultural integration yielded less than 12% sustained behavior change among participants, compared to 54% among programs embedded in daily workflow and managerial practice.³ This isn't just a programming question — it's a leadership and organizational design question.
The organizations winning the talent war and sustaining mission performance are those that have made wellbeing a strategic business function resourced like operations, measured like finance, and led from the executive level. They understand that healthy teams are not a liability offset; they are a competitive differentiator.
"Performance risk is not an HR issue. It is an enterprise risk issue and it belongs in the boardroom." Fran Dean-Bishop
Over 27 years of delivering health, wellness, and workforce performance programs across federal agencies and Fortune-class enterprises, my team at Aerobodies Inc. has developed a structured approach to what we now call Workforce Transformation Solutions (WTS) a systems-level framework for identifying, quantifying, and addressing the full spectrum of performance risk across an organization.
WTS operates across three integrated domains:
■ Human Performance Infrastructure assessing the physical, behavioral, and cognitive health baseline of the workforce through evidence-based screenings, occupational health protocols, and ergonomic evaluations.
■ Environmental Health Optimization ensuring that the built environment itself supports human performance through WELL Building Standard principles, workspace ergonomics, and air and light quality standards proven to enhance cognitive output.
■ Cultural and Behavioral Change Management equipping leaders with the tools, data, and coaching to embed well-being into organizational culture, not just programming calendars including addiction prevention, stress resilience, and psychological safety strategies.
What differentiates this framework from traditional wellness vendor offerings is its measurement architecture Every WTS engagement is built around a baseline assessment, quarterly performance risk reporting, and a return-on-investment model tied to specific organizational outcomes reduced absenteeism, clearance retention, injury rates, and talent acquisition costs. This is the language of the boardroom applied to the science of human performance.
The convergence of post-pandemic behavioral health decline, federal return-to-office mandates, and AI-driven workforce restructuring is creating a perfect storm of performance risk. Organizations that respond with legacy wellness thinking reactive, siloed, and unmeasured will find themselves managing the symptoms while the root causes compound.
Leaders in government contracting and enterprise environments must take three concrete steps:
First, conduct a Performance Risk Audit. Understand what your data is and is not telling you about workforce health. Most HRIS and EAP systems generate reporting that obscures as much as it reveals. You need an independent, structured assessment.
Second, invest in integration, not addition. Adding another wellness app or vendor will not move the needle. What moves the needle is weaving performance health into your existing operational rhythms onboarding, leadership development, facilities strategy, and contract performance management.
Third, demand accountability from your wellness infrastructure. Every dollar invested in workforce health should generate measurable returns. If your current wellness provider cannot show you a performance dashboard tied to business outcomes, you are not managing performance risk you are managing optics.
The future of competitive advantage in government contracting is not technology alone. It is technology plus human performance — and the organizations that understand this will be the ones that endure.
1. World Health Organization. (2024). Mental health in the workplace. Geneva: WHO Press.
2. American Psychological Association. (2023). 2023 Work and Well-Being Survey. APA Center for Organizational Excellence.
3. Goetzel, R.Z., et al. (2023). Return on investment in workplace wellness programs: A meta-analysis. Journal of Occupational Health Psychology, 28(4), 312–329.
4. Gallup. (2024). State of the Global Workplace: 2024 Report. Gallup Press.
5. McKinsey Health Institute. (2023). Addressing employee burnout: Are you solving the right problem? McKinsey & Company.
6. Harvard Business Review. (2023). The ROI of employee well-being programs. HBR Analytics Services.
Fran Dean-Bishop is the Founder, CEO, and Executive Performance Advisor at Aerobodies Inc. With over 27 years of experience designing and managing health, wellness, and workforce performance programs for federal agencies and global enterprises, she is a recognized authority on workforce resilience, human performance risk, and integrated occupational wellness strategy. She is a WELL Building Accredited Professional, an Executive Leadership Coaching Certificate holder from Georgetown University, and serves on the Board of Directors of the Professional Services Council. She is the publisher of the Performance Risks newsletter and creator of the Workforce Transformation Solutions (WTS) framework.
franb@aerobodies.com | 703-820-0217 www.aerobodies.com
Aerobodies Inc. operates at the intersection of government contracting and commercial wellness solutions, delivering programs focused on human performance, resilience, and workforce well-being. A woman-owned small business founded in 1997, Aerobodies provides federal and state agencies and private industry organizations with a comprehensive suite of health, wellness, and process improvement services — including occupational health management, ergonomic and WELL building consulting, behavioral health programming, fitness and wellness facility management, and enterprise workforce transformation engagements. Aerobodies consistently demonstrates quantifiable program outcomes, achieving measurable impact on business performance, operational efficiency, and the human capital that powers mission success. Alexandria, Virginia | Serving clients nationwide









Agencies can now collect vast quantities of health-related information. The challenge lies in transforming this information into insight that supports timely and effective decisions and interventions. There is a critical need to build integrated systems that connect digital infrastructure, exploratory analytics, and population health research into a continuous model for informed decision-making and improved outcomes. Authored by DLH Strategic Account Executive, Dr. Vicki Hart, this paper introduces the Readiness Data Value Chain, a framework for turning fragmented health information into actionable intelligence that strengthens population health and operational readiness across federal health systems.
Effective population health management requires a continuous value chain that connects the generation and integration of health data to scientific research that guides critical decisions and improves outcomes.
Within federal health environments, relevant signals emerge from many sources, including clinical records, occupational health systems, environmental monitoring, surveillance reporting, and communitylevel indicators, such as social determinants of health. When these signals are fully integrated and analyzed through robust methods, they reveal patterns that help leaders understand risk, anticipate emerging challenges, and intervene earlier.
The Readiness Data Value Chain organizes this process into a sequence of connected stages:
1. Data generation and collection across clinical, operational, environmental, and population health systems
2. Data integration and governance to ensure interoperability, quality, and secure sharing
3. Exploratory analytics that surface patterns, anomalies, and emerging signals
4. Scientific research that determines causal relationships and establishes evidence
5. Decision intelligence that translates evidence into operational guidance
6. Action and continuous learning, where interventions generate new data and insight
The Readiness Data Value Chain provides a structured way to connect the elements of modern health data systems, from the infrastructure for collection and integration to analytic discovery, scientific investigation, and operational decisionmaking. Rather than viewing these activities as separate functions, the value chain frames them as an integrated system that transforms health data into actionable insight for population health and readiness.
Figure 1 (below) illustrates the Readiness Data Value Chain framework, showing the progression from health data collection to decision-making and action. Within this value chain, analytic methods operate along a continuum from exploratory clustering and correlation to epidemiologic research and predictive modeling that establish causal relationships and inform action.
Integrated data systems operate alongside a continuum of analytic methods that detect emerging signals, establish causality, and inform evidence-based operational decisions.
Modern analytic tools offer powerful methods to identify patterns and opportunities in complex health data.
Artificial intelligence and machine learning can rapidly detect trends, identify anomalies, and uncover relationships across large and diverse datasets. However, pattern detection alone does not produce actionable knowledge. Insight emerges when exploratory methods are integrated with and inform scientific analysis and research.
The analytic continuum can be described in four stages:
analysis, modeling, correlation analysis
causality and intervention pathways Epidemiology, casual inference, study design
Inform decisions and actions Forecasting, visualization, decision support
In this framework, AI and machine learning play a critical role in generating hypotheses and identifying emerging patterns and are complemented by the scientific rigor of epidemiology and population health research. Together, these disciplines transform raw data into evidence that can reliably inform policy, operational planning, and targeted interventions.
For federal health agencies, this integrated analytic approach represents a critical shift towards a continuous pathway from pattern detection to evidence-based, defensible decision-making.
The Readiness Data Value Chain is illustrated through an environmental health study in which DLH scientists paired this framework with a continuum of analytic methods to transform disparate data into actionable population health insight.
DLH co-authored a study exploring the association between concentrated animal feeding operations (CAFOs) and immune-mediated disease outcomes. We first integrated diverse data sources, including geospatial location data, participant health records, demographic factors, and genomic data, to create a unified analytic dataset with appropriate quality and security controls.
We then applied methods across the analytic continuum:
• Through explorator y and statistical analysis, we identified population-level patterns suggesting that individuals living closer to CAFOs exhibited higher prevalence of immune-mediated diseases, including rheumatoid arthritis.
• We advanced scientific evaluation by incorporating genomic data to evaluate geneenvironment interactions, revealing that specific genetic variants affect susceptibility to environmental exposure and providing evidence of biologically plausible pathways between exposure and disease.
• By identifying populations at elevated risk based on both exposure and susceptibility, our findings enabled operational interventions, including more targeted surveillance, prevention strategies, and policy development.
The progression from signal detection to mechanistic understanding and meaningful action demonstrates the full value of the Readiness Data Value Chain and analytic continuum: Integrated data systems enable exploratory analytics that inform targeted evaluation and evidence-based findings, enabling leaders to protect population health and improve outcomes.
While modern technology enables powerful new analytic capabilities, successful health intelligence systems remain fundamentally people centered.
Advancing work along the Readiness Data Value Chain requires the collaboration of multiple disciplines, including data scientists, statisticians,
epidemiologists, clinicians, operational leaders, and more. Each plays a critical role in interpreting signals, validating findings, and translating evidence into policy or operational guidance.
Thus, effective analytic systems are not solely defined by technology but by the integration of human expertise with digital capabilities. AI may detect patterns, but experienced scientists determine whether those patterns represent significant relationships. Analysts and subject-matter experts provide the contextual understanding required to interpret results accurately and determine meaningful action.
Organizations that cultivate interdisciplinary teams and collaborative analytic environments will be better positioned to transform raw data into actionable insight. By aligning digital tools with scientific expertise and operational leadership, federal health agencies can create systems that support informed decision-making.
As federal health systems modernize their digital infrastructure, leaders face an important strategic choice: whether to treat data systems, analytics, and research capabilities as separate functions or to integrate them into a unified decision value chain.

Successful integration requires several critical capabilities:
1. Building interoperable data ecosystems: Population health insight depends on integrating clinical, operational, and environmental data across organizational boundaries.
2. Connecting AI-driven discovery to scientific research: Exploratory analytics lead the way to rigorous epidemiologic methods that ensure findings are reliable and defensible.
3. Cultivating interdisciplinar y analytic teams: Decision intelligence depends on collaboration between technical experts, scientists, and operational leaders.
4. Translating population health insight into targeted action: Effective analytic systems reveal patterns across large populations and environments, enabling early intervention and requiring evaluation of interventions across diverse subpopulations.
5. Designing for continuous learning: Each intervention generates new data that will refine models, improve associations, and strengthen future decisions.
By adopting this integrated approach, federal health agencies can move beyond fragmented analytics toward a comprehensive understanding of the factors shaping population health and readiness.
The Readiness Data Value Chain provides a framework for transforming health-relevant information into timely, reliable insight. By linking digital infrastructure, advanced analytics, and population health science into a continuous system, agencies can move from detecting signals to understanding causes and implementing effective interventions.
In doing so, federal health leaders turn today’s expanding universe of health data into a strategic asset for the future, strengthening both population health and operational readiness.
About DLH
DLH (NASDAQ: DLHC) enhances technology, public health, and cybersecurity readiness missions through science, technology, cyber, and engineering solutions and services. Our experts solve some of the most complex and critical missions faced by federal customers, leveraging digital transformation, artificial intelligence, advanced analytics, cloud-based applications, telehealth systems, and more. With a world-class workforce dedicated to the idea that “Your Mission is Our Passion,” DLH brings a unique combination of government sector experience, proven methodology, and unwavering commitment to innovative solutions to improve the lives of millions. For more information, visit www.DLHcorp.com.
We’d love to discuss further.
To learn more about DLH data solutions, please contact:
Dr. Vicki Hart
Strategic Account Executive, Science, Research and Development
Vicki.Hart@DLHcorp.com
Beneath The Greenbrier lies one of the most remarkable examples of Cold War continuity planning: a once-secret underground bunker built to house the United States Congress in the event of nuclear war. Known as Project Greek Island, this facility represents a unique intersection of government contracting, infrastructure innovation, and public-private collaboration.
For today’s government contracting community, the Greenbrier Bunker offers enduring lessons in continuity of operations, dual-use infrastructure, operational secrecy, and strategic partnerships. In an era defined by cyber threats, geopolitical uncertainty, and distributed risk, these lessons are more relevant than ever.
In the late 1950s, at the height of Cold War tensions, the federal government prioritized the development of secure facilities to ensure the survival and functionality of national leadership in the event of a nuclear attack. The result was the construction of a classified relocation site beneath The Greenbrier.
Completed in the early 1960s, the bunker was designed to accommodate all 535 members of Congress along with essential staff. The facility included fully operational House and Senate chambers, dormitories, medical areas, and communications infrastructure. It was engineered to allow Congress to reconvene and govern in the aftermath of a catastrophic event.
The driving concept continuity of government (COG) remains foundational today. While the nature of threats has evolved, the requirement to maintain operational capability during disruption has not.
What makes the Greenbrier Bunker particularly relevant to a Professional Services Council audience is how it was executed: within a private-sector environment
The facility was constructed beneath an active luxury resort and concealed as part of a routine expansion. Its ongoing maintenance was handled by personnel posing as civilian technicians, allowing the operation to remain classified for more than three decades.
This model highlights several principles still central to government contracting:
• Integration of federal missions into commercial infrastructure
• Reliance on private-sector expertise and discretion
• Long-term trust between government and industry partners
Today, similar frameworks underpin:
• Cloud computing and FedRAMP-authorized environments
• Defense-industrial base partnerships
• Critical infrastructure protection across energy, telecom, and transportation
The Greenbrier Bunker demonstrates that effective national security solutions often depend on seamless collaboration between public and private entities
The bunker was designed as a fully self-sustaining facility capable of operating independently for extended periods.
Key features included:
• Reinforced structural systems and massive blast doors
• Independent power generation and water supply
• Medical facilities and food storage
• Secure communications systems
From its completion until its decommissioning in 1992, the bunker was maintained in a constant state of readiness despite never being used.
For today’s contracting environment, this reinforces a critical point: Resilience is not reactive it is built, maintained, and continuously validated.
Modern parallels include:
• Secure and redundant data centers
• Continuity of Operations (COOP) facilities
• Cyber resilience architectures
• Distributed command-and-control systems
The shift from physical to digital infrastructure does not diminish the importance of resilience it expands it.
The bunker remained classified until it was publicly revealed in 1992, prompting its immediate decommissioning.
This moment underscores a key challenge that persists today: the difficulty of sustaining long-term secrecy in a connected world.
For government contractors, this raises several important considerations:
• Security vs. transparency: Balancing mission protection with public accountability
• Information control: Managing sensitive data in an era of digital exposure
• Reputational risk: Preparing for how programs are perceived once disclosed
In the modern landscape where cyber breaches, insider threats, and real-time media are constant factors contractors must design systems and programs with the expectation that information may eventually surface.
The Greenbrier Bunker offers a framework that translates directly to today’s operating environment:
A. Continuity Planning is Essential
COG and COOP remain central to federal missions and contractor support roles. Whether addressing cyber incidents, natural disasters, or geopolitical disruptions, continuity must be embedded in every layer of operations.
B. Public-Private Partnerships are Critical
The success of Project Greek Island depended on trust, discretion, and alignment between government and private enterprise principles that remain fundamental in today’s contracting ecosystem.
C. Dual-Use Infrastructure Maximizes Value
Combining civilian and government functions within shared infrastructure enhances efficiency, flexibility, and strategic resilience.
D. Preparedness Requires Investment
The bunker was never used, yet it justified its existence through readiness. Similarly, modern resilience investments particularly in cybersecurity and redundancy must be viewed as essential, not optional.
While the Cold War threat model centered on nuclear conflict, today’s risks are broader and more complex:
Nuclear attack Cyber warfare
Centralized government risk Distributed infrastructure risk
Physical destruction Data and systems disruption
Isolated secrecy Networked vulnerability
Government contractors are now on the front lines of addressing these challenges through:
• Cybersecurity and zero-trust frameworks
• Cloud-based continuity solutions
• AI-enabled threat detection
• Critical infrastructure resilience
The mission has evolved, but the objective remains the same: ensure continuity under any conditions.
The Greenbrier Bunker is more than a historical artifact it is a strategic case study in resilience, foresight, and collaboration.
Its legacy demonstrates that:
• Continuity planning is indispensable
• Public-private partnerships are powerful
• Infrastructure must be adaptable and secure
For the Professional Services Council community, the takeaway is clear:
The future of government resilience will depend not only on federal agencies, but on the innovation, reliability, and partnership of the private sector.

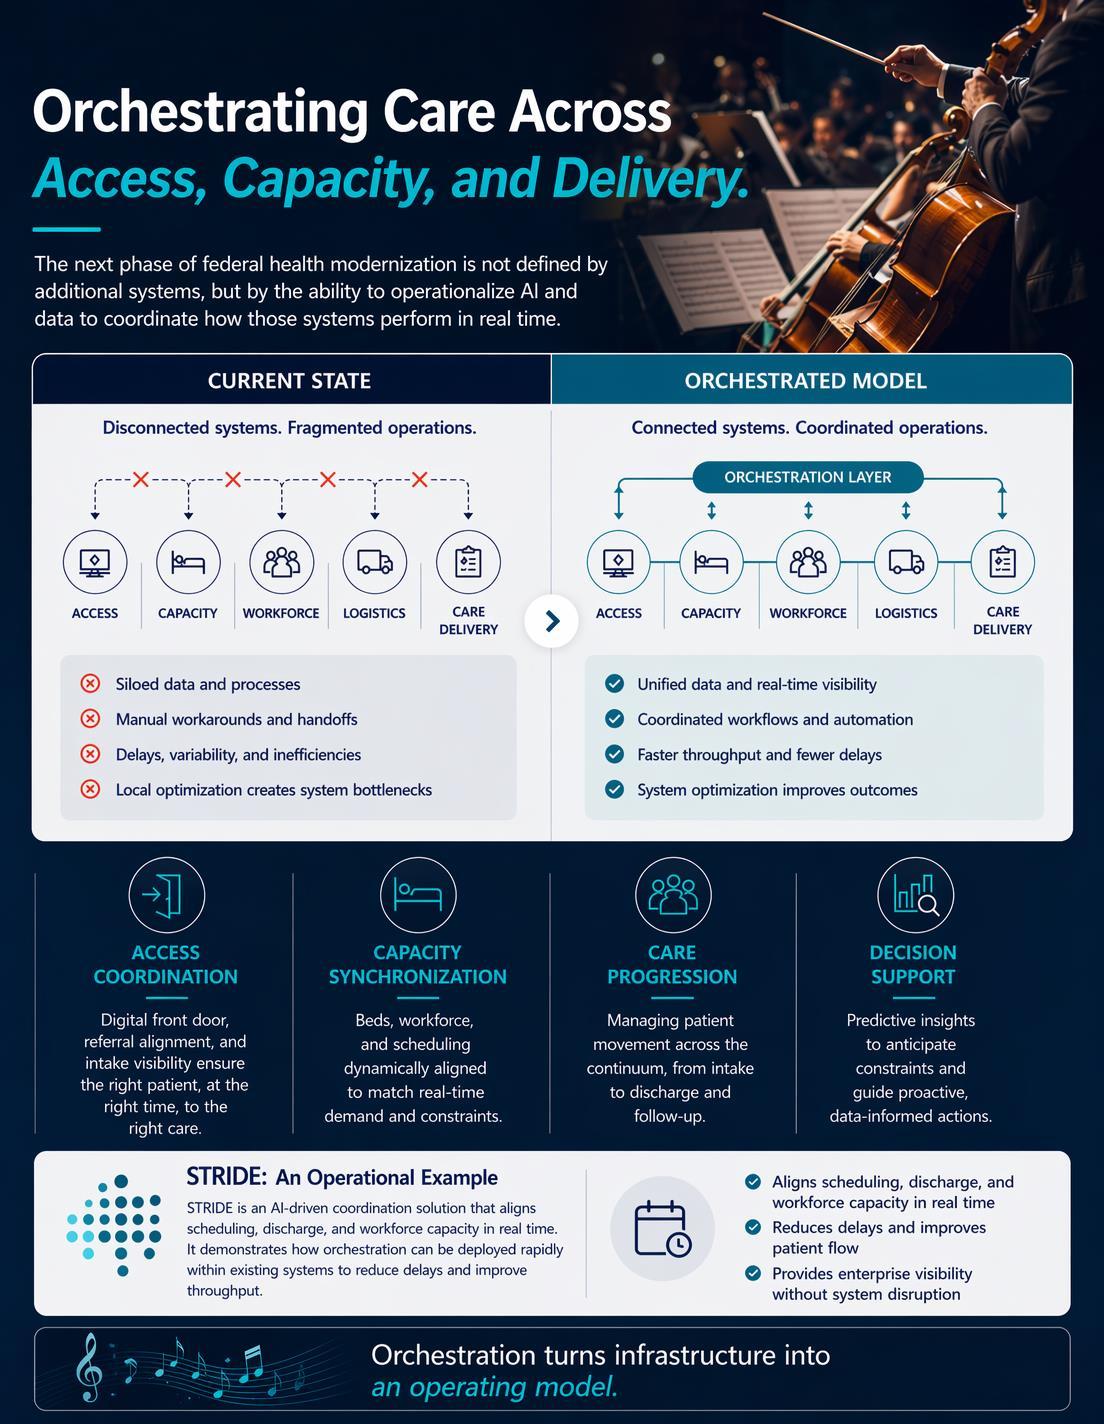
Healthcare is generating more data than ever—and the analytics market is projected to grow from $44.8 billion in 2024 to $133.2 billion by 2029, driven by advances in predictive modeling and personalized care tools.
But as data volumes surge, hospitals, healthcare providers, and public health agencies face a more urgent challenge: the ability to securely exchange information in real time. Rapid, reliable data sharing is essential for managing emergencies and addressing major threats like heart disease, cancer, substance use, and suicide.
The federal government recognized the need for interoperability in the late 2000s. Over the past 10+ years, Congress has passed laws and the Centers for Medicare and Medicaid Services (CMS) has introduced rules to push American healthcare organizations to modernize their data operations, including:
• The 21st Century Cures Act (2016) mandated the development of the Trusted Exchange Framework and Common Agreement (TEFCA) to enable network-tonetwork health information exchange and required certified health IT to support standardized APIs.
• The CMS’s Meaningful Use standards established specific criteria for EHR use to improve care quality, which later evolved into the Promoting Interoperability Program in 2018.
• The CMS Interoperability and Patient Access Final Rule (2020) requires Medicare Advantage, Medicaid, Children’s Health Insurance Program (CHIP), and Qualified Health Plan (QHP) issuers to implement APIs for patient access to health data.
• The CMS Advancing Interoperability and Improving Prior Authorization Processes Final Rule requires payers to establish APIs to share patient health information.
In each of these cases, the government has endorsed FHIR® (Fast Healthcare Interoperability Resources) developed by HL7® (Health Level Seven®), to facilitate the move toward interoperability.
FHIR®, developed in 2012, is a set of best practices and open standards developed by a global community to make data sharing more flexible and effective. Earlier data standards (V2, V3, and CDA) exist, but FHIR® delivered several advantages, including:
• The use of concepts familiar to software engineers, reducing the learning curve.
• Implementation guides for agencies and organizations.
• Enabling the creation of apps, similar to how public APIs facilitated the rise of services like Uber and Airbnb.
• Standardized analytics and secure data exchange.
Federal agencies are already implementing FHIR® in their data modernization efforts, and their work is providing valuable insights for leveraging these tools.
Interoperability standards can help healthcare providers and organizations remain compliant with federal laws. To comply with federal laws, medical providers must report annual quality metrics to CMS. While there are some standards for data exchange, reporting is complicated by differences in EHR systems.
FHIR® APIs allow standardized queries to gather quality-of-care data and generate reports. For example, a CMS quality measure for diabetes requires a yearly eye exam for each patient. FHIR® can query provider EHRs for relevant procedure codes, streamlining the reporting process.
Recent health crises also underscored the importance of interoperability in responding to emergencies. In 2020, public health agencies at all levels scrambled to obtain data from hospitals overwhelmed by patients. In the absence of centralized guidelines, hospitals developed their own approaches, which introduced variability and complexity into the response process.
The Helios FHIR® accelerator project aims to solve these issues by simplifying data sharing between hospitals and public health agencies. ICF is investigating how FHIR® APIs can be integrated into existing EHR systems to standardize tracking of aggregate data, such as ICU beds, ventilators, and personal protective equipment, enabling agencies to quickly access real-time data.
Agencies and developers can take these steps to accelerate FHIR® implementation:
• Use the HL7 registry: This centralized resource provides access to implementation guides, specifications, and reference materials developed by HL7 work groups and partner agencies.
• Consult open-source products: Tools like HAPI FHIR® enable rapid setup of compliant implementations and can serve as a reference for future deployments.
• Participate in HL7 Connectathons: These hands-on events provide a forum for organizations to engage with the FHIR® community and test new implementations alongside peers.
• Host a FHIR® hackathon: These innovation-focused gatherings unite technologists, clinicians, and policymakers to co-create practical solutions that enhance data sharing and interoperability.
Interoperability’s importance will only grow, not shrink, as agencies and healthcare organizations implement and scale their AI applications in the coming months and years. Agencies must leverage FHIR® now to ensure they’re primed to get the most from their AI investments. To see how these principles are being put into practice, explore how we support CMS in advancing eCQM standards and data harmonization.


ICF is a leading global solutions and technology provider with approximately 9,000 employees. At ICF, business analysts and policy specialists work together with digital strategists, data scientists and creatives. We combine unmatched industry expertise with cutting-edge engagement capabilities to help organizations solve their most complex challenges. Since 1969, public and private sector clients have worked with ICF to navigate change and shape the future.

In one sentence: the same methods used to keep satellites, bases, and critical infrastructure operating can and increasingly must be applied to the labs, hospitals, and biomanufacturing facilities that underpin infectious disease and biosurveillance work.

Infectious disease response no longer depends solely on pathogens, hosts, and “environment” as traditionally understood in clinical and public health practice. It now also depends on national laboratory networks, interconnected clinical and public health information systems, highly instrumented facilities, and global supply chains. The COVID-19 pandemic revealed that the U.S. laboratory system is not optimized for fast-moving pathogens, often failing due to "errors in design and execution" rather than biological limits (Health Affairs, 2023). When any part of that system fails, the consequences for detection, treatment, and control can parallel the consequences of a failed high-consequence defense mission.

Biology now runs on digital infrastructure: as genomic data, networked instruments, and automated facilities converge, cybersecurity, integrity, and resilience become central to mission critical biosurveillance.
Federal policy has evolved to recognize infectious disease threats and the central role of biosurveillance in national resilience. The National Biodefense Strategy and Implementation Plan (2022) shaped by the National Blueprint for Biodefense (2024) and bolstered by federal bioeconomy initiatives and execution plans from the Department of Health and Human Services, the Department of War, and the Department of Veterans Affairs positions preparedness and biosurveillance as core strategic capabilities for the nation.
A consistent theme across these policies is that effectiveness depends on coordination across clinical care, laboratories, public health, biosurveillance agencies and their subordinate entities, and security partners to enable faster detection, clearer situational awareness, and more timely, targeted interventions during routine operations and crises.
Two additional shifts are also reshaping this operating environment. First, the expansion of telemedicine and home-based care changes how signals enter public health systems, increasing the risk for decentralized data silos. Unless integration pathways such as patient identity matching and results routing are explicitly designed and governed, the shift to home care threatens the completeness of laboratory-confirmed reporting necessary for a national operational picture (Hospital Reporting Barriers; PMC7313984). Second, biosurveillance is an ecosystem that includes entities such as the National Biosurveillance Integration Center (NBIC), the National Center for Medical Intelligence (NCMI), and federal partners with animal, food, and agricultural surveillance responsibilities (for example, the U.S. Department of Agriculture (USDA)). Treating biosurveillance as a mission system, therefore, requires explicitly mapping roles and interfaces across the ecosystem.
To effectively bridge the gap between engineering and biology, this mapping should be governed by the principles of systems engineering and integration (SE&I), the same discipline used to manage complex interdependencies in satellite and defense programs. By adopting an SE&I approach, the operational picture moves beyond simple data sharing to a resilient architecture that fuses, validates, and shares signals across jurisdictions and sectors.
To support these goals, regulatory and standards-setting bodies establish expectations that critical systems produce results that are accurate, secure, and defensible. National Institute of Standards and Technology (NIST) emphasizes the confidentiality, integrity, and availability of systems and sensitive data. The Clinical Laboratory Improvement Amendments (CLIA) established quality standards for laboratory testing to ensure accuracy and reliability. Oversight from USDA addresses the safety and effectiveness of medical products, associated controls, and quality systems. Guidance from the Centers for Disease Control and Prevention (CDC) shapes biosurveillance practice and public health operations. Collectively, these frameworks converge on a practical requirement: decision makers must be able to rely on data and demonstrate through audit ready evidence how it was generated, protected, transmitted, and used.
Aligning daily practice with those expectations, particularly in environments constrained by legacy systems, workforce capacity, and fragmented governance, remains a challenge. Closing this gap is less about additional bureaucracy and more about focusing modernization and coordination on areas that measurably improve time to actionable information, continuity of operations, and demonstrable compliance especially across jurisdictions and populations where consistency and equity are hardest to achieve.
Recent public health emergencies have underscored the need for interconnected support systems to translate scientific insights and clinical data into practical, effective responses. COVID-19 highlighted the impact of manufacturing and logistics issues on the execution of an effective response.
In multi-state respiratory surveillance efforts, a disproportionate share of late reports can often be traced back to a small number of fragile interfaces, such as a single laboratory information system connection serving multiple Electronic Health Records (EHR) or public health reporting feeds. Statistical modeling of notification timelines identifies these bottlenecks as critical "notification delays" (D3 delays) that stall public health action (Timeliness of Notification Systems; PMC6002046). In these situations, epidemiologic methods and assays may be sound, but a single technical dependency becomes the bottleneck. The science is ready. The system is not. The result is delayed interventions and reduced ability to halt transmission chains.
Similar fragility is evident in the physical environment.
Public health laboratories that rapidly scale highthroughput molecular testing during a surge may find that instruments and assays perform as expected, while legacy building systems struggle to maintain stable temperature, humidity, pressurization, and airflow needed for reliable operations. When those engineering controls drift, triggering alarms, requiring corrective actions, or forcing temporary pauses to restore conditions, throughput can drop below planned capacity. This is consistent with long-standing biosafety guidance that treats ventilation and other engineering controls as foundational requirements rather than optional infrastructure enhancements (CDC/NIH BMBL 6th Edition; WHO Laboratory Biosafety Manual).
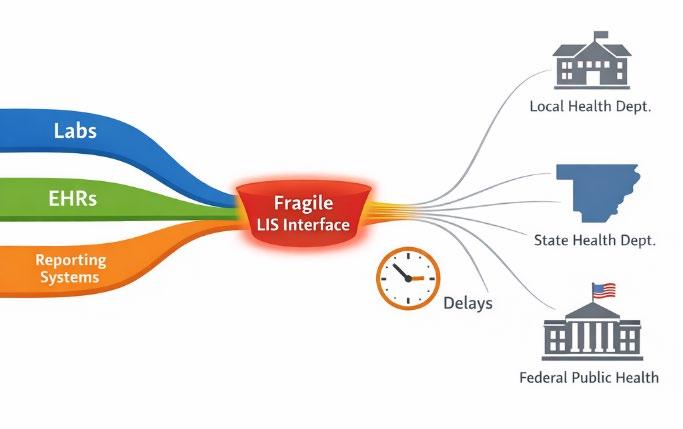
When many laboratories and EHRs depend on one fragile connection, that bottleneck not the assay defines how quickly actionable information reaches public health.

These facility “engineering controls” function as interdependent services rather than isolated components. Small disruptions can cascade. Loss of clean water can impair steam generation, disabling autoclaves and halting sterilization and waste decontamination. Similar cascades occur when heating, ventilation, and air conditioning (HVAC) instability undermines pressure relationships or air-change performance, triggering alarms, corrective actions, and temporary work stoppages until conditions are restored and documented.
For this reason, redundancy must be evaluated at the system level. “N+1” capacity in a single asset does not ensure continuity if upstream dependencies remain single points of failure. A practical mitigation is to map and test the minimum set of interrelated systems required for sustained operations. Beyond basic mapping, leveraging operational digital twins allows facilities to model how failures in HVAC or supply chains affect throughput and to prioritize investments that keep dependencies within acceptable bounds under surge conditions (Digital Twin Manifesto for Pathology; PMC12273362).
To remain defensible and audit-ready, engineering-control examples should be grounded in common, observable failure modes and documented facility evidence (alarm histories, trend logs, and maintenance records). Common cases include water supply disruptions affecting steam and autoclaves; pressure drift caused by control instability or sensor faults; and variable frequency drive failures that reduce airflow and compromise environmental conditions.
As part of the mission dependency map, programs should explicitly enumerate the interrelated systems required to sustain operations for example, power, water, steam, HVAC and pressure monitoring, sterilization, cold chain, waste handling, network connectivity, the LIS or laboratory information management system (LIMS), and key staffing and supply dependencies and document which are single points of failure versus redundant. The output should not only be a diagram but a countable inventory of dependencies with owners, monitoring signals, and recovery time objectives for each.
Once biology becomes part of complex technical and organizational systems, performance relies on how the entire system is designed and operated, rather than isolated capabilities. While stable facility conditions
enable testing, the value of biosurveillance depends on whether results move quickly and correctly through reporting systems. Facility resilience ensures production of results; data-path resilience ensures those results lead to timely, effective action.
Performance also depends on the scale of the event. Describing performance requirements in tiers baseline operations, outbreak surge, pandemic-scale surge, and exotic or high-consequence response helps identify which constraints are clarifies which constraints are technical versus policy driven and defines what “degraded but safe operations” should look like at each tier. This tiering should drive concrete artifacts such as surge staffing triggers, minimum on-hand inventory for critical consumables, alternate validated workflows, and predefined data-routing priorities so that completeness and timeliness degrade in controlled, transparent ways rather than failing unpredictably.
In high-consequence environments, “mission-critical” implies three core practices:
• The mission is defined in operational terms: what must be delivered, to whom, how quickly, and under what constraints.
• People, processes, facilities, technology, and data are treated as a connected system rather than as isolated projects.
• Disruptions are expected, and the system is designed to continue delivering essential functions, even in degraded conditions this is the core of mission assurance.
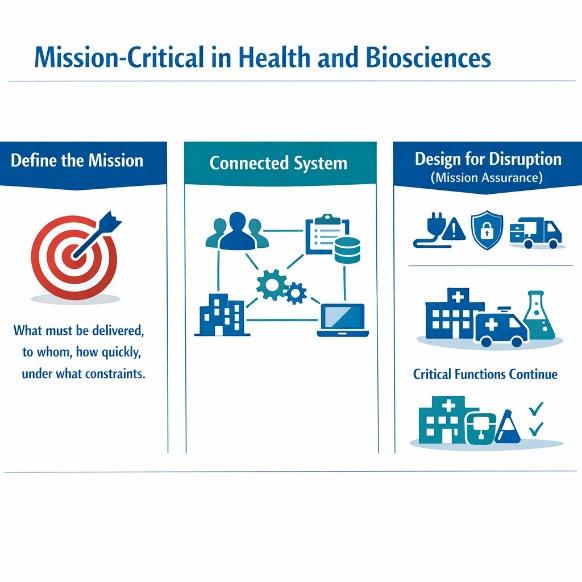

Mission-critical in health and biosciences means defining the mission in operational terms, treating people, processes, facilities, technology, and data as one connected system, and designing that system to keep essential functions running even under disruption.
When applied to health and biosciences, this approach focuses more on defining and governing integration pathways than on adopting new buzzwords. A federal mission oriented laboratory description might specify the ability to detect and confirm defined pathogens with stated performance metrics under conditions of power instability, staffing shortages, and supply disruptions. This framing makes explicit that instruments, staff, facility systems, informatics, procurement, and governance are mission-critical. If any of them fail in the wrong way at the wrong time, the mission does not hold.
Experience from lab and critical infrastructure modernization efforts shows that systematic mapping of dependencies often uncovers single points of failure and where limited resources will have the greatest impact. Done well, it simplifies decision-making by focusing attention on what truly supports the mission.
The convergence of biological and digital technologies has created new risk surfaces and corresponding expectations for assurance. Modern surveillance depends on networked instruments, cloud based analytics, and automated building controls, all of which affect data trustworthiness and operational continuity.
Treating the data path from instrument to LIS, EHR, and jurisdictional reporting as mission critical implies documenting and governing it with sufficient rigor to support resilience, compliance, and auditability. When results can be traced step by step, errors are easier to detect, incidents easier to manage, and transparency to regulators and the public easier to maintain.
Artificial intelligence (AI) and machine learning (ML) can strengthen infectious disease and biosurveillance missions only when treated as part of the system, not as a stand-alone capability. In the near term, the most mission-relevant applications are pragmatic and operational: anomaly detection in surveillance data streams, forecasting and nowcasting to support resource allocation, and automated triage of data quality issues before they propagate into downstream reporting.
In laboratory and biomanufacturing environments, these methods can also support predictive maintenance and process monitoring identifying instrument drift, abnormal run characteristics, or facility-condition trends that precede failures and interruptions.
However, AI also introduces risks that high-consequence missions cannot ignore. Model outputs are sensitive to data quality, representativeness, and changes in clinical practice or testing patterns. Poorly governed models can amplify reporting biases, reduce transparency, and create false confidence. For this reason, automation should prioritize speed while retaining human verification for consequential decisions. Models should be documented, validated, monitored for drift, and designed to fail safely like any other mission critical component.
A mission-oriented systems approach has several concrete implications for health and bioscience leaders.
1. First, capabilities should be defined in terms of operational outcomes, not technologies. Instead of “implement a new surveillance platform,” a program might define its objective as “ensure that every positive test for specified pathogens in this region is available to clinicians and public health authorities within a defined timeframe, with a defined level of completeness, even under specified stress conditions.” This type of outcome definition reveals cross-cutting dependencies involving laboratories, clinical services, IT, facilities, and governance, and aligns naturally with expectations in the National Biodefense Strategy and bioeconomy initiatives.
2. At least one critical end to end pathway is explicitly owned, monitored, and governed, so that fragile interfaces, manual workarounds, and single points of failure become visible and correctable.
3. Disruption is treated as a design condition, not an exception. Designs that reflect this reality explicitly define which functions must continue under all circumstances, where controlled degradation is acceptable, and what “degraded but safe operations” looks like
4. Workforce and change-management constraints must be built into planning to avoid adding burden during crises Systems approaches are most effective when they concentrate change on the highestvalue needs and reduce reliance on repeated emergency measures and ad hoc manual processes, rather than adding new reporting burdens.
5. Scalability is treated as a design attribute. The same principles that improve reliability and transparency in a single lab or hospital can be applied to regional networks, national surveillance systems, and bioindustrial supply chains.
A practical starting point is a time-boxed systems-risk review of one critical process, treated as a “starter mission thread” assessment. Programs can define the mission outcome, map the full clinical to reporting pathway, and produce decision ready outputs: single points of failure, named owners, monitoring signals, and one or two targeted improvements that materially reduce risk
Even at a modest scale, this approach improves transparency, supports oversight by CLIA, FDA, and CDC, and strengthens communication with clinicians, partners, and the public.
Conclusion: Matching Systems to Stakes
Health and bioscience capabilities sit at the intersection of public health, national security, and economic competitiveness. While infectious disease and biosurveillance work are mission-critical, the remaining gap lies in ensuring they are consistently prioritized in system design, governance, and readiness sustainment.
Adopting mission-oriented systems practices does not mean turning every program into a heavyweight engineering project. Instead, it emphasizes lightweight, practical methods that fit existing operations to reduce surprises, focus investment, improve compliance and auditability, and support more equitable, reliable responses across regions and populations. The proposition is straightforward: systems should be designed and operated in a way that matches the stakes of the missions they support. In the era of converging biological and digital threats, that alignment is no longer optional.


Why Post-Market Safety Monitoring Needs a Broader, More Real-Time Approach
Dr. Anthony Cristillo, PhD, MS, MBA Senior Vice President, Federal Health Revolutional
Pharmacovigilance plays a critical role in ensuring the long-term safety of drugs, biologics, and medical devices by detecting rare, delayed, or population-specific adverse events that often do not appear during clinical trials. As pressure grows to bring life-saving treatments to patients faster, post-market surveillance is becoming even more important.
The FDA has taken steps to accelerate approvals by streamlining certain regulatory processes and reducing some pre-market requirements. These efforts are designed to shorten development and review timelines, but they also shift more responsibility to real-world monitoring after products enter the market. That raises an important question: Are today’s pharmacovigilance systems equipped to detect safety signals early enough?
For decades, safety monitoring has relied heavily on passive adverse event reporting from patients receiving drugs, biologics including vaccines, and treatments involving medical devices. More recently, organizations have also looked to other established data sources such as claims data, electronic health records, clinical notes, and registry data.
These traditional sources remain necessary. They help identify low-frequency safety events and support informed action on recalls, warnings, and other safety decisions. But they are also often lagging, incomplete, and reactive. Many pharmacovigilance frameworks still depend on spontaneous reporting systems, manual case processing, and rule-based statistical methods that can struggle to keep pace with the volume, speed, and variety of safety-related data generated across today’s healthcare landscape.
The result is a system that can be slow to detect weak or emerging signals and limited in its ability to draw insight from less structured data.
If the goal is earlier detection, more informed action, and better injury prevention, incremental improvements to traditional data sources alone may not be enough. Pharmacovigilance may need to expand its field of view.
One approach is to incorporate non-traditional proxies of adverse events — signals that may emerge before a formal report is filed or a pattern is visible in traditional systems. These sources could include:
• Consumer behavior patterns, such as sudden discontinuation, switching, or substitution of over-the-counter products
• Care-seeking signals, such as urgent care visits, telehealth spikes, or pharmacy consultations
• Acuity indicators, such as changes in utilization intensity, diagnostic escalation, or symptom clustering
• Digital signals from patient journeys, such as search behavior, wearable data, and engagement patterns
Individually, these inputs may seem noisy. Collectively, they may offer earlier directional insight into emerging safety issues.
This is not about replacing traditional pharmacovigilance. It is about augmenting existing systems with more forward-looking signals that can support earlier hypothesis generation, faster signal triage, and more proactive risk mitigation.
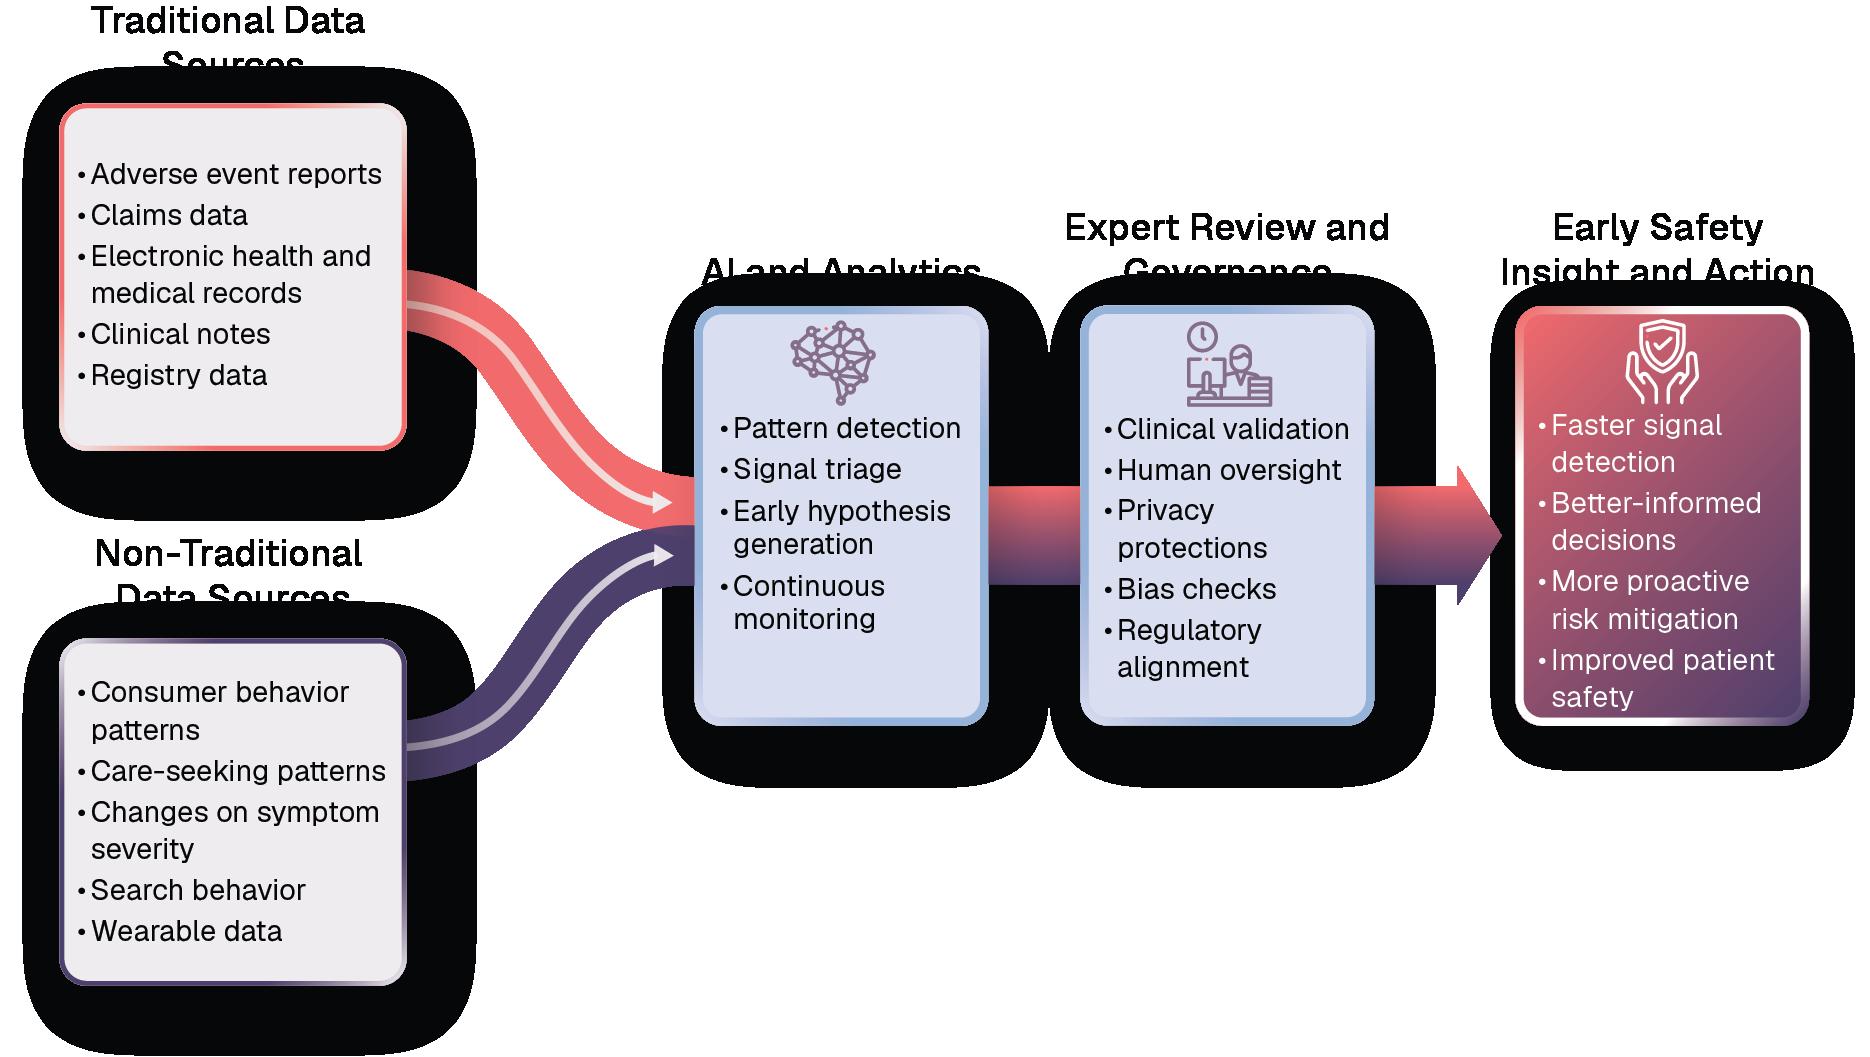
AI can accelerate insight but expert judgment, trust, and governance still lead
The challenge, of course, is that these data sources are large, messy, fast-moving, and often difficult to interpret. That is where AI and advanced analytics may play an important role.
Machine learning, deep learning, and natural language processing can help automate the ingestion and analysis of large, heterogeneous datasets, improve pattern recognition, and support learning from continuously evolving data streams. Used well, these tools may help surface weak or emerging patterns that warrant closer human review.
But AI does not eliminate the underlying challenges. It introduces its own concerns around data quality, representativeness, bias, transparency, interpretability, and generalizability across populations and therapeutic areas. It also does not eliminate the need for expert

oversight. A more modern pharmacovigilance model still requires subject matter experts to validate signals, assess relevance, and ensure clinical and regulatory rigor.
A more real-time, signal-driven approach to pharmacovigilance cannot succeed on technical capability alone. It also has to be trusted.
That means agencies and their partners need to think carefully about privacy, governance, validation, and responsible use, especially when discussing less traditional indicators such as search behavior, wearable data, or other signals outside formal clinical systems. The goal is not broader surveillance for its own sake. The goal is to identify patterns earlier, validate them responsibly, and improve public health action while maintaining transparency and trust.
A more proactive, signal-driven pharmacovigilance ecosystem will require coordinated action across federal agencies, industry sponsors, and health technology partners, with each bringing a distinct but complementary role.
Federal agencies can lead by establishing clear regulatory frameworks for how non-traditional data sources and AI-driven methodologies may be incorporated into pharmacovigilance. That includes setting standards for data quality, validation, and auditability; issuing guidance on the acceptable use of real-world and proxy data; and investing in modern infrastructure that enables secure, scalable data integration. Agencies will also need to evolve from retrospective signal evaluation toward more continuous, near real-time surveillance while maintaining oversight, transparency, and public trust.
Industry partners, including pharmaceutical, biotech, and device manufacturers, play a critical role in operationalizing these advancements across the product lifecycle. They are well positioned to integrate diverse data streams from development through post-market monitoring, test emerging approaches to early signal detection, and work with regulators to validate new methodologies. Their role is not only to innovate, but to ensure that expanded use of data and analytics remains grounded in scientific rigor, patient safety, and real-world applicability.
Health technology firms can help bridge the gap between fragmented data and actionable insight. With expertise in health, data engineering, AI and machine learning, and scalable analytics platforms, these organizations can support agencies and sponsors by designing systems that ingest complex, high-velocity data, surface weak or emerging signals, and present findings in ways that support clinical, operational, and regulatory decision-making. They can also help build the technical and governance frameworks needed to make these approaches more usable, transparent, and scalable in practice.
For federal health leaders, the opportunity is not simply to collect more data. It is to build a more practical and responsible framework for identifying, validating, and acting on the signals that matter most.
The most effective way to begin is with three practical steps that strengthen signal detection, oversight, and action.
• Set standards for AI and new data sources by defining clear guidance on data quality, validation, bias, and transparency so organizations can adopt AI and non-traditional signals with confidence and rigor.
• Build real-time, interoperable infrastructure by investing in modern platforms that integrate diverse data streams and enable continuous, near real-time safety monitoring across stakeholders.
• Launch focused pilots and scale what works by testing signal-driven approaches in high-impact areas with industry partners, then expanding proven models with built-in governance and clinical validation.
Revolutional enables agencies to modernize, defend critical systems, and deliver results without slowing down the mission. Working at the intersection of innovation and mission, we transform possibility into progress
We combine the capability, expertise, and resources of a large business with the entrepreneurial spirit and employee empowerment necessary to provide meaningful emerging technology at the speed agencies need.
Learn more at revolutional.com © RevolutionalTM All rights reserved.


20%
increase in answer rates
35%
decrease in call attempts
The phone is a critical communication channel to enable trusted constituent experiences. Research shows close to 80% of consumers prefer the phone channel when communicating with enterprises.1 However, 80% also block calls if they don’t know who’s calling.2
In fact, Veterans served by the U.S. Department of Veterans Affairs (VA) were missing important calls about their benefits due to: inaccurate spam tagging, call blocking, mislabeling or labeling as “unknown caller,” and suspected fraud on millions of outbound calls annually.
These missed connections led to degraded Veteran experiences, and increased call volumes and costs for the VA. The overall impact was less effective benefit utilization and care delivery.
The VA needed to quickly connect with more Veterans to enable timely access to well-deserved benefits and services.
The government agency worked with TransUnion® to implement a multi-faceted approach to improving outbound phone response using TransUnion Trusted Call Solutions
TransUnion began by auditing the VA’s outbound communications to gain a robust understanding of its phone system — including number registration needs, call volume, spam tagging challenges and inconsistencies in caller name.
As TransUnion helped to designate verified VA numbers consistently — regardless of whether constituents use a landline or mobile device — the agency reached devices across the phone channel more effectively. The approach further used TransUnion Caller Name Optimization (CNO) to mitigate and alert on spam tagging, as well as correctly label caller ID to landlines. Branded Call Display (BCD) was also used to help brand outbound calls to mobile devices with the VA’s name and phone number.
Using CNO, TransUnion also monitored the VA’s calling reputation on outbound dials, swiftly providing alerts about unusual activity and helping remediate suspicious use of registered numbers or new spam tag activity.
With the implementation of BCD and CNO, the VA reached more Veterans in moments that mattered.
In the first six months after implementation, the VA saw improved outbound phone response performance. Mitigating spam tagging on 13% of total call volume (almost 7 million outbound calls), the agency increased answer rates. Operational efficiency improved as the overall number of outbound calls decreased by roughly 35% in one program alone.
The VA noted increases in contact rate across programs — averaging a 20% lift in answered calls. Veterans were willing to answer the phone when they trusted who was calling. Even patients with no previous successful contact attempts were reached about important care alerts.
In addition to reaching more Veterans faster, the VA noted call recipients stayed engaged in phone conversations longer, reinforcing the value of the channel to register beneficiaries and deliver patient care.
With the success of Trusted Call Solutions, the VA expanded BCD and CNO to support additional service programs.

