Broadening the Treatment Horizon for Heart Failure Patients
Regenerative Medicine: Confusion or Complacency?
The Surge of Digital Health Technologies
Modernising Clinical Research
Challenges of Drug Development in Drug Resistant Focal Epilepsy
Clinical Research Solutions
Health Inspired, Quality Driven.
SGS provides clinical research and bioanalytical testing, with a focus on early stage development and biometrics.
Delivering solutions in Europe and North America, SGS offers clinical trial services. SGS has its own clinical unit in Belgium including a viral challenge testing facility and two phase I patient units based in Belgium and Hungary. SGS has a wealth of expertise in FIH studies, viral challenge testing, biosimilars and complex PK/PD studies with a high therapeutic focus in Infectious Diseases, Vaccines, and Respiratory. We offer a variety of tests that are bespoke, client-specific and support the full clinical development, from Phase I
Journal by Clinical Studies – ISSN 1758-5678 is published bi-monthly by Senglobal Ltd.
4 FOREWORD
WATCH PAGES
6 An Alternative Approach to Continued COVID-19 Research
COVID-19 has dominated our lives for two years now. Although we are returning to a new normal, with the help of rapidly developed vaccines, do we truly understand the virus? Why does it affect one patient more than another? Why do some patients deteriorate rapidly, while other slowly recover? COSMIC-19 is aiming to answer these questions using AI (Artificial Intelligence) and wearable technologies. Paul Blaney at Aptus Clinical, clarifies an alternative approach to continued COVID-19 research.
8 Broadening the Treatment Horizon for Heart Failure Patients
Through its issuance of recommendations and regulatory decisions concerning medical products, the US Food and Drug Administration (FDA) typically considers the “unmet medical need” surrounding a particular disease or condition. In the most extreme circumstances, as with many rare diseases, FDA-approved therapies may not be available. There are also numerous contexts, however, in which treatments are approved, but a need still exists for refinement to better target the patient population – such is the case for heart failure (HF) drugs. Deborah Komlos at Clarivate, explains more about treatment horizon for heart failure patients.
10 Rapid Rise of Decentralised Clinical Trials
As the world continues to adapt to the impact of the pandemic, a legacy has seen the evolvement of varying approaches to how clinical trials are designed and deployed. There has been a rapid rise of decentralised clinical trials (DCT) which brings benefits and poses potential challenges in equal measure. Lee Stopher at Peli BioThermal, analysis the rapid rise of decentralised clinical trials.
12 International Clinical Trials Day – R&D Experts Weigh in on What the Future Holds
Each year, on 20th May, the global health community celebrates International Clinical Trials Day, the anniversary of James Lind’s famous scurvy experiment in 1747 on H.M.S. Salisbury. Lind’s discovery – that sufferer of the disease recovered faster if they included citrus fruits in their diet – is considered one of the earliest examples of a successful controlled clinical trial. Craig Johnston at Automata and Richard Young at Vault CDMS show how important it is that the industry continues to strive for improvements in the trial process, looking to the future at how we can continue to innovate and adapt to improve trial outcomes for all involved.
REGULATORY
The opinions and views expressed by the authors in this magazine are not neccessarily those of the Editor or the Publisher. Please note that athough care is taken in preparaion of this publication, the Editor and the Publisher are not responsible for opinions, views and inccuracies in the articles. Great care is taken with regards to artwork supplied the Publisher cannot be held responsible for any less or damaged incurred. This publication is protected by copyright.
Volume 14 Issue 3 May 2022
Senglobal Ltd.
www.journalforclinicalstudies.com
14
Calculating
Sample Size for Medical Device Studies
Sample size has always been one of the first design choices a medical device sponsor has to make for a clinical study. But the calculation of sample size is not the most straightforward process and often leaves clinical teams wondering which method to use. What is the appropriate sample size for my medical device study/survey? How can I provide justification for sample size in medical device study? Can I use a sample size calculator for my clinical trial? These are the most common questions regarding sample size for medical device studies that Jón Ingi Bergsteinsson at SMART-TRIAL will try to answer in this article.
16 Get your Ducks in a Row for the Data-driven Future
Stakeholders across the life sciences industry now understand that data is more important than documents but also that it’s crucial that the data is reliable and can be trusted as a definitive source of truth. Agnes Cwienczek at Amplexor, sets out the steps that life sciences organisations must now take to get their data in order.
18 The Relevance of the Guidelines on Good Distribution Practice (GDP) in the world of International Clinical Trials
The successful execution of international clinical trials requires the involvement of service providers adhering to a wide range of regulatory guidelines and industry standards including the Good Clinical Practice (GCP), the Good Manufacturing Practice (GMP) or the Good Laboratory Practice (GLP). Companies following the guidelines of Good Distribution Practice (GDP) are also involved in ensuring that the logistics and quality assurance requirements of the products used in clinical trials are duly met. Tibor KOVÁCS at PHARMAROAD KFT.
aspires to highlight the different aspects of Good Distribution Practice (GDP) that are relevant to the sector of clinical trial management.
THERAPEUTICS
22 Regenerative Medicine: Confusion or Complacency?
The subject of Regenerative Medicine is currently at an inflexion point. There has been an enormous amount of financial investment, along with basic and clinical research, but despite these efforts there is only one tried and tested use of stem cells and that is bone marrow transplantation (using haemopoietic stem cells) which was first developed in 1957. The rest of Regenerative Medicine is currently confused with the identification of multiple stem cell types, many clinical trials but no real progress to a safe and effective routine stem cell-based procedure for any disease. Professor Peter Hollands will try to clarify if there is confusion or complacency around regenerative medicine.
24 Challenges of Drug Development in Drug Resistant Focal Epilepsy
Epilepsy is one of the most common and disabling chronic neurologic disorder that affects more than 50 million people worldwide. Despite current of over two dozen antiepileptic drugs (AEDs), about one third of people with epilepsy fail to achieve complete freedom from seizures with existing medications employed alone or in various combinations. This phenomenon is known as a Drug Resistant Epilepsy (DRE) and represents a major challenge in epilepsy treatment. Tomislav Babić at Worldwide Clinical Trials Inc. explains the challenges of drug development in drug resistant focal epilepsy.
28 Transcriptome Analysis of Acute Myeloid Leukaemia Cells
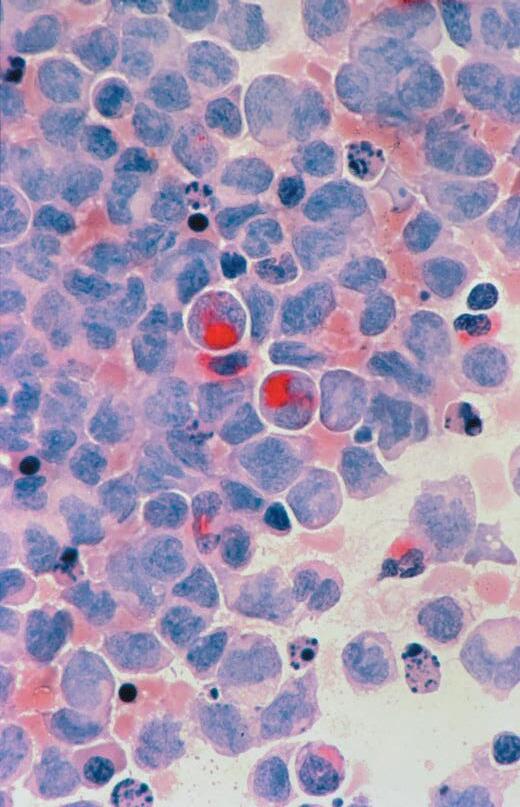
Acute Myeloid Leukaemia (AML) is a blood cancer characterised by overproduction of immature white blood cells in the bone marrow. These proliferating immature cells cause disease by swamping the production of normal blood cells. Christine Evans-Pughe is a freelance science and technology writer, talks more about transcriptome analysis of acute myeloid leukaemia cells.
TECHNOLOGY
30 The Surge of Digital Health Technologies Modernising Clinical Research
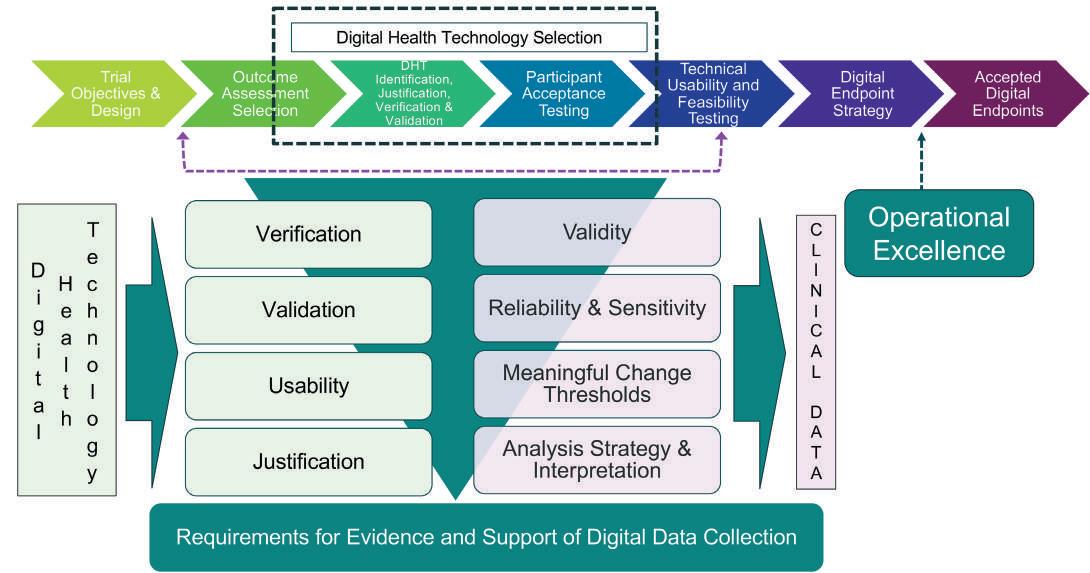
Using digital health technologies (DHTs) to generate digital endpoints adds significant value to the clinical trial process in several areas. Critical to success is ensuring that the right digital health transformation strategies are being implemented to really reap the benefits of the technologies now available. Isaac R. Rodriguez-Chavez at ICON plc. outlines the key considerations when developing these strategies.
APPLICATION NOTE
34 How to Hire a Translation Agency
Choosing the right medical translation provider can help inhouse regulatory and clinical departments and contract research organisations support strategic growth while controlling costs and minimising risk. In this practical guide to hiring a translation agency, DWL, A BIG Language Solutions Company discusses eight key steps to take when choosing a vendor, ranging from assessing domain knowledge to managing liability and security.
www.pci.com
talkfuture@pci.com
Heart Failure (HF) is a chronic, long-term cardiac condition that, over time, worsens and is exacerbated with no or inappropriate treatments. The American College of Cardiology (ACC) and the American Heart Association (AHA) define Heart Failure as “a complex clinical syndrome that results from any structural or functional impairment of ventricular filling or ejection of blood.” As the condition worsens, the heart muscle pumps less blood to organs, precluding them from receiving the oxygen and nutrients they need to thrive. Over time, the quality of life of patients with HF deteriorates inexorably.
Heart failure is a degenerative disease leading to poor quality of life, frequent, costly hospitalisations, and early mortality. Severe heart failure requires device-based therapy to enhance the left ventricle’s pumping capacity. Several new devices are being added to the clinical arsenal to fight against the disease, and advances in implantable HF technologies offer new approaches to treat heart failure more effectively.
Through its issuance of recommendations and regulatory decisions concerning medical products, the US Food and Drug Administration (FDA) typically considers the “unmet medical need” surrounding a particular disease or condition. In the most extreme circumstances, as with many rare diseases, FDA-approved therapies may not be available. There are also numerous contexts, however, in which treatments are approved, but a need still exists for refinement to better target the patient population – such is the case for heart failure (HF) drugs. Deborah Komlos at Clarivate, explains more about the treatment horizon for heart failure patients.
The subject of Regenerative Medicine is currently at an inflexion point. There has been an enormous amount of financial investment, along with basic and clinical research, but despite these efforts, there is only one tried and tested the use of stem cells and that is bone marrow transplantation (using haemopoietic stem cells) which was first developed in 1957. The rest of Regenerative Medicine is currently confused with the identification of multiple stem cell types, many clinical trials but no real progress to a safe and effective routine stem cell-based procedure for any disease. Professor Peter Hollands will try to clarify if there is confusion or complacency around regenerative medicine.
JCS – Editorial Advisory Board
• Ashok K. Ghone, PhD, VP, Global Services MakroCare, USA
• Bakhyt Sarymsakova – Head of Department of International Cooperation, National Research Center of MCH, Astana, Kazakhstan
• Catherine Lund, Vice Chairman, OnQ Consulting
• Cellia K. Habita, President & CEO, Arianne Corporation
• Chris Tait, Life Science Account Manager, CHUBB Insurance Company of Europe
• Deborah A. Komlos, Principal Content Writer, Clarivate
• Elizabeth Moench, President and CEO of Bioclinica – Patient Recruitment & Retention
• Francis Crawley, Executive Director of the Good Clinical Practice Alliance – Europe (GCPA) and a World Health Organization (WHO) Expert in ethics
• Georg Mathis, Founder and Managing Director, Appletree AG
In this journal, we will also explore more about Epilepsy. One of the most common and disabling chronic neurologic disorders that affect more than 50 million people worldwide. Epilepsy is the tendency to have seizures that start in the brain. The brain uses electrical signals to pass messages between brain cells. If these signals are disrupted, this can lead to a seizure.
Epilepsy is usually diagnosed when someone has had more than one seizure. Seizures can affect your feelings, awareness, or movement. Despite the current of over two dozen antiepileptic drugs (AEDs), about one-third of people with epilepsy fail to achieve complete freedom from seizures with existing medications employed alone or in various combinations. This phenomenon is known as Drug-Resistant Epilepsy (DRE) and represents a major challenge in epilepsy treatment. Tomislav Babić at Worldwide Clinical Trials Inc. explains the challenges of drug development in drug-resistant focal epilepsy.
I would like to thank all our authors and contributors for making this issue an exciting one. We are working relentlessly to bring you the most exciting and relevant topics through our journals.
Beatriz Romao, Editorial Manager Journal for Clinical Studies
• Hermann Schulz, MD, Founder, PresseKontext
• Jeffrey W. Sherman, Chief Medical Officer and Senior Vice President, IDM Pharma.
• Jim James DeSantihas, Chief Executive Officer, PharmaVigilant
• Mark Goldberg, Chief Operating Officer, PAREXEL International Corporation
• Maha Al-Farhan, Chair of the GCC Chapter of the ACRP
• Rick Turner, Senior Scientific Director, Quintiles Cardiac Safety Services & Affiliate Clinical Associate Professor, University of Florida College of Pharmacy
• Robert Reekie, Snr. Executive Vice President Operations, Europe, AsiaPacific at PharmaNet Development Group
• Stanley Tam, General Manager, Eurofins MEDINET (Singapore, Shanghai)
• Stefan Astrom, Founder and CEO of Astrom Research International HB
• Steve Heath, Head of EMEA – Medidata Solutions, Inc
An Alternative Approach to Continued COVID-19 Research
COVID-19 has dominated our lives for two years now. Although we are returning to a new normal, with the help of rapidly developed vaccines, do we truly understand the virus? Why does it affect one patient more than another? Why do some patients deteriorate rapidly, while other slowly recover? COSMIC-19 is aiming to answer these questions using AI (Artificial Intelligence) and wearable technologies.
COSMIC-19 is an innovative study which has combined a range of expertise to deliver a new approach to clinical trial delivery. COSMIC-19 stands for COntinuous Signs Monitoring in Covid-19 patients. The study has been delivered by Aptus Clinical in partnership with Zenzium (AI technology), The Christie NHS Foundation Trust and in collaboration with Manchester University Foundation NHS Trust.
COSMIC-19 is unusual in that it is utilising advanced AI capabilities, to search for patterns in the patient’s data. AI allows vast amounts of data to be assessed from each individual patient and patterns proposed and reviewed.
In August 2020 we were able to announce recruitment had started. Whilst the focus was on finding a vaccine, COSMIC-19 became one of a few investigatory studies to try and learn more about the virus. The study recruited 60 patients who were suspected or confirmed COVID-19 cases.
These patients went on to have their vital signs and observations monitored using advanced wireless wearable sensors, with AI technology used to retrospectively look for and predict patterns in the patients’ vital signs. The sensor used were the Isansys LifeTouch and LifeTemp skin sensors which measure heart rate, heart rate interval, respiratory rate and body temperature. In addition, patients’ blood pressure and oxygen saturation were measured via separate devices. Alongside this sensor data, patients’ medical history, ongoing care and clinical outcome were captured and validated using an Electronic Data Capture (EDC) system. This provided additional data to enhance the AI model development.
The concept tested the potential that the medical team could be proactively alerted if the patient is predicted to deteriorate in the coming hours or even days. If the prediction indicates that the patient needs critical care, the medical team could then intervene earlier giving patients the best chance of recovery.
The COSMIC-19 Principal Investigator, Professor Fiona Thistlethwaite, medical oncologist at The Christie, said, “Unfortunately some patients who are suffering from COVID-19 on our hospital wards can become seriously unwell. By using this system, we hope to be able to identify these patients early and this may mean
we can optimise their management without the need for them to go to intensive care.”
Dr. Anthony Wilson, the Intensive Care Consultant coordinating the trial at MFT, said, “This technology is a glimpse of how we will monitor hospital patients in the future and it’s fantastic that MFT and The Christie are frontrunners in such innovation.”
Our involvement and collaborations have led us to being entrusted with a new type of clinical trial data that includes the vast amounts of wearable data collected alongside the usual clinical data. This utilised our EDC (Electronic Data Collection) and file sharing systems in the best way, truly showcasing how they can be used to deliver a collaborative and state of the art study design. This study also included co-development of an eTMF (electronic Trial Master File) for several key pieces of data that the wearable sensors presented.
The new elements of the EDC and eTMF will benefit future studies in the collation and processing of data from a range of sources, specifically when the study involves AI modelling. These studies are at the forefront of digital advancements and to have been able to facilitate the data management demonstrates a passion for developing with technology whilst maintaining clinical integrity.
Steve McConchie, CEO of Aptus Clinical said: “We are delighted to have provided clinical operations and Data Management support for this important and transformative clinical trial. Working with the NHS and AI partners, we have developed a novel data sharing system that compliantly integrates biosensor data from patients with their clinical data and transfers it seamlessly to Zenzium for analysis. We are confident that the infrastructure we have built in Manchester can be easily applied to ensure future clinical trials benefit from these AI driven insights, and ultimately lead to better therapies for patients.”
Anthony D. Bashall, Managing Director & Founder of Zenzium stated, “We are extremely excited to apply our AI technology based on time-series Deep Learning including DeepHRV® to this challenge, with the potential to make a substantial impact on patient outcomes.”
Paul Blaney
Paul Blaney, Enablement Lead. Over 20 years’ experience in process improvement solving complex problems with innovative solutions in the clinical operations space.
Ramus Corporate Group
is a union between Ramus Medical, Medical Diagnostic Laboratory Ramus and Medical Centre Ramus. All the companies are situated in the Ramus building in Sofia, Bulgaria. They are certified in compliance with the requirements of ISO 9001:2015.
Ramus Medical is full service CRO, working CTs in a variety of therapeutic areas and medical device.
• Medical writing for drugs and devices
• Scientific review of documentation
• Clinical trial management
• Monitoring
• Data management
• Regulatory advising and services during clinical trial
Medical Diagnostic Laboratory Ramus (SMDL-Ramus)
• 30 clinical laboratories in Bulgaria and North Macedonia
• 325 affiliates for sampling in Bulgaria and North Macedonia
• More than 20 years’ experience in the CT field as central and safety laboratory;
• Largest PCR laboratory in Bulgaria
• Laboratory System integrates cluster generation, sequencing, and data analysis
• Total laboratory automation with Abbott GLP-System
Broadening the Treatment Horizon for Heart Failure Patients
Through its issuance of recommendations and regulatory decisions concerning medical products, the US Food and Drug Administration (FDA) typically considers the “unmet medical need” surrounding a particular disease or condition. In the most extreme circumstances, as with many rare diseases, FDA-approved therapies may not be available. There are also numerous contexts, however, in which treatments are approved, but a need still exists for refinement to better target the patient population—such is the case for heart failure (HF) drugs.
The FDA notes that, despite the availability of HF therapies in multiple drug classes, mortality remains high, and treatment options for a broader range of patients are needed. HF occurs when the heart is unable to pump sufficient blood and oxygen to support other organs. Because HF patients tend to accumulate excess fluid in the body, they can experience particularly debilitating symptoms that include shortness of breath, fatigue, and difficulty with physical movement.
HF can also take a toll on mental health. The authors of a literature review published in 2018 reported that “depression and anxiety disorders are associated with the development and progression of HF, including increased rates of mortality, likely mediated through both physiologic and behavioural mechanisms.”1 The article noted that antidepressants – in particular, selective serotonin re-uptake inhibitors (SSRIs), which are first-line treatment for major depression, generalised anxiety disorder, post-traumatic stress disorder, and panic disorder – are effective in patients lacking heart disease but have “mixed” evidence for their use in HF.
That the incidence of HF is increasing further supports the urgency to address this condition. The American Heart Association (AHA) 2021 annual report, produced in conjunction with the US National Institutes of Health (NIH), noted that the prevalence of HF continues to rise over time with aging of the population.2 According to data from 2015 to 2018, an estimated 6 million adults in the US aged 20 years and older had HF. Prevalence of HF is higher in women than men aged 80 years and above, and overall prevalence is particularly high in both Black females and Black males. Of incident hospitalised HF events, approximately half are characterised by reduced ejection fraction and the other half by preserved ejection fraction.
Treatment Alternatives for HF
As part of a wider commitment to reducing the impact of heart and vascular diseases, the NIH’s National Heart, Lung, and Blood Institute (NHLBI) funds many studies related to HF, including basic research, clinical trials, and large longitudinal studies. The NHLBI notes that not everyone responds to existing treatments, which include medicines, implanted devices, and surgery; thus, research is ongoing to discover alternative treatments. In collaboration with the NHLBI and Yale University, Duke University is conducting TRANSFORMHF (ToRsemide compArisoN with furoSemide FOR Management of HF), a large-scale, pragmatic, randomised, unblinded phase 3 study comparing torsemide versus furosemide as a treatment for HF.
The NIH webpage description for TRANSFORM-HF notes that loop diuretics such as torsemide and furosemide are a “cornerstone” of therapy for HF patients.3 Relative to furosemide, torsemide “advantageously alters pathophysiological mechanisms associated with progression, has a favourable pharmacodynamic profile, and may decrease HF morbidity and mortality,” the description states. However, it adds, furosemide “is overwhelmingly” used daily in the clinic, “which highlights clinical equipoise and an unmet need for an adequately powered study to definitively determine whether torsemide compared to furosemide improves outcomes to guide clinical practice.”
TRANSFORM-HF will enrol approximately 6,000 patients with HF at more than 50 US hospital sites, with the primary objective to compare the treatment strategy of torsemide versus furosemide on clinical outcomes over 12 months in patients with HF who are hospitalised. The trial is targeting enrolment of racial and ethnic minorities and women and is randomizing participants 1:1 to either oral torsemide or furosemide prior to hospital discharge. As of May 12, 2022 the trial status at ClinicalTrials.gov was listed as “active, not recruiting.”4
Modernised Therapeutics, New Indications
The FDA’s efforts to widen the breadth of treatments for HF patients has included the approval of new formulations. In June 2021, the agency approved an updated version of torsemide under the trade name Soaanz, from Sarfez Pharmaceuticals, Inc (Sarfez), for the treatment of edema associated with HF or renal disease in adults. The product label notes that the initial US approval of torsemide was in 1993. According to the sponsor, Soaanz is an improved once-daily formulation of torsemide that provides a new treatment option for HF patients who experience persistent edema and swelling in the lower limbs and/or abdomen, despite a loop diuretic therapy. The drug is intended to provide a longer duration of peak effects without causing excessive urination. Thus, it gives a therapeutic option to HF patients who choose to skip loop diuretic treatment due to concerns with increased urination, as well as patients with chronic kidney disease, Sarfez stated.
More recently, in February 2022, the FDA approved a new indication for Jardiance (empagliflozin), an inhibitor of sodium-glucose co-transporter 2 (SGLT2), from Boehringer Ingelheim Pharmaceuticals, Inc, (Boehringer), to reduce the risk of cardiovascular death and hospitalisation for HF in adults with HF. The FDA originally approved Jardiance in 2014 as an adjunct to diet and exercise to improve glucose control in adults with type 2 diabetes. It is also indicated to reduce the risk of 1) cardiovascular death in adults with type 2 diabetes and established cardiovascular disease and 2) cardiovascular death and hospitalisation for HF in adults with HF and reduced ejection fraction.
“While Jardiance may not be effective in all patients with heart failure, this approval is a significant step forward for patients and our understanding of heart failure,” stated Norman Stockbridge, MD, PhD, director of the Division of Cardiology and Nephrology, FDA’s Center for Drug Evaluation and Research (CDER), in the FDA press announcement of the approval.5
For this latest indication, Jardiance was granted priority review designation, one of the FDA’s programs intended to facilitate and expedite development and review of new drugs to address unmet medical need in the treatment of a serious or life-threatening condition. Under this designation, the agency’s goal is to take action on an application within 6 months (compared to 10 months under standard review). The agency anticipates that drugs under priority review, if approved, “would be significant improvements in the safety or effectiveness of the treatment, diagnosis, or prevention of serious conditions when compared to standard applications.”6
The February label update for Jardiance coincided with the annual observance of American Heart Month, which is hosted by the NHLBI and its health education program, The Heart Truth. American Heart Month is “a reminder for individuals to focus on cardiovascular health,” Stockbridge said, adding that Jardiance, through the latest approval, “will provide physicians another tool to address heart disease.”
REFERENCES
1. Celano CM, Villegas AC, Albanese AM, et al. Depression and anxiety in heart failure: a review. Harv Rev Psychiatry. 2018;26(4):175-184. https:// pubmed.ncbi.nlm.nih.gov/29975336/
2. Virani SS, Alonso A, Aparicio HJ, et al. Heart disease and stroke statistics –2021 update: a report from the American Heart Association. Circulation. 2021;143(8):e254-e743. https://www.ahajournals.org/doi/10.1161/ CIR.0000000000000950
www.journalforclinicalstudies.com
3. TRANSFORM-HF Clinical Coordinating Center (CCC) project details. Project Number 5U01HL125511-05. https://reporter.nih.gov/search/ wiLFZlZsqE2ntEfwWioK9Q/project-details/10234141
4. TRANSFORM-HF study description at ClinicalTrials.gov. NCT03296813. https://clinicaltrials.gov/ct2/show/NCT03296813?term=NCT03296813& draw=2&rank=1
5. FDA News Release: FDA Approves Treatment for Wider Range of Patients with Heart Failure. February 24, 2022. US Food and Drug Administration. https://www.fda.gov/news-events/press-announcements/fda-approvestreatment-wider-range-patients-heart-failure
6. Priority Review. US Food and Drug Administration. https://www.fda.gov/ patients/fast-track-breakthrough-therapy-accelerated-approval-priorityreview/priority-review
Deborah Komlos
Deborah Komlos, MS, is a Principal Content Writer for the Cortellis suite of life science intelligence solutions at Clarivate. In this role, her coverage centres on FDA advisory committee meetings, workshops, and product approvals. Her previous positions have included writing and editing for magazines, newspapers, online venues, and scientific journals, as well as publication layout and graphic design work.
Email: deborah.komlos@clarivate.com
Rapid Rise of Decentralised Clinical Trials
As the world continues to adapt to the impact of the pandemic, a lasting legacy has seen the evolvement of varying approaches to how clinical trials are designed and deployed.
There has been a rapid rise of decentralised clinical trials (DCT) which brings benefits and poses potential challenges in equal measure.
Clinical-trial sponsors are increasingly looking at alternative ways to make trials quicker, more cost effective, while improving the experience of patients and medical teams involved.
The rapid rise of DCT has become more prevalent and increasingly the pharma space is seeing the introduction of different products and services to help encourage enrolment, improve patient participation retention rates and enhance the reliability of data collection and results.
COVID-19 has been a major accelerator and catalyst in the move to DCT offering valid alternatives to the traditional clinical trial model, whereby the patient was expected to attend a site to be able to conduct the research and work with the investigators.
The clinical trial sector had to adapt accordingly as the world was subject to multiple lockdowns with restrictions including limitations on travel, during the COVID-19 outbreak. Home-based, patient centric trials, which were in their minority pre-pandemic, became more popular particularly as they negated the need for patients to travel to a trial site.
New scalable solutions were needed and dispersing trial sites globally provided a more convenient service for participants, existing and new. The rise in DCT meant new more diverse populations could be reached, which helped encourage patient enrolment rates and led to increasingly insightful results.
Changing Face of Clinical Trials
Increasingly biotech and biopharma businesses are adopting decentralised or hybrid models over traditional trials.
It’s anticipated the industry will continue to see a significant shift this year to decentralised and hybrid designs and according to GlobalData analysis approximately 1,300 trials with a decentralised and/or virtual component are anticipated to start in 2022, representing a 28% increase from 2021 and a major 93% boost from 2020.1
While there will always be that need for the traditional clinical trial we will continue to see a more hybrid approach within the clinical trial space.
Clinical trials employ a number of different models including:
• Depot-to-patient model – the medicinal drug is shipped straight from the depot or the pharmacy to the patient. Favoured from a reach and speed perspective if drugs need to be delivered quickly. Negates need for patients to travel to a site.
• Site to patient model – drugs are shipped from the depot to the clinical site and then from the study site to the home of the patient.
• Hybrid model approach encompasses elements of both of the above.
The prevailing patient centred approach aims to build a positive in-house, at home participant experience and a softer hospital approach. Some people don’t like going into a clinical environment. That is removed with the patient-centric approach, which in turn provides the opportunity to involve a larger patient pool, including more of a diverse population.
The traditional approach allows for the important patient/ investigator relationship to stay strong because if participants return to the same site and see the same people they build a good connection. Conversely, if you have a different person visiting a patient’s home each time that might potentially demotivate the participant over time.
The clinical research and drug development industry, alongside selected suppliers involved throughout the trial process, have had to evolve to ensure DCT are successful and encourage enrolment.
Specialist packaging suppliers operating in the clinical trial space play a pivotal part in ensuring the success of DCT and the service offered overall needs to be as holistic as possible. Thermal shipper solutions deployed for clinical trials are vital; however, all facets are key including storage, distribution and return logistics.
From a packaging perspective it’s critical to be able to supply an entire solution that is tried, tested and meets the high-quality standards and risk-averse nature of the pharma sponsors. Currently there are only a handful of thermal packaging suppliers that can provide this specialist service worldwide.
Apart from delivering a high-quality solution, that will maintain product integrity, it’s critical to be able to pivot and be flexible in the space. With more decentralisation sites popping up on a global scale, organisations need to be agile in their strategy to bring a trial through implementation and for it to be successful.
For specialist thermal packaging providers having a global standardised Standard Operating Procedure (SOP) in place is crucial to maintain good best practice, instil confidence in the sponsors and the clinical sites. It’s essential all organisations involved are abiding by the same standards.
High performing protective packaging is vital in the trial process where patient safety is paramount. When deploying drugs from a clinical site to a patient the integrity of the pharmaceutical product is critical.
Well-engineered thermal packaging helps mitigate temperature excursions, ensuring when the drug is administered to the patient it is at the right temperature and maintains its efficacy and potency. This improves the success rate of the trial and treatment administered.
DIRECT TO PATIENT
Having the ability to provide premium thermal solutions that remove the risk of thermal excursion is essential.
Within clinical trial models there can be variations in geographical reach. This requires flexibility and protection across different distances, climates, and transportation modes.
Encouraging and retaining patient enrolment is key to the clinical trial industry. Patient-centric solutions should convey convenience alongside simple to use systems. The clinical trial industry utilises innovative packaging products which don’t require conditioning or complex packing instructions. This means the user can easily prepare the box themselves with no expert intervention.
This ease of use is key from a Direct from Patient standpoint, whereby a biological sample needs to be sent back to the lab, so having an easy to use and activate shipper solution to hand, that doesn’t require any refrigeration or conditioning activity at the patient’s home, is important.
Therefore, selecting a packaging vendor who has a breadth of products is important to fulfil both DtP (Direct to Patient) and DfP (Direct from Patient) program requirements from one thermal packaging supplier.
Also crucial is having breadth of thermal performance, having flexibility in terms of cost and being able to offer a thermal solution that can be conditioned by the client site or prepared by the packaging vendor with the capabilities to offer a preconditioned service.
Offering reusable packaging solutions that can easily be returned and reused is also important from a sustainability standpoint. Choosing vendors who can provide packaging that can be tailored to the trial’s requirements is an advantage. There is a move toward agile, adaptable packaging whereby the shipper solution offers the option to flex the product and have the ability to scale the size of the box to fit the requirement.
Whether grouping cartons of multiple treatments, or shipping a single medical device or diagnostic kit, enlisting packaging suppliers whose product portfolio enables you to fit the box tailored to product requirements, reduces shipping costs and the number being shipped helps lower carbon footprint.
DCT Challenges, Benefits and Future Developments
Potential challenges linked to DCT involve the transference of information, which is imperative in any trial. The data collection and data security involved in the decentralised processes is a major consideration.
With the DCT model a lot of new virtual/mobile technology is being used at patients’ homes that would usually be held at the clinical site. It’s essential to ensure data is stored, accessed and requested in the right framework to make sure rules/regulatory requirements are being met from a data integrity and security perspective.
The DCT model offers benefits including the opportunity to involve a more diverse patient population, which leads to accessibility to more rich data. When collecting the data and opening the trial up to a bigger geography it allows access to a larger data set to draw insights from different populations and combined populations. That accuracy and intelligence and learning behind that data pushes the analysis further and we learn a lot more from it.
Going forward it’s anticipated the future growth in clinical trials will see a more hybrid approach and greater digitalisation across the entire supply chain when it comes to data gathering and data security.
There will be future developments, especially within the cell and gene space tying the patient to the shipment with real-time GPS tracking of shipments, providing greater visibility and the progression of the at home hospitalisation experience will grow.
Patients like the convenience DCT offers, which hopefully will increase attendance and enrolment rates. This is particularly vital as a significant percentage of clinical trials fail due to patient dropout rates which are estimated at; Phase 1: 60–70%, Phase 2: 40–50% and Phase 3: 30–40%.
Reducing those rates will ultimately benefit clinical research results and help bring new drugs to market.
REFERENCES
1. K Parkins and A Hillman: 2022 forecast:decentralised trials to reach new heights with 28% jump – https://www.clinicaltrialsarena.com/analysis/2022forecast-decentralised-trials-to-reach-new-heights-with-28-jump/
Lee Stopher
Lee Stopher is Product Manager at Peli BioThermal. He is responsible for launching high quality thermal packaging products, services and systems that are driven by people, problems and data. His areas of responsibility include market intelligence, product strategy, new product development and lifecycle analysis. Prior positions include design engineer and account management across a variety of industries, including software, health and fitness. He holds a First Class Honours degree in BSc Product Design from Middlesex University.
Email: lee.stopher@peli.com
International Clinical Trials Day – R&D Experts Weigh in on What the Future Holds
Each year, on 20th May, the global health community celebrates International Clinical Trials Day, the anniversary of James Lind’s famous scurvy experiment in 1747 on H.M.S. Salisbury. Lind’s discovery – that sufferers of the disease recovered faster if they included citrus fruits in their diet – is considered one of the earliest examples of a successful controlled clinical trial.
Today’s clinical studies are drastically different, benefiting from modern expertise, access to advanced technology and vast volumes of data. Yet, the overall objective is consistent with Lind’s study 275 years ago: getting innovative, tested, and safe treatments to those who need them most. It’s important that the pharmaceutical industry remembers these objectives and takes action to ensure that patients always come first, and new treatments can be brought to those who need it.
The opinions on what action needs to be taken varies depending on what area of the industry you operate in, and R&D experts have a range of thoughts on how to make the clinical trial experience better for all involved.
Putting Patients First Means Managing Data Effectively
One such expert is Richard Young, Vice President Vault CDMS at Veeva Systems. “Whilst they’ve been around for a while now, the
COVID pandemic saw the reported adoption of virtual clinical trials in pharma skyrocket” states Richard. “This meant that regardless of their proximity to research sites, volunteers could still participate in clinical trials without the need for in-person contact. Since then, the pharmaceutical industry has continuously made an effort to implement technology than can help make trials more patientcentric, and ultimately a more comfortable experience.”
But whilst patient centricity and the ability to conduct studies globally have been great steps forward for clinical trials, Richard believes it has covered up a somewhat inconvenient truth. “With decentralised trials, sponsors have no clear-cut way to aggregate and review the huge volume of patient data being gathered from disparate sources. This problem is not new – and it is inherent with decentralised trials that the same data for different patients will be collected in different ways.” Moving forward, Richard feels that aggregating data in a central clinical data management system (CDMS) will be “crucial to achieving the visibility and timeliness that we know contribute to more effective trials.”
In the coming years, Richard hopes to see an ambitious standard adopted industry-wide when it comes to digital trials. “The wishes of the patient should always come first” he claims, “and this needs to be taken into account at all levels when executing trials. As data collection becomes distributed, trial data should continue to be aggregated and harmonised on one central platform. This allows for study managers to effectively oversee and manage trials and allow for clinical studies to be incorporated seamlessly into everyday life.”
The Role of Automation in Clinical Trials
As trials become more intricate, the number of processes and manual tasks involved increases. With technological advancements, we’re seeing a huge opportunity for automation to empower scientists to work smarter and more efficiently. This leaves the repetitive, manual tasks of clinical trials to robotics, like pipetting into test tubes, and gives scientists in the lab a chance to focus on more strategic and analytical work.
Craig Johnston, Diagnostics & Genomics Lead at Automata, believes that automating processes can have a significant impact on every stage of a clinical trial. “From the initial development of the trial, through to sample collection and analysis, automating processes can ensure a level of repeatability and traceability that empowers lab technicians to process and analyse much higher volumes of high value data samples, with far greater precision,” claims Johnson.
“Clinical trials are a critical part of drug discovery, and many organisations will be running over ten different trials concurrently. When the stakes are so high, it becomes critical to reduce the risk of errors.” Craig notes, however, that it is not uncommon for organisations to track progress and results of multiple trials on paper. “Paper tracking is incredibly susceptible to manual error, especially when tens or hundreds of samples are managed per hour, and a single mistake can be costly and slow down the development of much needed drugs and treatments. With the full traceability offered by automated systems, lab technicians gain increased visibility to every step of the process, enabling them to eliminate potential mistakes and work more efficiently.”
When it comes to hospital trials, Craig has noticed that they have a particular challenge around scale, with huge volumes of samples coming in at speed and labs needing to be able to process them with efficiency and care. “One way to manage this is through dynamic scheduling” notes Craig. “Using an automated workflow management system can manage multiple lab processes across numerous trials at the same time, even when samples are coming in thick and fast from the ward. Automation also has an important role to play in data collection.
Machine learning and AI analysis technology is increasingly being applied in lab spaces, and as a result, this large volume of quality data is a true differentiator in producing precise results that support drug discoveries. To obtain these data sets, end-to-end automation is essential, as it gives lab technicians the ability to work with higher volumes of data than before without the fear of human error or losing track of results.”
International Clinical Trials Day is a chance for the pharmaceutical and R&D community to remember the past, and appreciate just how far clinical trials have come in recent years. But rather than resting on its laurels, it’s important that the industry continues to strive for improvements in the trial process, looking to the future at how we can continue to innovate and adapt to improve trial outcomes for all involved.
Craig Johnston
Automata is a leading provider of robotic automation solutions to the life science industry, and Craig leads the Diagnotics and Genomics team - one of Automata's key focus areas. After coming to the role two years ago with little knowledge about the world of robotics, Craig's role is now focused on making the application of that technology less daunting to customers.
Richard Young
Richard Young is Vice President, Vault CDMS, at Veeva Systems. With over 25 years of experience in life sciences, Richard is known for his executive vision and proven operational experience in data management, eClinical solutions, and advanced clinical strategies. His role at Veeva is helping to transform the way we approach clinical data, unifying every contributor and consumer in a single platform.
Calculating Sample Size for Medical Device Studies
Sample size has always been one of the first design choices a medical device sponsor has to make for a clinical study. But the calculation of sample size is not the most straightforward process and often leaves clinical teams wondering which method to use. What is the appropriate sample size for my medical device study/ survey? How can I provide justification for sample size in medical device study? Can I use a sample size calculator for my clinical trial? These are the most common questions regarding sample size for medical device studies. Note that it is recommended to avoid generic sample size calculators for clinical trials, as the many variables between different medical device studies vastly increase calculation uncertainty. In addition, medical device sample size justification may be negatively impacted by utilising simplified tools for sample size calculations.
In most cases, it’s impossible to conduct a medical device clinical study that includes the total population of interest (i.e. target population), especially if the population size is indefinite. Instead, we conduct studies with a sample from the population, in the hope that the information gathered about the sample will enable us to make inferences about the total population. So, sample size calculation in medical device studies is actually the process of determining the minimum number of samples that would make a study’s outcome/s statistically significant (make your results more reliable in statistical terms).
To calculate the sample size for a clinical study, we use statistical equations that employ inputs that mirror the population(s), study objective and design. But the problem with the calculation is that it is based on assumptions on these inputs, and not necessarily the ‘best’ or ‘correct’ values. Therefore, the calculation is only as good as the assumptions you make. If your assumptions are too far off you might end up with a too small or too large sample size, which may affect the study outcomes and conclusions. Thus, to minimise the likelihood of your calculation returning a too small or too large sample size, your assumptions must be evaluated thoroughly.
With the appropriate sample size calculation for a medical device study you can:
1. Increase the likelihood of study results to mirror a true effect (or difference). Your clinical study results are more likely to portray the reality, rather than just chance alone.
2. Limit unnecessary exposure. From an ethical and riskbased standpoint you should only include the necessary number of subjects in your study.
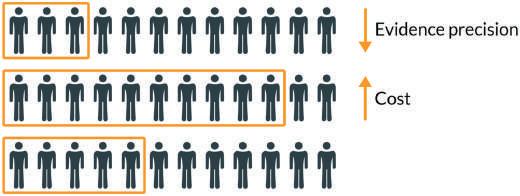
3. Improve precision and reduce cost. The sample size is highly correlated with the cost of operation and the precision of your clinical evidence. With the appropriate calculated sample size, you ensure that you miss both evidence precision and cost.
The EU MDR describes the requirements for both a Clinical Investigation Plan (CIP) and a Post-Market Clinical FollowUp (PMCF) plan. In both cases, medical device study sponsors must document the various design choices for a clinical study, such as the choice of sample size, and provide a rationale for the appropriateness of the procedures and the methods used. Even though you are not conducting a clinical study as a part of your PMCF plan, but a survey or a cohort of some kind, you still need to provide rationale or justification for your design choices – including the sample size. Many ethical committees also require justification for the choice of sample size before approving a clinical study. And depending on the study type, and the market approval pathway in the United States, the FDA requires justification of the sample size calculations as a part of a statistical analysis plan as well.
Many fail to realise that it is the combination of both the statistical and clinical assumptions that determines the sample size justification and thereby applicability. By leaving out either of the two, you are only providing partial justification on your sample size.
Preparing for Sample Size Calculations in Clinical Research
To calculate the appropriate sample size for your study, you need to have knowledge of the expected study results. This is used to determine how the study should be conducted, what data
Figure 1
Figure 2
should be collected and how its results should be analysed (and statistically tested).
When it comes to conducting the sample size calculation, you apply statistical equations that are derived from the hypothesis you want to test. But before the equations come into play you need to keep in mind that a few other things have an impact on the method of medical device sample size calculation, such as:
What is the Purpose of Your Clinical Study?
When it comes to conducting studies whose purpose is to confirm a theory or claim for clinical performance or safety, such as pivotal trials, clinical investigations for market access, or PMCF, you will need to provide justification for sample size calculation (at least according to the EU MDR).
What is the Objective of Your Clinical Study?
Every clinical study has an objective, i.e. whether you want to test your medical device's superiority, non-inferiority, equivalence, or another effect/difference. The study objective will have a direct impact on the choice of sample size calculation (the formula for sample size calculation) and your statistical hypothesis test.
Study Endpoints
Depending on the nature of the endpoints in your study, sample size calculation formulas have to be adjusted, especially if the endpoint involves multiple comparisons. In some cases, you can use different types of endpoints to evaluate the same clinical outcome. But depending on the endpoint you choose, the sample size can change drastically.
Study Design
Whatever design you choose, you need to know that it will impact the sample size calculation. For example, a crossover study and a parallel two-group study require two different equations to calculate the sample size. The crossover study only requires a part of what a two-group parallel study needs in terms of sample size.
Statistical
tests
There are numerous different statistical tests that can be used to analyse and test the results of your study. Usually, this must be a part of the statistical analysis plan and is highly related to the endpoints you are looking to collect. Depending on the statistical tests you choose for your study, you will need to use the appropriate sample size formula, and thus extract the sample size from the formula to calculate the sample size for the study.
The Basic Inputs behind the Sample Size Calculations
For most sample size calculations in clinical research you need five basic inputs. All five inputs are values (or numbers) that you must define or make assumptions on, and depend on the study objective, endpoints, and design. Sample size calculation is very sensitive to the inputs used, which invites a large risk of imprecision or error. Due to the nature of some of these inputs, it is rare to have an ‘accurate value’. But to minimise the imprecision, you need to carefully evaluate each input from both a clinical and statistical standpoint, using existing know-how of the domain of interest, the clinical pathway/setting and your device.
1. Statistical Hypothesis
2. Significance level
3. Power
4. The minimal, clinically meaningful, effect
5. Variability
Apart from the basic inputs, there are three additional factors that should be taken into account when calculating sample size: Test margin, Subject drop-out rate, and Treatment allocation. Depending on the study objective and design, these factors can impact the final number of subjects needed for your study.
Conclusion
Sample size calculation for medical device studies should not be treated lightly and there’s no ‘all-in-one’ solution to determine a clinical study sample size.
To pass the scrutiny of regulators and Notified Bodies, companies will need to provide statistical and clinical justification of the sample size calculation. It’s not enough to solely document the statistical assumptions made, but it’s the combination of both statistical and clinical (scientific) assumptions that determines the sample size calculation applicability. Sample size justification is required for both pre-market clinical investigations and postmarket activities.
Jón Ingi Bergsteinsson
Jón Ingi Bergsteinsson, M.Sc. in Biomedical Engineering, is the Founder and CCO-EMEA at SMART-TRIAL, where he helps MedTech companies to bridge the gap between their devices and clinical data. With a strong technical background, and 10 years of experience in clinical investigations, eClinical software, and medical devices, Jón is mostly occupied with sharing valuable insights and know-how on clinical data collection with the MedTech industry.
Email: jon.bergsteinsson@smart-trial.com
Get your Ducks in a Row for the Data-driven Future
Stakeholders across the life sciences industry now understand that data is more important than documents but also that it’s crucial that the data is reliable and can be trusted as a definitive source of truth. Amplexor’s Agnes Cwienczek sets out the steps that life sciences organisations must now take to get their data in order.
All life sciences companies aspire to a ‘data-driven’ operational and strategic future but right now many are a long way from that lofty aim.
The goal is that a range of interconnected business functions, including those involving suppliers and regulators, will be able to rely on a comprehensive, approved master data source which can be drawn from in order to support a whole range of critical next actions.
But if that data lacks integrity, or is out of date or incomplete, businesses could fall foul of the authorities, and even incur delays to market. Also, there is a danger than everything they do will be founded on false assumptions, meaning that problems are perpetuated and risks are magnified.
All too often, this is not realised until a new system implementation or update project is underway in a particular department. When the time comes to migrate existing data from existing systems, panic sets in as IT teams and business users discover that their ambitions for the new set-up will now be compromised or stalled because of the poor quality and/or unwieldy or incomplete nature, or conflicting and potentially irreconcilable formats of the incoming data.
This could cost companies dearly. On top of the inevitable delays and additional expense incurred by any reactive damage-limitation exercise, companies entering into a remedial data preparation exercise are likely to be investing those new resources in a finite project with a single target use case. This is directly at odds with the higher and more strategic aim of creating a more data-driven business.
What Steps to Take
So what should companies be aiming for in order to avoid this situation?
The first thing to note is that regulatory information is a great starting point for proactive data transformation, because it serves so many other functions and use cases beyond its own. That means that the transformation of regulatory information data quality warrants senior buy-in – since all commercial and reputational outcomes stem from this.
With this in mind, there are some critical considerations to ensure that investment in regulatory data quality rises up the corporate agenda and is targeted for transformation on a comprehensive scale.
1. Get Ahead of the Game
Any process and its supporting IT system is only as good as the data it has access to and what it is able to reliably do with it. So improving
the quality and usability of data is something that needs to start now, outside of any specific departmental system project. This it is both something that will take a long time, and which needs to happen continuously.
For this reason, it’s important to assess, and scope the work involved, which will involve prioritising target data and critical use cases, so that transformation can happen in a staged way towards a long-term goal.
2. Set Parameters
Setting realistic expectations will be important in ensuring that the quality, richness and overall value of regulatory data grows and benefits the organisation as a whole. Not all life sciences companies have the resources needed to overhaul all of their data in one go, which means data transformation, governance and maintenance should be a continuous discipline rather than a one-off effort. At some point the responsibility for data monitoring and upkeep needs to become part of everyone’s day-to-day remit and routine.
First, though, it will be important to set some parameters and decide which data takes priority. Logically, it may make sense to target improvements by geography (starting with strategically important target markets), and then by the data with the greatest impact (for instance, data that’s most likely to be consumed by others, outside of the Regulatory operation).
That’s likely to be:
• Details of existing product registrations and their status
• Details of the markets products are registered in
• Related submissions/the latest documents and information used in these registrations
• Information about safety-related changes and details.
Work on operational data, such as who made what changes as well as any data linked to the company’s internal planning and tracking objectives, can come later. Details of interactions with the various external authorities might fall within this tranche of data improvement/enrichment.
Once those parameters have been established for a first phase, those involved can begin to assess where they are now versus where they need to be – including where all of this data currently resides, and what state it’s in.
3. Keep an Eye on Upcoming Compliance Requirements
It makes sense to use upcoming regulations as an additional driver of data preparations, keeping a weather eye on the EU’s evolving implementation of ISO IDMP, the FDA’s PQ/CMC requirements in the US, and equivalents in Asia and beyond. This will both enhance the business case and ensure that work doesn’t have to be repeated if expected data fields or formats haven’t been taken into consideration during the ‘groundwork’ phase.
4. Use Cross-functional Teams
Appointing cross-functional teams will help ensure that all users of
regulatory data within the organisation have a voice and can play a part in determining any information’s relative value and various use cases. This will help pinpoint which data is most critical and needs the most work, and how that data is currently collated, stored, maintained and used across processes and departments.
As with any initiative of strategic importance, transformation needs to be desired, championed and led from the top of the organisation: better data and clearer process visibility needs to become part of the DNA of the business. In an ideal scenario, certainly if the company is big enough, dedicated data managers should be appointed or hired, to oversee the data transformation journey and to act as supervisors to execute the new framework.
External capabilities will typically span two camps: (change) management consultants who can advise on frameworks, optimal teams and the ramp up of the transformation effort; and technology providers whose systems hopefully offer sufficient flexibility and granularity to accommodate all current and future data requirements and which make it easy to adhere to good data practice.
5. When Upgrading IT, remember Data Quality Issues
Finally, unless companies start to allow for data analysis, preparation and quality maintenance as part of their overall project plans, they will continue to fall victim to project scope creep and last-minute fire-fighting.
Building data quality considerations into any Evaluation effort/ Request for Proposal (RFP) as separately itemised requirements becomes critical when evaluating a potential new IT solution or upgrade.
Beyond that it’s important to ensure that any new platform or solution can connect readily to legacy resources, and can access and work effectively with their data.
Commit to Being ‘Data Driven’
The road ahead may be steep but the regulatory data quality journey must start somewhere. Until companies get ahead of the situation, the discovery of poor-quality, inconsistent or incomplete data will continue to impact via audits, missed registrations and project disruption.
Taking the first step towards improved data quality has never been more important – and the time to start is now.
Agnes Cwienczek
Agnes Cwienczek is Head of Product Management and Consulting at Amplexor Life Sciences, with a remit including the provision of business process and data management expertise in the areas of Regulatory Information Management, Document Management, Submission Management and Labeling Management. Prior to joining Amplexor, Agnes worked at Merck in its Global Regulatory and Quality Assurance department, a milestone in a career spanning 15+ years at the frontline of regulatory information management. She holds a Master’s degree in Information Management from the University of Koblenz-Landau in Germany.
The Relevance of the Guidelines on Good Distribution Practice (GDP) in the World of International Clinical Trials
The successful execution of international clinical trials requires the involvement of service providers adhering to a wide range of regulatory guidelines and industry standards including the Good Clinical Practice (GCP), the Good Manufacturing Practice (GMP) or the Good Laboratory Practice (GLP). Companies following the guidelines of Good Distribution Practice (GDP) are also involved in ensuring that the logistics and quality assurance requirements of the products used in clinical trials are duly met. The article aspires to highlight the different aspects of Good Distribution Practice (GDP) that are relevant to the sector of clinical trial management. It also aims to identify those professional characteristics that sponsors, and contract research organisations (CRO-s) should look for in a potential service provider within the realm of pharmaceutical wholesaling and distribution services.
Diversity of Professional Standards
International clinical trials involve a wide range of stakeholders and service providers including pharmaceutical manufacturers, contract research organisations (CROs), laboratories, public and private healthcare institutions, IT solution providers, regulatory agencies, and pharmaceutical wholesalers to name a few. All these different parties must adhere to the certain regulatory rules and regulations that directly derive from guidelines that govern the operational and quality standards based on which their activities must be executed:
• The Guidelines on Good Manufacturing Practice (GMP) describe the minimum standards that a medicines manufacturer must meet in their production processes. The GMP guidelines concentrate on areas, such as manufacturing standards, releasing, or licensing procedures.
• The Guidelines on Good Laboratory Practice (GLP) define the requirements of quality systems under which non-clinical health and environmental safety studies are executed. The GLP guidelines focus on how such studies are planned, performed, monitored, recorded, reported, and archived.
• The Guidelines on Good Clinical Practice (GCP) identify the ethical and quality standards based on which clinical trials that involve the participation of human subjects should be conducted. The GCP guidelines specify the required processes for duly designing, organising, recording and reporting trials while protecting the rights, safety and wellbeing of trial subjects and preserving the credibility and robustness of the collected trial data.
Apart from these principal regulatory guidelines, additional standards also exist, which are less widely known and are not necessarily codified so formally in legislation on European or national levels. These additional standards do however have a substantial impact on all the primary guidelines relevant in the pharmaceutical sector (GMP, GLP, GCP, etc.) and do constitute the basis for industry best practices for all parties involved in the
manufacturing and distribution of pharmaceutical products, or the conduct of international clinical trials. Some of the most defining additional standards are the following:
• The Guidelines on Good Documentation Practice (GDocP) establish the standards for the full lifecycle of the formal documentation process in any operational settings. The GDocP guidelines outline how formal documents should be created, approved, modified, maintained, and archived.
• The Guidelines on Good Pharmacovigilance Practice (GVP) include measures to facilitate the due performance of pharmacovigilance activities in the entire supply chain of pharmaceutical products and with the participation of all stakeholders within all member states of the European Union.
• The Guidelines in Good Storage Practice (GSP) lay down the principles based on which pharmaceutical products should be stored and handled while in storage. The GSP guidelines cover the due requirements for infrastructure, equipment, personnel, documentation, and operations.
Guidelines for Pharmaceutical Wholesale Distributors
Along with the GMP, GLP and GCP guidelines, the Guidelines on Good Distribution Practice (GDP) are one of the most important regulatory standards within the pharmaceutical sector. Formally, they are enshrined in the Guidelines of 5 November 2013 on Good Distribution Practice of medicinal products for human use (2013/C 343/01) of the European Commission. The GDP guidelines determine the minimum standards that a wholesale distributor must meet to ensure that the quality and integrity of medicines is maintained throughout the entire supply chain from the manufacturer till the site of dispensation (e.g., pharmacy, private or public healthcare institution, etc.). Wholesale Distribution Authorization (WDA) holders should in all cases be strictly adhering to the GDP guidelines but there are other regulatory requirements (e.g., the Falsified Medicines Directive and Delegated Regulation) with which they should align their processes as well.
In general, the GDP guidelines identify the requirements for the infrastructure, the quality systems, the operational processes, and the personnel of wholesale distributors. The GDP guidelines include specific sections on all elements that could be relevant to the operations of wholesalers. These include the following topics:
• the composition of due quality systems,
• principles of documentation practices,
• the management of outsourced activities,
• the role of management review in quality assurance processes,
• quality risk management,
• requirements and training of personnel,
• requirements of physical premises including temperature monitoring and controlling systems,
• requirements of equipment including calibration, maintenance, etc.,
• qualification of suppliers and customers,
• management of falsified products, product recalls, returned products and complaints,
• receipt, storage, picking, packing, supply, and destruction of products,
• requirements for the transportation of products.
The Role of GDP Certified Service Providers in Clinical Trials Service providers adhering to the GDP guidelines and equipped with a WDA play a substantial but often forgotten role in the world of clinical research. GDP certified pharmaceutical wholesale distributors are responsible for a wide range of services required for the successful execution of clinical trials. These services include the procurement, storage, picking and packing of a wide range of products as well as their scheduled delivery to clinical trial sites. Wholesalers are also frequently entrusted with the task of collecting unused products from investigatory sites and ensuring their proper destruction. In principle, it is the role of pharmaceutical wholesale distributors to guarantee the uninterrupted, safe, transparent, and well documented supply chain of rescue medicines, comparators and all types of ancillary products needed to duly execute the planned trial protocols.
The contribution of WDA holders can also be crucial when it comes to quickly reacting to and solving unexpected challenges, such as the sudden occurrence of product shortages. In these situations, a seasoned pharmaceutical wholesaler can quickly leverage its regulatory know-how and connections with the national competent authorities in the concerned markets and acquire the necessary import permits to replace the products impacted by the shortage situation. In addition, a skilled service provider can quickly mobilise its network of international partners and ensure a timely procurement of the appropriate quantities from products that could potentially serve as due substitutes. An experienced wholesaling operator should be well aware of the documentary requirements of such import transactions and be well versed in all the additional processes that such transactions entail (e.g., lead times for delivery, customs clearance, international logistics, etc.).
Criteria to Select a GDP Certified Service Provider
Selecting a GDP certified service provider and WDA holder to fulfil all supply related and logistic requirements concerning the different types of products needed in a clinical trial can be a formidable challenge. To ensure that all the above-described standard tasks and responsibilities are carried out with utmost efficiency, operational expertise in various types of related activities and a solid relationship capital with suppliers and regulatory bodies are required. An ideal wholesaling partner entrusted with the entire supply chain of a clinical trials must be well versed in all the applying regulatory and industry standards (GMP, GDP and GCP); must have a widescale enough local and international network of suppliers to secure a stable supply of products even in case of shortages; and should maintain direct lines of communication to marketing authorisation holders to guarantee the availability of the required quality assurance related documentation as well as competitive prices. The following six points aim to identify those professional characteristics that sponsors and CRO-s should look for in a potential service provider within the realm of pharmaceutical wholesaling and distribution services:
1. Demonstrating regulatory expertise within the context of clinical trials is key to ensuring logistics support compliant with all the relevant rules and regulations which sponsor and CRO initiated activities need to adhere to. Naturally, such regulatory expertise should include the implementation of the GCP standards to all services performed in relation to a clinical trial as well as a clear understanding of the additional needs (e.g., specific documentation protocols) of clients. Sponsors and CRO-s should select pharmaceutical wholesale distributors with a substantial enough sectoral know-how and robust
enough quality system that could withstand a potential external inspection by a national competent authority or an internal audit by the sponsors or CRO-s themselves.
2. Maintaining a good relationship with regulatory agencies can play a major role especially when the transactions between the entrusted pharmaceutical wholesale distributor and the sponsors or CRO-s require frequent interaction with national competent authorities. These occasions might include situations where products needed for a clinical trial are subject to the issuance of imports permits on behalf of the national regulatory agency. Preexisting communication channels to the main regulatory body and experience with various application protocols concerning import permits might be extremely useful particularly when the scope of products supplied to a specific clinical trial includes controlled drugs as well. Also, a good working relationship with the authorities is a definite advantage, when unexpected shortage situations critically threaten the continuity of a clinical trial. In those instances, pharmaceutical wholesalers must act quickly to resolve the impeding supply situation to which a preceding dialogue with the regulatory bodies is indispensable.
3. Fostering a good relationship with marketing authorisation holders is vital for various reasons. From a GDP compliance point of view, sourcing products for clinical trials via the shortest possible supply chain is crucial. The longer such chain is, the higher the risk becomes in terms of unexpected events (e.g., deviations) taking place during storage, handing and transportation. Also, sourcing products via pharmaceutical wholesalers in direct contact with marketing authorisation holders provides a competitive advantage in terms of cost efficiency as prices do not escalate given the limited number of participants in the supply chain. Finally, when a direct channel to marketing authorisation holders exists through a single service provider, essential product documentation, such as Certificates of Analysis (COA) or Certificates of Conformance (COC), can be easily obtained. The same applies to more specific quality assurance related information, such as stability data needed to evaluate temperature deviations.
4. Cultivating a wide network of international suppliers might prove relevant especially when the uninterrupted supply of products required for a clinical trial can only be achieved via different import mechanisms. In such cases, it is of paramount importance to choose a service provider who is well embedded in the global supply chain of pharmaceutical products. A pharmaceutical wholesaler with a wide network of international suppliers that consists of manufacturers, marketing authorisation holders and other wholesalers can much more efficiently leverage its international relationship capital than service providers focused exclusively on their local markets. Also, wholesalers with an international edge are most probably better experienced with all aspects of import mechanisms including the application processes for permits, the procedures of international transportation or the requirements of custom clearance.
5. Maintaining a comprehensive scope of logistics operation could be a major advantage that a GDP certified wholesaler can provide to a sponsor or CRO responsible for organising a large scale, multi-centre clinical trial. Working with a local wholesaler who is already involved in the provision of goods to the healthcare institutions acting as investigatory sites in the clinical trial in question makes deliveries more efficient and economical. Also, given the selected wholesaler’s know how in terms of the
infrastructure layout, access or product receipt protocols of such healthcare institutions, potential mistakes concerning the delivery processes (e.g., delivery documentation not administered properly, products not delivered to the exact location or specified personnel, temperature deviations experienced during the handover process, etc.) can be minimised.
6. Offering manufacturing services required by clinical trials can be the cherry on top of the service cake offered by an ideal service provider. Naturally, manufacturing activities can only be carried out when the selected wholesaling partner also holds a manufacturing authorisation and adheres to the Guidelines on Good Manufacturing Practice (GMP). Additional activities carried out based on a GMP authorisation can include the storage, handling, and delivery of investigational medicinal products to clinical investigatory sites; or the labelling or packaging of any products as required by the regulations and specified in the clinical trial application dossier.
Conclusion
Regulatory guidelines and the involvement of service providers who strictly adhere to them play an important role within the world of international clinical research. Uniformity and standardisation are key principles to be uphold by all means in the context of services rendered and processes followed in case of clinical trials. Hence, sponsors and CRO-s must leave no stones unturned to ensure that they work with partners who are fully compliant with the guidelines relevant to their own activities, let those be the guidelines on Good Manufacturing Practice, Good Laboratory Practice or Good Clinical Practice.
Pharmaceutical wholesalers supplying products to clinical trials must abide by the guidelines on Good Distribution Practice. Such guidelines are complex and reflect on the wide scope of services typically rendered by pharmaceutical wholesalers to sponsors and CRO-s when it comes to physically storing, handling and delivering products to investigatory sites. The guidelines also include instructions on other tasks that could potentially arise during the administration of a clinical trial, such as arranging the destruction of unused products or the potential importation of products in case of shortages.
Sponsors and CRO-s have their work cut out in terms of finding a GDP certified pharmaceutical wholesale distributor who can serve
as a reliable and professional partner to fully support their clinical trial operations. The ideal attributes of such service providers can be easily identified as listed earlier in the article. Sponsors and CRO-s should look out for organisations that can boast of having a well-established network of suppliers and wholesalers locally and internationally; a direct line of communication with the national competent authority; an existing know-how and regulatory understanding about the specific requirements of clinical trials; and a complex enough operational service portfolio.
REFERENCES
1. Guidelines of 5 November 2013 on Good Distribution Practice of medicinal products for human use https://eur-lex.europa.eu/LexUriServ/LexUriServ. do?uri=OJ:C:2013:343:0001:0014:EN:PDF
2. Commission Directive 2003/94/EC of 8 October 2003 laying down the principles and guidelines of good manufacturing practice in respect of medicinal products for human use and investigational medicinal products for human use https://eur-lex.europa.eu/legal-content/EN/TXT/ PDF/?uri=CELEX:32003L0094&from=EN
3. Guideline for good clinical practice https://www.ema.europa.eu/en/ documents/scientific-guideline/ich-e-6-r2-guideline-good-clinicalpractice-step-5_en.pdf
Tibor Kovács
As Managing Director at PHARMAROAD KFT, Tibor is directly responsible for the activities of the Clinical Trial Supply Division. He oversees business relations with sponsors, clinical research organisations and clinical trial supply specialists. Tibor’s work entails commercial, logistic, and quality assurance related aspects of clinical trial supply services. He acts as the lead representative of the company during vendor qualification audits. He is a qualified International Clinical Research Auditor accredited by the International Accrediting Organization for Clinical Research. Tibor holds an undergraduate degree from the University of Lincoln in Lincoln, the United Kingdom, a graduate degree from the Asia-Europe Institute in Kuala Lumpur, Malaysia and a postgraduate degree from the Universidad Autónoma de Madrid in Madrid, Spain.
Tower Cold Chain Launches KTEvolution Container for Pharmaceutical Transport
The temperature-controlled transportation of pharmaceuticals, lifescience and biotech products is now even easier thanks to the latest launch from Tower Cold Chain – a robust lightweight handleable solution with the same reliable thermal protection and reusable durability of Tower’s existing container range.
Listening to customers’ needs, Tower Cold Chain has developed the KTEvolution, robust, reliable, and reusable cold chain solution, which can easily be carried by 1 or 2 people and is ideal for transporting clinical study samples.
The introduction of KTEvolution adds to Tower Cold Chain’s existing product portfolio for the easy, cost-effective and compliant transport of pharmaceutical products between suppliers, manufacturers, distributors and end patients throughout the global supply chain.
With up to 120 hours performance KTEvolution is customisable based on customers’ supply chain needs and will be launched in 26-litre and 57-litre options. In line with Tower Cold Chain’s range of solutions it will be available across a full temperature range and is ideal for the transportation of pharmaceuticals, life-science, and biotech products that require an internal temperature of -70°c, -20°c, +5°c, +20°C.
Market prototypes demonstrate the weight and handling of the KTEvolution make it ideal for the growing trend in smaller shipments such as clinical studies, direct-to-patient, samples shipment, and last-mile deliveries.
By providing 120+ hour thermal insulation and requiring neither external power nor human intervention during transit, products can be safely and reliably shipped worldwide in the KTEvolution.
The KTEvolution fills a gap in the cold chain shipping market, with a patent-pending design that strikes the optimum balance between high performance, durability, and optimised weight.
Innovation is achieved through the KTEvolution’s minimal fixtures and fittings, notably a light-weight webbing system which runs around the external body of the container. Designed with integral handles attached at the top (which can be folded into the container surface when not in use), this custom-built harness provides an even distribution of load to simplify the manual handling process.
The KTEvolution design meets Tower’s commitment to sustainability as it uses phase-change technology incorporated with lightweight vacuum insulated panels to achieve its long-term thermal protection without any manual intervention. With recyclable polyethylene foam strategically placed in critical areas to protect against potential damage through impact and shock sustained during transportation, the KTEvolution is a hard-shelled completely sealed unit, meaning it is a fully weatherproof and washable supply chain solution, minimising the risk of microbial and bacterial product contamination, and complementing a circular economy.
With built in datalogging technology to provide real-time confirmation of internal temperature and on-delivery sign-off, the KTEvolution has the potential to be fully connected with integrated smart technology solutions such as location, temperature, shock, and impact monitoring. The integrated temperature monitor display located at the top of all KTEvolution units provides peace of mind that the container has been properly pre-conditioned to meet customers’ temperature requirements, guaranteeing product integrity from the moment the product is loaded until it reaches its destination.
The KTEvolution is launched in conjunction with Tower’s on-going expansion of its global hub networks to provide robust, reliable, reusable cold storage solutions which are available and in close proximity to Tower customers in all geographies.
For more information on the KTEvolution, visit https://bit.ly/36XA44e
Regenerative Medicine: Confusion or Complacency?
The subject of Regenerative Medicine is currently at an inflexion point.1 There has been an enormous amount of financial investment, along with basic and clinical research, but despite these efforts there is only one tried and tested use of stem cells and that is bone marrow transplantation (using haemopoietic stem cells) which was first developed in 1957.2 The rest of Regenerative Medicine is currently confused with the identification of multiple stem cell types,3 many clinical trials4 but no real progress to a safe and effective routine stem cell-based procedure for any disease.
Perhaps the most studied stem cells (apart from haemopoietic stem cells) to date are mesenchymal stem cells (MSC) which are found in adipose tissue,5 umbilical cord tissue6 and even inside teeth.7 Despite this apparent abundance of MSC for potential clinical use there have been many problems along the way such as complicated and expensive isolation and preparation of MSC, lack of standardisation of MSC preparations, licensing issues in some countries and unreliable clinical outcomes. As a result, MSC technology has staggered to an almost halt with little or no standardised treatments available.
The second types of stem cell which caused great excitement, and even greater hype and cost, are embryonic stem cells (ESC)8 and induced Pluripotent Stem Cells (iPSC).9 The problems relating to ESC are that they are made by destroying a human embryo which causes considerable legal, ethical, religious and moral objections. They are also technically difficult to create and require extensive regulatory approval making them extremely expensive. The problems relating to iPSC are that they are ‘man made’ from normal body cells (e.g. skin cells) by the introduction of new genes into the skin cell to ‘turn it into’ a stem cell. The reservations here are cost, safety and efficacy and once again neither ESC nor iPSC have reached routine clinical practice.
Thankfully, there is one stem cell type which is readily available, cheap to produce and potentially very safe and effective. These stem cells have an unusual name and equally unusual properties. The name of the stem cells is human Very Small Embryonic Like (hVSEL) stem cells.10 These hVSEL stem cells are present in every tissue in the body (including blood) and they are pluripotent meaning that they can, in theory, regenerate any tissue type in the body.11 The fact that they are termed ‘embryonic like’ does not mean that they are embryonic stem cells, it simply means that they carry some of the surface antigens seen on embryonic stem cells.12 These hVSEL stem cells may be quiescent in normal physiology or may be the ultimate source of all other stem cell types in normal homeostasis.13 It has also been shown that hVSEL are mobilised during disease or injury and may be contributing to tissue repair in these circumstances.14–15
The most exciting thing is that hVSEL can be easily obtained by taking a blood sample from the patient and preparing Platelet Rich
Plasma (PRP) which contains millions of hVSEL stem cells. These hVSEL stem cells in PRP can then be activated using modulated laser light to make them highly safe and effective autologous reparative stem cell technology.16 The mechanism of action of the modulated laser light on hVSEL stem cells is still to be fully defined but a mechanism has been proposed using the principles of Quantum Mechanics which is once again a first in stem cell technology.17 It has since been found that the modulated laser does in fact interact with other stem cell types most notable umbilical cord blood derived expanded MSC which have been shown to be extremely effective in the treatment of end stage heart failure.18 In the same study we reported the safety and efficacy of autologous laser activated hVSEL stem cells in the treatment of end-stage heart failure.
Much more work is needed on laser activated autologous hVSEL stem cells, but they represent an easy to obtain, cheap to process and potentially a safe and effective treatment for a wide range of pathologies. The impact alone on global heart disease could be massive and similar as yet unpublished results have been obtained in neurological disease, neurological trauma and type 2 diabetes. Since hVSEL stem cells are pluripotent they can not only repair stem cell numbers in any stem cell compartment but also repair the damaged or diseased stem cell niche.19 The stem cell technology needed to provide safe, effective and affordable treatments in the future needs to be identified and focussed on now. If we continue with confused, complex and expensive technology then regenerative medicine will have a very poor, if not non-existent, future.
REFERENCES
1. Edgar, L., Pu, T., Porter, B., Aziz, J.M., La Pointe, C., Asthana, A. & Orlando G. Regenerative medicine, organ bioengineering and transplantation. Br J Surg. 107(7), 793-800 (2020).
2. Simpson, E. & Dazzi, F. Bone Marrow Transplantation 1957-2019. Front Immunol.10, 1246 (2019).
3. Zakrzewski, W., Dobrzyński, M., Szymonowicz, M. & Rybak, Z. Stem cells: past, present, and future. Stem Cell Res Ther. 10(1), 68 (2019).
5. Mushahary, D., Spittler, A., Kasper, C., Weber, V. & Charwat, V. Isolation, cultivation, and characterization of human mesenchymal stem cells. Cytometry A. 93(1), 19-31 (2018).
6. Xie, Q., Liu, R., Jiang, J., Peng, J., Yang, C., Zhang, W., Wang, S. & Song, J. What is the impact of human umbilical cord mesenchymal stem cell transplantation on clinical treatment? Stem Cell Res Ther.11(1), 519 (2020).
7. Hollands, P., Aboyeji, D. & Orcharton, M. Dental pulp stem cells in regenerative medicine. Br Dent J. 1, 5-9 (2018).
8. Vazin, T. & Freed WJ. Human embryonic stem cells: derivation, culture, and differentiation: a review. Restor Neurol Neurosci. 28(4), 589-603 (2010).
9. Ohnuki, M. & Takahashi, K. Present and future challenges of induced pluripotent stem cells. Philos Trans R Soc Lond B Biol Sci. 370(1680), 20140367 (2015).
10. Ratajczak, M.Z., Zuba-Surma, E.K., Machalinski, B., Ratajczak, J. & Kucia, M. Very small embryonic-like (VSEL) stem cells: purification from adult
11. Kucia M, Machalinski B, Ratajczak MZ. The developmental deposition of epiblast/germ cell-line derived cells in various organs as a hypothetical explanation of stem cell plasticity? Acta Neurobiol Exp (Wars). 66(4), 331341 (2006).
12. Kucia M, Zub a-Surma EK, Wysoczynski M, Wu W, Ratajczak J, Machalinski B, Ratajczak MZ. Adult marrow-derived very small embryonic-like stem cells and tissue engineering. Expert Opin Biol Ther. 7(10), 1499-1514 (2007).
13. Ratajczak, M.Z., Zuba-Surma, E.K., Wysoczynski, M., Ratajczak, J., & Kucia, M. Very small embryonic-like stem cells: characterization, developmental origin, and biological significance. Experimental hematology, 36(6), 742–751. (2008).
14. Hénon, P. Key Success Factors for Regenerative Medicine in Acquired Heart Diseases. Stem Cell Rev Rep. 16(3), 441-458 (2020).
15. Ratajczak, J., Zuba-Surma, E., Paczkowska, E., Kucia, M., Nowacki, P. & Ratajczak, M.Z. Stem cells for neural regeneration--a potential application of very small embryonic-like stem cells. J Physiol Pharmacol. 62(1), 3-12 (2011).
16. Hollands, P., Aboyeji, D.R. & Ovokaitys, T. The action of modulated laser light on Human Very Small Embryonic-Like (hVSEL) stem cells in Platelet Rich Plasma (PRP) CellR4 8, e2990 (2020).
17. Brindley, J., Hollands, P. & Ovokaitys, T. A Theoretical Mechanism for the Action of SONG-Modulated Laser Light on Human Very Small Embryonic-
Like (hVSEL) Stem Cells in Platelet Rich Plasma (PRP) CellR4 9, e3201 (2021).
18. Ovokaitys, T., Paronyan, A., Hayrapetyan, H. & Hollands P. Intravenous SONG-modulated laser-activated allogeneic cord blood mesenchymal stem cells for the treatment of end-stage heart failure: a preliminary clinical study, CellR4 9, e3280 (2021).
Peter trained at Cambridge University under the supervision of the co-inventor of IVF and Nobel Laureate Professor Sir Bob Edwards FRS. He has worked in various IVF clinics in the UK, Canada and Nigeria and has held executive positions in several stem cell companies. Peter has written a book on stem cell technology called ‘The Regeneration Promise’. His second book ‘The Fertility Promise’ is an explanation of IVF and assisted reproduction.
Email: peterh63@hotmail.com
Challenges of Drug Development in Drug Resistant Focal Epilepsy
Epilepsy is one of the most common and disabling chronic neurologic disorder that affects more than 50 million people worldwide.1 Despite current of over two dozen antiepileptic drugs (AEDs), about one third of people with epilepsy fail to achieve complete freedom from seizures with existing medications employed alone or in various combinations. This phenomenon is known as a Drug Resistant Epilepsy (DRE) and represents a major challenge in epilepsy treatment.
Several clinical types of DRE have been recognised to date including resistance from the onset of seizure treatment (ab initio), delayed resistance (after an initial seizure-free period), and a fluctuating pattern where seizure-free periods alternate with resistant periods. Long-term outcome studies in newly treated patients with epilepsy suggest that after failure of two well-tolerated AED schedules appropriately chosen for the seizure type(s), the chance of success with further drug manipulation becomes progressively less likely,2 which supports the operational definition of DRE as a failure of two appropriately selected and tolerated AED regimens.3 Although clinical trials of novel investigational agents repeatedly demonstrate that 30% to 40% of treatment-resistant participants are likely to improve with each drug tried,4 it is essential for patients to achieve either a seizure-free status or non-drug resistant epilepsy status with long-term treatment (usually more than a year).
The strategy for assessing the effectiveness of AEDs has not substantially changed in the last 30 years. Typically, AEDs are tested initially as an adjunctive therapy in patients with treatmentresistant focal (partial) epilepsy. This patient population is studied initially because it comprises the largest population of adult patients with DRE, making trial enrolment more achievable. Adjunctive or “add-on” trial designs are utilised in early studies as Food and Drug Administration (FDA) guidance demanding that these studies demonstrate superiority.5 While it is much easier to demonstrate superiority when a placebo control is used than an active comparator, it would not be ethical to expose patients to prolonged monotherapy with an experimental agent.
Due to the accessibility of many efficacious AEDs, it has become increasingly difficult for investigators to enrol patients in novel AED trials.6 This is particularly true in high income countries, where specialised centres usually have access to the entire therapeutic armamentarium, and physicians and patients are understandably reluctant to participate in trials which require prolonged exposure to compounds with unproven efficacy. It is often easier for these potential trial participants to simply try the complete list of already available AEDs7 than to enrol in a study. These concerns have been further exacerbated by the finding that patients with refractory epilepsy randomised to placebo treatment in trials have a seven-fold increase in the risk of dying of sudden unexpected death in epilepsy (SUDEP) compared with patients randomised to active treatment.8 Faced with difficulties in enrolling sizeable number of patients in highly specialised centres, the pharmaceutical industry reacted by steadily enlarging the recruitment base through involvement of less experienced investigators and inclusion of study sites located in
geographical regions where availability of AEDs (or patient’s ability to afford expensive medications) is severely restricted.9
Of course, including less experienced investigators may adversely impact the quality of the trial conduct and negatively influence trial outcomes. Evidence from other therapeutic areas suggests that the recent shift toward large multi-site trials can also lead to an increase in response to placebo and to a decrease in effect size of active medications.10 It appears that a similar situation may be occurring in epilepsy trials as well.11 Indeed, systematic reviews have shown that placebo response in epilepsy trials has increased gradually over the years, together with a trend toward a decreased effect size for efficacious AEDs. Post-hoc analyses of data from recent AED trials also suggest that the ability to discriminate active medication from placebo may be related to geographical location of study sites and this ability may decrease drastically for sites located in regions that do not have a long-standing history of participation in AED trials.12 Considering this heightened placebo response in AED research, study protocols in DRE should attempt to systematically evaluate predictors of placebo response which include age of seizure onset, pre-study number of seizures, and history of AEDs used in treatment.13
The circumstances outlined above have important implications for drug development in epilepsy. On one hand, enrolling difficulties related to practical and ethical concerns with prolonged placebo exposure severely restrict the possibility of conducting trials at sites possessing the optimal expertise/experience. On the other hand, extending recruitment to less experienced study sites can reduce the effect size and weaken the ability to differentiate active treatments from placebo.7 To date, the industry’s reaction to a decreased effect size has been to increase statistical power simply by enrolling larger number of patients through the involvement of additional sites, leading to a vicious circle that has only compounded the problem with the possible unintended effect of increasing the overall failure rate of epilepsy trials.5
DRE Study Design
Traditional study designs to evaluate AEDs in DRE usually require that patients be on a stable background treatment with one to three AEDs, have a seizure frequency of at least three to four focal seizures per month (but not weekly frequency), and no 21 to 28-day period of being seizure free. A retrospective screening phase can be used to determine the patient’s refractory status, followed by a prospective baseline evaluation during which baseline AEDs are held constant and the patient’s seizure diaries are kept. This phase should be of sufficient length to detect any fluctuations in seizure frequency (usually 8 to 12 weeks). Shorter baseline periods (i.e., 8 weeks) are preferred, as longer ones can hamper patient recruitment. The minimum exposure period in traditional randomised double-blind trial designs accepted by regulatory agencies is 12 weeks. The proper training of patients and their caregivers who will record seizures in the diary is crucial for study success. Investigators should explore the exact phenotype(s) of the seizures and make sure that patients or caregivers are recording seizures and not adverse events.
The outcome of interest for most therapeutic trials of AEDs is usually based on seizure frequency. This is typically specified as
median seizure reduction from baseline, or the number of subjects with a greater than 50% seizure reduction or both; preferences vary depending on the regulatory agency. While this outcome is obviously clinically relevant, it is notoriously difficult to measure reliably.14 In epilepsy trials, subjects are asked to complete seizure diaries often using paper calendars in which they note the date of their seizure and as well as the type of seizure they had. However, it is well known that patients with epilepsy are often not reliable reporters of their seizures. In a study of patients on an epilepsy monitoring unit which permitted observation and objective confirmation of seizure activity, only 26% of subjects reported being aware of all their seizures and 30% of subjects recalled none of their seizures.15 Even when subjects are aware of the seizure, they may fail to record this contemporaneously and diaries are often not completed in real time. The diary may not be available at the time of the seizure or in many cases the postictal state may be prolonged preventing accurate and timely recording.
Although a single study in subjects with epilepsy has noted good reliability of a paper diary compared with random subject interviews,16 studies in other fields have demonstrated very poor compliance with daily diary completion.17 Backfilling or the retroactive completion of the diary just prior to the study visit is a common practice and can lead to inaccurate recollection of seizure frequency and type. It is also not clear that subjects can reliably distinguish among their seizure types. In clinical practice, it is common that subjects mistake focal motor seizures with impaired awareness (previously known as a complex partial seizure) for non-motor seizures with preserved awareness (previously known as a simple partial seizure) because they are amnestic for part of the seizure. This phenomenon has significant implications for the accuracy of reported outcomes in clinical trials. Therefore, a reduction in seizure severity (e.g., from motor to non-motor) can be missed because subjects are unable to distinguish seizure types accurately and reliably. Tonic-clinic seizures are less likely to be misidentified or forgotten because they are less frequent and often associated with characteristic signs, such as muscle soreness or tongue biting, that are more obvious to the patient even if they are amnestic for the event.
Time to Event Designs
As noted above, traditional randomised placebo-controlled add-on designs that have been the mainstay for the clinical development of AEDs for decades are now facing major implementation difficulties which include both the ethical and practical concerns with exposing patients to placebo or ineffective treatments for prolonged periods of time (typically 12 to 24 weeks).7 One attractive approach which can circumvent these concerns involves the use of a time-to-event design whereby patients are required to exit the trial after a predetermined but not excessive number of seizures has occurred.18 In this paradigm, patients who receive a drug which reduces the frequency of their seizures will remain on treatment for longer periods of time compared with patients randomised to placebo, and the time elapsed before meeting exit criteria can be used as an efficacy endpoint.9 These time-to-event designs have been used before in epilepsy studies, mostly in clinical trials designed to assess conversion to monotherapy.19 Its application to adjunctive trials would be especially attractive to patients because only trial participants who show a beneficial response are required to remain on double-blind treatment for a prolonged period of time. The validity of this design has been demonstrated in three randomised double-blind placebo-controlled add-on trials of becampanel in adults with focal seizures.20 Using an endpoint of the time to return to pre-randomisation seizure count, a significant difference between perampanel and placebo was obtained for all focal seizures and
secondarily generalized tonic–clonic seizures. The time-to-event design is beleaguered by reduced retention of patients allocated to placebo which will not permit appropriate comparison of late-onset adverse events between study arms. In this case, a definition of a minimum duration of placebo exposure is warranted, as well as carefully planned extension studies after the double-blind phase is complete.
Conclusions
The efficiency of randomised controlled trials of AEDs can be improved not only by minimising trial duration, particularly for patients exposed to placebo, but also by reducing the number of patients needed to demonstrate efficacy.9 The latter goal can be best achieved by ensuring a large effect size, either by developing medications with higher expected efficacy and/or by increasing the accuracy and reliability of outcome measures (decreasing the variance). This is done by confirming accurate/contemporaneous ratings and assessments of seizure frequency and type, ensuring proper patient selection, and by refining the ability to identify beforehand those patients who are most likely to show a good response. The ongoing shift towards precision medicine or the development of treatments rationally designed to target wellcharacterised patient groups represents an important step in maximising effect size.21 There have been increased efforts to ensure that only the patients who have the disease of interest are enrolled in trials, and that these patients’ seizures are correctly counted. One method to ensure appropriate patient selection is by use of external individual patient review prior to randomisation.9 Optimising trial design features and using novel designs that will take advantage of the mechanisms of novel drugs with improved efficacy and tolerability profiles is essential to the approval of AEDs in DRE.
REFERENCES
1 World Health Organization 2022. https://www.who.int/news-room/factsheets/detail/epilepsy
2. Chen Z. et al. Treatment outcomes in patients with newly diagnosed epilepsy treated with established and new antiepileptic drugs: a 30-year longitudinal cohort study. JAMA Neurol 2018:75:279–286.
3. Kwan P et al. Definition of drug resistant epilepsy: consensus proposal by the ad hoc Task Force of the ILAE Commission on Therapeutic Strategies. Epilepsia 2010: 51:1069–1077
4. Rheims S. et al. Factors determining response to antiepileptic drugs in randomized controlled trials: a systematic review and meta-analysis. Epilepsia 2011;52:219–233
5. FDA guidelines for drug research in epilepsy. https://www.fda.gov/ media/71165/download
6. Friedman D et al. Clinical trials for therapeutic assessment of antiepileptic drugs in the 21st century: obstacles and solutions, Lancet Neurol. 2012:11: 827–834.
7. Perucca E. What clinical trial designs have been used to test antiepileptic drugs and do we need to change them? Epileptic Disord. 2012:14:124–131
8. Ryvlin P et al. Risk of sudden unexpected death in epilepsy in patients given adjunctive antiepileptic treatment for refractory seizures: a metaanalysis of placebo-controlled randomised trials, Lancet Neurol. 2011:10: 961–968
9. Franco V, et al. Challenges in the clinical development of new antiepileptic drugs. Pharmacologica Research. 2016:103:95-104.
10. Bridge JA et al. Placebo response in randomized controlled trials of antidepressants for pediatric major depressive disorder, Am. J. Psychiatry 166 (1) (2009) 42–49.
11. Rheims S et al. Factors determining response to antiepileptic drugs in randomized controlled trials: a systematic review and meta-analysis, Epilepsia 2011:52 219–233.
12. French JA et al. Efficacy and safety of extended-release oxcarbazepine (Oxtellar XR) as adjunctive therapy in patients with refractory partialonset seizures: a randomized controlled trial, Acta Neurol. Scand.
13. Schmidt D et al. Clinical features associated with placebo response in refractory focal epilepsy. Epilepsy and Behavior. 2013;17:393-398
14. Fisher RS et al. Seizure diaries for clinical research and practice: limitation and further prospects. Epilepsy Behav. 2012:24:304-10.
15. Blum DE et al. Patient’s awareness of seizures. Neurology 1996:47:260-4
16. Neugebauer R. Reliability of seizure diaries in adult epileptic patients. Neuroepidemiology 1989;8:228-33
17. Stone AA et al. Patient compliance with paper and electronic diaries. Control Clin Trials. 2003;24:182-99.
18. Pledger GW et al. Alternative analyses for antiepileptic drug trials, Epilepsy Res. 1993 (suppl 10) 167–174.
19. Perucca E. Designing clinical trials to assess antiepileptic drugs as monotherapy: difficulties and solutions, CNS Drugs 2008;22:917–938.
20. French JA. et al., Time to prerandomization monthly seizure count in perampanel trials: a novel epilepsy endpoint, Neurology 2015:84: 2014–2020.
21. EpiPM Consortiumn, A roadmap for precision medicine in the epilepsies, Lancet Neurology 2015;14: 1219–1228
Tomislav Babić
Tomislav Babić, MD, PhD is Vice President of Neuroscience Scientific Solution in Worldwide Clinical Trials Inc. He is board certified neurologist and clinical pharmacologist with particular interest in drug development of various neurodegenerative disorders. Author of more than 70 peer reviewed articles and books in neurodegenerative disorders and has been integral to the development of many approved drugs across a number of neurological conditions. His expertise has been widely noted in clinical neuroscience in both industry and academia for the past 30 years.
Transcriptome Analysis of Acute Myeloid Leukaemia Cells
Acute Myeloid Leukaemia (AML) is a blood cancer characterised by overproduction of immature white blood cells in the bone marrow. These proliferating immature cells cause disease by swamping the production of normal blood cells.
AML makes up about 1 percent of cancers, and is the second most common type of leukaemia diagnosed in adults and children. Relapse and chemotherapy resistance are the main challenges of AML care with 40 to 60 percent of adults and 30 to 40 percent of children relapsing within three years. Afterwards, relapsed patients often fail to respond to conventional chemo treatment. Together, this results in 5-year overall survival rates of only 28 percent for adults and 70 percent for children.
AML is thought to be caused by a combination of genetic alterations and aberrant gene expression patterns.
Over the last decade, genomic and transcriptomic studies into AML’s causes have helped improve risk classification and treatment options of the disease. But most of these transcriptomic studies have focused on gene expression signatures at diagnosis, with only a small number investigating differential expression in relapsed and primary resistant (R/PR) AML – and of these studies, most lacked detailed knowledge about underlying genetic alterations in the form of wholegenome sequencing or whole-exome sequencing data.
Dr. Linda Holmfeldt, Principal Investigator in the department of Immunology, Genetics and Pathology at Uppsala University in Sweden, has recently been using Qlucore Omics Explorer’s in transcriptomic studies to better understand the molecular characteristics of R/PR AML patients.
Holmfeldt’s group analyses molecular signatures in AML cancer cells using a combination of whole genome and/or exome sequencing, RNA sequencing, mass spectrometry analysis of the proteome as well as studies of the epigenome by DNA methylation microarrays. She and her team also employ machine learning to generate hypotheses around tumour progression and/or therapy resistance.
Using these methods, Holmfeldt and colleagues are helping to build a more complete picture of DNA and RNA alterations in AML tumour cells, as well as their protein composition. Long term, by identifying these changes, the group hopes more efficient treatment alternatives can be developed for high-risk R/PR AML patients.
In the past, finding sufficient samples from R/PR cases has been difficult, says Holmfeldt.
For the recent study (published in Blood Adv January 2022), her group was able to perform transcriptome-wide RNA sequencing on 70 relapsing or primary resistant AML patients (47 adult and 23 children) with known mutational background from samples held via Uppsala Biobank and Karolinska Institute Biobank, collected between 1995 and 2016.
There were 122 samples in all, comprising 43 samples collected at diagnosis and 73 at relapse, plus six primary resistance samples. CD34-expressing bone marrow cells from five healthy donors were used as a source of normal control RNA. The RNA-sequencing yielded an average of 41 million reads per sample. The composition of genomic alterations for all AML samples had previously been analysed via whole genome or whole exome sequencing. ('Genomic characterization of relapsed acute myeloid leukemia reveals novel putative therapeutic targets' by Svea Stratmann et al; Blood Adv (2021)).
Holmfeldt and her colleagues began by extracting DNA, RNA, and protein to understand which alterations might be leukaemia-specific.
“We started out looking at the RNA transcriptome, tracking back to mutations at the DNA level,” says Holmfeldt. “Around that time, our bio-informaticist left! We had a license for Qlucore Omics Explorer’s and had experimented with it, so it was the perfect time to try out the tool on our RNA-sequencing data.”
The group used Qlucore Omics Explorer for various types of analyses of RNA-seq data, as well as for generation of various figures used within the now published paper.
“To start with, we used Qlucore Omics Explorer for various preprocessing of the TMM-normalised [Trimmed Mean of the M-value] data, including adjusting the data for gene length, carrying out log2 transformation separately for each conducted analysis (including different sets of samples), as well as performing batch correction, “ says Holmfeldt.
“Thereafter, we used the software for differential gene expression analysis. We carried out PCA, hierarchical clustering analysis, generated t-SNE- and Volcano plots as well as Venn diagrams,” she added.
“When comparing AML samples collected at initial diagnosis with relapse samples from adult and paediatric cases, adults typically had around 400 statistically significant differently expressed genes between the two disease stages. Paediatric patients had around 200 differently expressed genes,” says Holmfeldt.
The group’s findings have revealed a number of novel or previously unappreciated differentially expressed genes associated with tumour progression in AML.
“Certain genes kept popping up in our analyses. Some proinflammatory ones [IL1R1 and GLI2, for example] were expressed at a much higher level in those patients who relapsed quicker. One gene inhibiting inflammation [ST18] was expressed at a much lower level, “ she explains.
Altogether, the researchers found six or so genes of specific interest including CR1, DPEP1, GLI2, IL1R1, and ST18. “Within these, we identified CR1 down-regulation and DPEP1 up-regulation as specific for relapse in AML both for adults and children,“ says Holmfeldt.
Qlucore Volcano plot showing down-regulated ST18 (inhibitor) and up- regulated IL1R1 and GLI2 (pro-inflammatory) in AML, associated with short event-free survival.
The finding regarding GLI2, IL1R1, and ST18 was a highly significant result as it matched data from two other cohorts. These were an independent adult AML cohort from TCGA (The Cancer Genome Atlas) and an independent paediatric AML cohort from TARGET (Therapeutically Applicable Research To Generate Effective Treatments). Both cohorts showed low ST18 levels as well as high GLI2 and IL1R1 levels being associated with shorter overall survival as well as shorter event-free survival.
Finally, machine learning–based and network-based analysis also identified overexpressed CD6 and downregulated INSR as highly co-predictive genes depicting important relapse-associated characteristics among adult patients with AML.
The findings highlight the importance of a tumour-promoting inflammatory environment in leukaemia progression, as indicated by several of the differentially expressed genes.
Holmfeldt says that it also looks as if there are factors that make the leukaemia cells proliferate at slower speeds. “Chemotherapy primarily targets cells that are proliferating fast. Cancer cells that are proliferating very slowly, go under the radar, which makes them less sensitive to chemotherapy,“ she explains.
“Treatment-wise, our data suggest that if you can inhibit proinflammatory pathways, it might make the chemotherapy work better and increase survival times. By doing this you could make the leukaemia cells more responsive to treatment by changing their environment.”
Together, this knowledge provides the foundation for novel personalised drug targets and has the potential to maximise the benefit of current treatments to improve cure rates in AML.
Sophisticated Analysis Without Bioinformatics Background
“Qlucore Omics Explorer is great because it allows users lacking a bioinformatics background to perform sophisticated analyses of large datasets, as well as to generate highly useful figures of publication quality,” says Holmfeldt.
For the next research project, the group will be using the same cohort at the proteome level. “We now have the transcriptomes from our entire AML cohort to use as a database to map our peptides to. We might be able to pick up novel leukaemia-specific peptides that come from regions previously thought to be untranslated, ” she adds.
“In parallel, we will analyse the proteomics data in Qlucore again to look at what proteins are around at diagnosis compared to relapse. We hope that our findings may be used as biomarkers or as targets for immunotherapy. For proteomics analysis, we are very lucky to have Qlucore.”
REFERENCE
1. Transcriptomic analysis reveals proinflammatory signatures associated with acute myeloid leukemia progression by Svea Stratmann et al; Blood Adv. (2022) 6 (1)
2. Genomic characterization of relapsed acute myeloid leukemia reveals novel putative therapeutic targets by Svea Stratmann et al; Blood Adv (2021) 5 (3)
Christine Evans-Pughe
Christine Evans-Pughe is a freelance science and technology writer whose work has featured in The Economist, The Guardian, The Independent, and BBC Focus as well as a wide variety of specialist journals. She was a regular feature writer for the UK's Institution of Engineering & Technology's award-winning Engineering & Technology magazine for over 15 years, and is co-founder of the website www.howandwhy.com.
The Surge of Digital Health Technologies Modernising Clinical Research
Using digital health technologies (DHTs) to generate digital endpoints adds significant value to the clinical trial process in a number of areas. Critical to success is ensuring that the right digital health transformation strategies are being implemented to really reap the benefits of the technologies now available. Here, Dr. Isaac R. Rodriguez-Chavez of ICON outlines the key considerations when developing these strategies.
The clinical trial landscape is changing fast with the increased adoption of modern trial approaches such as decentralised clinical trials (DCTs) and real-world evidence (RWE) enabled by DHTs. Over the last two years, the global COVID-19 pandemic has significantly shifted how clinical trials operate – we’ve increasingly witnessed some of the benefits of incorporating DHTs.
Against this backdrop, biotech and pharmaceutical companies are looking to transform their R&D approaches to improve efficiencies in bringing to market novel medical products and staying competitive. This has also been a factor in driving many companies to consider how best they can shift from traditional trial approaches to agile, participant-centric processes supported by DHTs and the use of their corresponding digital endpoints.
Incorporating these technologies into clinical research at every phase opens the possibility for reduced timelines and cost savings while increasing the accuracy of safety and efficacy evaluations of investigational medical products by assessing more holistically protocol-related health outcomes in trial participants. Innovative technology-supported clinical research also offers compelling opportunities to engage diverse populations in an unprecedented manner, a clear advantage to evaluating the effect of novel medicines in these populations. This is good news for the industry where a multitude of historical complexities and inefficiencies in medical product development has resulted in a declining return on investment.
However, the benefits of implementing a robust digital health strategy go further. Adopting increased digital approaches can also help with current challenges such as geographic barriers to participant engagement in clinical trials and extending the assessment of health-related outcomes beyond the bricks-andmortar, traditional clinical research sites. In fact, trials that include these technologies could potentially decrease the need for large participant sample sizes, ultimately leading to quicker decisions and shortened timelines.
Using DHTs also allows for the synthesis of RWE and the generation of digital biomarkers which could be more responsive to change, ultimately increasing the possibility of real-time decisionmaking and benefiting participants enrolled in RWE-based trials.
Finally, DHTs and a continuous data stream enable novel, agile trial designs such as DCTs – which are trials that reduce or eliminate in-person visits to traditional clinical research sites while maintaining remote safety oversight of participants by the investigator.
Barriers to Adoption
Notwithstanding these compelling benefits, there are some barriers to adoption to consider.
Internal silos – internal stakeholders can act as a barrier to the integration and use of DHTs. As with all clinical research, the engagement of key stakeholder groups across the research continuum is a critical success factor. An important function of DHT teams is to map key internal stakeholders. Bridging siloed teams starts with engaging with stakeholders early on and creating an operational matrix that brings key functions together based on common clinical research goals.
Regulatory concerns – there is emergence guidance with respect to the use of digital endpoints in trials. The lack of harmonised guidance and standardisation across countries and regulatory jurisdictions has led to cautionary usage of DHTs to generate digital endpoints in clinical research.
DHT selection – it is self-evident that the DHT selected for a trial needs to be fit-for-purpose, in that it supports the intended use in a specific population. In addition, some DHT vendors may not have a complete understanding of the necessary requirements for clinical research, for example, the need for robust data security and privacy processes.
Managing data to ensure integrity and quality – even though DHT selection is important, data management (i.e. initial data acquisition, curation, analysis, and generation of a report) is vital to the success of using DHTs in clinical trials and is a key consideration to regulators. When DHTs are selected and used in a trial without mapping out a data strategy and implementing it, sponsors will often find challenges in cleaning convoluted data, which can be a source of errors and escalating costs.
Strategy for Successful Implementation
So how can sponsors capitalise on the many benefits that DHTs can bring? Effective integration of fit-for-purpose DHTs into trial design, execution, and reporting requires a strategic end-to-end approach. At ICON, our DHT team, along with our participant-centred scientists have developed a framework to map the process from DHT selection, complying with verification, validation, usability and justification, to endpoint validation and final operational implementation in trials.
Prioritising the Trial Participant
The main focus of the framework is participant centricity and maps
the transition from digital sensor to digital endpoint validation. For success, sponsors need to shift their focus from asking how we can use DHTs in a clinical trial to asking why we are using DHTs.
Therefore, the first step in the framework is to take a participant-centred approach when considering trial objectives and design. Sponsors should select measures that are meaningful to participants. In some instances, endpoints may be focused on assessing improvement in everyday functioning, while in others, it will be about measuring stability or deterioration in a condition – how quickly, and by how much. In general, digital endpoints may measure a physiological biomarker, a behavioural outcome, a functional activity outcome, or a combination of parameters to create novel, composite digital endpoints.
Once sponsors understand which outcomes are meaningful to trial participants, they then can begin to identify and select the optimal measures to assess these endpoints. Outcome assessment to DHT selection includes considering:
• The trial design – for example, incorporating a DHT may allow for a greater number of participants and geographic diversity, or more frequent assessments than clinic visits would allow
• Accuracy in assessments by potentially improving an existing measurement approach
• The ability to measure in smaller increments
• Potential for a new measurement altogether, which would not be possible without DHTs
Typically, outcome assessments start with identifying those health parameters that are important to those individuals living with a specific disease, also known as meaningful health aspects (MHA).
Following this, sponsors will need to identify the specific measurement. At this stage, a digital physical activity monitor could be considered, in that it is likely to capture the evidence required.
At this point, it still needs to be validated for the specific context of use.
There are six main steps to a DHT selection – DHT identification, verification, validation, participant acceptance testing, technical usability and feasibility testing, and justification for using a particular DHT.
If one is considering using digital endpoints to support the regulatory approval of an investigational medical product, the same scientific principles that pertain to all assessments still prevail. Regardless of the source, clinically meaningful endpoints need to directly measure how a trial participant feels, functions, or survives. It is also important to think ahead to the interpretation of the data that the DHT provides in a trial; establishing meaningful change thresholds is a key requirement for each novel digital endpoint.
It is also essential to consider operations to ensure robust data collection. Overlooking operational excellence can severely jeopardise the endpoint. Sponsors will need to look at the end-toend process holistically and implement risk contingency and backup plans, including logistics, data management, DHT calibration and replacement services, participant engagement, compliance, and sites.
For logistics, considerations should include whether a trial is on a global or regional scale, in addition to country-specific issues such as adaptor or voltage requirements, DHT registrations, and language and translation requirements for participant-facing materials.
It is important to have an end-to-end approach to DHTs – from DHT selection to operational management, training, and participant engagement and compliance.
When looking at data management, before you begin to develop a statistical analysis plan, sponsors will need to determine how data will be aggregated, processed and curated. Further, sponsors will need to decide what constitutes a valid data set based on the stated objectives of a trial.
ICON Digital Health Technology Framework to Operationalise Excellence
Additionally, participants and trial staff will need training on DHT functioning to ensure proficiency and on how data will be shared (i.e. it is important to design and implement a communications plan). Sponsors will need to set up participants’ support services such as direct outreach, reminder apps and dedicated helpdesks to keep participants compliant and engaged. Regarding compliance, real-time compliance data is preferred, as connecting with trial participants and solving issues in real-time can save data before it may be lost.
Lastly, clinical research sites should be well equipped and prepared with firewalls, ample storage and technology support.
Digital Endpoints – From Supplementary to Primary DHTs are key enablers of DCTs providing new ways to gather data, while relieving stresses and burdens to trial participants. Clinical trial processes will become increasingly driven by large RWE datasets, interoperability, advanced computing power, and cloud storage with the potential to accelerate drug approvals.
As more DHTs enter the market and become increasingly integrated into clinical research, we will begin to witness a shift
from digital endpoints used as exploratory to primary endpoints. Sensor technology will advance, leading to a rise in clinical grade DHTs, increasing the quality and value of the data they provide, further spurring growth in the DHT market.
In summary, changes in clinical research are increasingly influenced by digital transformation strategies. Companies may take advantage of this surge in digital health transformation to ensure they are ready to capitalise on these benefits, both now and as DHTs become mainstream enablers of the clinical research enterprise.
Isaac R. Rodriguez-Chavez
Isaac R. Rodriguez-Chavez, Ph.D., M.H.Sc., M.Sc. Senior Vice President, Scientific and Clinical Affairs Head, Decentralised Clinical Trials and Digital Medicine Strategy Drug Development Solutions, ICON plc.
IPI
Peer Reviewed, IPI looks into the best practice in outsourcing management for the Pharmaceutical and BioPharmaceutical industry. www.international-pharma.com
JCS
Peer Reviewed, JCS provides you with the best practice guidelines for conducting global Clinical Trials. JCS is the specialist journal providing you with relevant articles which will help you to navigate emerging markets. www.journalforclinicalstudies.com
IAHJ
Peer Reviewed, IAHJ looks into the entire outsourcing management of the Veterinary Drug, Veterinary Devices & Animal Food Development Industry. www.international-animalhealth.com
www.journalforclinicalstudies.com
PHARMA’S DNA
Listen to industry experts on the latest in drug discovery, development, research, industry regulations and much more at Pharma,s DNA, the podcast channel by Senglobal Ltd., available on Sound Cloud, Spotify, iTunes and YouTube.
IBI
Peer reviewed, IBI provides the biopharmaceutical industry with practical advice on managing bioprocessing and technology, upstream and downstream processing, manufacturing, regulations, formulation, scale-up/technology transfer, drug delivery, analytical testing and more. www.international-biopharma.com
8 Steps Every Clinical Team Should Take to Find the Right Translation Partner
Choosing the right medical translation provider can help in-house regulatory and clinical departments and contract research organisations support strategic growth while controlling costs and minimising risk. In this practical guide to hiring a translation agency, we discuss eight key steps to take when choosing a vendor, ranging from assessing domain knowledge to managing liability and security.
It is a familiar scenario: the portfolio manager or project manager receives a call from an internal business unit or subsidiary. Management has approved a new trial concerning multiple sites and countries that they need the start-up team to manage. Translation will be required and the budget and timeline are limited. The clinical team sizes up their options and calls their trusted sites. Do they have a local contact they could use, and how much will it cost? Will the study follow the new CTR 536/2014 requirements and be submitted in the Clinical Trials Information System (CTIS)? Have all the necessary patents been requested?
Such a scenario can cause a sharp intake of breath for even those clinical departments with a well-managed network of local partners in place. The local site may not have the necessary skills to relay the trial documentation in plain language for instance. Alternatively, it may be cost prohibitive or unfeasible to use local sites to perform translations as local sites may still be charging by the hour. Furthermore, ‘translation’ may be far down the priority list in comparison with other activities required during the study.
There can be issues of consistency or quality too. Where work is scheduled as a one-off and under time or budget constraints, how can you be sure that the translations will be understood by trial subjects or accepted by regulators?
Clinical documents might not be scrutinised until they are needed most – for example, during the ICF review and signature stage. If quality is not assured early, there is a real risk that the sponsor will pay later either through additional costs, delays to the clinical trial or a risky misunderstanding by a trial subject.
When we talk about translating plain language summaries (PLS), the use of inadequate wording or approaches can also have
drastic consequences. Trial subjects and carers must understand the study requirements, the due diligence required to participate or the reasons why the drug may not have the desired effect. Lack of understanding may drive subjects away from participating in the study.
5 Reasons Clinical Documents Require Professional Translation Support
1. Domain Knowledge
Sourcing translations for global clinical trials starts with recruiting linguists with knowledge of the relevant market, therapeutic area, document types, audience and linguistic preferences. Oftentimes, clinical texts can be highly medical and these should not be entrusted to providers without domainspecific experience. Domain-experienced LSPs should be aware of, and help you adhere to, essential legislation like the EU Clinical Trial Regulation.
2. Local Knowledge
Established LSPs show awareness of local linguistic nuance, familiarity with diverse document types, appropriate register (scientific or lay), as well as the need for formal certification, legalisation or notarisation.
3. Certifications of Accuracy
Clinical documents require certification that translations have been accurately performed. Certification gives those parties that rely on the documents the added confidence that the translation has met the agreed standard.
4. The Right Language
To effectively manage global clinical trials, sponsors and CROs insist upon a diverse team of qualified linguists. Also essential are agile and ISO-audited recruitment processes allowing to scale at speed according to changing linguistic requirements.
5. Risk Mitigation
A company’s reputation can hinge on the quality of their translated materials. Errors and inaccuracies can increase regulatory hurdles, undermine a company's strategy or cause misunderstanding among trial subjects. In addition, having to find and correct errors introduces additional cost and takes time, meaning that both profit margins and schedules are negatively affected.
Application Note How to Hire a Translation Agency
Providing Consistency Across All Operations
Working with a Language Service Provider (LSP) that provides translations across all relevant medical fields, from clinical and pharmacovigilance to product registration and marketing helps to streamline the management of translation tasks and build consistency across all translated materials.
As sponsors and CROs know all too well, translating clinical texts is not the same as translating standard documents or training materials. The influence of non-specialist language coupled with insufficient knowledge of the therapeutic area introduces the risk of confusion among trial subjects or unwanted regulatory roadblocks.
As sponsors typically give each department the authority to choose their preferred language service providers, it’s common to rely on one LSP for clinical trials, another for corporate translations, another for marketing authorisation applications and another for patents, for example. While the technical expertise of the different providers is crucial in such scenarios, so too is the need to ensure security and quality across translations, and to set clear deadlines.
Using multiple translation suppliers can be not only timeconsuming and inefficient but also risks undermining efforts to achieve a consistent quality standard in a cost-effective manner.
LSPs, in contrast, prioritise translation consistency and quality. They combine in-house production management with global freelance linguistic talent to offer a single trusted resource for language services, adhering to tight timeframes and pre-set budgets. It is for these reasons that the emerging best practice among successful CROs is to unify traditionally disparate language requirements under one or two high-performing LSP.
Choosing the Right Provider: A Step-by-Step Guide
Today’s sponsors and CROs operate in an increasingly global marketplace. Within the Life Sciences especially there is a need for compliant and accurate translations no matter the target language. As the need for translation grows, so too do the risks and potential costs of getting it wrong. Avoid the potential pitfalls with our stepby-step guide to choosing a provider.
Step One: Identify Your Needs
It may seem obvious, but if your documentation is specific to the domain of clinical research then the LSP must have proven experience with the clinical trial process and a track record of accurately translating the relevant documentation.
An experienced LSP will not only help you identify and assess the documentation you need to translate, but also help you estimate a translation budget for your entire clinical trial.
Step Two: Chart the Workflow
Time is of the essence when setting up and recruiting subjects for a clinical trial or responding to adverse event reports. Understanding the translation requirements and outlining a tailored, semiautomated workflow early in the process is crucial. The agreed workflow can include back translation, linguistic validation, certification and also allow time for all of the necessary review and approval processes.
Step Three: Match Those Requirements with Providers
Does your LSP have the necessary domain knowledge, languages, and turnaround times that you and your clients need?
Not all LSPs specialise in Life Science translations, so it may be that your existing vendor struggles to provide end-to-end support across your entire industry. Rather than finding this out through quality issues, be open about the needs of all departments and seek out an LSP who is competent at unifying them.
Accurately translating your company’s message (whether clinical, regulatory, advertising or training, etc.) requires in-depth knowledge specific to each domain. For example, to translate an informed consent form (ICF) or a clinical trial summary, sponsors require a translator to be familiar with the therapeutic area as well as the language and culture of the region in which the trial is taking place.
As well as the idiosyncrasies of local languages, your chosen translation vendor needs awareness of specific glossaries such as medDRA where applicable. This will impact terminology choices and understanding by the target reader. Equally important is knowledge of any technical or scientific field or discipline covered by the text.
It is also appropriate and advisable to request references from any agency you consider working with. Do not hesitate to ask for references in your same field to ensure that the vendor has relevant previous experience.
Step Four: Consider Your Security, Confidentiality,
and Governance Requirements
No matter the content of your documents, your translation vendor should always have processes in place to ensure the security and protection of your confidential information both in transit and within their systems. Ideally, your chosen vendor should possess ISO certification and/or SOC 2 Type II security certificates. Be sure to discuss these issues in advance of sending content to your vendor.
Step Five: Make Sure You’re Covered
Initiate conversations about diverse translation requirements in your vendor selection process. Your vendor should carry public liability insurance at levels commensurate with the financial penalties that are commonplace in your area of specialisation. Request proof of coverage to ensure that you are protected against translation mistakes, negligence, and data breaches.
Step Six: Manage Costs
No one wants to deal with hidden charges and unexpected costs. Professional LSPs will always provide complimentary quotes that clearly detail all costs, often itemised by language. Any changes to the quoted costs should be communicated to you by your project manager for approval in advance of being added to an invoice.
Step Seven: Run a Test Translation
If time allows, run a test translation project with the providers you are considering. This will allow you to compare costs, turnaround times, and customer service across all of your potential vendors. Most LSPs will complete small sample translations (of 500 words or less) for free, but may charge for larger tests. If your budget allows, it is best to request test translations using at least 2,500-5,000 words of source content. This will give you the best sense of whether a vendor can meet your needs.
Step Eight: Extend the Partnership
Once you have successfully completed a test translation and selected a vendor, consider unifying the requirements of other teams in your company in order to benefit from synergies across
How to Hire a Translation Agency
departments. For example, BIG Language Solutions utilises various tools that help ensure consistency within documents and across multiple related projects by capturing and cataloging frequently used, specialised words and phrases that may be accessed during translation. BIG Language Solutions automates aspects of its workflow management to expedite the translation process where possible and deliver high quality translations in a timely fashion.
Why Hire a Translation Agency?
While many businesses operate globally, sometimes it can be hard to locate and enrol trial subjects across multiple sites/countries. Composed of various regulations and cultural perspectives, international regulatory systems are made up of a patchwork of different legislations, regulations, and directives, all with diverse and often inconsistent procedures, timeframes, and costs.
For in-house clinical and regulatory affairs departments to navigate this global landscape requires project management and language talent operating locally.
Traditionally, in-house teams have had no choice but to build a network of external advisors to meet their ever-changing needs. Meanwhile, language services providers have invested heavily in processes and technology to minimise cost and timelines without negatively impacting quality.
Outsourcing life science translations to a professional translation agency with local presence thus offers a quicker, more consistent, and more cost-conscious alternative to utilising unqualified, unreliable resources.
Global Reach, Local Expertise
BIG Language Solutions supports sponsors and CROs with fulfilling a wide range of translation requirements across diverse practice areas. Our expertise spans a wide range of disciplines in over 200 languages, and guarantees you the translation support you need to successfully operate global clinical trials.
Security First
We take a 360-degree approach to the translation process, looking at the bigger picture to extend security beyond our internal platform so that all touchpoints – people, processes, and technology – are fully secure. Our entire translation approach and IT infrastructure
are compliant with ISO standards 9001, 17001, and 27001 for quality, impartiality, and IT security, and we are SOC 2 Type II audited.
A Trusted Methodology
We follow a three-step quality process for every translation that we deliver. Our process ensures we deliver authoritative and accurate translations that support your success and help you mitigate unnecessary risk:
1. Expert Translation Done by a Qualified Professional
Each translation begins with an experienced linguist with an advanced degree in the subject matter. We require all linguists to pass a robust proficiency test that is overseen by our Medical Director who is a physician and professional translator. Less than 6% of candidates pass this initial stage. Those who do must complete evaluation to allow us to further assess their background, translation proficiency and industry expertise.
2. Independent Reviews
Unless otherwise agreed, every medical translation is revised by a second specialist translator.
3. Final Quality Assurance Review & Project Requirements Evaluation
Finally, QC checks are performed against your project brief and then a dedicated project manager packages and delivers the translation in accordance with your specific instructions.
DWL
DWL, A BIG Language Solutions Company is a global leader in medical translation services, providing specialised services across more than 300 languages. Drawing on 50+ years of experience, our united team of medical translation specialists provides prompt, secure, and cost-effective solutions to global pharmaceutical companies, CROs, universities, medical device companies and regulatory consultancies. Whether we're supporting global clinical trials, marketing authorisation applications or device registrations, our stringent quality assurance protocols ensure commercially sensitive data and documents are safeguarded and translated to the very highest standard. Contact us to discuss your medical translation needs.
BIO-Europe is back in person!
The 28th BIO-Europe will be held in Leipzig, Germany from October 24–26, 2002, to fulfil its pivotal role of bringing together the global biopharma community to accelerate dealmaking.
Over the years, BIO-Europe has become Europe’s flagship partnering event bringing together over 4,000 executives from biotech, pharma and finance companies from around the world. Your access to the entire life science ecosystem all under one roof. Be part of the 20,000+ one-to-one meetings that will take place at the event that will ultimately shape the future of our industry—one partnership at a time.
14 & 15 September 2022 | Geneva, Switzerland
The new event at the heart of European pharma dedicated to innovative packaging, drug delivery systems, CDMO/CMO and filling & assembling processes
New event designed to drive innovation for pharma and biopharma businesses
‘Connect in Pharma’ is the new event that will bring together key players in the pharma and biopharma production industry. The event will take place on 14 & 15 September 2022 at major exhibition space Palexpo Congress Centre, in the heart of the pharma and biopharma industry and conveniently located next to the Geneva airport.
Leading global events company Easyfairs say they are launching this new event after spotting a gap in the market.
FIND OUT MORE AND SECURE YOUR PLACE quote code 5017
Bringing Together Innovators
The event is designed to inspire collaboration and innovation between suppliers, specifiers and other influencers in four key areas of pharmaceutical production downstream from the molecule: packaging, medical devices, contract manufacturing (CMO/CDMO) and processing.
Visitors to Connect in Pharma can expect to discover a range of innovations that are changing the way drugs are brought to market. With new developments in the field, including personalised treatments and nanotechnology among others, even greater changes are expected in the near future.
Isabelle Levy-Dessart, WW Marketing Communication Associate Director at BD, said: “We believe that Connect in Pharma will be an exciting new force driving business and innovation in the pharma market, and we can’t wait to meet the whole market in Geneva.”
Heike Lang, Head of Marketing & Communications at Sanner GmbH, said:
“Connect in Pharma has the potential to become the top event for pharmaceutical packaging and for CDMOs in Europe. As one of the key players for primary packaging and medical devices, we want to be part of this development from the very start.”
Collaboration and Partnerships
The event is partnering with leading associations such as Biopole SA, Polepharma, Lyonbiopole, BioAlps, Swiss Biotech, Bionow in the UK and more.
Over 70 industry-leading suppliers and associations in the pharma and biopharma sector have already signed up to exhibit at the event, including Becton Dickinson SAS, Catalent, Uhlmann, Staubli Robotics, ARaymondlife, Essentra, Gerresheimer, IMA Automation, Körber AG, MARCHESINI GROUP SPA, Nextpharm, and Unither Pharmaceuticals, among others. A full list can be found at www.connectinpharma.com/ exhibitor/.
Stephanie Pellet, Marketing Manager at ARaymondlife, said the company was looking to showcase new injectable drugs and meet other companies. “We decided to join this new event because the pharmaceutical industry in Switzerland is a highly developed sector, from large corporations to small startups and research centres. This European-wide event is perfect in terms of the format and the time of year.”
Founding partners
Page
Page 5 Aptus Clinical
Page 38–39 Connect in Pharma (Easy Fairs)
Page 7 Ramus Medical Ltd
Page 33 Senglobal Ltd
Page 21 TOWER Cold Chain
Subscribe today at Email: info@senglobalcoms.com www.journalforclinicalstudies.com