Visionary HEALTHCARE Innovation, Leadership & Performance in 2026
Pg.28
EHR vs EMR: Key Differences, Similarities, and Which System Is Right for You
Pg.38
The Only Question That Builds a Legacy (While Everyone Else is Still Stuck Building a Website)
Pg.46
Why Smart Brands Never Sell—They Storytell (And Here’s How You Do It Right)
GREG BUCHERT Chief Executive Officer Makani Science
The Physician Who Sees What the ‘Best Healthcare System in the World’ Still Gets Wrong
EDITOR’S LETTER “Where Vision Meets the Vital Signs of Change” Dear Readers,
Healthcarehasalwaysneededmorethanscience.Ithasneededpeoplewhocanseethegap betweenwhatexistsandwhatispossible,andwhocarrythecourageandtheclaritytocloseit.
“VisionaryLeadersDrivingHealthcareInnovation,Leadership&Performancein2026”isa tributetoexactlythosekindsofpeople.Eachleaderfeaturedherehaslookedatabrokenor incompletepartofthehealthcareworldandchosennottowaitforsomeoneelsetofixit.Theyhave builtthings,ledteams,changedsystems,andheldthebeliefthatbettercareisnotaprivilegefor thefewbutarightforeveryone.Theirstoriesarenotaboutperfection.Theyareaboutpersistence, purpose,andthequietpowerofstayingintheworklongenoughfortheworktomeansomething.
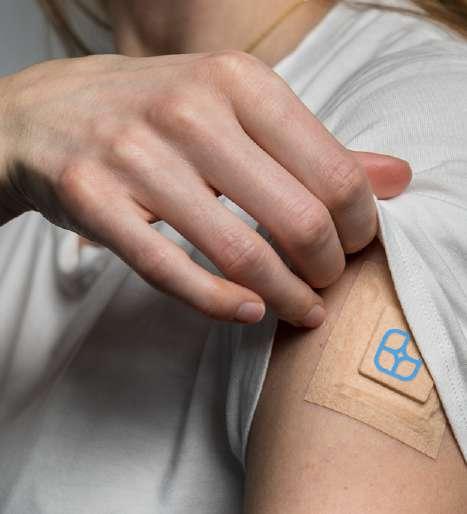
OurcoverstorythisissuebelongstoDr.GregBuchert,ChiefExecutiveOfficerofMakani Science.Heisaphysicianandasystemsthinkerwhohasspenthiscareermovingbetweenthe clinicandtheexecutivesuitewiththeconvictionthatbothare,attheirbest,thesamemission.His company,MakaniScience,isdevelopingabandage-sizedwirelessrespiratorymonitorbornfroma definingmomentinaneonatalintensivecareunit,whereamotherstoodbesidehernewbornson, surroundedbyeverytoolmodernmedicinehadtooffer,andstillcouldnotgetwhatsheneeded most.Dr.Buchertcarriesthatoriginstorynotasamarketingnarrativebutasamoralanchor.His careerhastakenhimthroughclinicalpractice,healthplanleadership,andmedicaldevice innovation,alwaysguidedbyoneorganizingprinciple:thathealthcaremustserveeveryone,not justthosewhocanaffordthebestofit.AtMakaniScience,heisbuildingthetechnologythatcould onedaytransformhowtheworldmonitorsbreathing,forprematureinfants,forambulatoryadults, andforthepopulationsthatinnovationhashistoricallyservedlast.
ThisissuealsobringsyouthevoicesandjourneysofKendellLeBray,DirectoratHealthCare ServiceCorporation(HCSC);RubenRathnasingham,AssistantDeanatDellMedicalSchool, UniversityofTexasatAustin;TimArgo,DirectoratChildren’sMinnesota;andJanHenk Hendriks,PresidentandChiefExecutiveOfficerofBiotts.Together,theyrepresentwhatitlooks liketoleadwithbothconvictionandcareinoneofthemostdemandingfieldsintheworld.
Sincerely,
SIMRAN KHAN Managing Editor
EDITOR-IN-CHIEF
MANAGING EDITOR
SIMRAN
PROJECT
SHADAB
PROJECT MANAGERS
NIKHIL MAHAJAN
AKASH PATIL
VISUALIZER
MARK DAVIS
GRAPHIC DESIGNER
HARSHADA MALI
AAKASH MAHAJAN HEAD
ROBERT SMITH
RESEARCH
JAMES ADAMS
ADVERTISING
MARIA SMITH
SALES CO-ORDINATOR
Peter Smith
Dr. Greg Buchert Cover Story GREG BUCHERT Physician Who Sees
Thereisaparticularkindofpersonwhowalksintoabroken roomand,ratherthanstandingtherecatalogingwhatis wrong,quietlyandmethodicallybeginstorearrangeit. Notoutofrestlessness.Notoutofego.Butoutofadeep, practicedconvictionthatthingscanandshouldwork betterthantheydo.Dr.GregBuchertisthatkindof person.
HeisaphysicianandaCEO,aboardmemberanda startupadvisor,ahealthcareconsultantwhohasspenthis careermovingbetweentheexaminingroomandthe executivesuitewiththeeaseofsomeonewhostopped seeingthemasseparateplacesaverylongtimeago.As ChiefExecutiveOfficerofMakaniScience,henow standsatthecenterofoneofthemorequietly consequentialhealthcaretechnologystoriesofthisdecade, astorythatbeginswithamotherinaneonatalintensive careunitandends,ifallgoesaccordingtoplan,witha transformationinhowtheworldmonitorsbreathing.
Dr.Buchert’swork,acrossclinicalpractice,healthplan leadership,andmedicaldeviceinnovation,isanimatedby asingleorganizingprinciple:thathealthcaremustserve everyone,notmerelythosefortunateenoughtoaffordthe bestofit.Inafieldwherethatconvictionisfarmore commonasastatedvaluethanasanoperationalreality,he hasspentdecadesmakingitpractical.
TheMakingofaSystemsThinker Dr.Buchert’spathintomedicinebeganwiththefamiliar ambitionofapre-medundergraduate.Butsomething shiftedearly,anditshiftedintherightdirection.
Heenrolledinwhatwouldturnouttobeagenuinely formativeexperience:theinauguralcertificateprogramat TuftsUniversity,titled “Community Health and Delivery of Health Services.” Itwas,byhisownaccount,anearly college-levelpublichealthcurriculum,anditwaswhere hefirstencounteredtheconceptofpopulationhealth,not theindividualpatientwithasinglediagnosis,butthe broaderandfarmorecomplicatedquestionofhowentire communitiesreceive,orfailtoreceive,thecaretheyneed.
ThatearlyintroductionledhimtotheTulaneSchoolof PublicHealthandTropicalMedicine,whereheearned anMPHinHealthAdministration.Betweenandbeyond thoseacademicchapters,heaccumulatedfrontline experiencesthatstretchedfromtheindividualtothe internationallevel,fromcommunityhealthsettingsto regionalsystemstoglobalhealthenvironments.
“I enjoyed front-line experiences at the individual, community, regional, and international level,” hehas reflected, “that drove me to take a systems-level approach to solving problems.”
Thatphrase,“systemslevel,”resurfacesthroughouthis careerwithakindofquietinsistence.Itisnota corporateaffectationoraresumeflourish.Itis,forDr. Buchert,agenuineorientation,ahabitofmindthatasks notonlywhatiswrongwiththispatient,butwhatis wrongwiththeconditionsthatmadethispatient vulnerableinthefirstplace.Itisthedifferencebetween treatingasymptomandredesigningasystem.
Itisalso,itturnsout,anextraordinarilyusefullens throughwhichtobuildahealthcaretechnology company.
ABirth,aCrisis,andtheBeginningofSomething New
MakaniSciencedidnotbegininaboardroomora strategysession.Itbeganinaneonatalintensivecare unit,intheparticularanguishofamotherwhocouldnot holdherson.
Dr.MichelleKhine,aProfessorofBiomedical Engineeringandaserialentrepreneurwithsixstartups alreadytohername,foundherselfstandingbesidea hospitalcribashernewbornsonstruggledwith respiratorydistress.Shewassurroundedbythefull machineryofmodernmedicine:monitors,wires,screens radiatingdata.
Andyet,forallofthattechnologicalsophistication,the “stateoftheart”respiratorymonitoringsystemsinthat unitfailedtodetectherson’scollapsedlung.
Therewasalsothematterofthewires.Atangle ofthem,connectinghersontothemachinesthatwere supposedtokeephimsafe,andkeepingherfromdoing theonethingamotherneedsmosttodo:pickhimup andholdhim.
Cover Story Cover Story Dr.Khinewasnotsomeonewhoabsorbedafailurelikethatand movedon.Shewassomeonewhosetaboutsolvingit.Asa biomedicalengineerwiththecapacitytointerrogateamedical problematthetechnicallevel,shebegantoaskwhethertherewasa betterwaytomonitorrespiration.ThatquestionbecameMakani Science.
Dr.Buchert,whoasCEOservesontheBoardofDirectors alongsideDr.Khine,carriesthatoriginstorynotasamarketing narrativebutasamoralanchor.EverydecisionaboutwhatMakani Sciencebuilds,andforwhom,isinsomesenseananswertothe questionofwhatthatmotherdeservedtohaveinthathospital room.
TheDeviceThatChangesEverything WhatMakaniSciencehasdevelopedis,initsphysicalform,almost deceptivelysimple.Abandage-sizedwirelessrespiratorymonitor.
Buttheimplicationsofwhatthatsmalldevicecandoareanything butsimple.
Themonitorissmallenoughtobeplacedonaprematureinfant, whichisnotaminorengineeringachievementinanysense.Itis comparabletothegoldstandardofspirometryinaccuracyand fasterthanpulseoximetryinitsmeasurements.Itsnovelstretch sensormakesitresistanttomotionartifacts,apersistentand frustratinglimitationoftraditionalrespiratorymonitoring technologythathaslongconfinedmeaningfulmonitoringto stationarypatientsinclinicalsettings.
I’ve never abandoned my role as one who should be doing everything in my power to help individuals obtain optimal care that will help them live their best life possible. ‘‘ Theresultissomethinggenuinelyunprecedented: the only respiratory monitor that can be worn 24 hours a day, seven days a week, by ambulatory individuals going about their ordinary lives.
AndwhatMakaniScienceisbuildingwiththedatathat flowsfromthosemonitorsisequallywithoutprecedent. Thecompanyisintheprocessofcreatingthefirst-of-itskinddatabaseofbreathingpatternwaveformsfor ambulatoryindividuals,aresourcethatclinicians, researchers,andpharmaceuticalcompanieshavenever hadaccessto,becausethetechnologytogenerateithas simplynotexisteduntilnow
Dr.Buchertdescribestheproductdevelopment philosophyintermsthatreflecthisbroaderapproachto healthcareasawhole:
“It is always important to start with identifying and defining the problem. Next is to understand the workflow of the provider and how a solution could be implemented. Finally, work on developing a solution that solves the problem in a realistic fashion and can be produced with an accessible price point.”
Accessible.Thatwordmatterstohimmorethanmost.It isnotincidentaltotheMakaniSciencemission.Itis inseparablefromit.
TheUncomfortableTruthAboutAmerican Healthcare
OneofthemoststrikingthingsaboutDr.Buchertiswhat heiswillingtosayoutloud,andtowhom.
AskhimabouthealthcareinnovationinAmerica,andhe willnotofferthereassurancesthatmanyinhisposition mightreachfor.Hewillnotsimplyendorsethefamiliar claimthattheUnitedStatesleadstheworldinmedical progress.Orrather,hewilltellyouwhatthatclaim consistentlyandconvenientlyleavesout.
“The United States has the best healthcare system in the world,” heacknowledges,whichisastatementmany peopleholdfirmly
“Admittedly, we do enjoy exposure to so many new technologies,” hesays,andthenarrivesatthepartofthe conversationthattendstomakeroomsgoquiet: “But it is important to point out some glaring truths to put that statement into perspective.”
Manyofthemostcelebratedmedicalinnovations,he notes,arerealisticallyavailableonlytothosewhocan affordthem.Thehighcostofsomeinnovations,with littledemonstrableimpactonlong-termoutcomes, displaceshealthcaredollarsthatcouldbenefit exponentiallymorepeople.Andthehealthoutcomesof theoverallUSpopulation,measuredagainstthoseof otherdevelopednations,remainacauseforserious concernratherthanself-congratulation.
Thisisnotpessimismfromamanwhohaslostfaithin thesystem.Itisprecisionfromamanwhohasworked insideitlongenoughtounderstandexactlywhereitis failing.Anditiswhatdriveshisinsistence,inevery ventureheundertakes,thatinnovationmustbedesigned withbroadaccessibilityinmindfromtheverybeginning, notawkwardlyretrofittedforwiderpopulationsafterthe commerciallyattractivemarkethasalreadybeenserved.
“In my work,” hesays, “I’ve done my best to ensure that innovations are available to as many individuals as possible.”
WhenLeadershipIsTested ThereisaparticularstoryfromDr.Buchert’scareerthat revealsmoreabouthischaracterthanalmostany credentialonhisprofessionalrecord.
HewasservingasDirectorofOutpatientServicesata Children’sHospitalthathadnointegratedEmergency Department.ThePediatricSpecialtyPhysicians, confrontedwithurgentcasesduringclinichours,would routethemtotheoutpatientclinic.Afterhours,thesame patients,manyofthemchildrencarryingcomplex medicalconditions,weresentreluctantlytothelocal emergencydepartment,whichwasnotdesignedor staffedtomeettheirparticularneeds.
Itwasasystemthatworkedforalmostnoone.Andit workedleastofallforthechildren.
Dr.Buchert’sresponsewasnottoescalatetheproblem upwardandwait.HehiredPediatricEmergency Physiciansfortheclinic.Hetemporarilyexpandedclinic operationstorun24hoursaday Andhewenttowork directlywiththelocalemergencydepartment, collaboratingonaredesignofitsfacility,itsprotocols, anditsstaffingconfigurationssothatchildrenwith complexmedicalissuescouldreceivegenuinely appropriatecareatanyhour
Eventually,theChildren’sHospitalbuiltitsown EmergencyDepartmentwhenanewtowerwas constructed.
Thedistancebetweenidentifyingaproblemand actuallysolvingitiswheremostorganizational failureslive.Itisalsowhereleadersprovewhat theyaremadeof.Dr.Buchertclosedthatdistance throughacombinationofpracticalaction, collaborativethinking,andarefusaltoacceptthat theexistingarrangementwasinevitable.
BuildingaModelWorthReplicating AnotherchapterinDr.Buchert’scareerspeaks directlytothoseworkingattheintersectionof healthcareaccessandhealthequity,a constituencythatincreasinglyincludesthelargest medicalcompaniesandhealthsystemsinthe world.
WorkinginacommunitywhereMedicaid beneficiarieshadseriousdifficultyaccessingcare, hebecameakeymemberoftheleadershipteam thatdesignedandlaunchedaMedicaidManaged CareHealthPlan,onebuiltonprinciplesthat were,atthetime,farfromstandardpracticeinthe field.
Theoutcomesweremeasurableand,byany objectivestandard,remarkable.Thenumberof providerswillingtoseeMedicaidmembersmore thandoubled.Theplanimprovedthequalityof care,loweredoverallcost,increasedprovider reimbursement,andremainedlocallyaccountable, acombinationthatisnotoriouslydifficultto achieveandalmostneverachievedallatonce.
Whathappenednextmaybethemosttelling indicatoroftheplan’srealsuccess.Itbecamea modelforbothRepublicanandDemocratic leaders,developingnewhealthcaredelivery strategies.
Inapoliticalenvironmentwherehealthcareis almostalwayscontestedterrain,building somethingthatearnsgenuinerespectacross partylinesisanachievementworthnoting carefully.Itsuggestsnotonlycompetencebuta clarityofpurposethattranscendstheusual ideologicalframing.
TheArtofBuildingHigh-PerformingTeams Dr.Buchert’sphilosophyonthepeoplehechoosestowork withis,initsway,ascarefullyconsideredashisapproachto healthcaresystemsdesign.
Heisnotonasearchforthemostcredentialedcandidates, thoughcredentialshavetheirplace.Whatheisconsistently lookingfor,acrossclinical,operational,andbusiness functions,issomethingthatdoesnotappearonarésuméin quitesolegibleaform.
“I always look for individuals with a ‘can-do’ attitude,” he says. “That characteristic associated with a respect for teamwork is a powerful combination that spans clinical, operational, and business functions.”
Itisadeceptivelycleanstandard.Butinpractice,itreflects asophisticatedunderstandingofhoworganizationsactually sustainperformance:notthroughthebrillianceoftheirmost individuallytalentedperformers,butthroughthecollective, sustainedeffortofpeoplewhobelievethatproblemscanbe solvedandwhoaregenuinelywillingtosolvethem together.
WhatComesNext TheimmediatehorizonforMakaniSciencecentersonthe launchofitsrespiratorymonitorforneonatalcare,adevice withthepotentialtorevolutionizethemanagementofbabies withrespiratory-associatedconditions,addressingthevery clinicalgapthatbroughtthecompanyintoexistence.
Beyondneonatalcare,theroadmapexpandsconsiderably. Dr.Buchertdescribesplanstoleveragethemonitor’s exceptionallysmallsizetoentermultipleadultmarkets, placingacomfortable,unobtrusivedeviceonambulatory individualswhocanwearitcontinuouslythroughthefull rhythmsofdailylife.
Thedatageneratedbythatnetworkofwearablemonitors willbeunlikeanythingcurrentlyavailabletothemedical community:aliving,accumulatingdatabaseofreal-world breathingpatterns,availabletocliniciansmakingtreatment decisions,researchersprobingthemechanismsof respiratorydisease,andpharmaceuticalcompanies developingandevaluatingnewtherapeuticapproaches.
Forinvestorsandmajormedicaldevicecompaniesassessing wherethenextdecadeofrespiratorymedicineisheading, thisisaspacethatrewardscloseandsustainedattention.
TheLifeBehindtheWork Foralltheprofessionalscopeofhiscareer,Dr.Buchertisquietly insistentononething:theworkhastocoexistwithalifethatis genuinelylived.
“I learned from experience that I must make time to exercise, spend time with my family, and enjoy a great meal with friends,” hesays. “The intermittent physical and mental escapes help me focus intensely on my work.”
Itisnotadramaticstatement,anditisnotmeanttobe.Itcarriesthe particularweightofsomethingarrivedatthroughhardexperience ratherthanborrowedfromawellnessframework.Heisnot describingalifestylephilosophy.Heisdescribingapracticethat keepshimfunctional,present,andcapableofthesustainedfocushis workdemands.
AdviceforThoseWhoFollow Whenaskedwhathewouldoffertoaspiringleadersinhealthcare, Dr.Buchertdoesnotreachforgranddeclarationsorpolished aphorisms.Heofferssomethingconsiderablymoredurable.
“Be a constant learner. Seize opportunities when they present themselves. Be humble and respect the value that every member of an organization contributes to the results. Engage in work activities that make a difference and benefit people.”
Fourdirectives.Eachoneisclear.Noneofthemiseasytosustain acrossanentirecareer.
Cover Story Theyarethevaluesofamanwhobeganhis professionallifeaskinghowhealthsystemscould servemorepeople,moreequitably,andmore effectively,andwhohasspentseveraldecades findinganswersthatarepractical,replicable,and genuinelyusefultothepeoplewhoneedthem most.
Dr.GregBuchertis,athiscore,aphysicianwho neverstoppedpracticingmedicine.Hesimply expandedhisdefinitionofwhatapatientcould be:fromasinglepersoninanexaminationroom, toacommunitywaitingforcare,toapopulation waitingforasystemthatfinallyworksthewayit should.
Theworkisnotfinished.Itmayneverbe finished.Butinthehandsofleaderslikehim,itis movingintherightdirection.
This new type of information will create an unprecedented database to be used by clinicians, researchers, and pharma companies. ‘‘ www.makaniscience.com
www.childrensmn.org
JAN HENK HENDRIKS Orchestrating
Synergies for Sustainable Pharma Growth President and Chief Executive Officer | Biotts
Jan Henk Hendriks JanHenkHendriksisaseasonedprofessionalwitha 28-yearcareer.Hestartedbyacquiringasolidscientific foundationbeforedelvingintobusiness,adoptingthe traditionalapproachthathebelievesisoptimalfor science-drivenenterprises.Jan’sexperienceincludes technicalrolesacrossvariousindustries,withapivotal entryintothepharmaceuticalrealmasaningredients supplier.Heevolvedwithinthepharmaceuticallandscape tobecomeanAPIsupplierand,now,atrailblazerin transdermalcarriertechnology.Ashenavigateddifferent sectors,Jan’srolesshiftedfromtechnicaltocommercial, accumulatingresponsibilities.
Janenteredthechemicalindustry,cateringtodiverse marketswithspecialtyingredientsandperformance additives,shapinghispathtothepharmaceuticalsector. Hevaluesthestabilityofthepharmaceuticalindustrywithitsemphasisoninnovation,science,andtechnologyalongwiththesatisfactionofcontributingtopatientwellbeing.Hefocusesonprovidingcutting-edgetransdermal carriertechnology,motivatedbytheopportunityto enhancetherapeuticsandfacilitatepatient-friendly deliveryoptions.Jan’scommitmenttoinnovationaligns withthepharmaceuticalindustry’sethos,whereresearch anddevelopmentdriveprogress.Hisultimaterewardisthe impactonpatients–curingdiseases,alleviating symptoms,orsimplifyingtreatmentprocesses.
StrategicLeadershipandMilestoneAchievements JanHenkHendriksisthePresidentandChiefExecutive OfficerofBiotts,aclinical-stagestart-up.Heensuresthe company’scontinuity,emphasizingfundraisinginitiatives tosecureresourcesforongoingoperations.Herecognizes theimportanceofhumancapitalandnurturesandleadsthe talentedindividualsinBiottswhodeliverscientific innovationforpatients.
Janalsotakesastrategicstanceonbuildingand positioningtheBiottsbrandinthepharmaceutical industry.Hetacklesthechallengesfacedbyinnovators, suchasconvincingstakeholdersthatwhatwas impossibleisnowpossible.Henavigatesthe conservativeenvironmentthroughstrategicpartnerships withindustryleaderslikeLaboratoiresServierand Bioton.ThesecollaborationsdemonstrateBiotts’ technologyappliedtoenhancemedicationsforpatients.
HisleadershipshowcasestheimpactofBiotts’ technology,asshownbyhiscollaborationwithBioton. Theinnovationprovidesanon-invasivealternativeto injections,offeringapatient-friendlyexperienceanda singleinsulinpatchinsteadofmultipleinjections.Jan believesthesesuccesseswillconvinceandinspirethe pharmaceuticalindustry
Additionally,JansupportedtheteaminsteeringBiotts throughamilestone–thefirstclinicaltrial.This achievementaffirmstheefficacyandsafetyofBiotts’ technologyinhumansandunderscoresthestart-up’s understandingofregulatoryrequirementsanditsability tobringinnovativesolutionstomarket.
PioneeringTransdermalCarrierTechnology Establishedin2018,Biottsisatrailblazingforceinthe pharmaceuticallandscape.Itdevelopeda groundbreakingtransdermalcarriertechnologythat enablesthedeliveryoflargermolecules,both hydrophilicandlipophilic.Biottsoffersanalternativeto injections,whicharestillusedforabout60%of medications.Itsalternativeiseffective,efficient,and morepatient-friendly
Thepharmaceuticalindustryhassoughtalternativesto injections,whichareunpleasant.Oraldosageformsare cost-effective,butsomemedicationscannotbedelivered orally,andothershavesideeffectsfrompassingthroughthe gastrointestinaltract.Biotts’technologyexpandstherange ofmoleculesthatcanbedeliveredtransdermally This approachhasadvantagessuchasaconstantandsustained effect,reducedadverseeffects,andapatient-friendly mechanism.Asafirststeptomarket,Biottsfocuseson peptidesandproteinsinDiabetes,asshownby collaborationswithsemaglutideandinsulin.Theseefforts showthecompany’scommitmenttoexploringtherapeutic opportunitiesforpatients.Biottschallengesthelimitations oftransdermaldeliveryandaimstobroadenitsapplication. Thecompany’strajectoryshowsitsdedicationtoinnovation andvisiontoreshapethepharmaceuticallandscapeby offeringenhancedoptionsthroughitstechnology
UnconventionalLeadership:EmbracingChangeand ChallengingPerceptions Janfaceduniquechallengesasaleaderbecauseofhis unconventionalapproachtoseekingnewopportunitiesand changingindustries.Somemightseehislackofindustry-specific experienceasadisadvantage,butJanseesitasanadvantage.He takestheroadlesstraveledandbringsafreshperspectivetoeach industry,approachingchallengesholistically.
OnechallengeJanfacedwastheperceptionofindustry-specific experience.Heovercametheinitialskepticismbyusing theadvantagesofafreshviewpoint.Heaskedfundamental questionsaboutthevaluecreatedbytheteam:Istheinnovation trulyunique?Doesitmakeapositivedifferencetocustomersor patients?Whatisthevalue,anddoesitresonatebeyondthe organization?Answeringthesequestionsfromanewperspective helpedJancutthroughcomplexitiesandclarifythevalueofthe productsorinnovations.
AnotherchallengeinJan’sjourneywasadaptingtochange.Jan stayednimbleandopen-mindedinthefaceofchanginglandscapes andnavigateduncertaintieseffectively.Hechangedindustries frequentlyandwasopentochangesandshiftsinthemarket. However,thisflexibilityrequiredadaptingtonewenvironments, dynamics,andcompetitors.
AligningTechnicalInnovationwithCommercialSuccess Biottshasahighlyskilled,motivated,andcreativeteamwithmany innovativeideas.Theteamhasevolvedtofocusontechnical innovationandcommercialsuccess.Janmotivatestheteamby focusingonopportunities,theimpactonpatients,progress milestones,andgoals.
Biotts’teamhasastrategicmindset,recognizingthatatechnical breakthroughmustimprovepatients’livesandbeaffordable.This approachreflectsasurgeinproductivityfortheteam.Theteamcan assessthecommercialviabilityoftechnicalinnovations,aligning withBiotts’commitmenttoimprovingpatients’lives.Moreover, theteam’sgrowthistechnicalandstrategic,reflectingan understandingofthemarketandtheimportanceofdeliveringvalue.
FosteringPatient-CentricInnovation Improvingpatients’livesisthefundamentalpurposeofthe pharmaceuticalindustry,andJanfocusesonthiscoremessage.It guideshismindset,emphasizingtheimpactofpharmaceutical innovationsonwell-being.HealsorecognizestheFDA’srolein publicsafetyandtheimportanceofearlyagreementonthe regulatorypathforBiotts’innovations.
“Today’s revenue comes from yesterday’s innovation and has a limited life cycle.” “We should constantly remind ourselves that not taking risks is a risk as well.” However,Jancollaborateswith regulatorybodiesliketheFDA,not justforcompliancebutforstrategy.He seeksearlyalignmenttoensure complianceandefficiencyinbringing innovationstomarket.Heunderstands thebalancebetweenpublicsafety andaccessiblemedicine,knowing thatlongdevelopmenttimesand highcostscouldlimitaccessand benefits.
Janalsoadvocatesacollaborative approach,emphasizingtheneedto simplifyprocessesandleverage synergies.Herecognizesthe importanceofimprovingregulationsto balancepatientsafety,innovation,and access.Hepointsouttherisksrelated toexclusivitythatcouldlimit life-changingmedications.
NavigatingTime,Costs,and Innovation Janaddressesthecomplexitiesof increasingtimelinesanddevelopment costsinthepharmaceuticalindustryby sustainingtheworkandinnovationat Biotts.Hebalancessafety,availability ofmedication,andinnovation, recognizingthedemandsofregulators andpeople.
Asastart-upwithlimitedresources,Biottsemphasizestimeto market,akeyfactorindecision-making.Janmeetsthechallengeof managingcostsandensuringabenefitfrominnovationsby improvingefficiencyandcost-effectiveness.HeleveragesBiotts’ platformtechnology,enhancingefficiencyandmaintaining momentumwithsynergiesbetweendevelopments.
Janalignsinnovationwithcostimprovementsandcapitalizeson synergieswithintheplatformtechnology,ensuringthatBiotts adaptsandstaysefficientintheevolvingpharmaceuticalindustry. Thisapproachhelpsthecompanynavigatechallengesand contributetoadvancementsinmedicationandpatientcare.
HarmonyinWorkandNature:Jan’sPursuitofBalance Janbalanceshisworkandnaturepassions,findingfulfillmentin both.Hetravelsfrequentlyforwork,buthecherisheshishomeand landinapicturesquelocation.Heretreatstothissanctuary,where heenjoysoutdooractivities,suchasmaintainingorchardsand breedingplantsandtrees.
TheconnectionwithnaturerejuvenatesJan,allowinghimtobuild andgrowthings.Heobtainshisownoliveoilfromthepressand shareshishomegrownfruitswiththeBiottsteam.Hefindsreward andfulfillmentintheoutcomesofhisefforts.
JanisdedicatedtohisjobatBiotts,buthealsoretreatstohishome andnature.Hebalanceshisprofessionalandpersonalpassions.His holisticapproachtoworkandlifeshowstheimportanceoffinding joyandsatisfactionindiversepursuits.Hecontributestoafulfilling andbalancedlifestyle.
NavigatingaMarathon:BuildingaLastingCareerinPharma Janadvisesaspiringpharmaprofessionalstohaveamarathon mindset,recognizingthatmakinganimpactintheindustryisa longjourney,notaquicksprint.Hecautionsthatprogressmaybe slow,giventhecomplexityofpharmaceuticalendeavors.
Heemphasizestheroleofinnovationandtheneedforcontinuous andcalculatedrisk-takingforsustainablebusinessgrowth.He arguesthatavoidingriskscanberisky,aspastinnovationshave limitedrevenuepotential.Cost-cuttingmeasurescanextendthis potential,buttruebusinessbuildingrequiresongoinginnovation. Heencouragesaspiringprofessionalstounderstandthatthe industryallowsforinnovation.Makinganimpactinvolvesaligning withtheindustry’sprinciplesandprioritizinginnovation.
Forthosepassionateaboutscience,innovation,andpatients’lives, Jansuggeststhatnavigatingthecomplexityandembracingriskare crucialforbuildingalastingandimpactfulcareerinpharma.
“If you are passionate about science and innovation, and you want to do good for patients in need you are denitely in the right place.” EHR vs EMR Key Differences, Similarities, and Which System Is Right for You Findingtherightdigitalrecordsystemcanfeellike
navigatingamazefilledwithtechnicaljargonand competingvendorclaims.Traditionally,medical practicesreliedonpaper-basedrecordsstoredinphysical folders,oftenconfinedwithinclinicwalls.However,like manyotherindustries,healthcarehasundergoneamajor digitaltransformation,adoptingelectronicsystemstoimprove carequality,streamlineworkflows,andreduceinefficiencies.
Today,theadoptionofelectronicrecordsystemsisnearly universalindevelopedhealthcaresystems.IntheUnited States,around95%ofoffice-basedphysiciansusesomeform ofdigitalrecordsystem,while96%ofacutecarehospitals relyoncertifiedtechnologiestomanagepatientdata.
Thiswidespreadshifthascreatedanextensivedigital ecosystemthatrequiresadvancedtoolstoensuredata remainsaccessible,accurate,andactionable.
AtthecoreofthistransformationareEMR(Electronic MedicalRecord)andEHR(ElectronicHealthRecord) systems.Whilebothhealthcaredatamanagementsystems, thedebatearoundEHRvsEMRlargelycentersonhow dataissharedandutilizedacrossdifferenthealthcare settings.
Despitetheirimportance,manyhealthcareprofessionalsare familiarwiththesetermsbutlackaclearunderstandingof theirfunctionaldifferences.
Asaresult,organizationssometimesinvestinEHRor EMRsoftwareforclinicsthatfailtoalignwiththeir long-termclinicalandoperationalgoals.
ChoosingbetweenEHRandEMRcansignificantly impacttheefficiencyandqualityofhealthcaredelivery However,distinguishingbetweenthetwoisnotalways straightforward.
Thiscomprehensiveguidewillhelpyoudifferentiate EHRvsEMRsystems,exploretheirbenefits,and evaluatetheirstrategicimplicationsinmodern healthcare.
TherightchoicebetweenEHRandEMRwillbenefityou inyourmedicaljourney
Let’sUnderstandTheEHRandEMRSystems WhatIsanEMR(ElectronicMedicalRecord)? Anelectronicmedicalrecordservesasthedigitalversion ofapatient’schartwithinasinglepractice.Cliniciansuse theEMRtooltotrackapatient’smedicalhistory, diagnoses,andtreatmentsovertime.Specifically,an EMRactsasalocalizedrepositoryforclinicaldata generatedduringvisitstothatspecificfacility.It improvesinternalefficiencybyallowingforfaster chartingandeasieraccesstopastvisitnotes.
WhereisEMRTechnologyUsedInHealthcare Small,independentpracticesthathandlespecific,internal caretasksoftenfindEMRssufficient.These organizationstypicallydonotrequireextensivereferrals orcoordinationwithlargehospitalnetworks.Fora specialistworkinginasoloenvironment,thelower complexityofanEMRmayofferafasterlearningcurve forstaff.However,ashealthcaremovestowardintegrated models,thesesoloEMRsarebecomingincreasinglyrare.
CoreFeaturesofEMRSystems EMRsoftwareprimarilysupportstheinternalclinical workflowofasmallofficeorsolopractitioner These systemsincludefeaturesforscheduling,documenting patientencounters,andmanagingprescriptionswithinthe office.
Theyallowdoctorstoidentifywhenpatientsareduefor screeningsorpreventivecarevaccinations.Additionally, EMRsstorelaboratoryresultsandimagingreportsthat thepracticeordersdirectly
LimitationsofElectronicMedicalRecordSystems ThedefininglimitationofanEMRisitslackofexternal interoperability Thesesystemsgenerallydonotsharedatawith otherhealthcareorganizationsorspecialists.
Consequently,ifapatientvisitsanemergencyroomora specialist,theirrecordstaysbehindintheprimaryEMR.
ProvidersusingEMRtechnologymustmanuallytransferthese filesviadigitalfaxorphysicalcopies.Thiscreates“datasilos” thathinderthecontinuityofcareacrossthebroaderhealthcare scale.
WhatIsanEHR(ElectronicHealthRecord)? Anelectronichealthrecordoffersamuchbroaderviewofa patient’stotalhealth.UnlikeanEMR,theEHRfollowsthe patientwherevertheygo.Itintegratesdatafromeveryprovider involvedinthepatient’scare,includingspecialists,laboratories, andimagingcenters.Thiscapabilityensuresthateveryclinician seesacomplete,longitudinalrecordofthepatient’smedical journey
Trueinteroperabilityallowsdifferentcomputersystemsand softwaretocommunicateandexchangedataaccurately.EHR systemsutilizestandardizedprotocolslikeHL7andFHIRto ensurethatinformationmovessecurelybetweenfacilities. Becauseofthis,ahospitalcaninstantlyaccessapatient’s primarycarerecordsduringanemergency Thisimmediate availabilityofinformationsignificantlyimprovespatientsafety andclinicaloutcomes.
FunctionsofEHRsystems EHRsystemsforhospitalsprovideasuiteoftoolsthatextend beyondsimpledocumentation.
● MostmodernEHRplatformsincludeintegratedpatient portals,telehealthmodules,anddigitalhealthtoolsforremote monitoring.Theyalsooffersophisticatedreportingand analyticsfeatures.Thesetoolsallowhealthsystemstotrack qualitymetricsandmanagepopulationhealtheffectively
● TheElectronicHealthRecordsystemssupportvalue-based caremodels Theyhelpprovidersmeettherequirementsof programsliketheMerit-basedIncentivePaymentSystem (MIPS).
● Bycapturingdataonpatientoutcomesandcarequality,these EHRsystemsensurethatpracticesreceivemaximum reimbursement Theyalsoautomatethesubmissionof requiredmetricstopayersandgovernmentagencies.
EHRvsEMR:DeepComparisonofCore Differences
WhilebothEHRandEMRdigitizeinformation,their impactonthepatientexperiencevariesgreatly Therefore,understandingthefunctionalgapsofEHR vsEMRisvital.
1. DataMobility AnEMRprovidesasnapshotofwhathappenedduring aspecificencounter.Incontrast,anEHRprovidesa completerecordofthepatient’smedicallife.This longitudinalviewallowsdoctorstoseepatternsthat theymightotherwisemissinasiloedenvironment.
Forexample,anEHRmightrevealthatthreedifferent specialistsprescribedmedicationsthatinteract dangerously AnEMR,lackingthatexternaldata, wouldnotflagtheconflict.
2. FinancialandOperationalScalability Asapracticeexpands,thelimitationsofanEMRoften becomeafinancialliability.Manualdataentryfor externalreferralsincreasesadministrativeoverhead andtheriskofbillingerrors.Ontheotherhand,EHR systemsautomatemanyoftheseprocesses.Integrated EHRplatformsoftenreportcleanerclaimratesand fasterpaymentcycles.
Healthcareadministratorsmustviewthehighercostof anEHRasaninvestmentindata-drivencareandlongtermviability.
3. SafetyandMedicationErrorReduction EHRsystemsprovidesuperiorpatientsafetycompared toEMRs.Specifically,EHRsincludeclinicaldecision supporttoolsthatcheckfordruginteractionsacrossall providers.Integratedsystemscanreduceprescribing errorsbyupto81%.EHRspreventunnecessaryrepeat testsbyshowingresultsfromexternallabs,reducing duplicatetesting.
SimilaritiesBetweenEHRandEMRSystems Despitetheirfunctionaldifferences,bothsystems representthedigitalfoundationofmodernmedicine. Theyshareseveralcorecharacteristicsthatimprovethe baselineofcareforallpatients.
1. ImprovingClinicalEfficiency BothEHRandEMRsystemseliminatetheneedtohuntfor physicalpapercharts.Clinicianscanaccessinformation instantlyfromanycomputerintheoffice.Thisspeed reduceswaittimesforpatientsandallowsstafftohandle largerpatientvolumesmoreeffectively.Bothplatformsalso utilizestandardizedtemplatestoensureconsistent documentationacrossthepractice.
2. EnhancingSecurityandPrivacyProtocols Digitalhealthrecordsofferfarsuperiorsecuritycompared topaperfiles.BothEHRandEMRsystemsincluderolebasedaccesscontrols.Thisensuresthatonlyauthorized personnelcanviewsensitivehealthinformation. Additionally,digitalsystemsmaintaindetailedauditlogs. Theselogstrackexactlywhoviewedarecordandwhat changestheymade,satisfyinghealthcaredatasecurity requirements.
3. SupportingResearchandQualityAnalysis Digitizingpatientinformationallowsforeasierdata extraction.Researchersandpracticemanagerscanrun reportstoidentifytrendsinchronicdiseasemanagement. Bothelectronicmedicalrecordandelectronichealthrecord systemssupportbasicclinicalresearchbyorganizingdata intosearchablefields.
ChallengesandLimitationsofEHRvsEMR Implementation Notechnologyisperfect,anddigitalrecordsystemscome withsignificanthurdles.Successfuladoptionrequires recognizingandplanningfortheseobstacles.
1. TheProblemofClinicianBurnout The“digitalpaperwork”requiredbythesesystemsisa leadingcauseofexhaustionamongdoctors.Manyproviders feelthatthesoftwareturnsthemintodataentryclerksrather thanhealers.Complicatedworkflowsandpoorlydesigned interfacescandoublethetimespentondocumentation.
2. SecurityVulnerabilitiesandCyberThreats Asmedicalrecordsmovetothecloud,theybecomeprime targetsforhackers.Ransomwareattacksonhealthcare systemshaveincreasedascybercriminalsseektolockdown sensitivedataforprofit. BothEHRandEMRsystemsrequireconstantmonitoring
EHR vs EMR: Comparison At Glance andfrequentsoftwareupdatestodefendagainstthesethreats. Smallpractices,inparticular,maylacktheresourcesto maintainhigh-levelcybersecuritydefenses.
3. ImplementationComplexityandDowntime TransitioningtoanEHRisamassiveorganizational undertaking.Itrequiresmeticulousdatamigration,staff training,andworkflowredesign.Duringthisperiod,practices oftenexperienceatemporarydipinproductivityandpatient volume.Furthermore,unplannedsystemoutagescan paralyzeaclinic,leavingdoctorswithoutaccesstovital patienthistory.
EHRvsEMRSystems:ChoosingTheBestforYour Organization Choosingthewrongsystemcancostapracticehundredsof thousandsofdollarsinlostproductivityandmissed reimbursements.Considerthesecriticalfactorsbefore signingavendorcontract.
1. YourPracticeSizeandScope Ifyourpracticeoperateswithinasinglebuildinganddoes notcoordinatecarewithexternalspecialists,asimpleEMR systemmightsuffice.However,ifyouhavemultiple locationsorworkwithinalargehospitalnetwork,anEHRis mandatory.Largehealthsystemsrequirethescalabilityand robustdata-sharingcapabilitiesthatonlyanEHRcan provide.
2. YourBudgetandCompliance Considerthetotalcostofownership,notjusttheinitial softwareprice.AnEHRoftenrequiresahigherinitial investmentbutprovidesbetterreturnoninvestment throughautomatedbillingandhigherclaimacceptance rates.Furthermore,ifyouparticipateingovernment programslikeMedicare,youmustuseacertifiedEHR toavoidfinancialpenalties.
EndNote ThedistinctionbetweenEHRvsEMRtechnologyisa fundamentaloneforthemodernhealthcaresector.While anelectronicmedicalrecorddigitizestheinternalchart ofasinglepractice,anelectronichealthrecordcreates aninteroperable,longitudinalrecordthatfollowsthe patientacrosstheentirecarejourney
Formostorganizations,theEHRistheclearchoicefor thefuture,offeringsuperiorpatientsafety,bettercare coordination,andimprovedfinancialoutcomes.
Healthcareprovidersmustchooseasystemthatnotonly meetstoday’sdocumentationneedsbutalsoprepares themforafutureofconnected,data-drivenmedicine.
Whetheryouareasolopractitionerorahospital administrator,understandingthesedifferencesis thefirststeptowardbuildingamoreefficientand effectivepractice.
Kendell LeBray The Healthcare Strategist Who Refuses to Leave Any Community Behind ThereisawordKendellLeBrayuseswithafrequencythat revealssomethingimportant:“access.”Heusesitwhenhetalks aboutruralcommunitieswherethenearestspecialistishours away.Heusesitwhenhedescribesunderservedneighborhoodswhere qualitycarehasneverbeenareliableexpectation.Heusesitwhenhetalks aboutthegapsinhealthcarethathavepersistedfordecadesdespitethe growthofanenormousandtechnicallysophisticatedindustryaroundthem.
Access,forKendell,isnotatalkingpoint.Itisthelensthroughwhichhe evaluateswhetheranyhealthcarestrategyisactuallyworththepaperitis writtenon.
TheWorkatHCSC HeisavisionaryhealthcareleaderatHealthCareServiceCorporation (HCSC),oneofthelargestcustomer-ownedhealthinsurersintheUnited States,operatingacrossmultiplestatehealthplans.Andoverthecourseof acareerthathasspannedHCSC,theAmericanMedicalAssociation,and anetworkofadvisoryboardsandleadershipcouncils,hehasbuiltarecord ofdoingthehardestthinginhealthcare:makingchangethatactually reachespeople.
“Real change happens when we blend visionary leadership, collaborative partnerships, and community-centered strategies to improve lives and expand access to quality care,” Kendellhassaid,andwhatisstriking aboutthesentenceisnotitsambition.Itistheword“real,”andthequiet insistenceitcarriesthatnotallchangecounts.
AtHealthCareServiceCorporation, Kendellhasledtransformative populationhealthinitiativesacrossthe organization’smulti-statereach, partneringwithexecutiveleadershipto shapestrategyandimprovehealth outcomesacrossmultiplestatehealth planssimultaneously.
Thisisworkthatoperatesatscalein bothsenses:thescaleofgeography, spanningstatesandcommunitieswith verydifferenthealthcarelandscapes, andthescaleofcomplexity,navigating theintersectionofclinicaloutcomes, memberengagement,payerstrategy, andcommunityhealthinrealtime.
Hehasdevelopedindustry-recognizedplatforms forevidence-basedknowledgesharing,creating systemsthroughwhichwhatworksinone communityoroneclinicalsettingcanbe identified,documented,andappliedelsewhere. Thisisthekindofinfrastructurethatrarelymakes headlines,butthatrepresentsoneofthemost durablecontributionsahealthcareleadercan make.
Hehasalsoexpandedaccesstocareinruraland underservedcommunities,acommitmentthat goesbeyondpolicylanguage.Ruralhealthcare accessisamongthemostpersistentandmost difficultproblemsinAmericanmedicine,shaped bygeography,economics,workforceshortages, andtheparticularkindofinstitutionalneglectthat comesfrommarketsthathaveneverfoundthe marginscompelling.
Kendellhasworkedinthatterrainwithbothstrategic sophisticationandgenuineurgency.Hehasalsoledprovider engagementeffortsthatsignificantlyimprovedcareutilization,a resultthatreflectsanunderstandingthataccessisonlymeaningful ifpeopleactuallyusethecareavailabletothem.Building pathwaysisnotenough.Thepathwayshavetobetraveled.
TheAmericanMedicalAssociationChapter
BeforehisworkatHCSC,Kendellbroughthisapproachtothe AmericanMedicalAssociation,wherehesteeredmulti-state coalitionsonchronicconditionprevention.
Chronicconditions,includingdiabetes,hypertension,heart disease,andobesity,accountforadisproportionateshareof healthcarecostsandhumansufferingintheUnitedStates,and theirpreventionrequiresthekindofsustained,coordinated, community-groundedinterventionthatisfarhardertoorganize thanitsounds.
Kendellorganizedit.Theresultsweremeasurable: increasesinclinicalreferralsandpatientparticipation acrossthecoalitionsheled,outcomesthatrepresent realpeoplemovingtowardcareratherthanawayfrom it.
Coalitionworkofthiskindisaspecificdiscipline.It requirestheabilitytoalignstakeholderswhose interestsarenotalwaysidentical,tomaintain momentumacrossorganizationsthatmoveatdifferent speeds,andtoholdasharedvisionclearlyenough thatitdoesnoterodeunderthepressureofcompeting priorities.Kendellhasdonethisacrossmultiplestates, inmultiplecommunities,withresultsthatholdup underscrutiny
APhilosophyofPartnership WhatrunsthrougheverychapterofKendell’scareer isafundamentalbeliefabouthowchangehappensin healthcare.Itdoesnothappenthroughanysingle organizationactingalone.Itdoesnothappenthrough top-downmandatesthatmissthespecificcharacterof localcommunities.Anditdoesnothappenthrough strategiesthatlookbrilliantonpaperbutfailto accountforthehumanrealitiesontheground.
“My guiding philosophy centers on bringing people together to overcome barriers and create sustainable impact across communities,” hesaid,andthe emphasison“sustainable”isdeliberate.
Healthcarehasalonghistoryofpilotsthatdonot scale,ofinitiativesthatproducepromisingshort-term resultsandthenevaporatewhenthefundingrunsout, orthechampionmoveson.Kendell’sorientationis towardthedurable:towardvalue-basedcare initiatives,towardplatformsthatoutlastanysingle person’stenure,towardpartnershipsbuilton alignmentdeepenoughtosurvivetheinevitable turbulence.
Hisexpertisespansmarketaccess,healthcare leadership,strategicpartnerships,andadvocacy,and acrossthesedomains,hehasledlarge-scale campaigns,value-basedcareinitiatives,product launches,andcommunityoutreacheffortswith measurablesuccess.Eachoftheserequiredadifferent setofskills,butallofthemrequiredthesame underlyingcommitment:tooutcomesthatarereal, andtothecommunitiestheyaremeanttoserve.
RecognitionandResponsibility Kendell’sworkhasbeenrecognizedbyModern Healthcareandbyleadingnationalorganizationsand prominentpublichealthagencies,honorsthatreflect thebreadthandtheconsistencyofhiscontributions. Healsoservesonadvisoryboardsandleadership councilscommittedtoequitablehealthoutcomes,roles thatextendhisinfluencebeyondanysingleinstitution.
Thiskindofrecognitionmattersnotsimplyasan accoladebutasanindicationofwherethefieldplaces him:amongthepeoplewhoseperspectiveon healthcareinnovationisconsideredworthseekingout, whosejudgmentondifficultquestionshasbeenearned throughtheworkitself.
Hebringsadeepunderstandingofmarketanalysis, brandmanagement,stakeholderengagement,andthe executionoftargetedmarketingandcommunication strategiestoeveryinitiativeheleads,abreadthof capabilitythatreflectstherealitythathealthcare changeisneversimplyaclinicalchallengeorsimplya strategicone.Itisalwaysboth.
LookingAhead Kendell’svisionforwhatcomesnextisconsistent witheverythingthathascomebefore.Heislookingto partnerwithorganizationscommittedtobreaking downaccessbarriers,innovatinghealthcaredelivery, andpromotingthewell-beingofallcommunities, languagethatsoundsaspirationaluntilyouunderstand thetrackrecordbehindit.
“My mission is to leverage my experience and network to drive even greater change,” hesaid,andfroma leaderwhohassteeredmulti-statecoalitions,built industry-recognizedplatforms,significantlyimproved careutilizationinunderservedcommunities,and earnedtherecognitionofsomeofthefield’smost respectedinstitutions,theword“greater”carriesreal weight.
Thecommunitiesthatstilllackreliableaccessto qualitycarearenotwaitingforaperfectstrategy They arewaitingforleaderswiththewill,theskill,andthe sustainedcommitmenttoclosethedistancebetween wherehealthcareisandwhereitneedstobe.Kendell LeBrayhasspentacareerclosingthatdistance.And heisnotdone.
THEONLYQUESTION THATBUILDSALEGACY (While Everyone Else is Still Stuck Building a Website) Let’sGetBrutalforaMinute.
You’renotconfused.
You’re avoiding the real question.
You’renotspinningincirclesbecauseyoudon’tknow howtobuildabrand.Orpriceyouroffers.Orwritethe perfectbiothatscreams“humblegenius.”
You’respinningbecauseyou’reaskingweak,generic questionsthatkeepyourpowerdiluted.You’vegotvisionboardglitterinyoureyesandyoucan’tseethedamnroad.
You’reasking:
· “WhatshouldIdo?”
· “WhatnicheshouldIpick?”
· “HowdoInotsoundtoobraggywhilealsosounding likeBeyoncé?”
You’rechasinganswerstoquestionsdesignedtokeep you small
NowI’mgoingtosaysomethingyourcoachwon’t. Thosearethequestionsthatamateursask.
Prosdon’task,“WhatshouldIdo?” Theyask,“WhatdoIwanttobeknownfor?”
Readthatagain.
ThatQuestionChangesEverything It’sthe power seat.Itdoesn’tcarewhat’strending.It doesn’tcarewhatyourcompetitor’scharging.It doesn’tneedaCanvatemplate.
Itasksyoutostandstillforonesecondand remember:You’renotheretofitin.You’rehereto own your lane.
Andnoonecanownanythingtheyhaven’t claimed. Sohere’sthetruthnoone’sputtingonInstagram: Ifyoucan’tanswer“whatdoIwanttobeknown for?”,thennothingelsematters.
Notthelogo.Notthepackages.NottheDMstrategy Notthethree-partemailfunnel.
Becauseifyoudon’tknow why yourworkmatters,whythe hellshouldanyoneelse?
Let’sTalkAboutYou.No,Seriously
You’vebuilt,orarebuilding,somethingthatmatters.That takesguts.Butsomewherealongtheway,youstopped buildingamovementandstartedbuildingabrochure.
Youoverthinkyourpositioning. Youwaterdownyourmessage.
Youwritecaptionsthatsoundlikeyouswallowedan inspirationalquotebookandpanickedhalfwaythrough.
Meanwhile,therealyou—theonewhohasstoriesthat couldchangelives,lessonsburnedintoherbones,anda truthonly you canspeak—iswaitingtobeinvitedtothe table.
Here’stheplottwist:Youarethedamntable.
LetMeAskYouThis:
· Whatdoyouknowfor sure aboutwhatyouoffer?
· Whatdopeoplesayaboutyouwhenyou’renotintheroom?
· Whatdoyou wish theysaid?
· Whatwouldyoufightfor,evenifnooneclapped?
Ifyoucananswerthat,youdon’tneedto“findyourniche.” Youaretheniche.
RealConfidenceIsn’tLoud.It’sClear Whenyouownwhatyou’reheretobeknownfor:
· Yourbiowritesitself.
· Yourcontentbecomesmagnetic.
· Yourpricingstopsfeelinglikeamathtestandstartsfeeling likeaboundary
· Youstopwaitingforpermissionandstartactinglikethe leaderyoualreadyare.
Youwalkintoroomsdifferently.Youpostdifferently. Hell,youwakeupdifferently.
Becausethisisn’taboutbeingperfect.It’saboutbeing undeniable
Here’sthe3-StepClarityDetox
(Ifyou’vebeenstuckin“I-don’tknow-what-to-say”land,thispart’sfor you.)
1.KilltheMediocreQuestions.
They’redeadweight.Stopasking, “WhatshouldIdo?”and“HowdoI lookcredible?”Askinstead:
· “What’sthestoryonlyIcantell?”
· “WhatamIalreadydoingthat peoplethankmefor?”
· “WhatimpactdoIwantmyname attachedto5yearsfromnow?”
2.ClaimYourCategoryofOne.
You’renotcompeting.You’recreating. You’renotheretofitthemold.You’re heretobreakit.Soask:
· “Whatpartofmyworkisnonnegotiable?”
· “WhatamItiredofapologizing for?”
· “WhatdoIdodifferentlywithout eventrying?”
3.SpeakFromThatPlace.Always.
Stopwritinglikeastranger.Stop diluting.Stopmarketinglikeyou’re askingsomeoneoutonadate.
Startsaying,“Here’sthework. Here’swhyitmatters.Ifit’sfor you,let’sgo.”
BeingtheAuthorityIsn’taTitle.It’s aDecision.
Youdon’tneed10,000followers.You don’tneedtolooklikeanadforForbes Women.Youdon’tneedtospeakon fivepanels.
Youneedtostopoutsourcingyour confidencetometricsthatdon’tmatter
Yournamebelongsinroomsyouhaven’tenteredyet—but onlyifyoustartusingyourvoicelikeithasadestination.
SoLet’sWrapThisUptheWayItStarted
Pullyourchaircloser
You’renot“figuringitout.”
You’re remembering who the hell you are.
You’reheretobuildsomethingbiggerthanabrand.
You’reheretobe known forsomethingthatoutlivesanysingle campaign,post,orlaunch.
Sostopwaitingto“haveitalltogether.”
Youalreadyknowwhatyoustandfor.
Nowmakeitundeniable.
FinalPrompt:WriteThisSomewhereBigandLoud
“WhatdoIwanttobeso wildly known for thattheysaymynameinroomsI'veneverevensteppedinto?”
That’stheonlyquestionworthanswering.
Andyou’vealreadygottheanswer.Startsayingitoutloud.
Rathnasingham Ruben The Healthcare Innovator Who Turned Academic Research Into 60X Returns ThereisanumberthatRubenRathnasingham mentions,andwhenyoufirsthearit,itdoes notquiteland.Sixty Asin60X,meaning sixtytimesthereturnoninnovationinvestments, generatedacrossacademicandindustrysettingsover thecourseofacareerspentturningresearchintoreality
Sixtytimes.
Inafieldwhereinvestmentreturnsaremeasuredagainst extraordinaryuncertainty,wheremostpromising discoveriesneverreachthemarket,andmoststartups neverreachscale,thatnumberisnotjustimpressive.It isthekindofresultthatmakesyouwanttounderstand howithappened.
RubenistheAssistantDeanatDellMedicalSchoolat theUniversityofTexasatAustin,andbeforethat,the formerAssociateDirectoratUCSF.The60Xreturnis onepieceofalargerstoryaboutwhatispossiblewhen someonebuildstherightinfrastructurearoundtheright mission.
“I lead strategic innovation initiatives that transform breakthrough research into market-ready solutions, generating exceptional returns while advancing patient care and community health,” hehassaid,andthe sentencecontainswithinitapairingthatisharderto achievethanitsounds:thefinancialandthehuman,the returnsandthepatients,heldtogetherratherthantraded againsteachother
APortfolioThatSpeaks ThemetricsofRuben’scareerformaportraitofsustained, deliberateimpact.Thereisa60Xreturnoninnovation investmentsacrossacademicandindustrysettings,a numberthatreflectsnotluckbutsystem-building.Thereis a4Xsurgeinintellectualpropertygenerationand protection,meaningthattheinstitutionsandcollaborators hehasworkedwitharenotjustproducingmoreideasbut protectingthembetter,creatingthelegalandcommercial infrastructureforthoseideastotravel.
Thereisa6Xincreaseinsuccessfullicensingagreements andstartupformations,afigurethatspeaksdirectlytothe thingthatmattersmostintechnologycommercialization: thetranslation,notjustthecreationofintellectualproperty, butitssuccessfulmovementintothemarket,intothehands ofcompaniesthatcancarryitforward.
Andthereisthe$60millionraisedacrossthreesuccessful healthcareventureexits,asumthatrepresentsnotjust financialreturnbutthevalidationofthreeseparatebetson threeseparatetechnologies,eachofwhichfoundenough commercialtractiontodeliveranoutcome.
Thesearenotsequentialaccomplishments.Theyarethe resultof50+strategicindustrypartnershipsspanninglife sciences,medtech,andhealthIT,anetworkof relationshipsbuiltoveryearsacrossmultipleinstitutions andmultiplesectors.
TheTexasHealthCatalyst AttheUniversityofTexasatAustin,Ruben hasdonesomethingthatgoesbeyond individualdeal-making.Hehasbuilta program.
TheTexasHealthCatalystandIndustry Partnershipprogramsaretheinfrastructure throughwhichresearchers,clinicians,and entrepreneursatUTAustinmovefromideato impact.Theseprogramssupporttheir participantsthroughanetworkofmorethan 350industryexperts,investors,and commercializationpartners,acommunity assembledspecificallytoclosethegapbetween academicdiscoveryandmarketdeployment.
Thatnumber,350ormore,isworthsittingwith foramoment.Buildinganetworkofthatscale, andmakingitfunctionalratherthanmerely largerequiresaspecifickindofleadership.It requiresknowingwhotherightpeopleare, earningtheirsustainedengagement,and creatingastructurethroughwhichtheir expertiseactuallyreachestheresearchersand clinicianswhoneedit.
Rubendesignedtheseprograms.Heleads them.Andtheresults,measuredinIP generation,licensingagreements,startup formations,andcapitalraised,speakdirectlyto whatawell-designedinnovationecosystemcan accomplish.Thisiswhatsystem-buildinglooks likeatitsbest:notasinglesuccessbuta platformformany
FromUCSFtoDellMedicalSchool Ruben’scareerhasmovedacrossinstitutionsin awaythatgiveshimanunusuallybroad perspectiveonhowacademicinnovation works,andwhereitgetsstuck.
AsformerAssociateDirectoratUCSF,one ofthecountry’spremierresearchuniversities andhealthsystems,hedevelopedadeep understandingofwhatworld-classresearch lookslikeinpractice,andwhatittakesto movethatresearchtowardclinicaland commercialapplication.
AtDellMedicalSchool,arelativelyyoung institutionwithadistinctlyentrepreneurial orientation,hehasbeenabletobuildmorefrom thegroundup,designingtheinnovation infrastructureratherthaninheritingit.
“I’ve built comprehensive innovation ecosystems that bridge world-class research with real-world clinical applications,” hehasnoted,andthe word“bridge”appearsinhisvocabularytheway precisetoolsappearinthehandsofsomeone whohaslearnedthroughexperiencewhat actuallyconnectsthings.
Hisapproachintegratesearlyclinicalvalidation withstrategicindustrypartnerships,ensuring thatinnovationsaretestedagainstgenuine healthcareneedsbeforetheyarebroughtto market.Thisisnotsimplyduediligence.Itisa philosophy:thatthecommercialviabilityofan innovationanditsclinicalvaluearenot competingconcernsbutmutuallyreinforcing ones.
AnUnusualJourney OneofthemostdistinctiveelementsofRuben’s backgroundisthatitdidnotbegininhealthcare atall.
Hismulti-sectorexperienceincludestimewith Schlumberger,theglobalenergyandtechnology company,workingonenergyinnovationsina domainascomplex,regulated,andtechnically demandingasmedicine.Thatbackgroundgives himaperspectiveontechnologytranslationthat isgenuinelyunusualinhealthcarecircles.
Hehasseenhowinnovationstravelthrough complex,regulatedindustriesmorebroadly,and hehaslearnedthatthefundamentalchallenges, thegapbetweendiscoveryanddeployment,the needforvalidatedproof,andtheimportanceof strategicpartnershiparenotspecifictomedicine.
Theyarethechallengesofanyfieldwherethe stakesarehigh,wherethepathfromideato impactislong,andwherethepeoplewho successfullynavigatethatpatharetheoneswho understandboththescienceandthesystem. Rubenunderstandsboth.
TheMissionBehindtheMetrics ItwouldbepossibletoreadRuben’scareer asastoryaboutreturnsanddealflow,about IPportfoliosandventureexits.Andthat storywouldbetrue.Butitwouldmissthe otherstory,theoneaboutwhythemetrics existinthefirstplace.
“Whether partnering with health systems, research institutions, or technology companies, I’m passionate about creating pathways that accelerate breakthrough innovations to market while delivering sustainable value for patients, communities, and stakeholders,” Rubenhassaid.
Thepatientandthecommunityarenotafterthoughtsinhisframing.Theyare thedestination.The60Xreturnoninvestment,the$60millionraised,the6X increaseinlicensingagreements:thesearenotends.Theyareevidencethat thepathisworking,thatinnovationsareactuallyreachingthepeoplewho needthem.
AtDellMedicalSchoolandacrossthebroaderUTAustinecosystem,Ruben hasbuiltamodelthatothersinacademicmedicinearewatchingclosely A modelthatdoesnotaskinnovatorstochoosebetweenfinancialreturnand patientimpactbutinsists,withconsiderableevidence,thatthetwobelong together Thatisthework.Andbyeveryavailablemeasure,itisworking.
Let’sgetonethingstraight—noonebuysyour product.Theybuytheirowntransformation.
That’sthepunchlinetoomanyentrepreneursmiss.If you’restillpitchingfeaturesorbraggingaboutyour process,you’releavingmoneyonthetable.
Thetruth?Peoplebuywhentheyfeellikethestory you’retellingsoundslike their story.Notyours.
Andthemostpowerfulwaytomakethathappenisby hijackingsomethingancient:TheHero’sJourney.
Thisisn’tatrend.Thisishumanpsychology.It’swhat ourbrainsdefaulttowhentryingtomakesenseoflife, change,orchallenges.Hollywoodknowsit. High-performingbrandsknowit.
Founderswhobuildcategory-definingstartupsknow it.
Let’sbreakdownhowyouembeditintoyourbrand messaginglikearealstrategist—notacontentcreator who’swingingit.
1.YourCustomerIstheHero.You’reJustthe Guide.AcceptIt.
Thisoneshiftwillcleanup80%ofyourmessaging clutter
Stoptryingtoconvinceyourcustomerhowsmart, qualified,orexperiencedyouare.Theydon’t care—yet.
Theycareaboutthemselves.Theirproblem.Their need.Theirconfusion.Theirdesiretostopthe bleeding.Soputthematthecenterofyourstory
You’renotthemaincharacter You rethepersonwhohelpsthemaincharacter win.
ThinkYoda.ThinkHaymitch.ThinkMoana’s grandmother They’retheoneswhonudgethe herooutoftheircomfortzone,handthemthe compass,andsay, “This way. I’ve walked this road. You're not alone.”
That’syourjob.
Sonexttimeyouwritecontent,don’tstart with, “I help women build soulful businesses.”
Startwiththis:
“You know that feeling when you’ve outgrown your business, but every pivot feels risky and wrong? Let’s fix that.”
Seethedifference?
2.TheProblemIsn’tJustaProblem—It’s theCalltoAdventure
Yourcustomer’sstuckmoment?That’swhere yourstory starts.
Notyouroriginstory.Notyour“why.”Theirs. Youneedtoarticulatethetensionthey feel—butcan’talwaysname.
Whendoneright,theyreadyourcontentand say, “Wait, how are you in my head?”
That’swhentheykeepscrolling.
Here’showyougetthatclarity:
· Lookatwhatyourbestclientssaidwhen theyhiredyou.
· CheckDMs.Emails.Exitsurveys.
· Payattentiontowheretheyalmostgave up.
· Usetheir actual words.Don’ttranslate themintobrandlanguage.
Example:
· Not: “I help burned-out professionals realign with purpose.”
· Try: “You thought quitting your job would feel like freedom. But now it’s 2PM, and you’re Googling how to price your service—again.”
That’sthecalltoadventure.
Makeitsovividtheyfeelslightly uncomfortablereadingit.That’swhenthe shiftstarts.
3.YouStepIn.NotWithHype—With Help.
Here’swheremostbrandsgowrong.They hear“guide”andthinkitmeans“guru.”
Nope.
Yourjobisn’ttosoundimpressive.It’sto offersomethingsolidtheycanuse today Somethingthatbuildstrustwithoutpressure.
Youofferawayforwardthatfeelssafe. Predictable.Testable.
Youbreakdownthenextstepsclearly.Like this:
“We map out your new messaging in 90 minutes. Then you try it out. We adjust what doesn’t land. You go live without overthinking it.”
That’saplan.
Youdon’tneedfireworks.Youneedstructure.
Shareasmallsuccessstory.Showproof.Bereal.Noneedforpolished perfection.That’snotwhatbuildsconversion.
Claritydoes.
4.ThenYouSelltheTransformation.NottheOffer.
Peopledon’tcareaboutyour6-weekprogram,yourgroupcalls,your templates.
Theycareaboutwhatchangesafterworkingwithyou. Sostoplistingdeliverableslikeamenu.Paintaclearbefore-and-after picture.
Makeitsogrounded,theycanvisualizethemselveslivingitnextweek.
Here’swhatthatsoundslike:
· Before: “I hate marketing. It feels fake. I never know what to post.” · After: “Now I write posts in 30 minutes flat—and people DM me saying, ‘This hit hard.’”
That’sreal.
You’reshowingthemthenewidentitywaitingontheothersideofthe work.
It’snotabout“6coachingcalls.”It’sabout“knowingwhattosaywhen someoneaskswhatyoudo.”
Sell that.
5.YouDon’tNeedaFunnel.YouNeedaNarrativeArc.
Let’sgetpractical.
ThisiswhattheHero’sJourneylookslikeinyourcontentecosystem:
Usethismap.Repeatit.Rotateitthroughyourchannels. Don’tjust“postvaluablecontent”—build narrative momentum.
6.IfYourBrandIsn’tSticky,YourStory’sNotSharp Enough
Mostpeopledon’tquityourcontentbecauseit’sbad. Theyquitbecauseit’svague.
You’renotnamingthetension.You’renotarticulatingthe shift.You’renotclosingtheloop.
Here’swhatfixesthat:
· Cut80%ofyouradjectives.Add20%moreverbs.
· Don’ttellpeopleyou’re“aligned.”Tellthemyou stoppedcryingonSundaynights.
· Don’tsayyouhelppeople“scale.”Sayyouhelped someonedoublerevenuewithoutdoublinghours.
Storystickswhenit moves.
7.LetTheirEndingBeYourBeginning
Here’sthebigone.
Whenpeopleseethemselvesinyourclients’wins,they self-select tostartthejourney
Sobuildyourcontentaroundtransformationsalready happening.
Documentyourclient’sfirstwins.Themessymiddle. Thesurpriseoutcomes.
Saythingslike:
· “Whenwestarted,Samwasn’tevensureshehadareal business.Today,shebookedoutQ3intwoweeks.”
· “Miratoldmeshefeltinvisible.Lastweek,shegother firstpressmention.”
Thesearen’ttestimonials.They’remini-herojourneys. Andtheyshowyouraudienceonething: This is possible for you, too.
NoOneBuysCoaching.OrCourses.OrSystems. Theybuybelief.
Beliefthat this time,they’llmakeitwork.Beliefthat someoneactuallyunderstandswhattheyneed.Beliefthat theywon’twastemoneyagain.
Storiesgivethemthatbelief.
Nothype.Nothacks.Nothigh-ticketurgencytactics. Stories.
Andnotjustanystory—astorywherethey win. That’stheonlypitchthatreallyworks.
FinalWord
Look.We’renotsellinglipstickhere.We’rebuildingtrust withpeoplewho’velikelybeenburnedbefore.Thattakes somethingdeeperthandopaminemarketing.
Ittakesnarrativestrategy
Soditchtheguruvibes.Stepintotheroleyou’reactually builtfor:thewomanwhoshowsupwithamap,amirror, andaflashlight.
You’renotsellingservices. You’resellingself-belief.
Getyourstorystraight—andwatchwhathappensnext.
Tim ARGO Thereisadistanceinsidemosthospitalsystemsthat
nobodyputsonamap.Itexistsbetweenthe momentaclinicianrecognizesaproblemandthe momentthatproblemactuallygetssolved.Aphysiciansees aninefficiencyinhowdataflowsbetweendepartments.A nursenoticesagapinhowpatientsaremonitoredathome.A therapistencounters abarriersopersistentitbeginstofeel immovable.Theseeinghappensconstantly,instinctively, almostreflexively.Whatalmostneverhappensnaturallyis solving.TimArgohasspenthiscareerstandinginthatgap.
HeisahealthcareinnovationleaderatChildren’s Minnesota,oneofthecountry’smostrespectedpediatric healthsystems,andhisworkisbuiltonararecombinationof capabilities:thelegalfluencytonegotiatelicensing agreements,thestrategicvisiontobuildlastingpartnerships, andthehumansensitivitytounderstandwhyanyofitmatters inthefirstplace.
“I am passionate about helping patients through bringing innovative technology into the clinic and to the market,” Tim hassaid,andthesentence’sdirectnessisnotasimplification. Itisaphilosophy.
TheCraftofCommercialization Intheworldofhealthcareinnovation,theword “commercialization”cansoundcold,asthoughitbelongs moretoaquarterlyearningscallthantoaconversationabout patientcare.Timusesitdifferently
Forhim,commercializationisthemechanismthrough whichagoodideabecomesarealtool,throughwhich aclinician’sinsightbecomessomethingapatientcan actuallybenefitfrom.
Hisexpertiseisspecificallyintechnologylicensing, partnerships,andinnovation,andoverthecourseof hiscareer,hehasnegotiatednumerouslicenses, collaborations,andpartnershipsthathavemoved technologiesfromconceptiontowardclinical deployment.
Eachofthesenegotiationsisitsowncomplex negotiation.Questionsofintellectualproperty, exclusivity,royalties,anddeploymentpathwaysdonot resolvethemselves.Theyrequiresomeonewho understandsthesciencewellenoughtospeakcredibly toresearchers,thebusinesswellenoughtospeak crediblytoexecutives,andtheregulatoryterrainwell enoughtoknowwherethelandminesareburied.
Timisthatperson.
Hisbackgroundasanexperiencedmedicalindustry professionalwithspecificexpertiseintechnology licensingmeansthathebringstoeverypartnership tableadepthofknowledgethatgoesbeyondgeneral businessacumen.Heunderstandstheparticular demandsofmovingmedicalinnovationthrougha systembuiltsimultaneouslyforrigorandurgency
DigitalHealthandtheNewTerrain Theemergenceofdigitalhealthasatransformative forceinmedicinehascreatedextraordinary opportunityand,simultaneously,extraordinary complexity.Remotemonitoringtools,telehealth platforms,AI-assisteddiagnostics,patient engagementsystems:thesetechnologiescarry enormouspromise,buttheydonotarriveinclinical settingsbyaccident.
Someonehastoevaluatethem,negotiatetheirentry, buildthepartnershipsthatsustaintheirdeployment, andensurethattheymeettheparticularstandardsof theinstitutionswheretheywillbeused.
AtChildren’sMinnesota,thosestandardsare especiallyhigh.Thepatientsarechildren.Everynew toolthatenterstheclinicalenvironmentcarrieswithit aweightthatisdifficulttooverstate,becausethe familieswhobringtheirchildrentoChildren’s Minnesotaaretrustingtheinstitutionwithsomething theycannotaffordtolose.
Timworkswithinthatweighteveryday.Itdoesnot paralyzehim.Itorientshim.
Hisworkinclinicalcommercializationanddigital healthreflectsanunderstandingthattechnologyin pediatriccareisnotsimplyaboutefficiency.Itis aboutcreatingsystemsthatworkreliably, compassionately,andsafelyinenvironmentswhere thestakesarealwayspersonal.
TheWorkofNewVentures Beyondhislicensingandpartnershipwork,Timis alsoengagedinnewventures,supportingthe developmentofcompaniesandsolutionsworkingto reimaginewhathealthcarecanlooklike.This entrepreneurialdimensionofhisworkaddsadifferent kindofenergyandperspectivetowhathedoes.
Healthsystemsandstartupsdonotalwaysspeakthe samelanguage.Astartup’surgency,itsneedtoiterate quickly,toraisecapital,toproveitselfbeforethe runwayrunsout,canfeelalientoinstitutionsbuilt aroundadifferentkindofclock.Andthecautionofa healthsystem,itscommitmenttosafetyand thoroughness,canfeellikeawallratherthan astandard.
Timservesasanadvisortobothhealthsystemsand startups,adualpositioningthatrequireshimtobe fluentinbothworldswithoutlosingsightofeither Heknowswhatahealthsystemneedstoseebefore itwillcommittoanewpartnership.Heknowswhat astartupneedstodemonstratebeforeaclinical environmentwillopenitsdoors.
Heis,inthetruestsenseoftheword,atranslator, helpingdifferentecosystemsunderstandeachother wellenoughtodosomethingneithercoulddoalone.
WhythePatientIsAlwaysthePoint Thereisaversionofinnovationworkinhealthcare thatlosesthepatientsomewhereinthemiddleofthe process,buriedundertermsheets,regulatory timelines,andIPportfolios.Timhasrefusedthat version.
Everynegotiation,everypartnership,everydigital healthsolutionbroughtintoclinicalpractice representsabetonsomeone’sbetteroutcome.A fasterdiagnosis.Amoreprecisetreatment.Amore connected,moreresponsiveexperienceofcare.
“I am passionate about helping patients through bringing innovative technology into the clinic and to the market,” Timhassaidmorethanonce,andthe repetitiondoesnotfeellikeatalkingpoint.Itfeels likeareminderhegiveshimselfasmuchasanyone else.
AtChildren’sMinnesota,thatremindertakeson particularmeaning.Thechildrenwhocomethrough thosedoors,andthefamilieswhocomewiththem, arenotabstractbeneficiariesofinnovation.Theyare thereasontheworkexists.
TimArgoknowsthat.Itshowsinhowheworks,in whatheprioritizes,andinthekindofleaderhehas chosentobe:steady,expert,andalwayspointed towardthepersonattheendofthecare.Innovation isonlyasmeaningfulasitsdestination.Timhas alwaysknownexactlywhereheisheaded.
USALEADERS THE BUILDING AMERICA