MAGA z INE f OR CUSTOMERS AND PARTNERS O f STRAUMANN 1 I 2012



MAGA z INE f OR CUSTOMERS AND PARTNERS O f STRAUMANN 1 I 2012
Imprint starget – magazine for Customers and Partners of straumann i © straumann usa i 60 minuteman road i andover, ma 01810 i Phone 800/448 8168 Fax 978/747 2490 i Editors roberto gonzález i mildred Loewen i E-Mail info.usa@straumann.com i Internet www.straumann.us/starget
Legal Notice exclusion of liability for articles by external authors: articles by external authors published in starget have been systematically assessed and carefully selected by the publisher of starget (straumann usa). such articles in every case reflect the opinion of the author(s) concerned and therefore do not necessarily coincide with the publisher’s opinion. nor does the publisher guarantee the completeness or accuracy and correctness of articles by external authors published in starget. the information given in clinical case descriptions, in particular, cannot replace a dental assessment by an appropriately qualified dental specialist in an individual case. any orientation to articles published in starget is therefore on the dentist’s responsibility. articles published in starget are protected by copyright and may not be reused, in full or in part, without the express consent of the publisher and the author(s) concerned. straumann® and all other trademarks and logos are registered trademarks of straumann usa and/or of its affiliates. third party corporate names and brand names that may be mentioned may be registered or otherwise protected marks even if this is not specially indicated. the absence of such an indication shall not therefore be interpreted as allowing such a name to be freely used.

Andy Molnar
Straumann Executive Vice President North America
Dear Valued Customer,
It is my pleasure to introduce myself as the new head of Straumann North America, and also to introduce this first installment of STARGET for 2012. The focus of this issue, "The Straumann Regenerative System," is particularly significant for me as I come to Straumann USA as the former Head of Straumann Global Regenerative Sales.
As you know, Straumann provides solutions for both tissue regeneration and GBR including Emdogain™, BoneCeramic™, Straumann AlloGraft, and most recently MembraGel ®, an innovative liquid membrane that can be precisely applied to the surgical site.
You’ll find several interesting articles on tissue regeneration in this issue of STARGET: “Why Repair When You Can Regenerate?“ on page 6, “Redefining the Membrane“ on page 12, and an interview with Prof. Dr. Christoph Hämmerle on the innovation and distinctiveness of MembraGel on page 16. You’ll also see an article on our Esthetic Case Book, which documents 11 cases illustrating the dramatic results that can be achieved through Emdogain, on page 18.
Restorative dentistry has seen breakthroughs over the past few years. This STARGET features articles on the latest development of Straumann CARES ® digital workflow. We hope you will enjoy the clinical case on Straumann's screw-retained hybrid solution from your peers, and an article based on the interviews with three key opinion leaders on global trends in dentistry.
Enjoy this issue of STARGET and please let us know how we can continue to improve upon it.
Sincerely,
Andy Molnar
Straumann Executive Vice President, North America

® regenerative SyS tem
Straumann, together with 3M™ ESPE™, has introduced a streamlined digital workflow that connects the Lava™ C.O.S. Intra-Oral Scanner to the Straumann® CARES® Digital Solutions platform.
The Straumann® Regenerative System offers solutions for oral tissue regeneration – ranging from conservative dentistry to dental restoration. New to the portfolio: Straumann® MembraGel®


Global Trends – Where is the final destination? We asked three prominent dentists to give us their perspective on things: Lyndon Cooper, Kenneth Malament and Daniel Wismeijer.
The biological process, or self-sufficient capability to restore deficient tissue is referred to as the ability for regeneration. In contrast to repair, i.e., wound healing, whereby the original biological structure is not fully rebuilt, the goal of regeneration is to completely restore the structure and function of tissue that has been lost or injured. This ability has continuously diminished as creatures have evolved and the complexity of these organisms has increased. Compared to the “champions” of regeneration, present day cnidarians, which can re-grow severed extremities and internal organs that have been lost, this capability in humans, without additional support, is limited to a few types of external tissue.
When a person’s tissue is injured, the body’s repair process, rather than regenerative process, begins. Here, the body does not primarily attempt to restore the original state and function of the tissue, but rather to close the wound as quickly as possible. This spontaneous healing process involves the formation of connective tissues that penetrate deeply into the original tissue and also remove “good” tissue in the process. During such a “radical” healing process, it is possible that even important functions are permanently destroyed.
To prevent this type of overcompensation in the healing process wherever possible, strong antiinflammatory drugs are administered today, such as in cases of back injuries. This prevents this destructive process from occurring, in turn making it possible to preserve part of the nerve tissue and mitigating deficits such as paralyses. In medical terms, regeneration entails assisting desirable tissue formation processes, and guiding and limiting the repair mechanisms involved in wound healing as to not impede the regeneration of intact, functioning tissue.
Fig. 1: The cnidarians (pictured here, a green anemone, anthopleura xanthogrammica) are equipped with astounding regenerative capabilities that far surpass those of humans.

Great advances in regeneration have been achieved in dentistry over that last 20 years. We can now regenerate the bone tissue of the jaw, opening the door for implants as a treatment for replacing teeth. This has required scientific evidence documenting the physiological processes involved in tissue formation and the necessary aids for controlling these processes. Today, for example, we know that lost or missing bone can only be regenerated by the body when the bone-forming cells can perform their work undisturbed. Without external intervention, this process would have to compete with the rapid natural wound repair mechanism, which would result in the growth of new connective tissue instead of the desired bone tissue.
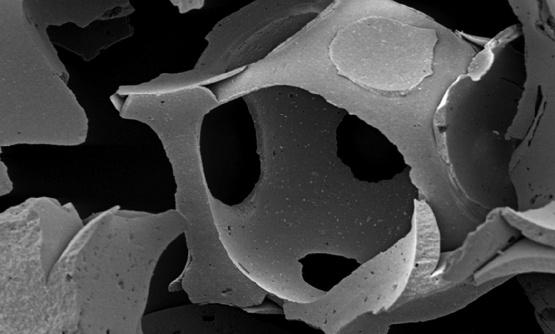
Today, one means of guiding the regeneration process requires two aids: a matrix and a membrane. The matrix keeps the space available for the bone to grow while a membrane serves as a barrier to prevent the connective tissue infiltration of the gingiva.
Various types of these matrices and membranes are used today for regenerative purposes. Some of these “placeholders” remain in the body, integrated into the newly formed bone for the rest of the person’s life. Applying membranes for this purpose is also quite complex and time-consuming. Straumann ® MembraGel ® was developed to deal with the disadvantages of the types of membranes used in the past. The time-consuming cutting and fitting of the membrane is unnecessary since MembraGel is applied in liquid form and polymerizes to form a solid film in less than a minute. The resulting hydrogel is biocompatible and completely biodegradable.
For implantology, the regeneration of the periodontium is equally as important as the new formation of bone, which is destroyed by periodontitis and can ultimately result in the loss of the tooth. Despite numerous attempts to regenerate the destroyed tissue, a breakthrough to achieve complete tissue reformation remains to be seen. Straumann ® Emdogain™ can be used in cases to undo some of this destruction, making it possible to prevent loss of the tooth. Emdogain contains the key components required for building up the cementum and periodontal ligament, important parts of the periodontium.
These elements, or proteins, tap into the body’s own natural ability to rebuild the surrounding tooth structures, using nature’s help.
Straumann’s successes in the field of regeneration are promising and we have yet to fully realize our dreams. We are already working on further innovations to guide regenerative processes in an even simpler and more effective manner. We are inspired by two great visions:
» A matrix for bone augmentation that breaks down fully and can be used without requiring a membrane.
» Guided tissue regeneration that allows for complete preservation of the tooth.
Now making its first entrance into the dental market with Straumann MembraGel, we view PEG technology as the foundation for achieving these goals. Beyond MembraGel, there are numerous combinations and degrees of cross-linking these biocompatible hydrogels, which present an exciting range of possible options. This innovative technology is only in the early phases of trials and development and has enormous potential for the future.
The Straumann ® Regenerative System: Everything from a
The Straumann ® Regenerative System offers you a variety of solutions for oral tissue regeneration –ranging from conservative dentistry to dental restoration. Our goal is to offer you a variety of predictable and scientifically proven regenerative treatment solutions – all from a single source and in the tried and tested quality that is Straumann’s hallmark.
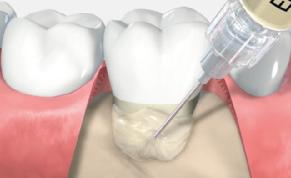
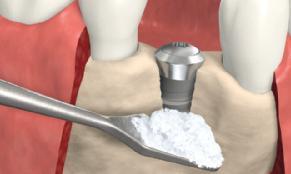
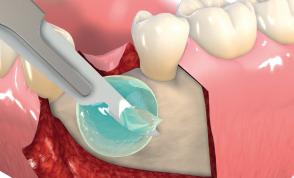
By mimicking the natural process of odontosis, Straumann® emdogain forms an insoluble, three-dimensional extracellular matrix that remains on the root surface for 2 – 4 weeks and enables a selective cell population, proliferation and differentiation.
Straumann® a llo g raft is a wide range of bone allograft solutions, allowing you the flexibility to choose the treatment that’s right for your case. Through a commercial partnership with LifeNet Health ®, Straumann’s allograft options provide confidence in the safety of the material you use to treat your patients.
Straumann® BoneCeramic™ is a fully synthetic bone substitute material with excellent morphology that promotes the new formation of vital bone. It can be used for a series of procedures used for dental bone regeneration.
Straumann® m embra g el ® is a membrane of the latest generation. It combines unique material properties that have been developed to promote undisturbed bone healing and to simplify the surgical procedure.

More than 100 clinical publications in peer-reviewed journals demonstrate Straumann® Emdogain to be safe and effective in stimulating the formation of new periodontal soft and hard tissue. These clinical studies involve more than 3000 defects in over 2500 patients.
Contact Straumann Customer Service at 800/448 8168 to learn more about Straumann solutions or to locate a representative in your area. www.straumann.us


1 Tonetti MS, et al. Enamel matrix proteins in the regenerative therapy of deep intrabony defects. J Periodontol. 2002;29:317–325.
2 Froum SJ, et al. A comparative study utilizing open flap debridement with and without enamel matrix derivative in the treatment of periodontal intrabony defects: A 12-month re-entry. J Periodontol. 2001;72:25–34.
3 Jepsen S, et al. A randomized clinical trial comparing enamel matrix derivative and membrane treatment of buccal class II furcation involvement in mandibular molars. Part I: study design and results for primary outcomes. J Periodontol. 2004; 75:1150–1160.
4 McGuire MK, et al. Evaluation of human recession defects treated with coronally advanced flaps and either enamel matrix derivative or connective tissue. Part 1: comparison of clinical parameters. J Periodontol. 2003;74:1110–1125.
5 Sculean A, et al. Ten-year results following treatment of intra-bony defects with enamel matrix proteins and guided tissue regeneration. Clin Periodontol. 2008; 35:817-824.
6 Data on file (McGuire 10 year)
STr AUMANN ® M eM bra G el ®
In 2010, Straumann introduced Straumann MembraGel, an advanced technology membrane that is one of the most significant innovations in guided bone regeneration in recent history.
Created with PEG (polyethylene glycol) hydrogel technology, Straumann MembraGel is applied in liquid form and molds to the defect. Shortly after application, the liquid components solidify, stabilizing the bone graft and providing an effective barrier to tissue infiltration. Straumann MembraGel then biodegrades over time. It is designed to achieve undisturbed bone regeneration, which is a prerequisite for achieving ideal clinical and esthetic results.
“Straumann MembraGel is a key innovation in Guided Bone Regeneration. With the PEG technology we are on the verge of something new, entering a new era in oral tissue regeneration.“ Christoph Hämmerle, University of Zurich
Straumann MembraGel provides effective support in bone formation for GBR (guided bone regeneration) cases due to its optimized barrier properties. It facilitates undisturbed bone healing as a basis for the optimal clinical outcome achieved by stabilization of the bone graft material. The precise and easy application simplifies the surgical procedure.


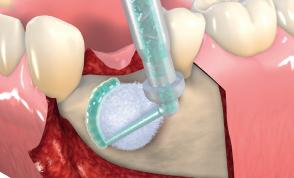
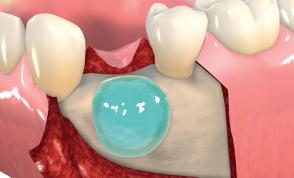
The gel-like consistency of Straumann ® MembraGel ® allows for precise application to the surgical site and adaptation to various types and sizes of bone defects.
Once solidified in situ (20 – 50 seconds after application), Straumann® MembraGel is designed to stabilize the underlying bone graft to facilitate undisturbed bone regeneration.
Straumann MembraGel is backed by preclinical1,2,3,4,5 and clinical 6 documentation including one- and three-year follow-up data7 presented in 2010 and submitted for publication. The ongoing clinical program with Straumann MembraGel includes over 40 centers and more than 200 patients in Europe and North America.
Straumann ® MembraGel was launched in conjunction with a well-received specialized education program that provides in-depth information on pre-clinical and clinical evidence, hands-on product training and the surgical techniques of this new application. Herbert Früh, Head of Business Unit Regenerative at Straumann explained, “MembraGel has allowed Straumann to bring a brilliant idea to






fruition. It is an innovative technology that requires training. Customers’ initial experience is that it saves time during intraoral application but it is different to handle. For this reason, it was the right decision to combine the launch of the new product with an intensive education program.”
Straumann ® MembraGel ® was introduced in Europe and North America toward the end of 2010, with roll-outs to other markets planned in the future.

Hands-on workshop at a Straumann MembraGel education event.
1 Humber CC, Sándor GK, Davis JM et al. Bone healing with an in situ formed bioresorbable polyethylene glycol hydrogel membrane in rabbit calvarial defects. Oral Surg Oral Med Oral Pathol Oral Radiol Endod 2010;109:372–384. 2 Jung RE, Lecloux G, Rompen E et al. A feasibility study evaluating an in situ formed synthetic biodegradable membrane for guided bone regeneration in dogs. Clin Oral Implants Res 2009;20:151–161. 3 Thoma DS, Halg G-A, Dard MM et al. Evaluation of a new biodegradable membrane to prevent gingival ingrowth into mandibular bone defects in minipigs. Clin Oral Implants Res 2009;20:7–16. 4 Herten M, Jung RE, Ferrari D et al. Biodegradation of different synthetic hydrogels made of polyethylene glycol hydrogel/RGD-peptide
®
Straumann MembraGel is a synthetic, biodegradable in situ -formed membrane made of polyethylene glycol (PEG) which forms a molecular network. The material is biocompatible, is applied in liquid form and sets quickly. Due to its gel-like consistency, it can be applied to cover the exact shape of the defect or augmented area and does not require cutting and trimming to shape before application – unlike traditional GBR membranes.
What exactly is PEG, and what makes it suited to this purpose? PEG is a polymer (a large molecule comprised of repeating structural units). It is produced through the reaction between ethylene oxide and water or the organic compound ethylene glycol, which is often used as a precursor to polymer materials.
PEG is available in a wide range of molecular weights. The molecular weight also determines the consistency of the material, which can vary greatly from waxy-solid to water-soluble liquid states. PEG has a number of properties that are particularly desirable in a number of biological, pharmaceutical and chemical applications: it is highly flexible, non-toxic and non-immunogenic. It is also hydrophilic, meaning that its attachment to biomolecules can increase solubility and decrease aggregation of the molecules.
Thanks to these very advantageous properties, PEG has been extensively used in many medical, pharmaceutical and medical device applications. For instance, it is used as a spray-on adhesion barrier and as a main ingredient in laxatives; as an agent for bowel irrigation prior to surgery or colonoscopy; as an addition to protein medications to extend their effect and increase dosing intervals; and as a carrier in various medications, such as soft capsules, ointments, tablets, and lubricants. Preliminary research is also underway to investigate the potential of PEG as a component in many other exciting applications, such as gene therapy, spinal cord injuries and the suppression of carcinogenesis. The use of PEG as a customizable, liquid-applied membrane is therefore another milestone in a long line of applications for this useful, versatile and extensively researched material.
modifications: an immunohistochemical study in rats. Clin Oral Implants Res 2009;20:116–125. 5 Jung RE, Zwahlen M, Weber FE et al. Evaluation of an in situ formed hydrogel as a biodegradable membrane for guided bone regeneration. Clin Oral Implants Res 2006;17:426–433. 6 Jung RE, Hälg GA, Thoma DS, Hämmerle CHF. A randomized, controlled clinical trial to evaluate a new membrane for guided bone regeneration around dental implants. Clin Oral Implants Res 2009;20:162–168. 7 Ramel C, Halg G, Thoma D et al. A randomized clinical trial to evaluate a synthetic gel membrane for GBR around dental implants – 1- and 3-year results. European Association for Osseointegration 19th Annual Scientific Meeting, Glasgow, UK, 6–9 October 2010; Abs 055.



i NTerview
“Being Part of this Network is Something Truly Exciting –Something We’ve Never Done in this Way Before.“

Prof.
Dr. Christoph Hämmerle Chairman of the Department of Fixed and Removable Prosthodontics and Dental Material Science, University of Zurich/Switzerland.
Andy Molnar, Straumann Executive Vice President, North America, interviews Professor Dr. Christoph Hämmerle of the University of Zurich about Straumann ® MembraGel ® .
professor Hämmerle, our company is introducing m embra g el by way of an international education-based program. this is a product which has been longawaited in the market; so many people would like to get their hands on it as soon as possible. What are your thoughts on this educational approach to the launch?
I think it’s very important to use an educational approach. What we’re dealing with here is a new technology, a new kind of membrane, a new way to apply the membrane. There are a lot of differences from all the membranes we’ve had before. I think it’s very important to launch the product in a well-structured way so that we know what experience we can rely on. It’s also an opportunity to learn about new things we need to become familiar with before we can use a new technology like this successfully and predictably.
“We treated over thirty defects and had minimal complications. Based on this experience and learning, we moved on to larger defects with a very good success rate once again.“ Christoph Hämmerle
i know you’re excited about m embra g el and the progress the product is making. How would you describe your involvement from the start, from inception all the way through the development of the project?
It has been very exciting for us. It’s really special to be there when the original idea is born and then to participate in the development of a new product, which is eventually able to solve problems and improve patient care. With all the sharing, teaching, and feedback we’re getting from different people all over the world, being part of this network is something really exciting, something we’ve never done this way before. For this reason, we’re looking forward to continuing with the



development of this scientific and educational network and really benefiting from the process. I think it’s great!
from our learning so far, what are the key points that we need to pass on to our educators?
There are three key points. One is that you have to change some of your surgical habits to adapt to the new technology, the new way to apply the membrane. The second is to adhere to published surgical guidelines. And the third is to begin with less complex cases until you have had around ten successful cases, and then move on to more difficult cases.
When we conducted our initial study, in which we used a collagen membrane as a control, we did not see any more difficulties with the membrane using the new technology than with the membrane using the older technology. I think this was the case because we were careful to use small dehiscence defects in non-esthetic areas. We treated over thirty defects and had minimal complications. Based on that experience and learning, we began to expand to larger defects, again, with very good success.
Professor Hämmerle, thank you very much for your time. It’s much appreciated.
“I think it’s very important to launch the product in a well-structured way so that we know what experience we
can rely on.“ Christoph Hämmerle
Returning to the topic of changing habits, this is a new technology, and there is a great temptation to use it in all kinds of different ways because it is rather easy to use and very new and exciting. We need to exercise restraint and really adhere to new practices in aspects of our surgical work.
The second point pertains to the surgical guidelines. We have seen that the surgical guidelines are not always followed accurately. Following the surgical guidelines could improve the practical outcomes when it comes to using this new product.
The third aspect is the size of the defects we tackle first.
GrOwT h i N rece SS i ON

Clinicians have been predictably treating gingival recession with Straumann ® Emdogain™ for years and talking about the beautiful smiles they gave back to their patients – we gave them the chance to prove it.
The best cases from the 2009 “Growth in Recession” Esthetic Case Competition were chosen by a renowned international jury to appear in Straumann’s Growth in Recession Esthetic Case Book. This casebook, published in 2011, features eleven cases presented together with the patients’ histories and images of each step to facilitate a detailed understanding of the surgical procedures involved.
This valuable tool is complimentary to you with your next order of Straumann Emdogain. Please reference order code “RECESSION” when placing your order.
Designed to help achieve excellent esthetic results
Esthetic Casebook: Straumann ® Emdogain
The following clinicians contributed their Case reports to this publication:
p Brazil: Dr. Robert Carvalho da Silva, DDS, MS, PH.D. (co-authors: Dr. Julio Cesar Joly, DDS, MS, PH.D., and Dr. Paulo Fernando Mesquita de Carvalho, DDS, MS)
p USA: Dr. Robert Levine, DDS – Dr. Ken Akimoto, DDS, MSD – Dr. Mark I. Gutt, DMD– Dr. Eunseok Eugene Oh, DDS (co-author: Dr. Vincent Iacono, DDS) – Dr. Paul G. Luepke, DDS, MS
p Canada: Dr. Ira Paul Sy, DDS, MS, Dip. Periodontics
p Germany: Dr. med. dent. Andreas Hofmann, M.Sc. – Dr. Bjørn Greven (coauthor: Dr. Bernd Heinz)
p Spain: Dr. Ion Zabalegui, MD
“BOTH THE SCIENTIFIC EVIDENCE AND MY PERSONAL Ex PERIENCE SUPPORT THAT WITH THE APPROPRIATE CASE S TRAUMANN ® E MDOGAIN ™ SIGNIFICANTLY IMPROVES ROOT COVERAGE COMPARED TO THE CORONALLY ADVANCED FLAP ALONE.”
Treatment of recession defects with Straumann Emdogain
Courtesy of Dr. Paul G. Luepke, DDS, MSD
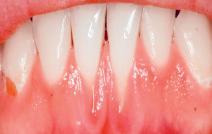
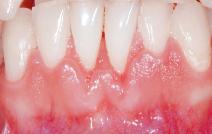
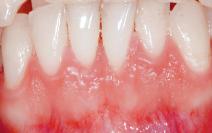
A referred 23-year-old female patient was presenting with multiple gingival recessions (teeth #8 to #3). The prominent canine showed a Miller Class III recession, the other teeth presented with Miller Class I recessions. The treatment procedure began with a thorough cleaning and scaling of the exposed root surfaces with hand and sonic instruments and was followed by a split thickness flap preparation of a Zucchelli-style flap (without vertical releasing incisions). A dissection into the vestibular mucosa allowed for further mobilization.
Straumann ® PrefGel ® (EDTA) was applied for two minutes on the root surface. Subsequently, the surgical area was rinsed with sterile saline and Straumann ® Emdogain™ was applied to the root surfaces. Connective tissue graft (CTG) was harvested from the palate with the single incision technique. The graft was then split. The CTG was fixed on the root surface and the flap coronally positioned and fixed with sling sutures.
Mechanical tooth cleaning in the surgical area was avoided during the first 4 weeks and a chlorhexidine solution was prescribed. Sutures were removed 10 days after surgery.

Dr. Paul G. Luepke, DDS, MS
1996 Master’s degree in Periodontics, University of Texas at San Antonio Health Science Center, Tx, USA • 1997 Diplomate of the American Board of Periodontology • 2008 Assistant Professor of Surgical Services Periodontics Division, Marquette University School of Dentistry in Milwaukee, WI, USA • 2009 Interim Department Chair of Surgical Sciences at Marquette University School of Dentistry in Milwaukee, WI, USA
Straumann is pleased to expand the options available for you through our commercial partnership with LifeNet Health,® allowing you the flexibility of choice when treating your patient. Processed with LifeNet Health’s proprietary and patented Allowash xG ® technology, Straumann AlloGraft gives you confidence that your graft is safe and effective.





Straumann AlloGraft C/C mix, Mineralized Ground Cortical/Cancellous mix
A mix of the strength of cortical bone with the structure of cancellous bone to support bony ingrowth in one product
Straumann AlloGraft OCAN 0.25 cc, Mineralized Ground Cancellous
Straumann AlloGraft GC 0.25 cc, Mineralized Ground Cortical
Straumann AlloGraft DGC 0.25 cc, Demineralized Ground Cortical For smaller defects, when extensive grafting is not needed
IMPLIFy
From crown to root, Straumann provides you with the convenience of ordering solutions from one provider – all from the scientifically driven company you know and trust.

Pave your way to success. Covering a full product range from temporary restorations to esthetic crown and bridge restorations, Straumann® CARES ® Digital Solutions is now featuring: new generation scanner new cAd software new applications leading range of materials
Straumann® CARES® Digital Solutions brings modern digital dentistry to dental professionals as a complete system –reliable, precise, and dedicated to your needs.
Please contact us at 800/448 8168 More information on www.straumann-cares-digital-solutions.com

Dr. Stefano Storelli
Graduation in Dentistry and Dental Prosthetics at the University of Milan/Italy. PhD in Implant Dentistry. Postgraduate in Oral Surgery (class of 2012).
Lecturer at the Department of Implant Prosthetics at the University of Milan. Author of various national and international publications and collaboration on various transcriptions. ITI and SIO member. Private practice in Milan.
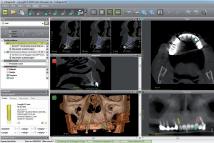
The use of guided surgery is paving the way for the future of implant surgery. Softwarebased pre-operative planning differs considerably from traditional planning with casts and x-ray printouts. The following case report involves a restoration for a partially edentulous woman with a fixed prosthesis preceded by pre-operative planning with the Straumann® Guided Surgery System using coDiagnostix™ (software) and gonyx™ (scan and surgical template fabrication device).
An 87-year-old Caucasian woman referred to our clinic, asked for a solution for her faulty fixed bridge which was causing pain and difficulty in eating. She had never worn a removable prosthesis and was willing to do anything possible to keep her fixed dentition. The patient suffered from an unspecified choreia with symptoms of involuntary movements, and was on aspirin treatment for her high blood pressure. Despite these restrictions, she was in a good physical and mental health. Clinically, the following situation was diagnosed: (1) a faulty fixed bridge (7 to 12), still anchored on the left side, where an old implant was still in use, (2) two
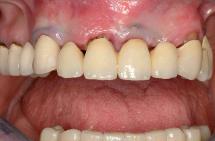
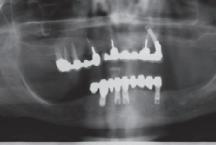
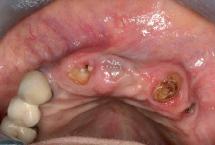


remaining teeth (8 and 11) which were fractured, and (3) a resorption on site 8 and a fracture of 11 revealed by the OPG as well as the inclination of the distal implant placed in 12 (figs. 1 – 3). Under these circumstances the clinician decided to remove the bridge and to restore the patient with a removable prosthesis.
After a couple of weeks the patient stated that it was impossible for her to wear the temporary denture and she returned to the dental practice several times due to fractures to the prosthesis. Therefore, it became apparent that a removable restoration was not suitable for this patient and that an implant solution had to be taken into consideration. Since minimally invasive surgery was intended, the clinician opted for a guided implant insertion in the post-extractive sites.
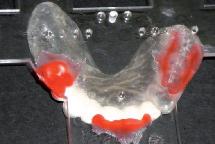
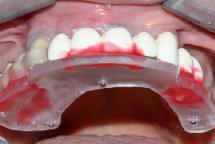
A mock-up of the future teeth was evaluated, followed by the preparation of the diagnostic template with the Straumann ® gony x table. The plate was attached to the barium teeth and the three titanium pins were placed according to the manufacturer’s instructions (f igs. 4, 5). The diagnostic guide was tested for


Graduation in Dentistry and Dental Prosthetics at the University of Milan/Italy. Author of various national and international publications and collaboration on various transcriptions. ITI, AO, SICOI and SIO member. Private practice in Gallarate (VA).

Teacher of post-graduate courses in dental implant technologies at the University of Milan.
Author and co-Author of professional articles and reference books. Private practice in Lomazzo (Como)/Italy, specialized in implant prosthetics, ceramics and state-of-the-art technologies (CADCAM etc.). Speaker at national congresses on the topics listed above.

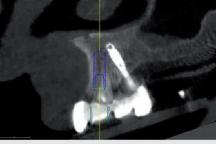
stability in the mouth of the patient before performing the Cone Beam CT scan (f ig. 6). The CT showed a remarkable resorption on site 8 and confirmed the inclination of the implant placed in 12. Therefore, the implant to be placed immediately in position 8 was moved to 7 and a miniflap was raised. The implant in position 11 had to deal with the position on the other implant.
The final treatment decided upon was a fixed implant supported prosthesis on 3 implants in positions 7-11-12. The Straumann ® coDiagnosti x ™ software was used to plan the treatment (f igs. 7, 8). The implant positions were defined in the software and the resulting template plan was sent to the lab. The implant in position 7 was planned to be a Roxolid ® implant with small diameter (Straumann ® Bone Level implant, NC Ø 3.3 mm, SLActive ® 12.0 mm); for the implant in 11, a Straumann ® Bone Level implant (RC Ø 4.1 mm, SLActive 12.0 mm) was chosen.
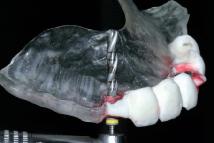
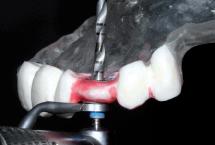
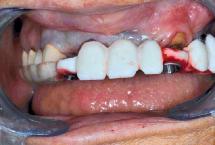
It was possible to identify the implant in 12 as a CoreVent1 Ø 4.0 mm implant placed about 15 years ago and, after some research, some prosthetic component of the respective implant manufacturer was found that was compatible with the internal connection to this implant. After drilling the holes into the scan template according to the template plan, the lab provided the surgical guide (f igs. 9 – 11)
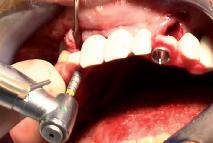
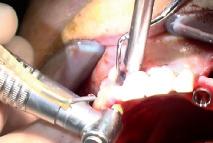
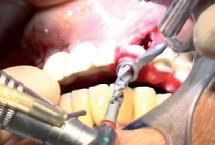
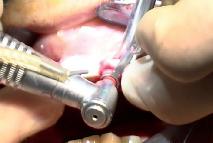
The two teeth were removed together with the granulation tissue around the root of tooth 8 under local anesthesia. The considerable resorption needed to be treated with regenerative material (bovine bone substitute material covered by a resorbable collagen membrane) to avoid major alteration of the contour. The surgical guide was placed on the remaining teeth and on the healing cap of the distal implant (f ig. 12). The surgical procedure was performed according to the surgical plan. The implant in position 7 was positioned after raising a mini-flap and by using the extra-long drill (Ø 2.8 mm) through the Ø 2.8 mm sleeve (f igs. 13, 14)

Prof. Eugenio Romeo
Graduation in Medicine and Surgery in 1984 at the University of Milan/Italy. Director of the Department of Implant Prosthetics at the University of Milan since 1992. Associate Professor since 2005. Author of various educational books and national and international publications. Chairman of the Advanced Oral Implantology course at the University of Milan. ITI fellow.
The implant was positioned after the guide had been removed, since the implant, having a diameter of 3.3 mm, cannot be inserted through the Ø 2.8 mm sleeve. The implant in position 11 was placed after using the extra-long drill series (Ø 2.2/2.8/3.5 mm) with the 1 mm reduction handle through the Ø 5 mm diameter sleeve (figs. 15, 16). The implant was positioned through the surgical guide. Transmucosal healing caps were positioned and the bone substitute material was inserted into the extraction sockets. Both sites were covered with the resorbable collagen membrane.
After 6 weeks, the OPG showed correct healing with no radiolucencies (f ig. 17). Clinically, the implants sounded correct and were stable (f ig. 18). The healing abutments were removed and screw-retained transfer parts were placed
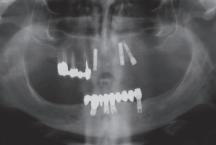
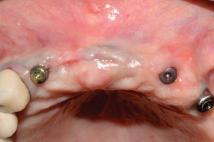

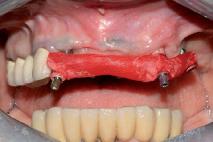
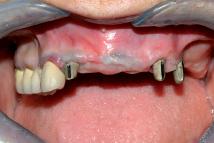
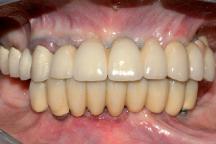
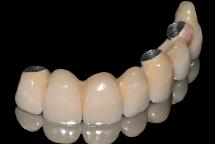
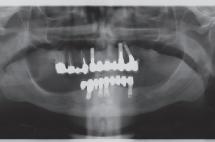
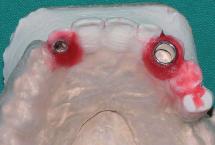
in order to take the impression. The three impression copings were splinted with a bridge of acrylic resin that had been prepared a few days before (figs. 21, 22). The three abutments were placed in position (f ig. 22) and the metalceramic prosthesis (f ig. 24) was cemented with a removable cement (f ig. 23) After one month of loading, no complications were registered or stated by the patient. By comparing the values obtained by computer planning with the x -ray taken after implant placement (f igs. 19, 20) , the precision of the system became visible, with the postextractive implant being about 1 mm deeper than planned and without much variability in the other dimensions.
Conclusion
The use of computer-guided implant placement allowed expanded treatment options and a fast, minimal invasive surgery for a patient who was not able to withstand long procedures. Producing the guide in such a manner is efficient and it fits well on natural teeth because it has been customized on the patient's impressions. The implant placement in the case reported here demonstrates the reliability of the Straumann ® Guided Surgery system.
With software-based treatment planning, the implants could be placed in the same practiced manner as with traditional techniques – but with higher precision and peace of mind. However, the learning curve for software-based planning should not be underestimated; in addition to familiarization with the software, new surgical techniques have to be applied and the surgeon needs to get accustomed to visualizing the surgical procedure through the software.
di Gi TAL w O rkfLO w
Surgical planning

Digital impression taking
Scan master model
® C ARES ® Scan CS2

A digital workflow to thousands of scanners
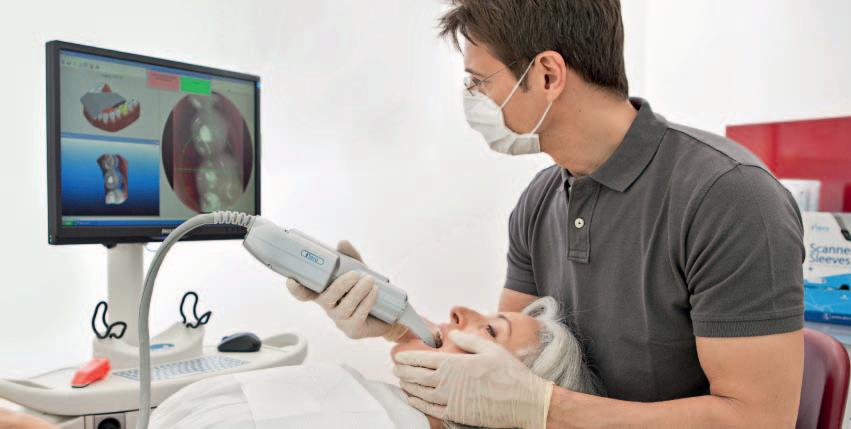
Straumann, together with 3M ESPE, has introduced a streamlined digital workflow that connects the Lava C.O.S. Intra-Oral Scanner to the Straumann® CARES® Digital Solutions platform. Parallel to the Cadent iTero ® intraoral scanner, dentists using the Lava C.O.S. scanner are now able to transfer digital scan data of the patient’s oral geometry to the dental lab using the Straumann ® CARES ® system. The CARES ® platform offers seamless connectivity to thousands of scanners in dental practices worldwide.

CARES ® 7.0: the open standard software platform
Straumann® CARES ® Visual 7.0 offers a wide range of benefits: the advantages of a flexible, open software standard – through the Dental Wings Open Software (DWOS ®) software core – and the quality and predictability of the validated workflow of Straumann ® CARES ® – through specific Straumann software applications. Powered by the combined resources of the partners, the CARES ® platform strives for the leading role in dentistry and provides you with access to future high-class developments of the digital dental industry.



VALIDATED STRAUMANN WORKFLOWS

Ex TERNAL WORKFLOWS
Via open STL format
Straumann milling centers: specialists in prosthetics
Straumann has a strong and long-time expertise in CADCAM manufacturing of prosthetic restorations in industrialgrade precision and quality. The high reliability of these restorations is based on Straumann’s strategy of validated design software and manufacturing that are compatible with each other. Via the Straumann milling centers, design expertise is offered as a service for complex restorations such as screw-retained bars and bridges, and as a scan service for customized abutments1
For modern implant and restorative dentistry:
Customized Straumann ® CARES ® Abutments (Ti, ZrO2), Straumann ® CARES ® Screw-retained bars and bridges (CoCr, Ti)
Copings, crowns and bridges, inlays, onlays and veneers
Resin nano ceramic:
3M™ ESPE™ Lava™ Ultimate Restorative Ceramics: zerion® (ZrO2), IPS e.max ® CAD, IPS Empress® CAD, VITA Mark II, VITA TriLuxe
Metals: ticon ® (Ti), coron ®, (CoCr)
Polymers: polyamide, polycon ® ae, polycon ® cast2
The Straumann ® CARES ® Digital Solutions portfolio provides a leading range of CADCAM materials and applications –according to your needs of serving your customers’ requests and of working cost-effectively without compromising on quality: from single-tooth restorations to 16-element bridges and from well-known to innovative materials like the new 3M™ ESPE™ Lava™ Ultimate Restorative.
The conventional prosthetic workflow using traditional impression taking, casting and waxing techniques can lead to inconsistent impression quality due to human errors. This can result in poor clinical and esthetic outcomes and time-consuming adjustments during seating. Digitalizing these processes can improve this situation from both a professional and business perspective.
From the intra-oral scan to the final restoration
Straumann offers a new and complete digital workflow for implant restorations. Starting with an intra-oral scan of the implant site, the customized Straumann ® CARES ® Abutment or full contour crown is designed to provide accuracy together with time and cost efficiency through the whole restorative procedure.
This kind of digital workflow for implant restorations eliminates cumbersome and time-consuming manual steps in dental practice and in the laboratory. Digital impressions allow immediate quality control by the dentist, and result in an excellent impression being sent to the laboratory. The workflow therefore eliminates or reduces impression retakes and restoration remakes, ensuring that seating appointments are efficient due to the excellent occlusion and contact-points of the restoration.
de NT i ST
Scan the scanbody directly on the implant with iTero™ intra-oral scanning and send the digital data to your partner laboratory.
L ABO r ATO rY
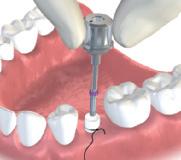
Design the customized Straumann® CARES® Abutment in Straumann CARES Visual and send data to the Straumann milling center for production.


L ABO r ATO rY
Finalize the restoration using the highprecision Straumann ® CARES ® Abutment, iTero™ model, Straumann Repositionable implant analog, and full contour crown.

de NT i ST
Serve patient with high-quality customized restoration designed to provide optimal function and esthetics.


3M™ e SP e ™ LA v A™ ULT i MAT e reSTO r ATive
3M ESPE and Straumann have partnered up to offer a new CADCAM restorative material, 3M™ ESPE™ Lava™ Ultimate Restorative, through Straumann ® CARES ® Digital Solutions. The material is based on Resin Nano Ceramic (RNC) technology, defining a new material class that combines the benefits of ceramic based on true nano technology and highly cross-linked resin.1
The field of nanotechnology has expanded dramatically as nanostructured materials exhibit unique properties on the macroscale that offer high-potential technological benefits. Typically, the critical properties of nanomaterials are attributable
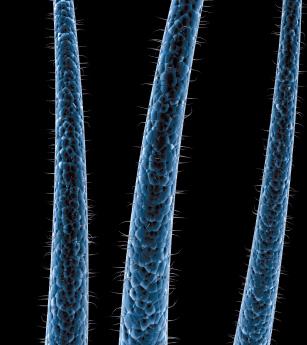
to internal structures between 1 and 100 nanometers in dimension, defining the nano world. In comparison, a human hair is about 200,000 nanometers in diameter, and a typical virus is about 100 nanometers long, a size which is at the outer boundaries of nanotechnology. As size is decreased to nanoscale dimensions, physical properties, e.g., optical characteristics, get altered, especially when size nears the molecular scale, meaning < 5 nm. These unique properties are in the focus when research starts its innovative work to achieve materials with greatest efficiencies. In the dental field, 3M™ ESPE™ Lava™ Ultimate Restorative offers an advanced dental material designed and engineered to be tooth-like and to deliver workflow advances.
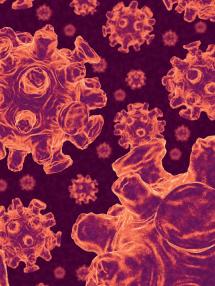
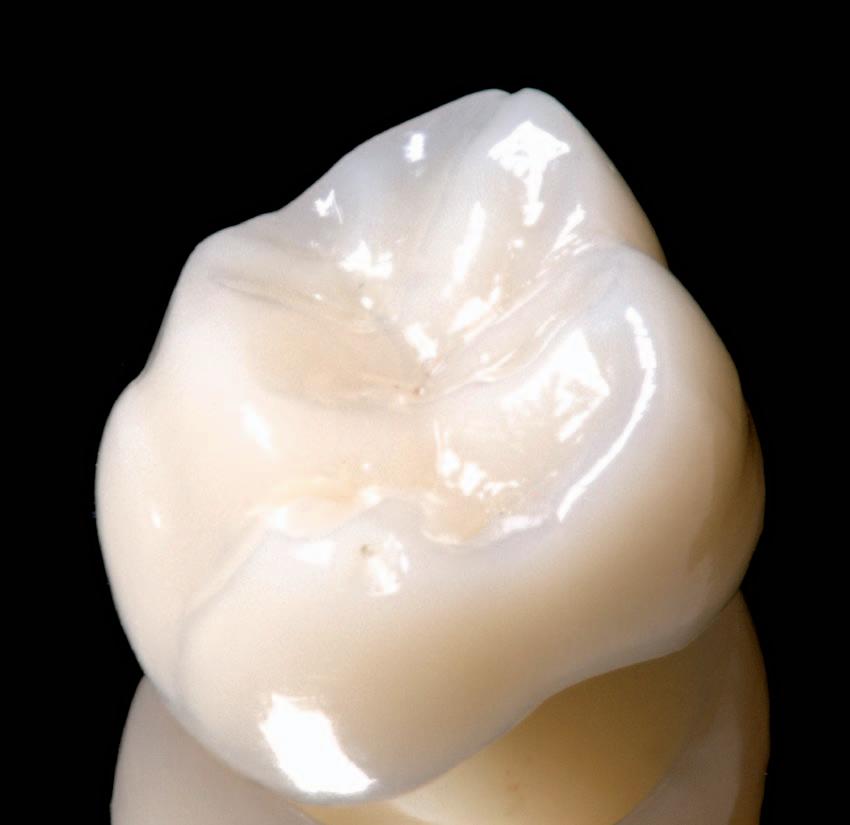
3M™ ESPE™ Lava™ Ultimate Restorative is a Resin Nano Ceramic containing approximately 79 % surface-modified nanoceramic particles. The ceramic particles are made up of three different ceramic fillers (of silica and zirconia) ranging between 4 and 20 nm that reinforce a highly cross-linked polymeric matrix.
The ceramic fillers are a combination of:
Silica filler: non-agglomerated/non-aggregated, 20 nm
Zirconia filler: non-agglomerated/non-aggregated 4 to 11 nm
Zirconia/silica cluster filler: aggregated, comprised of 20 nm silica and 4 to 11 nm zirconia particles
According to 3M ESPE
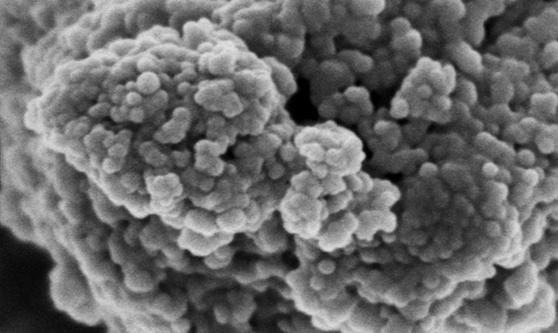
Bonded zirconia/silica nano particles clustered and surface treated in a proprietary process. Courtesy of 3M ESPE AG.



rNc – A N ew MAT eri AL c LASS
3M™ ESPE™ Lava™ Ultimate Restorative is a new CADCAM material based on Resin Nano Ceramic (RNC) technology, which is defined as a new material class. RNCs consist of nano ceramic components embedded in a highly cross-linked polymeric matrix. The true nanotechnology imparts excellent esthetics, strength and wear resistance. Using RNC technology 3M™ ESPE™ Lava™ Ultimate Restorative is designed to support a streamlined, flexible workflow.
» Brilliant esthetics – Resin Nano Ceramic for lasting polish
The physical properties of 3M™ ESPE™ Lava™ Ultimate Restorative make this material very similar to the natural translucency and fluorescence of the teeth in its behavior. The Straumann® CARES® Restorations made of it have a glossy appearance when delivered. An easy polishing step taking less than 4 minutes makes the restoration highly brilliant.
» 10-year limited warranty* – Designed to be durable for reliable restorations
The high flexural strength and fracture toughness of the 3M™ ESPE™ Lava™ Ultimate Restorative material make it a strong one-piece restoration. It is not brittle, allowing for chipping-free restorations. The material properties make it possible for the Straumann milling centers to produce thin and minimally invasive restorations, which also open up new treatment possibilities.
» Maintains functional balance – Absorption of chewing forces and less wear to opposing enamel
The nanoceramic technology makes it very kind to the opposing tooth regarding abrasion. 3M™ ESPE™ Lava™ Ultimate Restorative absorbs chewing forces and brings a new quality to all single tooth restorations.
iMPrOved wO rkfLOw ThrOUG h A dvANTAG eS i N Pre PA r ATi ON AN d h AN dLi NG
The high efficiency of the workflow made possible with 3M™ ESPE™ Lava™ Ultimate Restorative is of special interest for both dental labs and dental practices.
*If all the conditions of the Straumann Guarantee® are fulfilled and if the material is used in strict compliance with approved

» No further processing or firing
Once the Straumann ® CARES ® Restorations made of 3M™ ESPE™ Lava™ Ultimate Restorative are milled and delivered to the dental professional – no firing is required before being seated. The restoration can be polished, characterized with light-cured restoratives, and the anatomy can be changed by addingon or build-up. The abolition of the firing step specially emphasizes the new material category RNC of 3M™ ESPE™ Lava™ Restorative.
» Easy adjustment. Adjustments and customizations can be carried out extra-orally or intra-orally with light-cured composite, such as 3M™ Filtek™ Supreme x TE Universal Restorative / 3M™ Filtek™ Ultimate Universal Restorative, for excellent esthetic match.
» Benefits for dentists, dental labs and patients. Straumann ® CARES ® restorations made of 3M™ ESPE™ Lava™ Ultimate Restorative deliver esthetics without the requirement of further processing steps. They offer advantages across the dental workflow which are of true benefit to dentists, dental labs and patients. 3M™ ESPE™ Lava™ Ultimate Restorative offers high control and efficiency.
The new 3M™ ESPE™ Lava™ Ultimate Restorative is indicated for single tooth restorations and can only be processed by using modern CADCAM technology. 3M ESPE and Straumann have partnered up to offer 3M™ ESPE™ Lava™ Ultimate Restorative, through Straumann ® CARES ® Digital Solutions. The backing of Straumann as a reliable provider supports the opportunities this material offers through highlevel milling expertise and qualitative prosthetic outcomes. New treatment options are possible using 3M™ ESPE™ Lava™ Ultimate Restorative via the Straumann milling centers – specialists in CADCAM prosthetics.
For more detailed information on 3M™ ESPE™ LAVA™ Ultimate Restorative, please go to website http://solutions.3m.com/wps. portal/3M/en_US/3M-ESPE-NA/dental-professionals/products/category/digital-materials/lava-ultimate/. 3M™, ESPE™, Lava™, Filtek™ are trademarks of 3M or 3M ESPE AG.
Multiple data sources with Straumann ® CARES ® Digitalization of patient situation with various scanners, the intraoral scanners iTero® or Lava™ C.O.S. and the Straumann® CARES ® Scan CS2 desktop scanner.
No firing required after milling
An additional polish makes the restoration highly brilliant.
Validated workflow through Straumann CARES Visual Quality and predictability of the validated workflow via the specific Straumann software applications.
Easy adjustment
Adjustments and customizations can be carried out with lightcured composite.
Straumann CARES restorations in high Straumann quality Thin and minimally invasive restorations made of 3M™ ESPE™ Lava™ Ultimate Restorative via the Straumann milling centers.
Less wear to opposing enamel
3M™ ESPE™ Lava™ Ultimate is not brittle, allowing for chipping free restorations. It shows no abrasion or opposite tooth damage.
ShAdeS AvAiLABLe
Eight shades available, four of which include high translucency

iNTerview

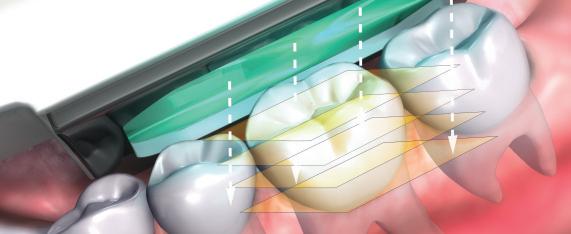
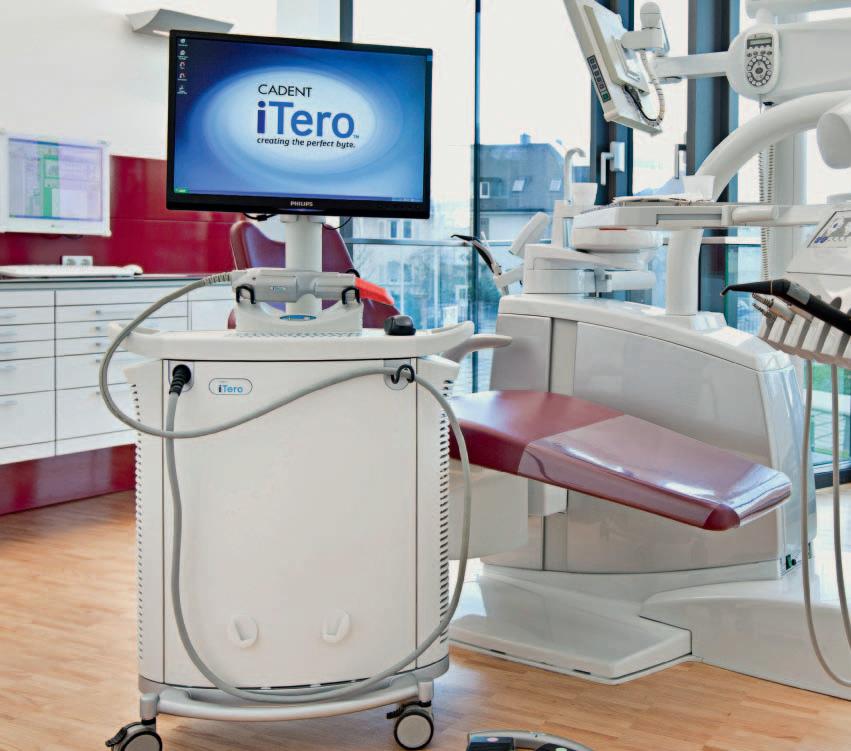
An interview with Michael Rynerson, Straumann Global Head of iTero™ Sales, on the iTero™ intraoral scanning system.
How do you view the market acceptance for a system such as itero?
Interest in digital impression-taking is truly tremendous. In particular, we have experienced this at congresses where the system is demonstrated live. Commercially, the iTero system with its highly developed 3D technology has gained a leading position in the USA. We also enjoy widespread interest from dentists and dental laboratories across Europe, where we have achieved a leading position in intraoral scanning in some markets. There are a number of good reasons for deciding in favor of iTero: user-friendliness, precision, and efficiency – also in terms of time and costs. Of course there is an emotional element too – many of our customers are passionate about adopting great new technologies for the benefit of their patients.
What role does itero play in the Straumann portfolio?
Intraoral scanning is an integral part of our digital portfolio because it is the most direct link between the restorative dentist, the laboratory, and our CARES ® production centers. Our focus is on solutions which enable our customers to offer their patients the best possible treatment available on the market. The advantages of iTero make intraoral scanning a key technology in dentistry and, thus, of interest to all dental professionals.
a re there any innovations especially for implantologists?
As an innovative company, Straumann has developed a complete digital workflow, from intraoral scans to Straumann® CARES ® copings and crowns, to customized abutments for
Straumann implants. True to the motto of our digital portfolio “Seamless Connections,” Straumann will now take the next step together with our customers. The new digital workflow is the basis for increasing efficiency and quality, and facilitates the cooperation between surgeons, dentists, and dental laboratories significantly. We view digitalization as a pronounced added value for customers at every stage of the workflow.
“The role as a center of digital competence makes the laboratory an important partner for the dentist.”
Michael Rynerson
Can you explain digital workflow for implants in more detail?
Following the recovery period, a scanbody is screwed onto the implant. The dentist scans the scanbody and the adjacent teeth in sequence and immediately sees on the screen the completed digital impression. The scanbody provides the necessary data on the position of the implant in the scan. Then the data is forwarded to the laboratory for the design of the customized Straumann CARES abutment in CARES Visual. The laboratory sends the production data to Straumann for fabrication of a CARES custom abutment, and orders a precision-milled iTero™ model from an iTero Regional Milling Center. The laboratory orders a Straumann Repositional Implant Analog that fits into the iTero model.
a re dental laboratories also a target group for itero?
In most cases modern dental laboratories are already centers of competence for digital technology – with CADCAM being a top subject for some time now. This role as a center

of digital competence makes the laboratory an important partner for the dentist. Thus, the iTero™ system also offers the dental laboratory new service opportunities. This is of special value because cooperation is closely linked via the intraoral scan workflow.
a re there other possibilities for using itero as part of the digital workflow?
We are presently uniting the various workflows to provide optimum compatibility. For example, our surgical planning software, the Straumann ® Guided Surgery System, combines the DVT and CT information on the bone situation to a 3D image for implant planning. Even today, we can already combine such data sets with intraoral scanning information to provide better documentation on the bone, soft tissue and tooth situation. This allows improved surgical and prosthetic planning.
C adent, the manufacturer of itero, is part of align technology as of a pril 2011. What are the implications?
Align Technology is a heavyweight in the orthodontic industry and includes invisalign™ in its portfolio, a well-known and widely used digital service for orthodontic treatments. Therefore Align truly understands digital dentistry, as well as knowing the needs of dental professionals, making them an ideal new home for the iTero™ technology. Furthermore, because Straumann is the exclusive distribution partner for iTero™ in Europe, and, since February of this year, also official distribution partner for iTero™ in North America, Straumann is one of the closest and most important partners of Align. Our cooperation to date with Align has been superb and we are enthusiastic about continuing our partnership.



What does the future hold in your opinion?
For me it is not a question of will the majority of dentists work predominantly with intraoral scanners, but when will this become reality. We have all seen a similar revolution in photography. Who still uses film cameras these days?
Popular smartphones are another good example of how digital impression technology will evolve. iTero is comparable to smartphones in so far as it is a platform for a range of dental services that can be expanded through the installation of new software applications. If you will, iTero™ is an extremely precise digital 3D camera with which dentists can already cover a wide range of restorative and orthodontic indications today. Future developments of the software and connected services will generate added value. In short, if somebody purchases an iTero™ scanner today, they should have confidence that it will continue to gain in value through software innovations. The system already generates considerable added value, we are only really at the beginning of this technology – the development potential for the next few years is enormous. For example, in future one could well imagine taking 3D “snapshots” of patients at their first visit and after subsequent treatments. Thus, dentists could not only document tooth situations in a digital manner, but would be better able to assess future developments in the patient’s oral condition. Today, dentistry is still very reactive in many cases – using digital tools dental professionals will be able to be much more proactive.
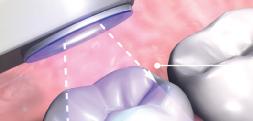
The highly advanced intraoral scanner iTero utilizes parallel-confocal 3D imaging and is thus 100 % powder-free and autofocus. Both features allow the dentist to place the scanning head directly on the teeth to take a series of 3D images which are combined into a precise 3D representation of the patient’s teeth. This provides stable handling as well as high precision and is often more pleasant for the patients than conventional methods. iTero guides the treating professional from tooth to tooth, similar to an automobile navigation system. The scanner is not only easy to operate, but also inspires patients as they can follow every step on the screen.

Straumann is the #1 dental implant system worldwide




Ivoclar Vivadent ®
Combining Outstanding Properties – Now Available for NC
Straumann is the partner of choice for innovations in implant and restorative dentistry. Ivoclar Vivadent is the established specialist in ceramic materials and final restorations. The synergy of technologies has resulted in a premium esthetic solution: the Straumann Anatomic IPS e.max Abutment, now also available for Narrow CrossFit ® (NC).
Esthetics by Design
Designed by Straumann and produced by Ivoclar Vivadent to fit a range of patient needs, this abutment is specifically intended for reliable use and esthetic results and offers great flexibility in its application. It gives you the high-end esthetics
of a custom restoration in combination with the flexibility and predictability of a stock abutment.
High-end esthetics: all-ceramic zirconium dioxide (ZrO 2) material in two shades for natural-looking restorations.
Effectiveness: pre-shaped abutment, straight and angled design in two gingival heights for cost-efficient restoration.
Predictability: Straumann Anatomic IPS e.max Abutment –strong connection between the implant and the restoration. Flexibility: modifiable abutment (chair-side and lab-side) for screw-retained and cemented all-ceramic restorations.








Screw-retained full ceramic restorations


Cemented full ceramic restorations directly veneered


individualized emergence profile

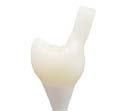








» Different shades
» Different gingival heights
» Straight and angled
» RC and NC




The abutment serves as an excellent basis for cost-efficient restorations for those clinicians looking to transition into the all-ceramic world of dental restorations.


cO
rBiN P ArT rid G e AN d Bre NT G A rriSON
Initial Situation
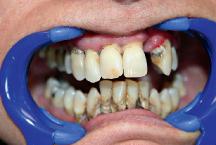
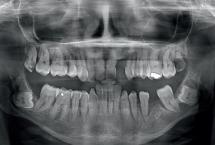
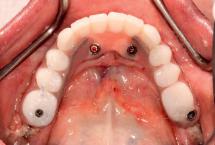
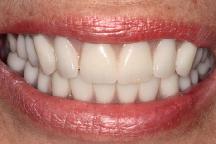
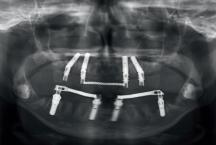
A 49-year-old woman with an unremarkable medical history presented for a full mouth extraction. Severe periodontal disease was present in addition to mobile teeth and noted bone loss (figs. 1, 2). She indicated that she wanted to have an implant-supported fixed prosthesis in order to avoid having to wear traditional dentures long term.
Treatment Plan
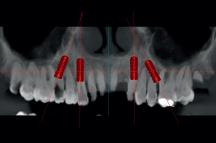
A CT scan was performed and converted into implant planning software. Upon examination of the CT scan and reconsultation with the patient, it was determined that four implants in each arch would be placed to support a fixed prosthesis. Using the converted scan, the implant sizes and locations were planned for both the mandible and the
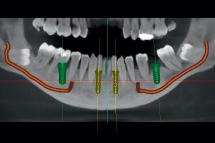
maxilla using the implant planning software. Four Straumann ® Bone Level implants1 were planned for the maxilla and four Straumann ® Soft Tissue Level implants2 were planned for the mandible (figs. 3, 4). The posterior implants in the areas of #14 and #25 were angled to avoid the sinus and still provide for first molar occlusion in the final prosthesis. A guided surgical stent was then ordered through the software for the maxilla. The referring office supplied the immediate denture prior to surgery. The patient was scheduled for surgery approximately one month after the second consultation to allow for creation of the stent and immediate dentures.
The initial phase of the surgery involved removing all of the existing teeth with the exception of the #38 and #48, due

Corbin G. Partridge, DMD
Oral and maxillofacial surgeon. Full-time private practice at Northeast Oral and Maxillofacial Surgery in Indianapolis, Indiana. He has published several papers in both the Journal of Oral and Maxillofacial Surgery and the Journal of the Indiana Dental Association. He served in the U.S. Army as the Executive Officer of the Head and Neck Surgery Team with the 47th Combat Support Hospital in Mosul, Iraq during Operation “Iraqi Freedom“ 2005 – 2007. He is an ITI member.
cpartridge@neomsindy.com
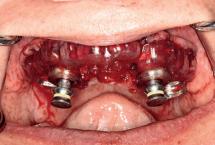
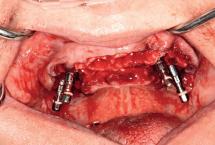
to nerve involvement. The patient was sedated and the teeth were extracted as atraumatically as possible. Once the teeth were removed, the maxillary arch was exposed and the surgical stent was secured to the maxilla. The osteotomies were performed through the guide using a Straumann ® Guided Surgical Kit with a final drill diameter of 3.5 mm (fig. 5). Stabilization pins were used to secure the stent while other osteotomy sites were prepared. The four Straumann ® Bone Level implants were then placed with primary stability using a hand piece at 35 Ncm (fig. 6). Sutures were used for ridge closure in a continuous and interrupted fashion. Attention was then directed to the mandible, where osteotomies were performed in the areas of #36, #33, #43 and #46. The Standard Plus implants were placed in the anterior sites #33 and #43. The Regular Neck Tapered Effect implant was placed in the area of #36 and the Wide Neck Tapered Effect implant was placed in the area of #46 (fig. 7). All implants were placed with primary stability using a hand piece at 35 Ncm. No sutures were required as the mandibular ridge was not exposed.
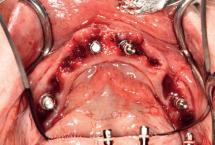
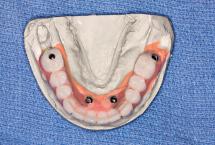
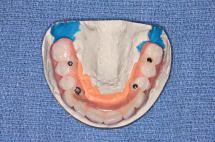
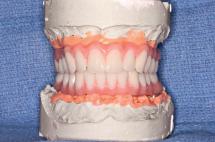
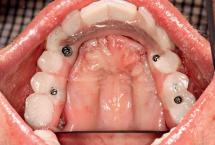
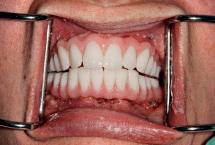
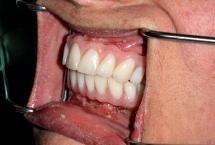
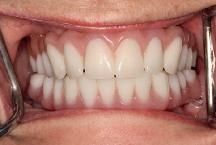
Immediately after the implants were placed, impression posts were attached and impressions of both arches were taken. After the impressions were taken, healing caps were placed on all implants, the impressions and immediate dentures were sent to the lab, and the patient left the office. Using the impressions, the lab converted the immediate dentures into screw retained immediate prostheses, which were heat cured overnight (figs. 8 – 10). The patient returned to the office the next day for placement of the provisional prostheses. The healing caps were removed and the appropriate abutments were placed. The maxillary prosthesis was placed over the abutments and attached using four screws, with the mandibular prosthesis fixed in a similar fashion (figs. 11, 12). The patient’s bite was adjusted using a handpiece with a denture bur. Once the adjustments were finished and the patient was satisfied with her bite, a temporary filling material was placed in the screw holes of the prostheses and final x-rays were taken (figs. 13 – 17). The patient was given instructions for post-op hygiene and told not to chew for eight weeks to allow

Oral and maxillofacial surgeon. Full-time private practice at Northeast Oral and Maxillofacial Surgery in Indianapolis, Indiana. He has published several articles and given numerous presentations on all aspects of oral and maxillofacial surgery. He has served terms as President of the Great Lakes Society of Oral and Maxillofacial Surgery, the Indiana Society of Oral and Maxillofacial Surgeons and the Indianapolis District Dental Society. He is Assistant Clinical Professor of Oral and Maxillofacial Surgery at the Indiana University Medical Center. He is an ITI member.
bgarrison@neomsindy.com
for proper integration, after which a limited soft-chew diet was recommended. This is recommended due to the limited strength of the provisional prostheses, which serve a more esthetic rather than functional purpose.
The patient returned to the office for her one week check, and was healing well. She will wear the provisional fixed prostheses for approximately six months, allowing the ridges to form fully and heal. At this time, she will return to the office for final impressions, which will be used by the laboratory to create the permanent bar retained prostheses. Combining the milled bar-retained prostheses with the splinted Straumann ® SLActive ® implants will result in a strong and permanent alternative to traditional dentures.

STr AUMANN ® SL a ctive ®
The Straumann SLActive implant surface offers confidence in all treatments thanks to its unique properties of hydrophilicity and chemical activity, which help to accelerate the osseointegration process.1 The excellent osseoconductive properties of the SLActive surface have been supported by numerous preclinical and clinical studies.
Now clinicians can access the updated SLActive Scientific Evidence Brochure to review some of the key scientific studies supporting the SLActive implant surface. The newly available and updated version of the SLActive Scientific Evidence Brochure features summaries of 14 preclinical and 7 clinical studies on SLActive. A few new clinical studies from this information-rich brochure are highlighted below. If you wish to have an SLActive Scientific Evidence Brochure sent to you, please contact your local Straumann territory manager or contact the Straumann Customer Service team at 800/448 8168.
A prospective study on 3 weeks loading of chemically modified titanium implants in the maxillary molar region: 1-year results
M. Roccuzzo, T.G. Wilson Int J Oral Maxillofac Implants 2009;24:65–72
Abstract: SLActive ® implants were placed in the posterior maxilla, which tends to have lower bone density, and loaded after 3 weeks. Preliminary results suggest no complications and no early implant failures in this challenging indication.
Conclusions
Successful functional loading is possible in the maxillary molar region after 3 weeks with SLActive implants
Implant survival was 100 % after 12 months in low density bone
The procedure represents an important step toward faster healing and increased treatment predictability
1 Compared to SLA in an animal
Early loading of nonsubmerged titanium implants with a chemically modified sand-blasted and acid-etched surface: 6-month results of a prospective case series study in the posterior mandible focusing on peri-implant crestal bone changes and implant stability quotient (ISQ) values Bornstein MM, Hart CN, Halbritter SA, Morton D, Buser D. Clin Implant Dent Relat Res 2009;11(4):338-347
Abstract: Forty patients received 56 SLActive ® implants, which were functionally loaded after 3 weeks. Implant stability (ISQ) was measured at various time points for up to 26 weeks and showed a steady increase from implant placement to week 26.
Conclusions
Early loading with SLActive implants 3 weeks after placement in the posterior mandible has a low risk for early failures
Definitive functional restoration after 3 weeks is possible



Early loading at 21 days of non-submerged titanium implants with a chemically modified sandblasted and acid-etched surface: 3-year results of a prospective stu dy in the posterior mandible
Bornstein MM, Wittneben J-G, Brägger U, Buser D. J Periodontol 2010;81(6):809-818.
Abstract: SLActive ® implants were placed in patients and functionally loaded after 21 days; clinical and radiographic parameters were evaluated for up to 36 months. No implants were lost and clinical attachment levels and probing depths were improved versus historical SLA ® controls.
Conclusions
Early loaded SLActive implants can achieve and maintain successful tissue integration over 3 years
The procedure offers rehabilitation with a definitive restoration after 3 weeks, increasing cost-effectiveness for the patient
Loading after 3 weeks can be recommended in defined clinical situations for standard sites without bone defects
A multicenter prospective ‘non-interventional’ study to document the use of and success of Straumann ® SLActive implants in daily dental practice
Luongo G, Oteri G. 24th Annual Meeting of the Academy of Osseointegration, February 26-28, San Diego, CA, USA; poster P220. J Oral Implantol 2010; 36(4):305-314.
Abstract: A multicenter non-interventional study was conducted, in which 276 SLActive implants were placed and documented in 218 patients according to situations where implants would normally be placed. After 1 year the survival and success rate was 98.2%, similar to that observed in strictly controlled clinical trials.
Conclusions
The 1-year cumulative survival and success rate was 98.2%

All failed implants were associated with a simultaneous sinus floor augmentation procedure
The success rate of SLActive implants in daily practice is similar to that observed in formal clinical trials with strictly controlled patient populations

On July 29-30, 2011, twenty-four dental professionals braved the Dallas, Texas drought and 100+ degree temperatures to learn about the digital dentistry workflow at Baylor University’s College of Dentistry.
Over the course of two days, the participants—comprised of clinicians and lab technicians—learned about where the dental world is headed and how interdisciplinary digital dentistry will continue to play a larger part in their practices and labs. The course, cosponsored by Straumann, was designed for the interdisciplinary team (surgeon, restorative dentist and lab technician) to attend and learn about the different digital technologies available to each member of the team, and to understand how each team member and their technology plays a role in achieving optimal patient care and esthetic results.
Participants were exposed to all of the links in the digital dentistry chain, including Straumann Guided Surgery Planning Software, the gonyx table, the iTero scanner, and the CS2 scanner.
It was a jam-packed two days, filled with lectures, case presentations and hands-on sessions. Participants learned how to treatment plan implant cases with the Straumann Guided Surgery treatment planning software and how a radiographic template and surgical guide can be made with precise accuracy on a gonyx table. They also experienced firsthand how to take an intra-oral impression with an iTero system and how to open an iTero file into the CS2 CADCAM scanner and design a coping, abutment or crown.
It was an excellent course, and many of the attendees left excited to start incorporating digital dentistry into their practices.
The advice from previous attendees is to register as a team- many who came alone said they wished they had brought their interdisciplinary team members.
Baylor will host this course again July 27-28, 2012. If you are interested in learning more about the Interdisciplinary Digital Dentistry Courses, please contact the Straumann Education Department at 800/448 8168 and press 5, or register on the Baylor CE website at: http://www.bcdce.com/courses/ course/category.php?id=2
Basel, Switzerland – The International Team for Implantology (ITI), a leading academic organization dedicated to the promotion of evidence-based education and research in the field of implant dentistry, announced on October 17, 2011 that it had welcomed its 10,000th member. This achievement marks another milestone in the 31-year history of the ITI.
This growth is due in large part to the recently launched ITI Study Club concept, which has evoked an overwhelming response around the globe. Exceeding its own expectations, the ITI to date has established more than 500 Study Clubs on every continent. Free participation in ITI Study Clubs as part of the annual benefits package has proven to be a significant membership value. ITI Study Clubs are characterized by an approach to learning through presentations and interactive discussion in relatively small groups at a local level. They represent an efficient platform from which to disseminate and exchange knowledge on the latest treatment approaches in implant dentistry.
The 10,000th member of the ITI is Dr. Jocelyn Shand, a well respected Oral & Maxillofacial Surgeon from the Royal Children’s Hospital, University of Melbourne and President of the Australian & New Zealand Association of Oral & Maxillofacial Surgeons. She was welcomed personally by the ITI President Prof. Dr. Daniel Buser and the leadership team of the ITI Section Australasia.
“We are very pleased with the current membership development and the opportunity to welcome our 10,000th member,“ said Prof. Buser. “The continued growth of the ITI, which is a result of the systematic implementation of our strategic Vision 2017 developed in 2007, is a clear sign of the
strong demand by colleagues for evidence-based education and treatment guidelines that are delivered independently of commercial interests.“
“I heard about the ITI several years ago and since then traced its activities,“ said Dr. Shand. “After attending several ITI education courses in Melbourne and working with a number of esteemed ITI Fellows in Australia including Dr. Anthony Dickinson and Dr. Stephen Chen, I was immediately drawn to becoming a member of this global organization with its wealth of benefits that will significantly enhance both my professional activities and international perspectives.“
Established in 1980 by a small group of visionary pioneers led by Prof. Dr. André Schroeder and Dr. Fritz Straumann, the ITI has championed the cause of implant dentistry since the early days, playing a continuous role in its development to the present day. Today, the organization has a true global presence through its 27 national or regional Sections. The ITI takes a leading role all over the world in continuing dental education and the development of standard treatment methods to ensure reliable outcomes. In addition, the ITI is the largest non-governmental organization worldwide to award research grants in implant dentistry.
The ITI welcomes all appropriately qualified professionals with an interest in implant dentistry as members of the organization. Membership of the ITI offers a wealth of benefits and the highest quality educational support as well as the opportunity to meet likeminded professionals through the extensive event schedule. Dental practitioners who are interested in finding out more or joining the ITI should go to www.iti.org. international team for implantology




How will the world’s demographics, technologies and economies develop in the future? Will these developments impact implantology, dentistry and the other related medical disciplines? The answers to these questions determine how Straumann designs our products and services, and how we drive innovations. Perhaps the most globally influential trend is the aging population and the attendant need for health services, including restorative dentistry. Practices of the future will look different than those of today.
In the 1970s, the discovery of titanium’s osseointegrative properties and high compatibility with the human body led to the development of dental implants for the replacement of lost teeth and anchoring of prostheses. Key advantages of implants over conventional denture techniques allowed manufacturers and specialized dentists to develop a new discipline of dentistry, which has since evolved into today’s standard treatments with restorative dentistry.
Nearly forty years after discovering the osseointegration of titanium, we are entering the next quantum leap in dentistry: the digitalization of restorative dentistry. This will have tangible effects on the way we look at various occupations and, in turn, how dental experts work together. New products and innovations are constantly developed, potentially leading to new treatment opportunities.
STARGET interviewed three prestigious dental specialists on trends and new technologies in restorative dentistry: lyndon Cooper, Kenneth m alament and d aniel Wismeijer.

Stallings Distinguished Professor, Professor & Chair, Dept. of Prosthodontics; University of North Carolina School of Dentistry
How can the implant industry serve its customers better?
Implant therapies are evolving rapidly, yet dentists with mature practices learned little about implants in dental school 10 years ago. The industry must continue to help educate dentists. There needs to be an ethical discussion between the industry and the profession about standards in product testing, documentation and training. Finally, the industry truly serves both patient and dentist by providing clinical data about the products. How many implants failed? We clinicians care and need to know.
restorations on a metal frame? Zirconia? What if the patient only has enough bone for 6 mm implants? Should we graft bone and place 8 mm or 10 mm implants, or is 6 mm enough?
I’m not suggesting there is only one answer, but together the profession and industry can use evidence to determine which therapies provide maximum return on patient investment with a minimal number of interventions and components.
What about standards for products?
One implant system rarely covers everything, so you may need at least two different systems. There may be some value in diversity. However, I also see value in having evidence based standards and shared criteria that reflect clinical outcomes. It would be good to have efficacy data for implants tested six to 12 months before a product is sold. The drug industry gathers data after the product has been introduced. That model might work for our very fast product evolution.
Have we reached the limits in osseointegration?
“The industry must continue to help educate dentists. There needs to be an ethical discussion between the industry and the profession about standards in product testing, documentation and training.“ Lyndon Cooper
Will dentistry develop standards of care?
Simplification and standardization can improve the quality of care. For example, what possibilities exist for an edentulous maxilla – four, six or eight implants? Ceramic or acrylic
We continue to improve the osseointegration potential of implants, but we still must learn to identify high risk patients and develop successful strategies for them. From a broader perspective, our knowledge of how soft tissues integrate with the abutment is very immature. We need new scientific understanding so we can get healthy soft tissue integration that protects the underlying bone, stays free of inflammation and looks natural.
is peri-implantitis a latent epidemic?
We don’t know; we don’t fully appreciate its incidence or prevalence. We must acknowledge its presence and dentists must evaluate implants regularly for inflammation and act appropriately. Does the inflammation begin at the implant
surface, at the implant-abutment interface, or at the abutment itself? The solutions could be very different.
How has the economic crisis affected dentistry?
US laboratories are making fewer crowns and veneers, while removable and complete denture volume is less affected, suggesting that people still need teeth but they have adopted a cost-conscious attitude. The growth of implant sales has been slower since 2008. The growing debate about nationalized healthcare in the US is fueling new discussion about access to dental care.

ke NN eT h M ALAM e NT
Clinical Professor of Postdoctoral Prosthodontics, Tufts School of Dental Medicine, Boston
What have been the most significant developments in prosthodontics in the past two to three years?
Digital scanning equipment and software continues to improve. Then, for the very first time a material, lithium disilicate, has shown no signs of breakage over 2½ years. This monolithic material can be CADCAM’d to full contour in one step, unlike the bilayer materials. Finally, bone grafting materials and techniques have significantly improved, allowing more
Simply doing more
complex restoration of defects. These three developments really open the door for tremendous growth in implant dentistry.
What will the relevance of prosthodontics be in the future?
As we move to smarter, more capable technologies, we need better understanding of how to create occlusion, form, color, and natural esthetic appearance within the whole mouth. These are the concerns of the specialty of prosthodontics, and I am very confident in its future.
“Preventive dentistry is more successful than ever before, but many people don’t go to a dentist regularly, and their mouths show the usual levels of decay and periodontal problems.“ Kenneth Malament
Will better prevention reduce the need for prosthodontics?
I don’t think so. Preventive dentistry is more successful than ever before, but many people don’t go to a dentist regularly, and their mouths show the usual levels of decay and periodontal problems. Also, people are still affected by accidents and disease. Dental restorations break and cause serious problems. In my practice, I haven't seen any diminution of required care.
a re the products coming onto the market adequately tested?
No. Look at the whole cosmetic dentistry concept, where people were putting plastics on everything and considering it conventional and thorough and long-term successful dentistry. Bacteria grow on and within resinous materials, and can cause serious breakdown when they attack tooth structure. Recent research on how ceramic materials flex and fracture has completely



changed the way we understand the mechanics and strength of ceramic materials. As we develop new materials, we must understand and test them better.
a re high-end esthetics out of reach for the average patient?
Right now, access to great esthetics is limited by the supply of great dentist/technician teams. As we move to smart systems, the expertise of the best practitioners will be built into the software. I think CADCAM dentistry will eventually drop the price of dentistry, but I’m not sure when.

“As we move to smart systems, the expertise of the best practitioners will be built into the software.“
Kenneth Malament
What major advances do you expect in the near to mid term?
Low-radiation, noninvasive CT scanning for all dental impressions while the patient sits in a chair. Spectrophotometric color analysis will help design the whole mouth on a giant computer monitor.
Has the economic crisis had an effect on prosthodontics?
No. The companies that will win in the next 10 years are those that best integrate the technologies and educate dentists and technicians. The real explosion will come from well-funded industrial giants who are very active players within the story.
dAN ie L wi SM eijer
Professor & Chairman, Dept. Oral Function & Restorative Dentistry; Head, Oral Implantology & Prosthetic Dentistry Section, Academic Center for Dentistry, Amsterdam (ACTA)
d o you think all of dentistry is going to become digital?
A dentist’s work is two-fold: handicraft and oral medicine. It will be a while before we digitize interaction with the patient, looking at the medical and psychological background, diagnosis, and individual treatment design. On the handicraft side, digital radiography improves diagnostics and reduces chemical waste. Starting with oral scanning, digital articulators and planners will replace physical models, and the whole workflow will become digital, ending in CADCAM production. Once we get good light images of the teeth, a machine will also produce the prosthesis in the right color.
is digitalization the most important trend in dentistry now?
It’s where things are happening. Virtual implant planning is getting more precise, and computer manufacturing of prosthetics is getting simpler than the casting method. We can design the treatment digitally (site, position, implant type, superstructure) and insert the implants plus superstructure in one treatment sequence with a fault margin of 40 μm – the width of the thinnest human hair. Everything is more controllable, and if something doesn’t fit during the digital design phase, we can correct it before it reaches the patient. So the digital environment is going to be very important.
What do you see as the biggest risks in digital dentistry?
We will become more dependent on commercial software. Some jobs will be lost. In order to rely on machines and software, the safety standard must be very high. And in order to rely on internet communication, the transmission, security, format and integrity of private medical information must be ensured. Finally, the machines are not cheap, and it may be a long time before we can deliver digital dentistry at a lower price.
How will technological changes affect current dentists?
Young graduates will want to practice digital dentistry. Mature dentists close to retirement face the choice of investing in new technologies to attract young dentists who will then buy their practices, or continuing the old way and losing some of their original investment. There is no choice in between. If they want to stay in dentistry they will have to invest in new technologies.
d oes digitalization get ample attention in dental education?
Students leaving ACTA in a few years will be used to working with intra-oral scanning, cone beam CT scans, digital planning, drill guides, and CADCAM. As they join practices, they will show other dentists the new techniques. We are lucky that our school is new and so are all the fittings. Many other schools are looking at what we are doing, but it will take them time to convert.
What sort of innovations can we expect in the next years?
Improved navigation, so the dentist can monitor inside the bone and teeth as he or she works. Apparatuses that convert hand movements into very small precise machine movements will make micro treatment possible. Finally, I hope companies agree on data standards, so all the machines and software can communicate with each other.
Providing high quality, safe, effective, and lasting solutions that restore dental function and enhance the quality of life is perhaps the greatest contribution we can make to society. In 2009, around a million patients spread across 70 countries invested in a Straumann dental solution, and we have simply done more to make certain that it will meet their expectations for many years to come.
At the same time, many people around the world are unable to benefit from dental care due to geographic and economic limitations. As a leader in our industry and as a responsible corporate citizen, we believe we have a duty to help in a practical, meaningful way. Our aim is to ensure that our contributions benefit not only the recipients but also, indirectly, our other stakeholders.
TO de
‘Straumann AID’ (Access to Implant Dentistry) is our structured global program to assist patients who need implant treatment but are unable to afford it. Through this program, we donate all the Straumann products necessary, relying on dentists in the ITI network to provide the clinical services without charge.
Our strategy for corporate sponsorship is to concentrate primarily on charitable activities where we can have the greatest impact, based on our own competencies and the collaboration of our partners. For this reason, we focus on dentistry-related programs that help people who do not have access to dental care or cannot afford implant dentistry.
We continued our tradition of sponsoring charitable missions and activities that bring basic dental care and education to the underprivileged. Our contributions in 2009 included support for the following:
p SDI Secours Dentaire International, treating patients in Tanzania
p A team of young dentists from the University of Connecticut Health Center, School of Dental Medicine to provide dental treatment and oral hygiene to underprivileged children in Chile
p The ‘Hope for All’ project to sponsor the education of two dental students in Cambodia
p A team of young dentists from the Dental Institute of Basel University, to provide dental treatment to orphaned children in Cambodia

p Three teams of young dentists from the Dental Institute of Zurich University, to provide dental treatment to children in the Dominican Republic, Guatemala and the Ukraine
p The Smile Charity Foundation/Korean Universities and Schools of Dentistry, to improve the oral health of disabled persons and to provide scholarships in Korea.
In each case the sponsorship goals were met. Thanks to the assistance of our dental partners, these projects have been an extremely efficient use of funding and have made a real difference to hundreds of people, most of whom are children. We intend to continue our global charitable activities with the goal of providing access to dental treatment to disadvantaged people. Although economic downturns frequently result in reduced charitable giving, we plan to continue our Straumann AID program and to support the National Foundation for Ectodermal Dysplasia (NFED) and other relief projects. We will continue to focus our charitable sponsoring on fields related to dentistry, where we feel we have most to offer and where our involvement is appreciated by our stakeholders.
Ectodermal dysplasia
Ectodermal Dysplasia (ED) refers to a group of genetic disorders characterized by abnormal development of the skin and associated structures. Patients typically have few teeth and the teeth they do develop are usually severely malformed. On average, each ED patient in the US faces dental charges of $28,000. This is a considerable burden because more than 50% of patients are not covered by insurance. The NFED, based in Mascoutah, Illinois, is committed to providing help and hope to families around the globe who are affected by this condition.
WE CONTINUE OUR TRADITION OF SPONSORING CHARITABLE MISSIONS AND ACTIVITIES THAT BRING BASIC DENTAL CARE AND EDUCATION TO THE UNDERPRIVILEGED
Today, several thousand individuals affected by ED in more than 65 countries receive services from the Foundation, which has provided financial assistance and information, in addition to connecting affected families with each other and with practitioners.
Once patients reach adulthood, they can be treated with dental implants, which make a significant difference. Straumann provides free implants to ED patients, but these represent a small portion of the overall treatment costs. We work with the NFED to expand its network of dental professionals who provide free services to ED patients; we also support the foundation with financial aid.
Cleft lips and palates (clefts) are one of the most common major birth defects in developing countries and occur in 1 in 600 to 1000 births. Despite the fact that surgery is straightforward, it is not widely available, with the result that millions of children suffer from unoperated clefts. Although the condition is not usually life-threatening, patients are stigmatized by their appearance and have great difficulty in eating and speaking. Straumann contributes to non-profit organizations providing free surgery to children with clefts in developing countries.

Casarin RCV, Ribeiro Edel P, Nociti FH Jr, Sallum AW, Ambrosano GMB, Sallum EA, Casati MZ. Enamel matrix derivative proteins for the treatment of proximal class II furcation involvements: a prospective 24-month randomized clinical trial. J Clin Periodontol 2010;37(12):1100-1109.
A total of 12 patients with bilateral proximal furcation defects ≥ 5 mm and bleeding on probing were treated with open flap debridement and EDTA alone (control) or in combination with EMD (test). Clinical parameters were evaluated prior to treatment and after 6, 12 and 24 months. No significant differences were observed after 24 months. Probing depth reduction was 1.9 ± 1.6 mm and 1.0 ± 1.3 mm in the test and control groups, respectively, and the gain in relative horizontal clinical attachment level was 1.4 ± 0.9 mm and 0.7 ± 1.3 mm in the test and control groups, respectively. After 24 months, only five class II furcations remained in the test group, compared to 10 in the control group (p < 0.05).
S
® D ENTAL I MPLANT Sy STEM
Bilhan H, Kutay O, Arat S, Çekici A, Cehreli MC. Astra Tech, Branemark, and ITI implants in the rehabilitation of partial edentulism: two-year results. Implant Dent 2010;19(5):437-446.
In 26 patients, Astra Tech implants (42), Brånemark implants (36) and Straumann ® implants (29) were placed; abutment connection was performed for the Astra Tech and Brånemark implants after 3 months and all implants received fixed pros -
theses after 4 months. Clinical parameters were recorded after 6, 12 and 24 months and radiographic bone level was recorded after 2 years. Implant survival was 100 % for all systems. Plaque index and peri-implant inflammation scores were higher for the Brånemark implants in the first year. Marginal bone loss around ITI and Astra Tech implants was similar at 2 years (p > 0.05). The marginal bone loss around Branemark implants was higher than Astra Tech implants (p < 0.05) but similar to ITI implants at 2-year recall appointment (p > 0.05).
Nedir R, Nurdin N, Vazquez L, Szmukler-Moncler S, Bischof M, Bernard J-P. Osteotome sinus floor elevation technique without grafting: a 5-year prospective study. J Clin Periodontol 2010;37(11):1023-1028.
Osteotome sinus floor elevation was performed without grafting in 17 patients (mean residual bone height 5.4 ± 2.3 mm) and a total of 25 Straumann SLA® implants (10 mm in length) were placed. Implant survival after 5 years was 100 % and the mean increase in peri-implant bone was 3.2 ± 1.3 mm, while implant protrusion into the sinus decreased from 4.9 ± 1.9 mm at baseline to 1.5 ± 0.9 mm. Mean crestal bone loss was 0.8 ± 0.8 mm, which stabilized over 5 years; bone gain after 1 year was noted at 20 implants. Grafting is therefore not required for bone gain of at least 3 mm.
Bosshardt DD, Salvi GE, Huynh-Ba G, Ivanovski S, Donos N, Lang NP. The role of bone debris in early healing adjacent to hydrophilic and hydrophobic implant surfaces in man. Clin Oral Implants Res 2011;22(4):357-364.
Straumann experimental implants (4.0 mm long and 2.8 mm diameter) with either an SLA or SLActive surface were placed in the retromolar region in 28 volunteers and retrieved by
Simply doing more
trephine after 7, 14, 28 and 42 days. All surfaces were partially coated with bone debris and new bone formation was observed after 7 days. New bone gradually increased over time while fractions of old bone, soft tissue and bone debris gradually decreased. New bone was higher with SLActive after 2 and 4 weeks. The change in bone debris:soft tissue ratio changed significantly from 7 to 42 days for both SLActive and SLA. The bone debris:soft tissue ratio suggested that bone debris had a significant influence on the initiation of bone deposition.
Buser D, Wittneben J, Bornstein MM, Grütter L, Chappuis V, Belser UC. Stability of contour augmentation and esthetic outcomes of implant-supported single crowns in the esthetic zone: 3-year results of a prospective study with early implant placement postextraction. J Periodontol 2011;82(3):342-349.
A total of 20 patients received implant-supported crowns on Straumann Bone Level implants in the esthetic zone, and clinical, radiologic, and esthetic parameters were recorded for 3 years follow-up. All implants were successfully osseointegrated and stable, with good peri-implant soft tissues after 3 years. Good results were obtained for the pink and white
esthetic scores, with white esthetic scores being slightly superior. Mean crestal bone loss was 0.18 mm after 3 years; bone loss from 0.5 to 1.0 mm was observed at only two implants, one of which showed minor recession of the facial mucosa (< 1 mm).
Zupnik J, Kim SW, Ravens D, Karimbux N, Guze K. Factors associated with dental implant survival: a 4-year retrospective analysis. J Periodontol 2011;82:1390-1395.
A retrospective chart review of patients at the Harvard School of Dental Medicine (HSDM) who had one of two types of rough-surface implants (group A: Straumann SLA®, group B: Nobel TiUnite ®) placed by periodontology residents from 2003 to 2006 was performed. Demographic, health, and implant data were collected and analyzed by multi-model analyses to determine failure rates and any factors that may have increased the likelihood of an implant failure. The study cohort included 341 dental implants. The odds ratio for an implant failure was most clearly elevated for diabetes (2.59) and implant surface group B (7.84), and male groups (4.01).
There was no significant difference regarding the resident experience. The success rate for HSDM periodontology residents was 96.48% during the 4-year study period.




Cochran DL, Jackson JM, Bernard J-P, ten Bruggenkate CM, Buser D, Taylor TD, Weingart D, Schoolfield JD, Jones AA, Oates TW Jr. A 5-year prospective multicenter study of early loaded titanium implants with a sandblasted and acid-etched surface. Int J Oral Maxillofac Implants 2011;26(6):1324-1332.
A total of 439 implants were placed in 135 partially and fully edentulous patients, with abutments connected after 6 weeks in type II and III bone and after 12 weeks in type IV bone. Evaluations were performed for up to 5 years, after which the cumulative implant survival and success rates were 99.1% and 98.8%, respectively; all implant failures were between surgery and 1 year. SLA-surfaced implants can therefore be loaded after 6 weeks in type II and III bone and maintain high survival and success over 5 years.
STr AUMANN N OrT h A M eric A edUc AT i ON cOU rSeS
For more information on programs in the US contact the Straumann US Education Department at 978/747 2553 or education.us@straumann.com or visit us on the website: www.straumann.us and click on the courses tab.
For more information on programs in Canada contact the Straumann Canada Department at 905/319 2900 or education.ca@straumann.com or visit us on the website: www.straumann.ca.com and click on the courses tab.
March 23, 2012
Dental Implant Complications Symposium: Etiology, Prevention & Treatment new york, ny
Lecturers: Dr. Stuart Froum et. al.
Target Audience: Dental Clinicians
Products: Implants
Registration: Straumann.cvent.com/event/march23
March 30-31, 2012
Digital Interdisciplinary Dentistry farmington, Ct – university of Connecticut
Lecturers: Dr. Don Somerville, Dr. David Shafer and Charlie Meneguzzo
Target Audience: Interdisciplinary Team consisting of Surgeon, Restorative Dentist and Lab Technician
*must attend in a team
Product: SGS, CADCAM, Implants, Restorative Components
For more information on this program or to register: http://smile.uthscsa.edu
March 30-21, 2012
The Art, Science and Business of Clinical Implant Practice
las vegas, nv
Lecturers: Dr. Paul Fugazzotto, Dr. Kanyon Keeney
April 20-21, 2012
The Art, Science and Business of Clinical Implant Practice
Washington, dC
Lecturers: Dr. Paul Fugazzotto, Dr. Kanyon Keeney
April 20-21, 2012
Digital Interdisciplinary Dentistry
louisville, Ky – university of louisville
Lecturers: Dr. Dean Morton, Dr. Jay Beagle, Travis Roy
Target Audience: Interdisciplinary Team consisting of Surgeon, Restorative Dentist and Lab Technician
*must attend in a team
Product: SGS, CADCAM, Implants, Restorative Components
April 23, 2012
"Are y ou Referring to Me?" Strategies for Marketing the Oral and Maxillofacial Surgery Practice
JaWS Society annual meeting
Dr. David Schwab


April 27-28, 2012
Understanding the Basics of Surgical and Restorative Dental Implant Therapy
detroit, mi – university of detroit mercy
Lecturers: Ahmad M. Fard DDS, MS and Anthony Neely, DDS, PhD
Target Audience: Clinicians
Products: Implants
For more information on this program or to register: http://dental.udmercy.edu/ce
May 18, 2012
Advanced Implant Surgery & Tissue Grafting
dallas, tX at Baylor university
Lecturer: Dr. Thomas Wilson
May 19, 2012
Advanced Implant Surgery & Tissue Grafting –Cadaver Course
dallas, tX at Baylor university
Lecturers: Dr. Thomas Wilson and Dr. Jim Ruskin
June 4-8, 2011
ITI Education Week
Boston, ma
July 27-28, 2012
Digital Interdisciplinary Dentistry
Baylor university, dallas, tX
Lecturers: Dr. Frank Higginbottom and Dr. Thomas Wilson
Target Audience: Interdisciplinary Team consisting of Surgeon, Restorative Dentist and Lab Technician
*must attend in a team
Product: SGS, CADCAM, Implants, Restorative Components
For more information on this program or to register: http://www.bcdce.com/courses/course/category.php?id=2
August 5-12, 2012
Simplification and Predictability of Implant Dentistry
alaska Cruise
Lecturer: Dr. Robert Vogel
Target Audience: Entire Implant Team
Products: Implants
To register please go through www.kennedyseminars.com and click on “REGISTER NOW“
November 2-3, 2012
Temple University 2nd Annual Straumann Lecture –Current Trends and Techniques in Planning and Restoring Implants in the Esthetically Demanding Patient
philadelphia, pa
Lecturer: Dr. Will Martin
December 14-15, 2012
Digital Interdisciplinary Dentistry
Baylor university, dallas, tX
Lecturers: Dr. Frank Higginbottom and Dr. Thomas Wilson
Target Audience: Interdisciplinary Team consisting of Surgeon, Restorative Dentist and Lab Technician
*must attend in a team
Product: SGS, CADCAM, Implants, Restorative Components
For more information on this program or to register: http://www.bcdce.com/courses/course/category.php?id=2
Simply doing more

ITI Education Week Boston – June 4-8, 2012
Comprehensive Implant Dentistry: From Treatment Plan to Clinical Implementation
Subsidiary companies Distributors
HQ Switzerland
i nstitut s traumann ag
Peter m erian-Weg 12
4002 Basel
tel. +41/61 965 11 11
Fax +41/61 965 11 01
Subsidiary companies:
Australia/New Zealand
s traumann Pty. Ltd.
7 g ateway Court
Port m elbourne 3207
victoria
tel. +61/39 64 67 060
Fax +61/39 64 67 232
Austria/Hungary
s traumann g mb h a ustria
Florido tower
Floridsdorfer h auptstr. 1
1210 Wien
tel. +43/12 94 06 60
Fax +43/12 94 06 66
Belgium
s traumann
Belgicastraat 3
1930 Zaventem
tel. +32/27 90 10 00
Fax +32/27 90 10 20
Brazil
s traumann Brasil Ltda rua Funchal 263
04551-060 s ão Paulo
tel. +55/11 30 89 66 83
Fax +55/11 30 89 66 84
Canada
s traumann Canada Ltd.
3115 h arvester road
s uite 100
Burlington/O n -L7n 3n8
tel. +1/905 319 29 00
Fax +1/905 319 29 11
Czech Republic
s traumann s.r.o. n a Žertvách 2196
180 00 Prague 8
tel. +420/284 094 650
Fax +420/284 094 659
Denmark
s traumann Danmark aps h undige s trandvej 178
2670 g reve
tel. +45/46 16 06 66
Fax +45/43 61 25 81
Finland
s traumann Oy Fredrikinkatu 48a 7 krs. 00100 h elsinki
tel. +358/96 94 28 77
Fax +358/96 94 06 95
France
s traumann France
3, rue de la g almy – Chessy
77701 m arne-la-vallée cedex 4
tel. +33/164 17 30 00
Fax +33/164 17 30 10
Germany
s traumann g mb h
Jechtinger s traße 9 79111 Freiburg
tel. +49/76 14 50 10
Fax +49/76 14 50 11 49
Great Britain
s traumann Ltd.
3 Pegasus Place, gatwick road Crawley rh109ay, West s ussex
tel. +44/12 93 65 12 30
Fax +44/12 93 65 12 39
Italy
s traumann i talia s.r.l.
viale Bodio 37a
20158 m ilano
tel. +39/02 39 32 831
Fax +39/02 39 32 8365
Japan
s traumann Japan K.K. s apia tower 16F, 1-7-12 m arunouchi, Chiyoda-ku, tokyo, 100-0005 Japan
tel. +81/352 18 26 00
Fax +81/352 18 26 01
Mexico
s traumann m éxico sa de C v
rubén Darío # 281 int. 1702
Piso 17
Col. Bosque de Chapultepec 11580 m éxico DF.
tel. +52/55 5282 6262
Fax +52/55 5282 6289
Netherlands
s traumann B.v. Postbus 338
3400 ah i Jsselstein
tel. +31/30 60 46 611
Fax +31/30 60 46 728
Norway
s traumann as P.O.Box 1751 vika
0122 Oslo
tel. +47/23 35 44 88
Fax +47/23 35 44 80
South Korea
s traumann s outh Korea
(formerly: B.i trading Co. Ltd.) 1467-75, s eocho3 -Dong, s eocho- g u, seoul
tel. +82/72 265 8777
Fax +82/72 265 8797
Spain/Portugal
s traumann s.a.
edificio a rroyo - a avda. de Bruselas, 38 Planta 1
28108 a lcobendas (m adrid)
tel. +34/902 400 979
Fax +34/913 449 517
Sweden
s traumann aB Fabriksgatan 13
41250 g öteborg
tel. +46/31 708 75 00
Fax +46/31 708 75 29
USA
s traumann usa , LLC
60 m inuteman road
a ndover, ma 01810
tel. +1/800 448 8168
+1/978 747 2500
Fa x +1/978 747 2490




This book, which presents 11 prominent clinical cases, is the product of an international competition organized by Straumann. The objective was to illustrate the esthetic results that can be achieved when using Straumann® Emdogain in combination with conventional surgical methods in the treatment of gingival recession. See page 18 of this issue of STARGET for more information.
Please contact your local Straumann sales team member if you would like to order a copy of this case book.