


Strep B’s Colorful Secret pg 2
Revisiting LDL Cholesterol pg 3

High School Essay Contest
A Double Edged Legacy pg 4


Strep B’s Colorful Secret pg 2
Revisiting LDL Cholesterol pg 3
High School Essay Contest
A Double Edged Legacy pg 4
Group B Streptococcus (Strep) is a highly infectious bacteria that can cause infection and complications like pneumonia in newborns. Dr. George Liu was studying this bacteria at UC San Diego, specifically interested in the toxin that makes it so infectious. Group B Strep uses the CYlE gene to produce this toxin, so by removing the gene, Dr. Liu could study the bacteria without the toxin. Removing the gene also stopped the bacteria from producing an orange pigment. Using these mutated bacteria, Liu showed that mice infected with the toxin-free Strep bacteria had higher survival rates than mice infected with the original, unmutated bacteria in his 2004 paper.
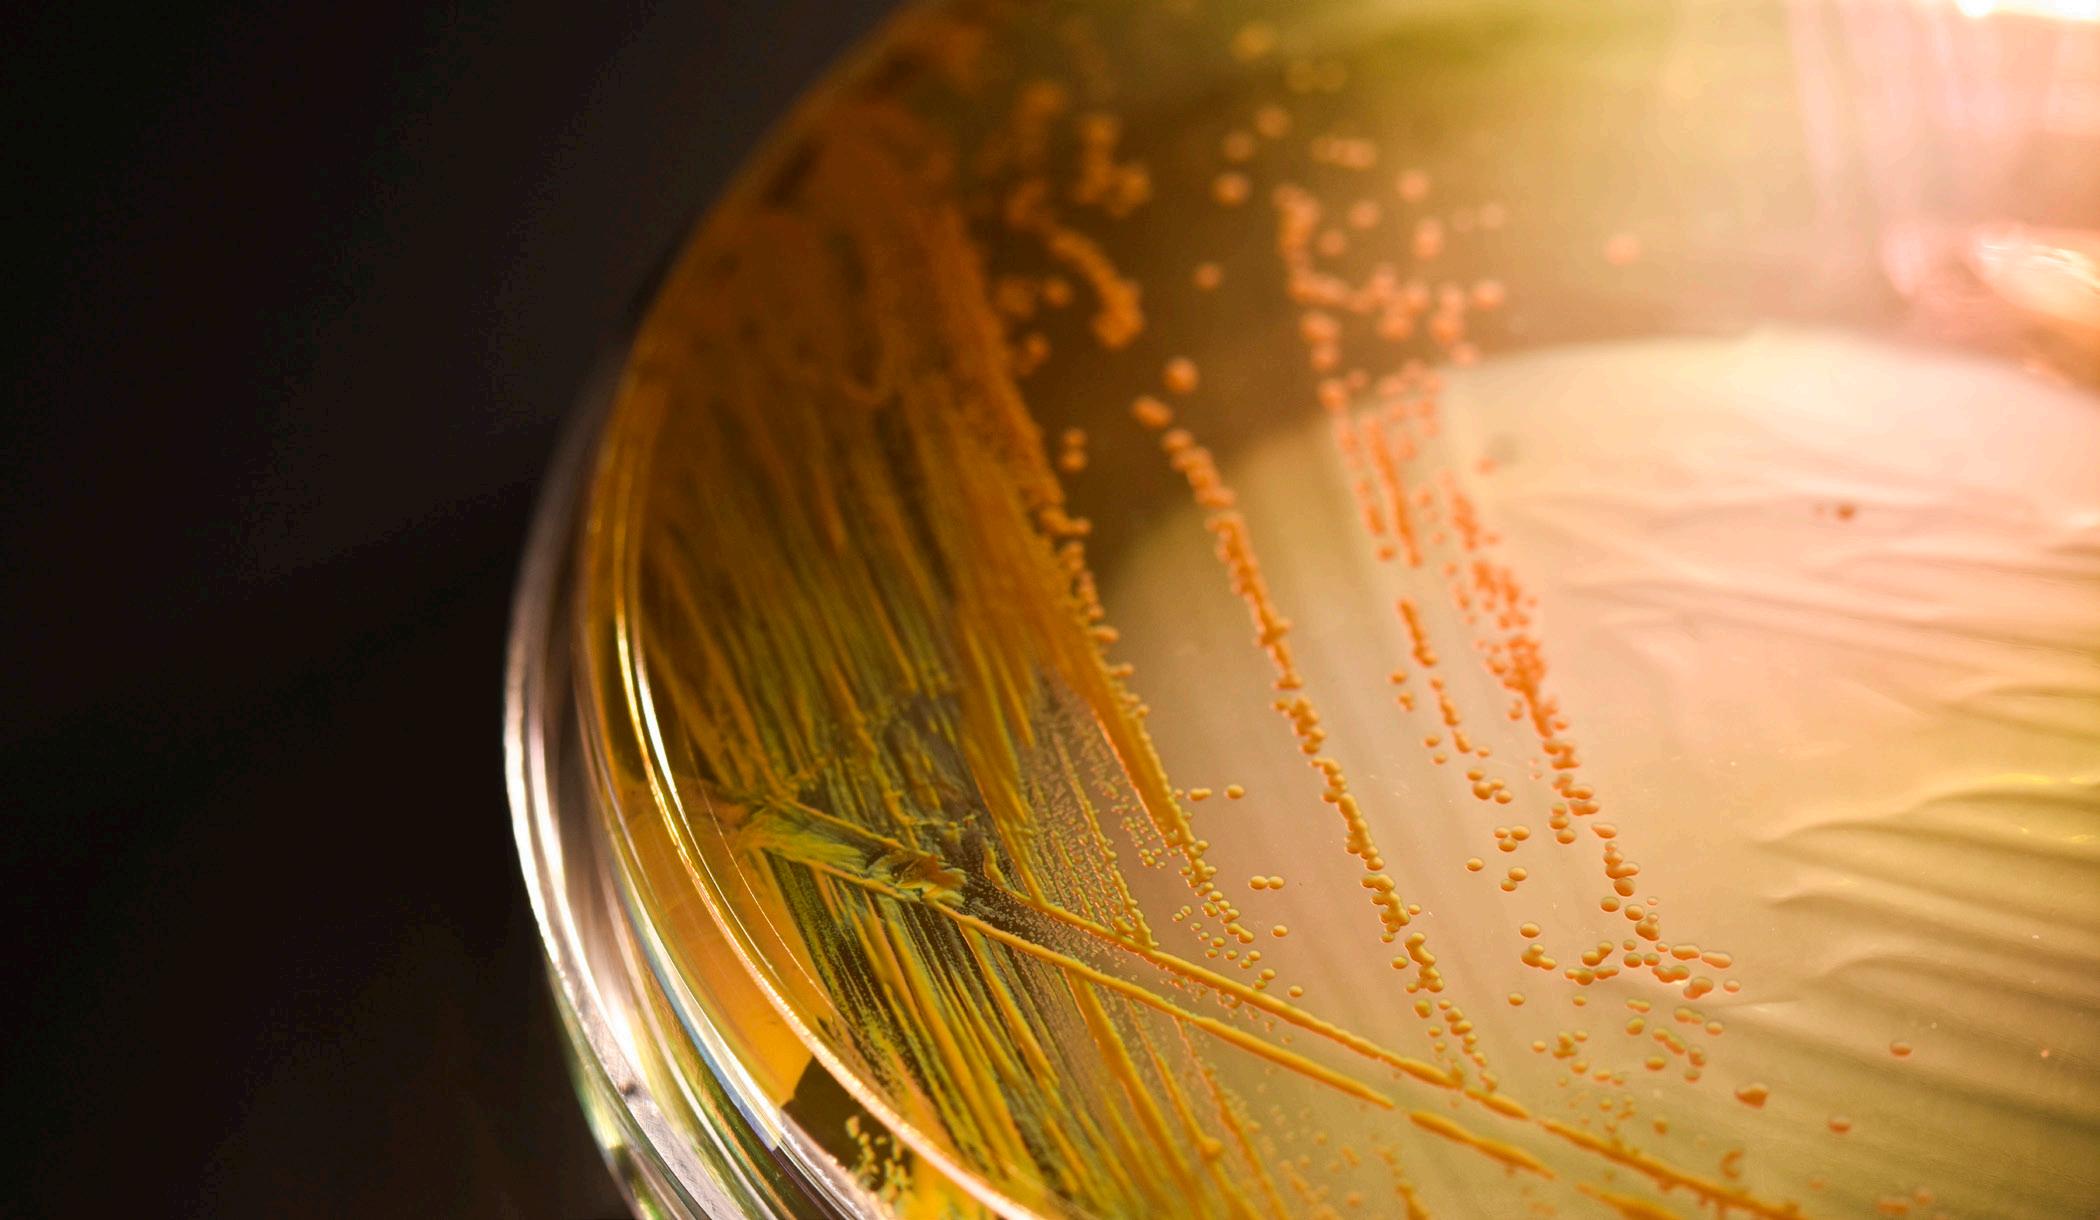
written by: Catherine Som De Cerff photographed by: Andre Lin
Despite the promising results, Dr. Liu noticed that many of his bacterial samples were dying off mysteriously. He found that the samples grown in plastic flasks were fine, it was only those grown in glass containers that were affected. Even stranger, the unmutated bacteria that contained the toxin and pigment-producing CYlE gene were far less affected than the mutated, pigment-free bacteria. The culprit? Bleach contaminating the glassware he was using to grow the bacteria. The autoclave - a dishwasher that sterilizes lab equipment - the lab was using was broken, so a student working in the lab was tasked with washing and disinfecting the glassware. The bleach wasn’t getting properly washed out, so it was killing bacteria cells that Dr. Liu was trying to grow.
Once Liu figured out the problem with his glassware, he could have written this off as a few botched experiments and ignored the results from contaminated bacteria. But, these results intrigued him. Why were the mutated bacteria more susceptible to bleach contamination? Was the toxin produced by the CYlE gene somehow protecting the bacteria from disinfectants? Or, was the orange pigment serving an unknown function, shielding the cells from bleach?
The answer came from an unsuspecting source: Dr. Liu’s mother’s advice. Liu was discussing his strange findings with his mom, when the orange color of group B
Strep bacteria reminded her of carrots. She mentioned to Liu that carrots are high in antioxidants, and the light-bulb went off in his head. The unmutated bacteria was orange because of a carotenoid pigment, the same pigment that turns carrots orange. This pigment is an antioxidant, meaning it can break apart oxygen containing compounds, like hydrogen peroxide and hypochlorite, also known as bleach. The orange pigment, then, could destroy the bleach, protecting the bacteria cell. The effect Dr. Liu was seeing wasn’t related to the toxin at all, it was because of the pigment that had previously been ignored.
Why, then, would a bacteria evolve to protect itself with an antioxidant pigment? Cells don’t encounter bleach on a regular basis. Or do they? The body’s immune cells actually produce oxidants like bleach and hydrogen peroxide that help fight infections like those caused by group B strep. Dr. Liu hypothesized that this antioxidant behavior is why the mutated, pigment-free bacteria were more susceptible to the accidental bleach contamination than the orangepigmented bacteria. In the same 2004 paper that demonstrated the strep B toxin’s impact on survivability in mice, Liu found that the unmutated orange bacteria were more than five times as likely to survive exposure to human immune cells than the mutated, pigmentless bacteria.
The problem now was that the toxin Dr. Liu had originally been studying and the orange, antioxidant pigments were inextricably linked. The CYlE gene coded for both the
toxin and the pigment, so there was no way to remove one without also removing the other. Thus, there was no way to ensure that the antioxidant “shield” behavior, as it came to be known, was only caused by the orange pigment and not by the toxin. To separate these two variables, Liu turned to a different bacteria species, Staphylococcus aureus.
Staphylococcus aureus (staph) is another human pathogen, like group B strep, that contains a carotenoid pigment that gives the bacteria a unique golden color. The golden pigment in staph is created by the crtM gene, a gene that unlike in group B strep, does not code for any other traits in the bacteria, meaning that the carotenoid pigments can be isolated for research. In Liu’s 2005 paper looking at mutant staph bacteria, he did indeed find that the unmutated, pigmented bacteria were more resistant to human immune cells than the mutated bacteria that lacked the golden pigment.
Dr. Liu credits most of this accidental discovery to the student and his mother. Without bleach- contaminated glassware and his mother’s insight into the antioxidant function of orange pigments, he likely wouldn’t have discovered this shieldlike behavior of carotenoid pigments in bacteria. His accidental discovery not only introduced a new function of carotenoid pigments, it presents a promising target for new antibiotics. A drug that removes a bacteria’s ability to shield itself from the immune system could help the body fight off infection more easily, helping those most at risk for bacterial infections.

Editors-in-Chief:

Editor-at-Large:
Head
Head
The longstanding reliance on low-density lipoprotein (LDL) cholesterol as the primary marker of cardiovascular disease (CVD) risk is a cautionary tale of reductionist thinking in biomedical research. For decades, the healthcare community prioritized LDL cholesterol over more comprehensive predictors of cardiovascular health, such as lipoprotein particle number (LDL-P) and systemic inflammation. This commentary examines the scientific and ethical dimensions of this error, analyzes its implications for public health, and evaluates the lessons it offers for modern research practices. By critically reflecting on the historical missteps of LDL-centric paradigms, we can explore how this case has reshaped the approach to evidence-based medicine and fostered a more integrated understanding of human health.
Scientific Oversight: LDL Cholesterol as a Surrogate for Cardiovascular Risk
The focus on LDL cholesterol emerged in the mid20th century from landmark studies such as the Framingham Heart Study, which identified correlations between elevated LDL cholesterol and CVD. While groundbreaking at the time, these findings conflated association with causation, overlooking the nuanced role of lipoproteins in atherogenesis. Subsequent research revealed that LDL cholesterol levels alone fail to account for the heterogeneity of cardiovascular risk. For example, patients with similar LDL cholesterol levels can exhibit markedly different risks based on their LDL particle count and size. These insights illuminated a fundamental flaw in the original hypothesis: LDL cholesterol is merely a surrogate marker, not a causal agent.
This reductionist focus persisted because LDL cholesterol was straightforward to measure and target therapeutically. Statins, which effectively lower LDL cholesterol, became a cornerstone of CVD prevention, further entrenching the LDL-centric model. However, this approach often left high-risk patients undiagnosed or undertreated, particularly those with elevated LDL-P but normal LDL cholesterol levels. By oversimplifying complex biological systems, this oversight perpetuated suboptimal care for millions of individuals.
The ethical ramifications of this scientific oversight are profound. Public health policies, influenced by the LDL hypothesis, emphasized the reduction of dietary cholesterol and saturated fat while promoting low-fat, high-carbohydrate diets. These recommendations, codified in national dietary guidelines, were disseminated to millions without sufficient evidence to support their efficacy. The unintended consequences were catastrophic: rising rates of obesity, insulin resistance, and type 2 diabetes. This public health crisis raises ethical questions about the responsibility of researchers, policymakers, and industry leaders to critically evaluate and revise guidelines when emerging evidence contradicts prevailing paradigms.
Furthermore, the pharmaceutical industry capitalized on the LDL-centric narrative to promote statins as a universal solution for cardiovascular prevention. While statins have undoubtedly saved lives, their widespread prescription often ignored the nuances of individual risk profiles, leading to overtreatment in low-risk populations and undertreatment in those with elevated LDL-P. This raises concerns about the role of profit motives in shaping research priorities and clinical practices, underscoring the ethical imperative to align scientific inquiry with patientcentered care.
The LDL cholesterol controversy underscores the dangers of reductionism in biomedical research and highlights the need for a systems-level approach to complex diseases. Three key lessons emerge from this case:
1. The Importance of Multidimensional Metrics: Advanced lipid testing, which measures LDL-P, apolipoprotein B (ApoB), and other markers, has demonstrated superior predictive power for CVD risk. Incorporating these metrics into routine care represents a significant advancement in personalized medicine. This shift reflects a broader recognition that disease risk cannot be distilled into a single biomarker but must be understood within the context of interconnected biological pathways.
2. The Role of Rigor in Research Translation: The persistence of the LDL hypothesis, despite mounting evidence of its limitations, highlights the inertia of established paradigms in science and medicine. This case emphasizes the need for rigorous evaluation of existing models and a willingness to challenge orthodoxy when data contradicts prevailing beliefs. It also underscores the importance of designing studies that account for multifactorial disease processes rather than focusing narrowly on isolated variables.
3. The Ethical Imperative of Adaptive Policy: The delayed revision of dietary guidelines, despite evidence undermining the cholesterol-diet hypothesis, illustrates the ethical obligation of policymakers to adapt to new evidence. Modern public health initiatives must prioritize transparency, actively engage with emerging research, and ensure that recommendations are rooted in the best available science. This requires collaboration among researchers, clinicians, and policymakers to align health interventions with evolving scientific understanding.
In response to the LDL cholesterol debacle, the biomedical community has adopted more sophisticated approaches to cardiovascular research and clinical care. Systems biology, which integrates data across molecular, cellular, and physiological levels, has become a cornerstone of modern science. This paradigm shift reflects a commitment to understanding diseases as dynamic, multifactorial processes rather than linear
written by: Christabel Graton illustrated by: Leo Harris
cause-effect relationships. Advances in bioinformatics, high-throughput omics technologies, and machine learning have further enabled researchers to identify novel biomarkers and therapeutic targets with unprecedented precision.
Additionally, the movement toward evidence-based and personalized medicine has transformed clinical practice. Risk assessment tools now incorporate a broader range of metrics, including genetic predisposition, inflammatory markers, and social determinants of health. These innovations exemplify how lessons from past mistakes can inform a more nuanced and equitable approach to healthcare.
The flawed understanding of LDL cholesterol as a singular risk factor for cardiovascular disease is emblematic of the broader pitfalls in biomedical research, where short-term experimental outcomes are often prioritized over long-term systemic understanding. By focusing on LDL cholesterol reduction as an immediate and measurable goal, decades of research and public health policies neglected the complexities of cardiovascular risk, ultimately contributing to unintended consequences such as the obesity and diabetes epidemics.
This case underscores the dangers of privileging short-term results—such as rapid reductions in LDL cholesterol—over longitudinal data that account for the dynamic interplay of metabolic, inflammatory, and lifestyle factors. Modern research practices must integrate a commitment to long-term studies that evaluate not only immediate outcomes but also the broader, systemic impacts of interventions on public health. Without such a shift, the biomedical community risks repeating the mistakes of the LDL-centric era, perpetuating cycles of incomplete understanding and reactive policies.
By embracing systems-level thinking, fostering transparency, and prioritizing long-term perspectives, the scientific community can transcend the limitations of reductionism and ensure that research serves the best interests of patients. This approach challenges researchers, clinicians, and policymakers to move beyond convenient proxies and invest in the development of comprehensive, multi-dimensional models of health.
As science advances, this case serves as both a cautionary tale and a guidepost, reminding us of the need for humility in the face of uncertainty, integrity in the pursuit of knowledge, and a steadfast commitment to long-term impacts over short-term gains. Only by adopting this mindset can we hope to achieve a truly patient-centered and ethical vision of modern medicine.
In the late 1950s, thalidomide was the seemingly perfect solution for the widespread issue of morning sickness, afflicting millions of pregnant women. Its purpose was simple: offer relief to women who suffered from nausea, primarily during their first trimester. But for many families, this miracle cure quickly turned into anyone’s worst nightmare. Thousands of babies were born with severe deformities, with many missing limbs or experiencing facial nerve paralysis, causing a dire issue to erupt that would change the course of medical history. In the wake of thalidomide’s devastating effects (particularly around the 1960s), the world realized not all drugs are safe during pregnancy, particularly for the developing embryos. This disaster also led to widespread changes in drug testing and regulatory processes, ensuring that future drugs would undergo rigorous safety evaluations before being released to the public.
Thalidomide was born to Franz Kunz in 1954 and was the product of this German chemist’s experimental trials at Chemie Grünenthal GmbH. According to German researchers studying thalidomide in 2001, the drug was regarded as particularly safe. In rodent testing, doses of thalidomide exceeding 10g/kg failed to show lethality, leading people to put their faith in this novel drug. In fact, in a 1964 article published by the Journal of Pediatrics, researchers examined thalidomide in rats for teratogenic effects (the ability to cause structural or functional abnormalities in a developing fetus or embryo) and noted that thalidomide failed to produce malformations and did not interfere with embryonic growth at all, with litters containing normalsized fetuses. These initial findings led to thalidomide’s widespread distribution as a non-prescribed sedative in twenty countries, with sales reaching a shocking 14.6 tons in Germany alone.
However, two doctors weren’t quite convinced about the drug’s miraculous abilities. By 1961, two physicians—Dr. William McBride in Australia and Dr. Widukind Lenz in Germany— independently arrived at the same realization about thalidomide and its possible link to birth defects. According to an article by researchers at Grand Valley State University in 2011, McBride and Lenz suspected a link between the two after the obstetrician and pediatrician noticed that 41 in 46 mothers of babies with phocomelia (shortened limbs) had taken thalidomide in the early stages of their pregnancies. This suspicion was later confirmed as thousands of children were born with deformities, including amelia (absence of limbs), and abnormalities affecting the ears, eyes, heart, and gastrointestinal tract. As a result, thalidomide was withdrawn from the market in the twenty countries that had sold the drug. The United States, however, never approved thalidomide for sales and distribution, thanks to the vigilance of Dr. Frances Kelsey, a U.S. Food and Drug Administration officer who denied approval based on insufficient safety data. An article written by Rehman, Arfons, and Lazarus in 2011 explains Kelsey’s decision to pause the approval process played a key role in preventing the
widespread use of thalidomide in the U.S., and this very decision may have pre]vented millions more from suffering the same fate.
The teratogenic effects of thalidomide can be attributed to the biological changes that the drug is responsible for inside the body, many of which are not fully understood. According to an article by the Therapeutic Advances in Hematology in 2011, thalidomide possesses anti-inflammatory, immunomodulatory (modifying the immune system), and anti-angiogenic (inhibiting the formation of blood vessels) properties. One key action of thalidomide is its selective inhibition of TNF-α—tumor necrosis factor alpha— production in human white blood cells, scientifically known as monocytes. This protein is a proinflammatory cytokine, and its primary role is to work as a signaling molecule in immune responses. This means normal inflammatory responses are disrupted in embryonic development, explaining the deformities.

In addition, thalidomide can also cause birth defects by increasing reactive oxygen species (ROS) and inducing oxidative stress, specifically by damaging DNA and disrupting essential signaling pathways involved in limb development. Though ROS are naturally produced during cellular processes, ROS can damage DNA and proteins, causing mutations and potentially leading to cell death or uncontrolled growth. According to an article published in the Toxicological Sciences in 2011, the drug binds to cereblon (CRBN), a critical protein involved in cellular processes during embryonic and early fetal development. This binding can interfere with normal limb development, which leads to phocomelia and amelia, deformities that were observed in large numbers of children.
Despite its rollercoaster of a history, thalidomide has found a place in modern medicine. Today, thalidomide is used to treat cancers such as multiple myeloma, myelodysplastic syndrome (a group of blood disorders characterized by abnormal blood cell production in the bone marrow), and certain types of melanoma. However, thalidomide remains under strict scrutiny and regulatory controls, especially due to its teratogenic risks. The World Health Organization wrote in 2011 that thalidomide should not be used in areas of poorer medical surveillance due to the risk of birth defects that run rampant in these regions. Thalidomide’s approval in certain treatments of diseases, including leprosy, has been carefully monitored since the 1960s to prevent another catastrophe. This tragedy taught the world valuable information about approving correct drugs and designing experimental tests, and its effects increased public awareness regarding potential risks in pharmaceutical treatments. While thalidomide may have redeemed itself from its tumultuous history, the story continues to influence the way modern medicine operates to this day, and the lessons learned from thalidomide encapsulate the need for safety and transparency in the medical field to protect ourselves and our future generations.
written by : Keya Patel illustrated by: Maia Lazor