

Forecasting Medical Costs
Enables Timely Intervention
At the heart of expecting the unexpected
Leverage captive insurance to self-fund your healthcare.
As your business grows, so will your healthcare expenses. Customized captive insurance from QBE creates strength to self-fund your catastrophic employee healthcare coverage, allowing you to increase transparency and reduce the cost of risk. The QBE Captive Curve® solution model removes barriers to entry and allows you to move easily to new strategies.
Take advantage of QBE’s Captive Curve solutions:
• Fronted policy that is “AA-” rated by S&P for single-parent and group captive programs.
• Reinsurance placement covering direct writing captive insurers assuming medical stop loss (MSL) risk.
• Agora, an open MSL group captive that makes it more efficient to participate in a group program.
Together, we’ll find a solution so no matter what happens next, you can stay focused on your future.



Written By Laura Carabello
Philip C. Giles,
Written By Anthony Murrello
Written By Bruce Shutan
(ISSN

Forecasting Medical Costs Enables Timely Intervention
YouYWritten By Laura Carabello
have probably heard about a “Choose Your Own Adventure” book that allows readers to select the next chapter or ending that leads to different paths and outcomes based on the reader's decisions. The reader actually becomes the main character, changes the book’s plot and gets to choose what path the characters take -- which changes how the story unfolds.
This is an appropriate analogy for forecasting medical claims where access to the right data, at the right time, enables healthcare decision-makers to intervene in the member treatment journey and impact the outcome.
“For stakeholders throughout the self-insured ecosystem, the ability to predict where costs are heading, not just where they've been, is the defining challenge of modern risk management,” Rajiv Sood, General Manager, Insurance & Risk, Evidium, Inc. “Most analytics tools in use today answer the wrong question. They tell you what happened -- a look in the rear-view mirror – rather than seeing through the front windshield for a clear answer to what's coming, and why.”
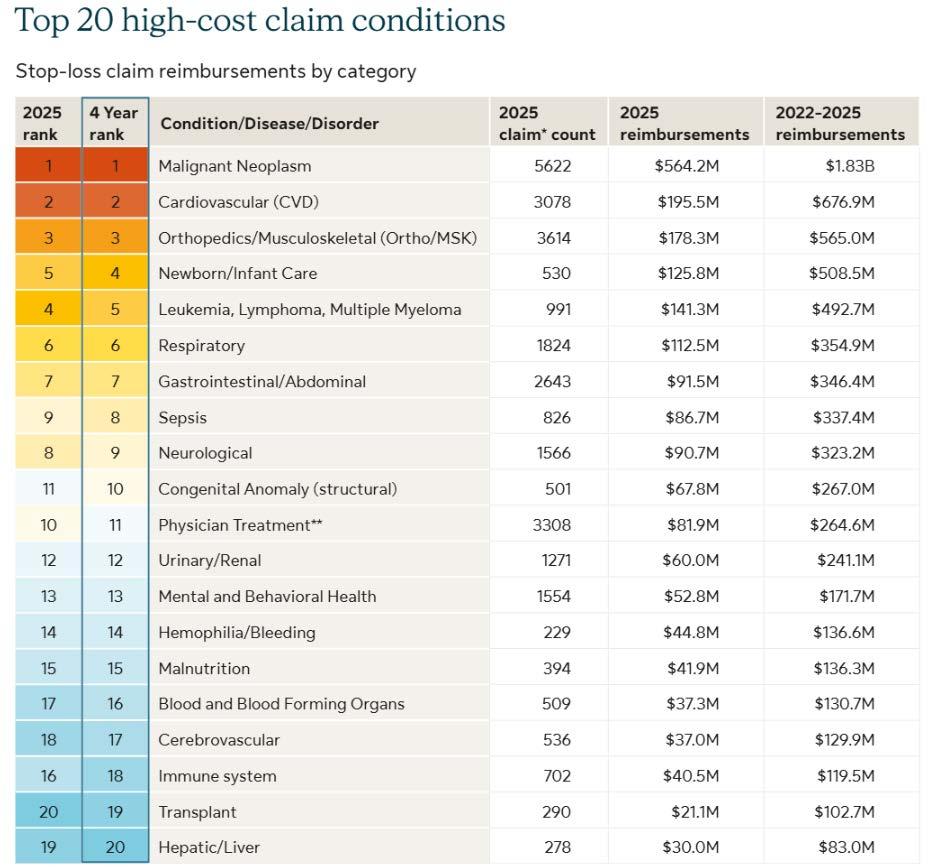
Sood says this gap is especially acute in high-cost conditions like oncology, which has ranked among the top five causes of employer healthcare spending for four consecutive years. With more than 18 million cancer survivors in the U.S. today — a number projected to surpass 26 million by 2040 — the downstream cost burden extends well beyond acute treatment into chronic condition management, care coordination and stop-loss exposure that plan sponsors struggle to anticipate.

“A core problem is data fragmentation,” he continues. “Clinical, claims, biomarker, Rx and historical treatment data typically reside in separate systems, slowing processes and obscuring the complete picture of a member's care journey. Claims data tells you a test was ordered, not what the result revealed. It records that a member moved to a second line of therapy, not whether that escalation was clinically appropriate or an artifact of coding convention. Without clinical context layered alongside claims, cost forecasting remains reactive rather than predictive.”
He points to the Evidium’s AI-powered platform which changes the equation, adding, “Rather than generating risk scores that signal a problem without explaining it, Evidium models each member's actual clinical journey at the individual level. This empowers organizations to track disease progression, care patterns, and cost trajectories with full clinical transparency. Every insight is explainable and auditable, giving nurse case managers, TPA analysts and stop-loss underwriters the context they need to act early and defend their decisions to plan sponsors.”
Earlier visibility into emerging high-cost conditions means the difference between intervention and reaction, the ability to manage costs vs. absorbing them.
“Forecasting isn't a back-office function – it's a fiduciary imperative,” he avers.

Source: Smart Health Asia
WHAT’S WORKING
In the Milliman MedInsight 2025 Payer Market Survey, reflecting input from data and analytics practitioners at mid-to-large payer organizations, most respondents (85%) indicated that using and analyzing data to generate insights is a primary part of their role. Nearly half (49%) also reported responsibility for identifying clinical and business needs and translating them into analytics requirements and solution specifications.
Rajiv Sood

Brad Hansen VP of Provider Relations
THE REINSURANCE PERSPECTIVE

Proactive care management combined with predictive analytics has significant potential to help plans identify members who are likely to become high-cost claimants, allowing for earlier clinical and financial intervention before conditions worsen.
Jakki Lynch, RN, CCM, CMAS, CCFA, Director, Cost Containment, Carbon Stop-Loss, shares, “By analyzing medical claims, pharmacy data, diagnoses, demographics, specialty drug utilization, and provider referral activity, we believe predictive modeling can help identify members at risk for highcost events. For example, predictive models can assist plans in identifying maternal risk factors such as diabetes, hypertension, or inconsistent prenatal care that increase the likelihood of premature delivery.”
While Lynch and colleagues are highly interested in the capabilities these technologies offer, they continue evaluating critical considerations related to data security, privacy protections, PHI handling and data governance.
“We believe these operational safeguards must be fully addressed before broader implementation,” she cautions. “We also recognize the absolute importance of validating predictive models for accuracy and equity.” Recent industry research published in Health Affairs underscores that many healthcare organizations are still struggling to implement consistent governance standards, noting a distinct divide in how effectively platforms are locally evaluated for clinical accuracy and bias.
“Moving forward, reinsurers and plans must ensure that any deployed models strictly align with emerging industry compliance standards specifically ensuring that algorithms remain Fair, Appropriate, Valid, Effective, and Safe (the FAVES principles),” says Lynch. Furthermore, the operational effectiveness of these predictive models remains entirely dependent upon the quality and completeness of the data available.
“Reinsurers routinely receive fragmented, snapshot data rather than complete clinical pictures, which can obscure a member’s true trajectory of care,” she explains. “The more comprehensive, accurate, and timely the data received, the more effectively predictive models can support underwriting visibility, early risk identification and overall cost containment efforts.”
EMPLOYER MARKET FRENZIED TO ADDRESS HIGH COST CLAIMS
“Forecasting has always existed in healthcare, but it used to be a luxury good,” shares Barbora Howell, CEO, Co-Founder, TrueClaim. “AI has made it a utility. Organizations that could never have justified building a predictive analytics team can now plug their data into models that deliver member-level risk insights on day one. The barrier is no longer technology or talent; it's the willingness to act.”
Jakki Lynch

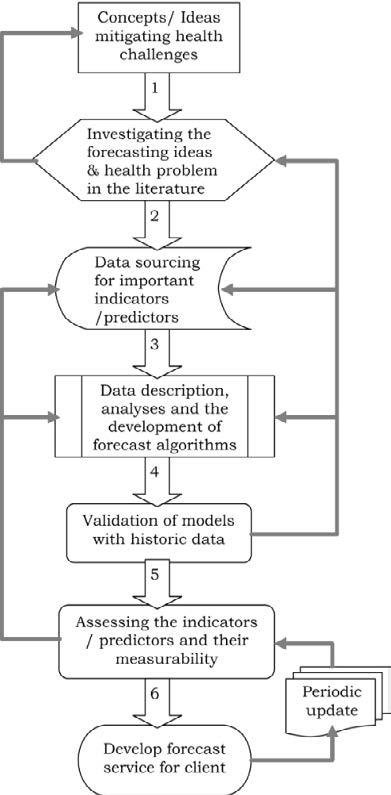
In the maelstrom of runaway costs, stakeholders recognize the value of key tools that have some overlap but are highly productive in forecasting health events. Since the raw pricing data can be large and cover multiple conditions, industry thought leaders say it is necessary to provide an engine to process the data to facilitate its usage and understanding. Many recommend creating computational models that predict healthcare costs for various patient conditions and demographics.
Today, many plan sponsors ascribe to the belief that proactive care management, including predictive analytics, can identify patients likely to become high-cost, allowing for interventions before conditions worsen.
“At the end of the day, no matter how well we can predict cost, it has no bearing on prevention,” clarifies Michelle Bounce, SVP of Client Operations, VBA. “Current care management models that focus on telephonic outreach are relatively ineffective -- but there is hope. Our current technological landscape offers our industry the opportunity for Impactability Modeling.”
She explains that this model allows for better identification of ‘Who’ is most likely to be impacted by interventions in a given risk pool.
“Imagine reinvested dollars being wasted, chasing people who are unlikely to engage into more effective care management like onsite/near site clinics, stronger transitional care models and significant incentivebased plan models focusing on quality of care,” says Bounce.
Amalgamated Life Insurance Company Medical Stop Loss Insurance—
The
Essential, Excess Insurance
As a direct writer of Stop Loss Insurance, we have the Expertise, Resources and Contract Flexibility to meet your Organization’s Stop Loss needs. Amalgamated Life offers:
• Specialty Rx Savings Programs and Discounts
• “A” (Excellent) Rating from A.M. Best Company for 48 Consecutive Years
• Licensed in all 50 States and the District of Columbia
• Flexible Contract Terms
• Excellent Claims Management Performance
• Specific and Aggregate Stop Loss Options
• Participating, Rate Cap and NNL Contract Terms Available


Michelle Bounce

Rethink what’s possible with
your stop-loss partner
For over 40 years, Sun Life has partnered with self-funded employers to help manage risk. Today, we’re continuing to evolve, connecting stop-loss protection with programs designed to help employees access appropriate care for complex and high-cost conditions.
Clinical 360+ transforming care for everyday and complex health challenges
Our enhanced program builds on the industry-leading Clinical 360 foundation, which achieved over $68 million in savings in 2025. Available for select clients, this advancement adds personalized care pathways and expert navigation with the goal to deliver even greater value. Through proactive outreach and dedicated support, your employees gain seamless access to specialized programs, digital health tools, and clinical guidance—all designed to improve health outcomes while managing costs effectively.
*Hinge Health will be provided to eligible members at Sun Life’s expense through the first policy year.
Learn more about our offerings by scanning:

It’s time to reconsider what you expect from your stop-loss partner. Let Sun Life support your business with innovative health solutions that prioritize access to quality care.*
Ask your Sun Life Stop-Loss Specialist about Clinical 360+ today.
Sun Life is not responsible or liable for the care, services, or advice provided by Somatus, OptiMed Health Partners, or Hinge Health, and reserves the right to discontinue this service at any time.
Sun Life will collaborate with your TPA on eligibility and applicability of programs. Health Navigator is provided by PinnacleCare. PinnacleCare is a member of the Sun Life Financial Inc. (“Sun Life”) family of companies. PinnacleCare and its employees do not diagnose medical conditions, recommend treatment options or provide medical care, and any information or services provided should not be considered medical advice. Any medical decisions should be made only after consultation with and at the direction of the member’s medical provider. Any person or entity who provides health care services following a referral or other service provided does so independently and not as an agent or representative of PinnacleCare. Group stop-loss insurance policies are underwritten by Sun Life Assurance Company of Canada (Wellesley Hills, MA) in all states, except New York, under Policy Form Series 07-SL REV 7-12 and 22-SL. In New York, Group stop-loss insurance policies are underwritten by Sun Life and Health Insurance Company (U.S.) (Lansing, MI) under Policy Form Series 07-NYSL REV 7-12 and 22-NYSL. Policy offerings may not be available in all states and may vary due to state laws and regulations. Not approved for use in New Mexico.
© 2026 Sun Life Assurance Company of Canada, Wellesley Hills, MA 02481. All rights reserved. The Sun Life name and logo are registered trademarks of Sun Life Assurance Company of Canada. Visit us at www.sunlife.com/us.
BRAD-6503-af
Source: SunLife 2026.
Lynch believes organizations can significantly reduce financial risk by identifying high-risk members earlier and implementing proactive clinical management strategies designed to prevent avoidable hospitalizations, ER visits, and worsening disease progression.
“Organizations that closely manage their populations through strong care coordination, medication adherence programs, accessible outpatient care and early intervention strategies are consistently better positioned to mitigate catastrophic claim severity and reduce overall plan volatility,” she says. “However, even with the strongest proactive care management, certain catastrophic conditions and complex disease progressions remain fundamentally unavoidable, and acute, high-cost events will still occur. As a result, rigorous backend financial containment strategies remain equally vital in managing overall catastrophic risk exposure.”
UNIVERSITY

At the start of reinsurance relationships, Lynch and colleagues conduct a structural evaluation of how closely their clients manage their members, looking at what clinical and cost containment programs they have active, and how effectively they identify and engage high-risk claimants.
“Through this upfront assessment, combined with analyzing claims data within our own platform, we can better isolate specific exposure areas and evaluate where additional financial risk mitigation strategies are required,” she continues. “We actively assist our clients in securing optimized, prenegotiated contract rates for catastrophic conditions involving transplants, ventricular assist devices (VADs), congenital heart disease (CHD), complex oncology and cell and gene therapies, while also supporting targeted, one-off negotiations for costly out-ofnetwork admissions.”
Additionally, pre-payment forensic bill review paired with a detailed medical record review remains a critical pillar of catastrophic claim management.
“This is particularly vital on high-dollar facility claims that frequently contain upcoding, unbundled billing, excessive markups on implants and specialty drugs, or charges related to hospital-acquired conditions,” says Lynch.
“Ultimately, even the strongest provider contracts are only as effective as the underlying billed charges, making detailed pre-payment claim auditing an essential tool to protect plan assets and control catastrophic exposure.”
ROLE OF CASE MANAGEMENT
Case management is the operational backbone that turns insight into action. By coordinating care, supporting chronic condition and disease management programs that identify lower-risk individuals before their conditions advance, and reinforcing adherence to treatment plans, case managers help ensure patients receive care in the right setting and at the right time.

Choquette affirms, “This not only improves health outcomes but also helps prevent costly escalations that drive financial risk. Case management remains central to this strategy, directing patients toward the most appropriate level of care and reinforcing preventive health measures, including pre-and post-operative outreach.”
She maintains that AI and ML enhance these efforts rather than replace them, noting, “Predictive analytics identifies risk, while AI strengthens execution by streamlining administrative tasks and improving workflow efficiency. By reducing manual burdens, AI allows clinicians to focus more on patient interaction and care delivery. In this way, technology supports better decision-making and enables care teams to apply their clinical skills more effectively. While forecasting is possible with traditional analytics, the scale, speed, and precision required today make AI an increasingly valuable component.”
FUNCTIONALITY OF AI & MACHINE LEARNING
The role of AI is critical and is revolutionizing the healthcare industry, as a 2026 Eliciting Insights poll of health systems across the US regarding AI adoption showed 75% of U.S. health systems are using at least one AI intelligence application. Another survey from Health Edge revealed that 94% of payers are either leveraging or actively adopting AI. There is growing consensus that health leaders are using AI tools to identify trends, create intervention strategies, optimize electronic health record (EHR) workflows, and improve many other processes at their organizations.
Peggy Choquette

Scott Geye
Scott Geye, chief technology officer, Handl Health, considers healthcare to be deeply personal: “Integrating AI has to be done thoughtfully with an eye toward preserving human connection. Person-to-person interaction is what makes patients have trust in the healthcare system.”
But just as consumers are integrating AI into their daily healthcare lives and doctors layer AI atop patient data to provide better outcomes, Geye says, “The self-funded industry can use AI to reduce costs and improve patient care. AI tools layer on top of healthcare price transparency files and other data to quickly analyze large, complex datasets and identify patterns, enabling timely action at the appropriate cost and setting. AI helps us understand the data by making complex actuarial analysis available to everyone.”
As a follow-on to this perspective, Bounce expands, “AI and ML provide us with a meaningful expansion of what we can forecast. Learning to co-exist with these tools will enhance our
understanding of the data and provide insights to encourage more effective strategies.”
For example, she says to consider a common disconnect: “According to the US Bureau of Labor Statistics, the median tenure of workers ages 25 to 34 is 2.7 years, yet most employer-sponsored healthcare investments often take 2-3 years to achieve ROI. This creates a meaningful barrier in both predictive analytics and managing healthcare spending using current healthcare intervention techniques. Current forecasting models accept this constraint and attempt to optimize around it. AI allows us to ask different questions entirely like “Which sub-populations show measurable health and cost signals within 12 months?” and What interventions actually move those signals?"

AN EMPLOYER STEPS UP: PHIFER, INC.
Russell DuBose, Vice President of Human Resources at Phifer Incorporated, a leading manufacturer of engineered fabrics and innovative screening products, recognized globally for quality, durability, and American craftsmanship, shares this perspective:
“Phifer’s healthcare strategy is anchored in proactive care supported by predictive analytics that identify early indicators of disease across the population,” says DuBose. “To strengthen this capability, Phifer is implementing an advanced AIdriven analytics platform through selected partners, which expands its clinical dataset by integrating claims information with onsite EMR records, including genomic profiling.”
He says this richer set of markers will enable far more precise risk identification and earlier intervention, adding, “The resulting insights will guide clinicians in selecting the most appropriate diagnostics, medications and treatment plans, ultimately improving outcomes and elevating the overall performance of the healthcare plan.”

Russell DuBose
Forecasting Medical Costs

ACTION STEPS
For Angel Onuoha, CEO, Avelis Health, AI and ML are most useful when they help organizations move from retrospective reporting to earlier, more actionable signals.
“In medical cost forecasting, the challenge is not just predicting that costs will rise; it is understanding why, where and what can actually be done about it,” says Onuoha. “Claims data, plan documents, reimbursement policies, provider behavior, utilization trends, and member risk indicators all contain signals, but they are difficult to interpret manually at scale. Traditional actuarial and claims analysis can identify broad trends, but AI can help surface patterns faster and with more granularity.”
He argues that AI should not operate as a black box, noting, “In healthcare, the most valuable systems are explainable, auditable, and grounded in the plan’s actual rules, contracts, and policies.”
From a cost containment perspective, Lynch asserts that the role of AI and ML are to pull deeply buried clinical patterns out of fragmented data snapshots to identify exactly where plan assets are slipping through the cracks.
“At the start of a new client relationship or during the renewal process, we see a clear opportunity for ML to rapidly scan the initial claims data to uncover hidden risk vulnerabilities, helping reinsurers map out a customized cost containment recipe with the client from day one,” she explains. “During the contract year, AI then can continuously monitor 50% notification reports and active reimbursement claims to track a population's clinical trajectory, providing clear visibility into whether the client’s current cost mitigation strategies are actually working.”
She clarifies that this is the ideal scenario, adding, “The reality is that data quality is still a major bottleneck. The sheer volume of unstructured data such as scanned PDFs, clinical notes, and disparate claim data formats remains a problem for predictive accuracy. To truly leverage AI, the industry will have to adopt better, more standardized data submission practices.”
While forecasting catastrophic exposure is entirely possible without these tools by relying on historical claims averages, manual trigger reports and standard medical trends, she notes that doing so may keep the approach more reactive than proactive.
“Traditional forecasting methods treat a 50% deductible notification as a static, backward-looking milestone unless of course the condition is chronic, and care is ongoing,” she continues. “Conventional approaches can struggle to anticipate sudden cost spikes or the rapid financial impact of fast-tracked, high-dollar specialty therapies. Without advanced data tools to instantly cross-reference sparse notification codes against complex diagnostic patterns, cost containment teams may miss subtle indicators of rising clinical exposure – though this capability ultimately depends entirely on the quality and completeness of the incoming data.”

Angel Onuoha
Kari Niblack
Niblack echoes these perspectives: “AI and ML accelerate something that good data and experienced clinical teams have always done well, which is identifying patterns before they become problems.”
She says the tools matter, but they are not a substitute for clinical judgment or member relationships: “A model can flag a member as high-risk, but it takes a real person to call them, build trust, and actually change the trajectory of their care. That said, the scale and speed AI enables is real and provides faster stratification, earlier flags and better timing on outreach. The organizations that get this right are those that use AI to sharpen human intervention, not automate their way around it.”
For David Ostrowsky, Manager, Corporate Communications, The Phia Group, the incorporation of AI into the health insurance ecosystem has already had a transformative impact on forecasting medical costs.


“Accurate medical cost projections necessitate a wide range of data sources and AI tools can extract realtime data from pharmacies, hospital records, and insurer databases among many other resources,” he states. “Whether it’s gathering a patient’s up-to-the-minute medical records via APIs or providing empirically sound confidence scores for predictions, AI agents have the ability to generate dynamic expense predictions instantaneously. This still relatively nascent development marks a significant change from prior models that largely operated with fixed datasets and is one that continues to bear watching closely.”
While forecasting is possible without AI, Morris believes that scaling success and meeting the needs today’s ‘speed of business’ paradigm—no longer months, but now weeks and sometimes days— requires advanced technology and tools.
“AI can illuminate critical insights expeditiously,” says Morris. “Rapid advancements with AI in healthcare—if they are developed responsibly—are making predictions faster, easier, and more accurate. Generative business intelligence (BI) tools are now making analysis more accessible through natural language prompts and simplified search tools. These AI tools make insights available to business users without extensive data analytics expertise or in-depth knowledge of a technology platform. Critically, as technology vendors develop these tools, they must include necessary guardrails to secure proprietary data, protect brokers’ and employers’ competitive advantages, ensuring the information available to users has safeguards for PHI protection and appropriate use.”

Solomon believes that AI and ML can play an important role in helping organizations prioritize outreach, identify patterns across large datasets, and scale intervention strategies more efficiently.
David Ostrowsky
David Morris
Carrie Solomon
“These technologies are particularly useful when integrating multiple data sources such as claims; precertification requests; pharmacy data; eligibility; member demographics, behavior, and preferences; and care management activity,” she observes. “Remember that forecasting healthcare risk existed long before AI. Experienced clinical and utilization management teams have historically used utilization patterns, diagnoses, treatment pathways, and referral triggers to identify members who may require intervention. AI now allows us to speed up that pattern recognition, freeing up valuable time for clinical teams to spend on secondary review, personalized engagement and custom care plan design with patients.”

Trevor Colhoun
IMPACT ON BEHAVIORAL HEALTH
AI (AI) has emerged as a transformative force in various healthcare fields and its application in mental healthcare is no exception. Experts say that as the diverse range of applications and implications of AI in this field are explored further, the synergy between human expertise and AI capabilities holds the potential to usher in a new era of mental healthcare.
Researchers are currently seeking to develop a predictive model for behavioral health with a goal to develop AI models trained on continuous behavioral data linked to large-scale electronic health records. Funded by the Advanced Research Projects Agency for Health (ARPA-H), the project focuses on integrating behavioral health data from smartphones, wearables and electronic health records to develop predictive AI models.
Trevor Colhoun, CEO, TPN.Health believes that organizations reduce their financial risk by anticipating needs and preventing costly hospitalizations and ER visits.
“Organizations that invest in proactive behavioral healthcare navigation – getting members matched to appropriate care quickly and keeping them engaged – are addressing one of the most overlooked drivers of high-cost claims,” says Colhoun. “Untreated mental health and substance use conditions drive medical costs two to three times higher across the entire system, generating higher ER utilization, more preventable admissions, and worsening comorbidities that compound over time.”
He points to TPN.Health's 95.2% match proficiency rate that reflects what human-guided care navigation achieves when the network data behind it is accurate.
“Getting people matched to the right behavioral health provider the first time is where the savings begin, and where behavioral health stops being a blind spot and starts driving financial strategy,” says Colhoun.
TOOLS AND COMPONENTS FOR FORECASTING
As the industry shifts from a reactive approach to proactive, data-driven care, these systems empower all stakeholders to anticipate diseases, personalize treatments, prevent adverse events, and optimize facility operations.

Amwins Ancillary is a full-service general agency and strategic consulting center of excellence, combining sales expertise with intelligent technology to give brokers an advantage from strategy through renewal. We are high-tech and high-touch, independent and fully broker aligned.
Brokers get deep expertise across every line without adding headcount or cost. Behind every relationship stands the full strength of Amwins, bringing national scale, broad carrier access, and resources few can match.
Explore Our Ancillary Solutions Today!


Ancillary
These tools are crucial for several core reasons, especially proactive disease management. They identify early signs of illness or high-risk patients before acute symptoms appear, which is vital for managing costly chronic conditions like diabetes or heart disease. They enable precision medicine by matching patient profiles with vast datasets to determine the most effective and least toxic therapies for an individual. By anticipating patient deterioration or discharge complications, providers can intervene early to prevent costly emergency room visits and hospital readmissions.
Source: Environmental Health and Preventive Medicine; https:// pmc.ncbi.nlm.nih.gov/articles/PMC3541816/
PREDICTIVE ANALYTICS IN HEALTHCARE
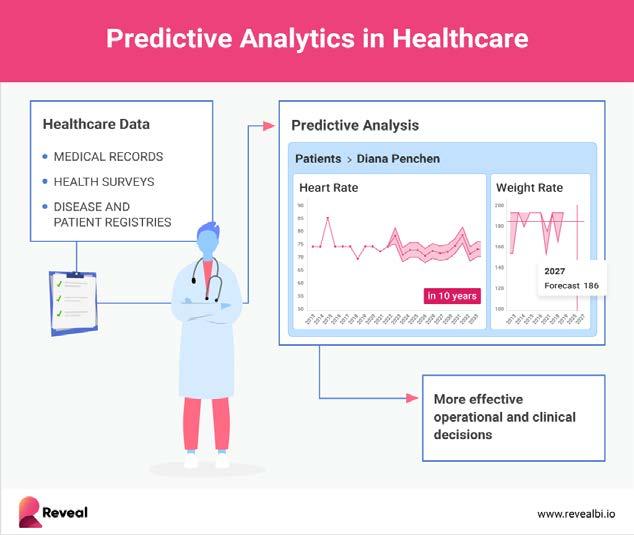
This refers to a type of data analysis that evaluates current and historical data to predict future events, make informed decisions about health management and benefits and enhance employee wellness while controlling costs.

Source: Stony Brook University. Institute for Engineering-Driven Medicine
Another trend is the integration of real-time data and analytics to provide immediate insights into employee health and benefits utilization. This immediacy allows companies to adjust their benefits offerings dynamically, based on current data rather than outdated information. There is also the benefit of using predictive analytics to evaluate stop-loss insurance needs, determining at what point stop-loss coverage should kick in and how much coverage is necessary based on claims data.
Unlock Mayo Clinic for Your Clients’ Most Complex Cases
Mayo Clinic Complex Care Program

As a trusted benefits advisor, you understand the impact of high-cost claimants with rare or undiagnosed conditions. The Mayo Clinic Complex Care Program offers your clients direct access to world-class subspecialty care, leading to better outcomes and long-term cost savings. All without added fees.
Let’s collaborate to bring clarity, confidence, and care to your clients.
Learn more: mayoclinic.org/complex-care-program
55% of patients experience a change in diagnosis
82% see a change in treatment plan

“The groups that hurt a stop-loss portfolio rarely look dangerous at bind –they look average,” says Ali Panjwani, CEO and Founder, Merit Medicine. “What sets them apart is volatility – unpredictable claim concentration in a small number of members that traditional underwriting inputs struggle to see early enough.”
He points out that Merit Medicine’s Merit Predict was built to solve exactly that problem. “Our AI and ML models evaluate risk at the member level –clinical trajectories, high-cost drug signals, comorbidity progression – and surface the handful of groups most likely to produce extreme outcomes before pricing decisions are finalized,” he continues. “In a recent actuarially validated retrospective study, identifying the highest-risk groups before binding would have improved underwriting margin by 107% and cut reimbursements in half.”
At this resolution, forecasting is not possible without AI and ML, as he explains, “But the technology alone is not enough. TPAs, brokers, stop-loss carriers, and employers each hold a piece of the picture. Making that collaboration work – getting the right predictive insights to the right stakeholder at the right time – is what turns forecasting into timely intervention and ultimately better outcomes for the members we all serve.”
Sood at Evidium affirms that underwriting is not simply a data exercise, “It is grounded in experience, context, and informed judgment. At the same time, this view reflects how both AI and healthcare risk are currently understood. At Evidium, we see a broader shift taking place. As healthcare risk becomes more clinically driven, the ability to connect medical knowledge with financial outcomes is becoming increasingly important to how risk is evaluated.”
He further explains that today, AI is primarily used to improve efficiency within underwriting workflows, noting, “It helps with the RFP process, cleans and normalizes data, identifies high-cost claimants, generates baseline pricing assumptions, and helps streamline renewal analysis. These applications are valuable and help reduce manual effort, allowing underwriters to focus more on actual decision-making. In a market where margin discipline and stricter underwriting standards are increasingly non-negotiable, this kind of investment in better underwriting tools is becoming a competitive necessity.”
Sood clarifies that these tools and approaches do not fundamentally change how risk is actually understood, adding, “Most approaches still rely on historical claims data and pattern recognition. They are retrospective, focusing on what has already happened and projecting it forward. This is where limitations begin to emerge.”
Ali Panjwani
Predictive Modeling: Often used interchangeably and considered a subset of predictive analytics, predictive modeling is the process of running mathematical algorithms on data to predict what’s most likely to happen in the future.
Healthcare Cost Modeling: This describes the practice of evaluating historical and current healthcare delivery and expenditures. It focuses on analyzing how much a service costs, why it costs that much and how resources are distributed. It empowers stakeholders to understand the financial impact of various conditions, treatments and populations.
Healthcare Care Modeling: Creating models that are targeted, multimodal and action oriented. Mercer maintains that building successful care models is expensive, advising that insurers must zero in on areas with true, clinically addressable spend. For example, clinically appropriate site-of-care shifts alone could spark approximately $114 billion in savings across the entire US healthcare system.

Source: REVEALBI.io
GO IT ALONE – OR TAP RESOURCES?
The reality is that no single party typically has the full picture.
Onuoha advises, “Forecasting requires clean claims data, plan-specific rules, reimbursement knowledge, clinical context, and the ability to translate insights into action. That is difficult to do well with internal resources alone, especially for smaller or mid-sized employers. The best model is collaborative. Brokers/consultants should set the goals, TPAs should enable the workflow, and outside vendors should provide specialized analytics, AI infrastructure and payment integrity expertise.”
From Bounce’s perspective, “It will ‘take a village’ to make impactful change and will require engagement from all stakeholders. The employer must be willing to step outside the box and take the time to understand the needs of their employee population from lifestyle to access to care to language and/or financial barriers.”
She explains that they need to work with a broker who will take the time to understand their needs while also partnering with the appropriate resources to adequately address them.
“A great broker will avoid shiny, new objects and easy dollars,” she continues. “Their focus should remain on proven methods with a pulse of real breakthrough models. The stop-loss carrier, with all of their data, could play a much more integral role in forecasting and predictive analytics. Their information is being wasted when their only involvement is underwriting at renewals. In addition to predicting spend, they have valuable knowledge on what works and what doesn’t to save the plan dollars.”
Finally, she recommends that the TPA should be your glue.
“They serve to bring all of the ideas and parties together into a seamless model,” she concludes. “They need to be flexible enough to manage the plan accurately, engaged enough to keep all parties aligned, transparent and timely in how they share valuable information, kind enough to build trust, yet strong enough to protect the plan’s financial interest.”Lynch also thinks that true success requires a synchronized approach.
“The plan owns the strategy, but the TPA or plan payer drives the operation using predictive analytics (internal or resourced) – all while keeping the broker and reinsurer aligned,” she notes. “As the reinsurer, if we are given the opportunity to assist, we can help catch what is missed on the front end and help manage the cost of the exposure on the back end. Because we live and breathe these complex cases every day, our volume and familiarity give us the leverage needed to help better mitigate the financial outcomes.”
However, effective cost mitigation relies on strong cooperation from the plan payers.
“Specifically, Lynch and colleagues look for partners who are fully aligned and willing to: collaborate for a third-party bill review program, provide the necessary detailed data support, allow for targeted cost containment interventions, and adhere to the intervention findings when ultimately paying the claims.
She maintains that when this level of payer alignment is achieved, “It transforms risk management from a reactive safety net into a powerful, proactive financial strategy.” Niblack concurs that the TPA has to lead, maintaining that no other party sits closer to the data or the member.
“Brokers are essential translators who help employers understand what's possible, but they don't have the operational capacity to manage interventions,” says Niblack. “Stop-loss carriers are increasingly sophisticated partners for high-cost case coordination, and that relationship matters. Employers set the tone, and the plans that perform best have leadership genuinely committed to member health, not just cost reduction. No single party succeeds here without the others. But if someone isn't actively leading, the member falls through the gap, and that's where costs explode.”
Morris believes that everyone has a role to play in identifying high cost and utilization, focusing on quality outcomes, measuring ROI, benchmarking risk-adjusted performance and ensuring positive impact on populations we serve.
“Advancing the responsible implementation of analytics and AI are the responsibility of each constituent participate in the healthcare ecosystem,” he says. “To be effective, TPAs, broker consultants, and employers need an external strategic technology partner with advanced data management capabilities, in-depth analytics and data for benchmarking—seamlessly integrated into their tech ecosystem—with guardrails for responsible AI development and implementation.”
Similarly, he considers that technology vendors should rely on the experience of broker consultants, employers, and stop-loss carriers to inform development and optimization, adding, “The partnership will result in an advanced analytics platform with predictive AI that delivers intuitive insights and actionable steps to curb rising costs and improve employees’ care quality Solomon emphasizes that no single stakeholder can independently solve today’s cost management challenges because each organization sees a different part of the member journey.
“As such, this process should be collaborative between stakeholders — and, most importantly, with a strategy that centers the member,” she explains. “Because of the complexity of healthcare cost management, many organizations benefit from working with vendors. Vendors are especially useful in terms of scalability and can apply their expertise in areas like compliance, security, and current regulation across a variety of organizational types and structures. This results in a level of efficiency and results that individual organizations cannot usually achieve on their own.”

Mike Lanza, Senior Vice President, USBenefits Insurance Services, LLC, sums up this issue: "To effectively control medical costs, it is essential that the health plan, third-party administrator (TPA), and stop-loss carrier work collaboratively throughout the claims process. Although pre-authorizations often receive negative attention, they remain a critical tool for TPAs to verify that a proposed medical procedure is medically appropriate and covered under the plan document.”
He says AI can enhance this process by analyzing large volumes of preauthorization data and identifying cases that warrant additional review.
“For example, approved high-cost procedures can be referred to case management, ensuring that qualified clinical personnel actively monitor the member's care and treatment plan,” shares Lanza. “Potential high-dollar claims that may exceed the specific deductible should be reported to the stop-loss carrier as early as possible. Early notification is critical because it allows the TPA and stop-loss carrier to coordinate before provider payments are made. This collaboration helps ensure that claim evaluations are aligned and that stop-loss reimbursements accurately reflect the amounts paid by the plan.”
Mike Lanza
Lanza notes that the review of complex, high-cost cases often require specialized expertise, adding, “Selecting a vendor with deep clinical resources, including physicians across multiple specialties, helps ensure that reviews are based on current medical standards and evidencebased practices. Providing healthcare providers with a comprehensive, well-documented review report can also expedite the process, improve transparency, and reduce the likelihood of appeals."
April Gill advises, “No single stakeholder has all the answers. TPAs, employers, brokers, and stop-loss carriers as well as employees themselves, each bring unique insights, but success depends on collaboration and access to connected, actionable data. Organizations that can turn fragmented information into timely interventions will be best positioned to improve outcomes while managing healthcare costs more effectively.”

Echoing these perspectives, Choquette insists that no single stakeholder can drive this transformation alone:
“Each contributor brings something others can’t replicate—data access, financial oversight, clinical expertise, patient engagement— and the value emerges from coordination rather than parallel effort. Successful implementation depends on a collaborative, multidisciplinary framework in which case management serves as the coordinating force, leveraging the expertise of TPAs, payers, employers and specialized vendor partners.”

April Gill

Geye affirms that outside technology vendors have been pouring time and resources into developing AI and machine learning tools that transform how patients use healthcare.
“These companies work on behalf of all industry stakeholders to bring down collective costs and increase healthcare value,” he remarks.
“That said, demand for medical cost forecasting must start with employers – after all, they're staring down the largest healthcare cost increases in 15 years. If employers are not already having conversations with their brokers about jumping off the renewal carousel and focusing instead on the heart of the cost issue, they might need to look elsewhere.”
He says another reason not to go it alone comes down to security: How do you make sure health data stays secure as it passes through an AI model? How do you ensure AI model vendors aren't training on your data?
“Healthcare technology companies should focus on building AI that can truly reshape the industry,” concludes Geye. “Price transparency analysis was just the first wave. Brokers now need detailed modeling, more intelligent plan design, and activation of new variable copay plans that don't exist in the market today. That’s where AI can truly shine.”

Do you aspire to be a published author?
We would like to invite you to share your insight and submit an article to The Self-Insurer! SIIA’s official magazine is distributed in a digital and print format to reach 10,000 readers all over the world.
The Self-Insurer has been delivering information to top-level executives in the self-insurance industry since 1984.
Articles or guideline inquires can be submitted to Editor at Editor@sipconline.net.
Laura Carabello holds a degree in Journalism from the Newhouse School of Communications at Syracuse University, is a recognized expert in medical travel and is a widely published writer on healthcare issues. She is a Principal at CPR Strategic Marketing Communications. www.cpronline.com
The Self-Insurer also has advertising opportunities available. Please contact Shane Byars at sbyars@ sipconline.net for advertising information.
George Stiles
Rx Rightsizing
Experts advocate a smarter approach to polypharmacy
InIBy Bruce Shutan
America’s pill-popping culture, it’s not surprising that the prevalence of patients taking multiple medications to manage leading chronic conditions such as diabetes, heart disease, hypertension and high cholesterol is surging along with the graying of America. Just turn on any TV and commercials extolling the clinical benefits of a host of new drugs are inescapable.
The number of U.S. adults taking five or more prescription medications concurrently – a phenomenon known as polypharmacy – has more than doubled to 17.1% and tripled to nearly 44% for those age 65 in the past 20 or so years.
The implications for self-insured health plans are enormous in terms of both cost and clinical outcomes. While necessary and beneficial in many cases, this strategy also significantly increases the risk of adverse drug interactions, falls and fractures, cognitive impairment or confusion, hospitalizations, higher healthcare costs and poor adherence to treatment. That’s why experts suggest a more thoughtful approach to managing polypharmacy claims.
One industry insider suggests that inappropriate prescribing of even a single script can have ramifications on par with polypharmacy concerns, noting that 30% of hospitalization issues are tied to inappropriate medications. Indeed, inappropriate administration of medications on hospital discharges can complicate matters for polypharmacy patients.
“They’ll send you out with your discharge papers that are very clear about the drugs you should be on, but no one looks back at what you were on before and says, ‘stop taking these,’” says Amy Ball, PharmD, President of Innovative Rx Strategies, who was a hospital pharmacy director for 10 years. “Maybe they changed medication therapy for your blood pressure or cholesterol while you were in the hospital, but nobody tells you to stop taking the medication you’re on at home.”

The more drugs that are added to a prescription drug regimen, the harder it is to learn what’s causing health problems in the first place, Ball explains. She always recommends carefully studying a patient’s chart before adding scripts, which increases the chance of medication errors being made.
JUGGLING DISEASE STATES
With about two-thirds of Americans said to be overweight, the increasing prevalence of “diabesity” (diabetes and obesity) has become a major concern in polypharmacy. Many of the complications associated with diabetes result in other comorbidities that can all be diagnosed at the same time, Ball explains. When that occurs, she says “someone can go from being on zero meds to six or eight medications all at once.”
Other scenarios involving multiple medications include oncology, hemophilia, Parkinson’s, Alzheimer’s, inflammatory bowel disease, asthma, dyslipidemia, COPD, and psychiatry conditions. They also may involve patients who start out on just one drug, having others prescribed to treat troubling side effects.
Implementing a meaningful approach to polypharmacy is particularly crucial for very treatment-resistant patients, according to Dea Belazi, Cofounder, President, and CEO of AscellaHealth. If Lipitor isn’t helping lower cholesterol, for example, another statin, fibrate, or PCSK9 inhibitor may be needed.
Polypharmacy is a widely accepted medical practice to treat advanced or very complex hypercholesterolemia, diabetes or even some specialty conditions such as challenging psoriasis or rheumatoid arthritis, he notes.
“We could go through hundreds of diseases where the complex or treatment-resistant models are just polypharmacy,” he says.

Another consideration is that medical advances have elevated the use of polypharmacy. Ten years ago, Belazi notes that HIV patients were burdened by a double-digit daily drug cocktail to treat their illness, which used to be a death sentence, whereas now there are combination drugs that will last multiple months and help people live with the disease.
But the model is also riddled with shortcomings. One example he cites is treating behavioral health conditions such as schizophrenia with two or three atypical antipsychotics without a single data point that suggests it’s the right way to proceed. This can lead to psychiatric hospital readmissions.
When Ball did long-term care consulting at a hospital, she recalls how a physician with whom she was making the rounds one day suggested putting an elderly woman who was having heart palpitations on a beta blocker.
“In the elderly, oftentimes low thyroid can result in heart palpitations, especially in women, and so I noticed in the chart that no one ever done a thyroid test on her,” she says.
Amy Ball
Dea Belazi
It turns out that her hunch was right after running a test: the patient didn’t need to go on a beta blocker after all. The danger in prescribing it for the elderly is that they’re more prone to falling and breaking their hip when getting out of bed, standing up and walking. As people age, she notes that muscle mass decreases, they lose weight and become more fragile, which means they may not need the same level of drugs that they did when they were younger. In addition to losing their mobility, they could also develop an infection and increase their risk of mortality.
Most patients who are older than 65 have more than 10 medications to manage their chronic disease states, thus making them more prone to acquiring polypharmacy status, notes Adva Tzuk Onn, M.D., a family and geriatric physician and Chief Medical Officer at FeelBetter. With an aging population working later into life, this becomes a concern for employers that are trying to retain graying talent with deep knowledge and institutional memory.
THE IMPACT OF GLP-1S

With so much attention drawn to the use of GLP-1 drugs for weight loss, this trend could have a massive impact on polypharmacy. As more people on those drugs are able to lose weight, Ball says lower blood pressure, cholesterol, and blood-sugar levels could help eliminate the need for meds to treat those conditions. By the same token, she notes that there’s still uncertainty around how other drugs interact with GLP-1s.
“We could potentially have up to 40% of the U.S. population on GLP-1s based on obesity statistics,” Ball predicts. “That’s a big deal.”
Most people with Type 2 diabetes are on two or three medications that could be include a generic drug called Metformin or branded set of drugs called SGLT2, which helps rid urine of sugar, Belazi explains. In addition, they could be on a GLP-1 to lose weight. He says what’s worth noting is that weight-loss drugs have many side effects and that a significant proportion of those who’ve been prescribed the medication gain back most or all of their weight if they stop using it.
While the addition-by-subtraction approach to polypharmacy will no doubt help weed out unnecessary or harmful scripts in a patient’s drug regimen, it’s vital not to lose sight of a larger goal. Tzuk Onn suggests using medications as a tool for whole-person health vs. focusing too narrowly on medication adherence and deprescribing.
At the heart of polypharmacy is a need to first examine whether there are any indications that prescribed medication is inappropriate for a patient, according to Tzuk Onn. In some cases, the script may no longer be needed after being taken for a while and showing tepid or poor results.
Another concern she has is whether an appropriate dosage has been dispensed for each particular condition (i.e., the amount of medication for hypertension or cardiac arrhythmia might be different). Issues involving kidney and hepatic functioning, as well as the patient’s age, will require a change in dosage according to the patient’s comorbidity and elements of the drug’s pharmacokinetics.
Adva Tzuk
AI’S HELPING HANDS
Since it’s easy for time-pressed physicians to encounter drug-interaction alert fatigue, Tzuk Onn says it’s important to prioritize a review of potentially dangerous interactions, “and then you have to see what happened once you gave both medications,” she adds. This is where technology can help because unlike physicians, chatbots can follow patients who have multiple diseases all of the time and assess the dangers of so-called drug-drug interactions.
Considering that clinical pharmacists may be responsible for anywhere from 500 to 100,000 patients, she considers technology vital to helping them manage a heavy workload and approach patients who need them the most. Artificial intelligence can provide a list of patients and the necessary insight so that each clinician has a comprehensive view of each patient and understand the relationship between their conditions, medications, lab tests, and overall wellbeing. “Instead of seeing just one patient, they would be able to see up to 10 patients at the same time,” she says.
The trouble with these AI agents is that they save any information given to them, which would violate patient privacy, “and we don’t know what they will do with that,” she cautions. Given that they’re also not actually clinical pharmacists and have limitations, she says users cannot trust the information they dispense.
However, Tzuk Onn believes the technology can be quite useful if an AI algorithm is trained on evidencebased and rule-based data that is kept anonymous to ensure the information isn’t used for nefarious purposes and quality assurance is implemented to verify results.
REPLACING PILLS WITH CANNABIS
Making available Rx alternatives can help make a dent in polypharmacy claims. Research shows that cannabis helps patients achieve better symptom management, reduces their reliance on prescription medication, and on occasion, completely eliminates them altogether, explains Emily Fisher, Founder and CEO of Leafwell, whose team of data scientists, cannabis specialists, and patient advocates help people unlock the medicinal benefits of cannabis.
As a two-time breast cancer survivor, Fisher knows that while polypharmacy is a necessary tool for clinicians to manage disease, taking several powerful medications at the same time also can produce harmful side effects. Having worked with thousands upon thousands of patients, she says cannabis is a much safer and gentler alternative to pharmaceuticals for chronic conditions. Leafwell, which facilitates more than 20,000 monthly clinical encounters across the U.S. for patients exploring cannabis therapy, has been collecting millions of data points. One such finding was a more than 50% drop over a three-month period in the use of multiple medications, including opioids, taken to treat anxiety and sleep disorders in over 250,000 patients who were surveyed between 2021 and 2024.

Fisher says there are some very practical steps employers can take to reduce adverse drug interactions and eliminate unnecessary scripts. One is to embrace a fiduciary-aligned pharmacy benefit manager that ensures contracts mandate 100% pass through of manufacturer rebates and replace percentage-of-cost fees with a fixed administrative charge.
Emily Fisher
“Organizations whose incentives are aligned with employers formalize a managed deep prescribing protocol to integrate automated data tools that flag candidates for treatment deescalation,” he explains.
From the perspective of cannabis therapy, she says it’s important to introduce evidence-based adjunct therapies early. When clinically guided and structured correctly, they lower the risk of this cascading prescribing effect that can happen with polypharmacy, reduce the reliance on prescription medication, support better symptom management and improve quality of life.
The ultimate goal behind any attempt to clean up polypharmacy is to elevate clinical value and outcomes. “If I was a self-insured employer, health plan, TPA or whatever,” Belazi says, “I would be very much focused in this particular area with their partners or vendors, whether it’s a PBM or otherwise, to be looking at what programs are in place –particularly around spending money on drugs that don’t have an effect.”

Bruce Shutan is a Portland, Oregon-based freelance writer who has closely covered the employee benefits industry for nearly 40 years.


MEDICAL STOP-LOSS APPROACHES AN INFLECTION POINT
Reinsurance Retrenchment, Rising Claim Severity, and the Return of Pricing Discipline

TheTWritten By Philip C. Giles, CEBS
medical stop-loss (MSL) market appears to be entering a period of meaningful and sustained rate firming, driven by a convergence of deteriorating underwriting performance, rising claim severity, and tightening reinsurance capacity. After more than two decades of persistent competition, several structural pressures are beginning to materially alter pricing dynamics and underwriting behavior across the sector.
Earlier this year, two major reinsurers announced their immediate exit from the medical stop-loss market, while another signaled plans to materially reduce a sizable block of unprofitable business. Industry estimates suggest these actions could remove more than $1.5 billion of effective reinsurance capacity from the market. At the same time, several leading carriers have reported significant underwriting losses and have begun implementing portfolio remediation initiatives.
The medical stop-loss market has been one of the fastest growing segments of the health insurance industry over the past fifteen years. Since implementation of the Affordable Care Act (ACA), annual premium volume has expanded from approximately $8 billion in 2010 to an estimated $40 billion by the end of 2025.
Despite that growth, underwriting performance has steadily deteriorated. Industry-wide gross loss ratios have trended upward for much of the past decade, reaching nearly 86% in 2024, the most recently reported underwriting period. Importantly, these figures reflect gross rather than net loss ratios. Given typical acquisition, administrative, and operational expense loads within the sector, current results suggest that many carriers may be operating at or near unprofitable combined ratios in this line.
Although some carriers initiated corrective pricing and underwriting actions during 2025, early market indications suggest overall results have continued to deteriorate and the industry-wide loss ratio will exceed 90% when the full-year data is released later this year.
The reduction in available reinsurance capacity is expected to reinforce pricing discipline throughout the market. Direct-writing carriers and managing general underwriters (MGUs) are likely to face tighter underwriting parameters, increased facultative review requirements, and higher reinsurance costs on excess treaties. Those additional risk charges will ultimately flow through to employer pricing.
As underwriting profitability becomes a greater priority, carriers are expected to pursue more selective risk selection, stricter renewal underwriting, tighter contract terms, and heightened claims scrutiny. Delegated underwriting authorities for MGUs may also narrow materially as reinsurers seek greater control over risk selection and claims exposure.
A MARKET DEFINED BY PROLONGED COMPETITION
The medical stop-loss market has remained intensely competitive for decades. The last broadly recognized hard market occurred more than twenty-five years ago, around the turn of the millennium. Since then, sustained competition has compressed pricing and gradually eroded underwriting margins across portions of the industry.
Competitive pressures have consistently driven demand for broader contract provisions, restrictive rate caps, and increasingly aggressive pricing, even as underlying medical costs and catastrophic claim severity continued to rise.
While carriers generally seek to price business at actuarially sound levels, prevailing market conditions have often constrained pricing flexibility. As a result, underwriters have frequently been forced to balance pricing adequacy against competitive positioning and retention objectives.
Premium Growth vs. Underwriting Performance (2015–2024)
Source: NAIC Accident and Health Policy Experience Report.
While 2023 reflected temporary moderation in reported loss ratios, preliminary market indications suggest deterioration resumed during 2024 and into 2025.
Market concentration has also increased materially. In 2010, the top twenty-five carriers controlled approximately 70% of the market. Today, the top ten carriers control a similar share of a substantially larger market. Consequently, the underwriting performance of a relatively small group of carriers now exerts disproportionate influence over broader market conditions.

DRIVERS OF CONTINUED MARKET DETERIORATION
Medical stop-loss coverage is specifically designed to protect self-funded employers from catastrophic claims exposure. However, the continued escalation in both the frequency and severity of high-cost claims is creating substantial underwriting pressure.
The primary drivers of catastrophic claims have remained relatively consistent in recent years. Oncology, cardiovascular disease, musculoskeletal conditions, injectable drugs, and infusion-based therapies continue to represent a significant portion of high-cost claims activity. Additional pressure has emerged from delayed diagnoses, worsening comorbidities, and increased disease severity following the COVID-19 pandemic.
One of the industry’s most significant emerging concerns is the rapid development of cell and gene therapies (CGTs). While many of these treatments offer potentially transformative or curative outcomes, their long-term financial impact remains uncertain. Individual therapies are increasingly expected to cost from several hundred thousand dollars to multiple millions per treatment.
The actuarial challenge is compounded by limited longitudinal claims data and uncertainty regarding longterm durability, recurrence risk, and future treatment protocols. As a result, carriers and reinsurers are increasingly pricing for the inevitability of these claims through higher rates, targeted surcharges, tighter underwriting, and more restrictive contract provisions.
SPECIALTY PHARMACEUTICALS AND PBM DYNAMICS
Outside of provider and hospital system charges, specialty pharmaceuticals remain among the most significant contributors to rising healthcare costs.
Health benefits redesigned with you in mind.
Turn complexity into clarity with:
• 24/7 access to actionable insights
• Proactive and engaging member advocacy solutions
• In-house teams from implementation to renewal

See what sets us apart from other TPAs. hpiTPA.com
Prescription drug distribution is largely controlled by pharmacy benefit managers (PBMs), which operate within a highly complex and often opaque pricing structure involving rebates, spread pricing, administrative fees, and manufacturer contracting arrangements. Limited transparency throughout the supply chain continues to contribute to elevated drug costs.
Specialty pharmaceuticals, many of which are used to treat chronic, rare, or life-threatening conditions, now represent a rapidly expanding share of total healthcare expenditures. Compounding the issue is the absence of a universally accepted regulatory definition for what constitutes a “specialty” drug. In many cases, classifications are effectively determined by manufacturers or PBMs rather than through consistent regulatory standards.
Annual treatment costs for specialty pharmaceuticals can range from several thousand dollars to multiple millions per patient. Although newer PBM models and biosimilar strategies may improve cost efficiency, specialty pharmaceuticals are expected to remain a significant driver of medical trend and stop-loss claim severity.
NO NEW LASER CONTRACTS AND RATE CAP COMPRESSION
No New Laser (NNL) contracts combined with restrictive rate cap provisions may represent one of the most significant contributors to underwriting deterioration in recent years.
A foundational principle of alternative risk financing is that predictable or manageable risk is often more efficiently retained by the employer than transferred to an insurer at commercial premium levels. When carriers are unable to appropriately isolate or price known high-risk claimants through lasers or other underwriting mechanisms, underwriting performance will inevitably deteriorate over time.
In many cases, carriers have offered broad NNL protections and restrictive renewal caps in order to remain competitive. That environment now appears to be changing. Underwriters are becoming increasingly selective in offering these provisions and are placing greater emphasis on employer risk management, claims oversight, and cost-containment capabilities.
Going forward, employers seeking broad renewal protections are likely to encounter stricter underwriting scrutiny, narrower eligibility standards, and increased expectations regarding plan management and clinical intervention strategies.
STRATEGIC IMPLICATIONS FOR SELF-FUNDED EMPLOYERS
As the market hardens, self-funded employers will likely need to adopt more disciplined and proactive approaches to managing catastrophic claim exposure and long-term healthcare cost trends.
Pharmacy Management
Prescription drugs and specialty pharmaceuticals remain one of the most significant drivers of medical cost inflation. As a general benchmark, pharmacy-related costs should typically account for no more than 25–30% of an employer’s overall health plan spend; however, it is not uncommon for those costs to approach or even exceed 50% in plans utilizing inefficient or non-transparent PBM arrangements. Employers are placing increasing emphasis on PBM transparency, international and alternative sourcing strategies, biosimilar substitution, patient assistance programs, and more direct pass-through of manufacturer rebates. While these approaches may help mitigate pharmacy trend, broader structural pricing pressures in the pharmaceutical market are likely to persist.
Infusion Management
A meaningful portion of infusion therapy cost is driven by the site of care rather than the underlying drug. Shifting treatment from hospital outpatient departments to specialty infusion centers or home-based infusion models can produce significant reductions in overall claim severity and total plan cost.
Leverage alternative provider arrangements
Self-funded employers have significant flexibility to adopt more efficient provider payment and network strategies, including narrow networks, direct contracting, reference-based pricing, and cash-pay models. These approaches can be layered within traditional networks to preserve access and employee acceptance while improving cost efficiency. Selecting the optimal provider strategy is often one of the most impactful levers for reducing total plan cost—and by extension, stop-loss premiums.
Index specific deductibles to offset leveraged trend
Leveraged trend reflects the amplified effect of first-dollar medical inflation on stop-loss reimbursements. For example, a $100,000 claim under a $50,000 specific deductible produces a $50,000 reimbursement. If the same claim increases by 10% to $110,000, the
stop-loss reimbursement rises to $60,000—a 20% increase on only a 10% increase in the underlying claim. This dynamic causes carrier exposure to grow faster than underlying medical inflation unless deductibles and premiums are regularly adjusted. Because the cost of expected claims rise annually, specific deductibles should be reviewed and indexed periodically.
Consider aggregating specific deductibles
In addition to selecting an appropriate specific deductible, an aggregating specific deductible can help moderate rate volatility. This structure adds a secondary layer of employer-retained risk above individual claim deductibles and is typically defined as a fixed annual threshold (e.g., $50,000 or $100,000). Once the aggregating specific threshold is met, the carrier begins reimbursing otherwise eligible claims, providing an additional mechanism for premium stabilization.


Captives
A longstanding principle in alternative risk is to transfer risk in soft markets and retain risk in hard markets. Group stop-loss captives have become one of the most significant growth mechanisms in selffunded healthcare, offering employers greater underwriting transparency, volatility control, and long-term financing stability. As the stop-loss market continues to harden, captives are likely to
Today’s stop-loss market demands more than rigid structures that offer stock solutions.
Confidence to Think Creatively


At Federal Life Insurance Company, entrepreneurial thinking is driven by institutional experience, creative solutions are executed with discipline, and flexibility comes from reliability.
Working with program administrators, TPAs, MGUs, brokers and intermediaries, our partnership-driven approach is built for program business today.

Fronting, Captives & Selective Risk Participation
Structured for flexible program design.
Easy to Work With
Responsive, collaborative, and structured to keep programs moving.
125+ Years of Insurance Experience
Disciplined execution backed by long-term stability.
Stop-Loss–Led A&H Program Business
Supporting modern group benefit strategies.
www.FederalLife.com •
become increasingly relevant as a tool for high-quality self-funded employers seeking to manage volatility and improve long-term rate predictability.
LOOKING AHEAD
The medical stop-loss market is not experiencing a routine cyclical shift; it is undergoing structural recalibration. Years of pricing compression, increasing claim severity, and expanding coverage expectations have converged to require a rebalancing of risk and pricing.
In the near term, this will likely result in higher costs and tighter underwriting. Over the longer term, however, a more disciplined market, characterized by appropriate pricing, stronger risk selection, and better-aligned incentives, can improve sustainability across the self-funded ecosystem.
Success for carriers, brokers, and employers will depend on adapting to this environment with analytical discipline, strategic flexibility, and a willingness to reconsider long-standing assumptions about risk transfer and cost management.
Phil Giles is Chief Growth Officer for Skyward Accident & Health. He has more than 38 years of experience including senior leadership roles within the medical stop-loss and captive industry. Phil has received multiple industry honors, including Captive International’s U.S. Reinsurance Individual of the Year (2023) and Cayman Reinsurance Individual of the Year (2019 and 2021). He was also named Captive Professional of the Year at the 2017 U.S. Captive Awards and has been named to Captive Review’s Power 50 listing of the most influential individuals in the worldwide captive industry.







STATE LEGISLATIVE SESSION WRAP-UP

Written By Anthony Murrello
TThroughout the year, SIIA’s Government Relations Team monitors and advocates for the self-insurance industry on a wide range of policy proposals advanced at the State level. This includes opposing efforts to enact unreasonable prohibitions on the sale of stop-loss insurance and efforts to erode ERISA’s preemption powers, while advocating for policies beneficial to stop-loss insurance coverage and captive insurance arrangements. Most of this work is done between January and June when the majority of the State Legislatures around the country are in Session.
Now that most state legislatures have adjourned for the year, we wanted to provide an update on the most relevant activity we tracked throughout 2026. Compared to 2025, this was a noticeably quieter year on the state legislative front for our issues. While we continued to see targeted proposals around stop-loss regulation and broader efforts that could have impacted self-insured plans, there were fewer large-scale, high-impact bills that advanced compared to prior sessions. At the same time, we also saw continued movement at the federal level, particularly with new PBM reform and prescription drug transparency measures.
Looking ahead, the 2026 cycle reinforced the ongoing themes we have been tracking: states continue to explore ways to address affordability through insurance regulation, while also testing the boundaries of ERISA preemption. On the captive side, enacted legislation generally continued a constructive trend toward expanding access and modernizing domicile frameworks, even if the overall pace of activity was lighter than in 2025. SIIA will continue to monitor developments in both state legislatures that remain in session or reconvene for special sessions, as well as any regulatory activity that may emerge heading into 2027 and will keep members informed as these policy discussions evolve.
COLORADO:
SB 26-178 – As introduced, SB 26-178 proposed approximately $140 million in health insurance assessments, including a $40 million assessment on health insurance companies. Early discussions indicated that the legislation's sponsors intended for stop-loss carriers to be included within the scope of those assessments. SIIA engaged alongside industry stakeholders to oppose the proposal, emphasizing that imposing additional assessments on stop-loss coverage would increase costs for employers sponsoring self-insured health plans and undermine access to self-funding as a risk management tool. We are pleased to report that opposition efforts were successful, and the assessment provisions impacting stop-loss carriers were removed from the final legislation before passage.
Status – Signed into law on June 3rd, 2026, and the assessment language impacting stop-loss carriers was removed.
HB 26-1327 – This bill is also known as a “Walmart bill,” it would impose an assessment on employers with 500 or more employees if a specified number of their workers were enrolled in the State Medicaid program. Although the bill was primarily directed at large employers rather than self-insured health plans specifically, the proposal was closely watched by SIIA and employer stakeholders due to its potential implications for employer-sponsored coverage and future efforts to shift public program costs onto private employers. The legislation faced significant opposition from employer organizations, including the U.S. Chamber of Commerce and the National Retail Federation.
Status – Passed the House but was postponed indefinitely in the Senate Finance Committee. The bill is effectively dead for the 2026 session.
CONNECTICUT:
SB 342 – Connecticut continues to be one of the most active states in pursuing policies affecting stoploss insurance and employer-sponsored self-insured health plans. Over the past decade, SIIA has opposed numerous proposals that would have effectively regulated self-funded arrangements as fully insured health coverage. This year's legislation directs the Insurance Commissioner to study "excess insurance," which may include stop-loss insurance arrangements utilized by employers sponsoring self-insured plans. While the bill does not directly regulate stop-loss coverage, SIIA remains attentive to these studies because they have historically served as precursors to future legislative proposals.
Status – The bill failed to pass the Legislature and is now dead.
MAINE:
Proposed Regulation 02.031, Chapter 135 – Employee Benefit Excess Insurance Standards – The Maine Bureau of Insurance proposed new standards governing employee benefit excess insurance, including stop-loss coverage. Among other provisions, the proposed regulation would prohibit carriers from providing financing arrangements below market rates for claims that have not yet reached the attachment point. The proposal would also require carriers to report stop-loss attachment points for each covered group. SIIA is monitoring the rulemaking process closely due to its potential impact on stop-loss product design and underwriting practices.
Status – Rulemaking remains ongoing.
NEW HAMPSHIRE:
SB 498 – SB 498 establishes the New Hampshire Children's Behavioral Health Association, which would be responsible for collecting assessments from certain "assessable entities" to fund children's behavioral health services. The definition of assessable entities includes insurance carriers, stop-loss insurers, and third-party administrators serving both fully insured and self-funded health plans. The legislation would establish a governing Board of Directors and create a new funding mechanism supported by assessments on market participants. Given the inclusion of stop-loss carriers and TPAs, SIIA has monitored the proposal closely to evaluate its potential impact on the self-insurance marketplace.
Status – The bill failed to pass the Legislature and is now dead.
Protect your business from the unexpected — and drive cost savings
When you add Anthem Stop Loss to an Anthem ASO medical plan, you can manage claims expectations and protect against catastrophic losses. There’s no need to coordinate with multiple vendors — everything is integrated into your Anthem plan. This helps make doing business simpler and reduces risk.
To learn more, contact your Anthem Sales Representative.



NEW JERSEY:
A.3543 / A.3284 / S.2890
– These bills were introduced as companion bills and would require insurers issuing stoploss (or excess risk) insurance to small employer health benefit plans to provide at least 90 days' written notice before canceling or declining to renew a policy. In addition to the 90-day cancellation/nonrenewal notice requirement, the bill codifies and reinforces existing New Jersey standards governing smallgroup stop-loss arrangements. Introduced January 13, 2026; referred to committee with no further action taken.
Status – The bills remain pending and alive through the 2026–2027 legislative session.
WASHINGTON:
HB 2626 – The bill proposed increasing the general premium tax on insurers from 2% to 3% while also creating a new 1% premium tax specifically applicable to stop-loss insurance. The proposal represents another example of states exploring additional revenue streams through targeted assessments on stop-loss coverage and related products.
SIIA opposed the bill, voicing our concern that proposals of this nature ultimately increase costs for employers sponsoring self-insured health plans and reduce access to affordable risk protection mechanisms.
Status – The bill failed to pass the Legislature and is now dead.
RHODE ISLAND:
HB 5465 – This bill would have established a universal, comprehensive, single-payer healthcare insurance program. The program would be funded by consolidating government and private payments into a Medicare-for-all style single-payer program. SIIA opposes any universal health plan proposals that create additional financial burdens on employers, and particularly on any organization sponsoring a self-insured health plan. The bill was held for further study and will not pass this year. This is the identical bill that was introduced in the 2024 session as HB 8242. SIIA expects this bill to be reintroduced in the next session as well, and we will continue to oppose proposals that limit employer choice in providing health benefits for their employees.
Status – Held for further study, and no further action taken in 2025
RECURRING FOCUS AREAS/TENDS
Captive Insurance - In 2026, the Captive Insurance legislation that was enacted across key states continued a clear trend toward expanding access to captive structures and reinforcing a more competitive, business-friendly domicile environment. States such as Vermont and South Carolina advanced modernization packages that refined governance standards, streamlined regulatory processes, and enhanced flexibility for protected cell and sponsored captive arrangements, while jurisdictions like Florida and Louisiana pursued updates to improve competitiveness and attract new captive formations. Iowa also strengthened its framework for specialized captive and reinsurance activity, particularly in the life and reserve financing space. As a continuation of the trend we have seen in recent years, the 2026 enacted bills reflect a broader pattern of states competing for captive business by reducing friction in formation and operation, enhancing regulatory clarity, and positioning captives as a more accessible risk financing tool for employers and other commercial entities.
ERISA
Preemption – State-oriented organizations (like NCOIL) and some trade groups (like the community pharmacists) have made it clear that they would like to chip away at ERISA’s preemption powers. On account of this interest, we have seen an uptick in State efforts to enact laws regulating PBMs. However, many of these State PBM laws have a “direct impact” on (1) a self-insured health plan’s design and (2) the administration of the self-insured plan. As a result, SIIA – along with our Coalition partners – believe these types of State PBM laws are preempted by ERISA, and we have made this point clear not only to the State Legislators and Insurance Commissioners, but we have argued in the courts that these types of State PBM laws are preempted by ERISA. At the Federal level, these same groups

have made noise on Capitol Hill about the extent and scope of ERISA’s preemption powers, arguing that Congress should limit ERISA preemption in certain cases. As part of our Federal lobbying efforts, SIIA has pushed back hard on these arguments. We remain vigilant and active in our pursuit to protect ERISA’s preemption powers. For more information on ERISA and our position, see SIIA’s White Paper on ERISA Preemption.
PBM/Drug Pricing Legislation – This year, there was a wave of Federal PBM reform activity, including provisions included in the Consolidated Appropriations Act of 2026, enacted in February, as well as the Department of Labor’s final regulations on compensation disclosure. However, states remained highly active in advancing their own drug pricing and PBM-related legislation. While overall volume was more targeted than the record-setting activity in 2025 (when more than 150 bills were introduced), states continued to pursue a broad range of policies focused on PBM regulation, pricing transparency, and prescription drug affordability. These proposals included expanded reporting and disclosure requirements for PBMs, as well as restrictions on utilization management tools such as prior authorization and step therapy, along with continued growth in Prescription Drug Affordability Boards (PDABs) aimed at addressing drug cost concerns.
A number of States have attempted to extend beyond PBM regulation and directly impact self-insured health plan design, including requirements that would influence how plans structure prescription drug benefits and reimburse pharmacies. SIIA has continued to maintain that these types of state-level PBM and drug pricing mandates are preempted under ERISA when applied to self-insured employer plans, and we remain actively engaged in opposing efforts that would directly or indirectly regulate self-insured plan design or operations at the state level.

Accelerating Progress



We study risk, research it, speak on it, share insights on it and pioneer new ways to manage it. With underwriters who have many years of experience as well as deep specialty and technical expertise, we’re proud to be known as experts in understanding risk. We continually search for fresh approaches, respond proactively to market changes, and bring new flexibility to our products. Our clients have been benefiting from our expertise for over 50 years. To be prepared for what tomorrow brings, contact us for all your medical stop loss and organ transplant insurance needs.
Tokio Marine HCC – A&H Group
HCC Life Insurance Company operating as Tokio Marine HCC – A&H Group
NAIC and NCOIL 2027 Priorities and State Legislative Efforts – The NAIC and NCOIL continue to play an increasingly active role in shaping the policy framework that influences state insurance regulation, including areas that can affect self-insured employer plans. In 2026, the NAIC updated its committee structure and expanded the scope of its Health Insurance and Managed Care (B) Committee, including a renewed focus within the ERISA and Alternative Health Coverage Working Group on “alternative health coverage.” Looking ahead to 2027, that working group is expected to concentrate on key issues, including ERISA preemption and state PBM laws, the development of a draft paper on level-funded arrangements, and a broader review of excepted benefits products such as short-term limited duration insurance, healthcare sharing ministries, and other arrangements marketed as alternatives to comprehensive major medical coverage. Together, these efforts reflect a continued regulatory interest in defining the boundaries between fully insured coverage, alternative products, and ERISA-governed self-insured plans.


Anthony Murrello is SIIA’s state government relations manager. He can be reached at amurrello@siia.org.
PASSAGE Safe

We deliver best-in-class solutions that cover your clients and support you with experts in data analytics, underwriting, claim reimbursements, dedicated account management and CompanionCARE SM
With CompanionCARE, you have access to experts in large case management and emerging therapies.
Our stop loss contracts are backed with the strength reflected in our A+ AM Best company rating.
In addition to specific and aggregate stop loss insurance, Companion Life offers an array of innovative products:
or

NEWS FROM SIIA MEMBERS
SIIA boasts a very active and dynamic membership. Here are some of the latest developments from member companies and individuals powering the self-insurance industry.
Tim O’Brien Named New President at HPI
Health Plans, Inc. (HPI), a leading national TPA of self-funded benefits and subsidiary of Point32Health, has announced the appointment of Tim O’Brien as president. O’Brien brings more than 25 years of experience across payer, third-party administration, PBM, care delivery, and surgical network organizations. Interim President Glenn MacFarlane worked closely with O’Brien to ensure a smooth leadership transition.

“Tim is an accomplished leader with deep experience across the healthcare ecosystem and a proven track record of driving growth and innovation. His expertise in building high-performing organizations and delivering clientfocused solutions makes him the right leader for HPI’s next chapter,” said Marti Lolli, executive vice president of markets & chief growth officer at Point32Health. "We’re excited to welcome Tim and confident that he'll further strengthen HPI’s position as a trusted partner to brokers and employers nationwide.”
“I’m excited to join HPI and build on the strong foundation already in place,” said O’Brien. “The organization has established a reputation for delivering flexible, outcome-focused solutions. I look forward to working with the team to advance operational excellence, accelerate growth, and expand our impact across the healthcare ecosystem.”
O’Brien joins HPI from Vitori Health, a vertically integrated health plan platform, where he served as chief executive officer. He led the company through a period of significant growth, culminating in a successful exit to Global Excel Management in 2025. Prior to joining Vitori Health, O’Brien served as division president at Blue Cross Blue Shield of Kansas City and as president and COO of Nueterra Companies.
Vālenz Announses New CEO
Vālenz Health® has announced the appointment of Vince Cole as its new Chief Executive Officer.
Cole draws on more than three decades of executive leadership experience spanning healthcare services, insurance, and global enterprise transformation. Most recently, he served as Chief Executive Officer of Ontellus, where he led the nation’s largest technology-enabled medical and legal records retrieval business. Prior to that he served as CEO, Americas, of professional services firm Charles Taylor, and CEO, Americas, of publicly traded Crawford & Company, the world’s largest provider of claims management solutions to the risk management and insurance industries.

“Vālenz is entering an exciting new phase of growth from a position of strength and confidence in the vision,” said Hank Mannix, Investment Partner at Kelso & Company, the private equity sponsor of Vālenz. “Vince brings deep experience operating at scale, a proven ability to drive organic growth, and a strong track record of building high-performance teams in dynamic and complex industries.”
“I am honored to join Vālenz at such a pivotal moment,” Cole said. “The company has built a strong foundation, and I look forward to working with the team to expand impact, strengthen partnerships, and continue delivering on its mission to support strong, vigorous, and healthy lives for all.”
Tim O'Brien Health Plans, Inc. (HPI)
Vince Cole Vālenz Health®
Cole’s appointment follows an intentional and thoughtful succession process aimed at positioning the company for its next phase of growth and expansion. He succeeds Rob Gelb, who will transition to the role of Non-Executive Chairman of the Vālenz Board of Directors..
MedWatch Expands it Business Development Team
MedWatch is pleased to announce the addition of Kari-Ann Karaffa as Vice President of Business Development.
Karaffa brings more than 15 years of experience across healthcare technology and employee benefits sectors. She is recognized for advancing business development initiatives, strengthening client relationships, and delivering long-term value for partners.
Most recently, she served as a Senior Client Success Manager, where she oversaw key Reference-Based Pricing partnerships, including a large national book of business. In this role, she partnered closely with employer groups nationwide to support strong service delivery and positive client outcomes. Earlier in her career, Karaffa held multiple Vice President of Business Development roles, leading strategic growth efforts and building high-impact relationships across the industry.
Costly Claims Don’t Untangle Themselves



Kari-Ann Karaffa MedWatch
Sourced exclusively from licensed Canadian pharmacies — DIN-matched, pharmacist-verified, cold-chain certified. 30–70% below domestic cost. Same therapies. Zero disruption.
100%
CANADA-SOURCED
Licensed Canadian pharmacies. Every order documented.
DIN → NDC
MATCHED EQUIVALENCE
Every drug DIN-matched to U.S. NDC. Therapeutic equivalence.
One country. One standard. Fully documented.
30–70%
DAY-1 SAVINGS
Not a rebate. Immediate cost reduction from the first fill.
$0
WORKFLOW CHANGE
Overlays your existing PBM or TPA program seamlessly.
Day 1
SAVINGS BEGIN
No ramp-up, no rebate lag. Savings on the first claim cycle.
We source exclusively through licensed Canadian pharmacies and prove it on every order — pharmacist credentials, cold-chain records, and dispensing documentation. No grey market. No mystery origins.
COST-CONTAINMENT PROGRAMS
Your fastest-growing cost has a proven answer.
GLP-1s and biologics are your #1 uncontrolled specialty spend. ColdRxMeds delivers 30·70% immediate savings with CFO-ready quarterly reporting · audit-ready, board-presentable, measurable from the first fill. Not a rebate. A permanent cost layer.
REGULATION
Licensed Canadian Rx
DIN-matched to every U.S. NDC.
PBMS & TPAS
Zero disruption. Instant overlay. No rip-and-replace.
We plug into your existing formulary and plan design · no rip-and-replace. Full cold-chain logistics, temperature-controlled shipping, and compliance documentation on every order. DIN-to-NDC matching confirms equivalence.
BROKERS
& CONSULTANTS
The specialty tool your clients haven't seen yet.
Canadian sourcing is the international option you can defend at the regulatory level · and prove to skeptical CFOs. Bring 30·70% savings to your next renewal conversation. Measurable ROI from day one.
LOGISTICS
Cold Chain End-to-End
Temp-controlled, pharmacy to member's door.
VERIFICATION
Pharmacist-Reviewed
Licensed Canadian pharmacist on every order.
BUILT FOR
Benefits Brokers & Consultants
Third-Party Administrators
Pharmacy Benefit Managers
Cost-Containment Programs
Self-Insured Employers
Confidential · No Commitment
COMPLIANCE
Audit-Ready Docs
Full documentation with every shipment.

“Kari-Ann’s deep industry relationships and long-standing connection to MedWatch make her a natural fit for this role,” said Sally-Ann Polson, MedWatch President and CEO. “She brings a thoughtful, partner-first approach and a strong understanding of the market that will help us continue to expand and strengthen the value we deliver to our clients.”
Reflect Health Appoints New Operations Executive

Reflect Health, the Benefits Hub built for modern healthcare programs and strategic partners, announced the appointment of Be-bi Singh as Senior Vice President of Operations and Performance. Singh brings decades of healthcare operations leadership experience, including extensive expertise managing complex third-party administrator (TPA) implementations, operational transformations, and large-scale healthcare initiatives.
In her role, Singh will lead operational strategy and performance optimization initiatives across Reflect Health’s growing platform. Her focus will be on strengthening health plan integrations, streamlining vendor connectivity, enhancing operational efficiency, and driving improved outcomes for clients and partners.

Be-bi Singh Reflect Health

“Be-bi brings an exceptional combination of operational leadership, strategic insight, and deep industry expertise,” said Vincent Esposito, CEO of Reflect Health. “We are excited to officially welcome her into this leadership role. Since joining Reflect Health earlier this year, she has already helped drive meaningful operational improvements, strengthen execution across teams, and elevate the experience we deliver to our clients and partners. Her experience navigating complex TPA implementations and large-scale healthcare operations has made an immediate impact.”
Prior to joining Reflect Health, Singh led operational and implementation initiatives across major healthcare organizations – including most recently at Anthem – where she built a strong reputation for improving service delivery models, managing large-scale integrations, and developing high-performing operational teams.
Custom Design Benefits announced that Julie D. Mueller, President and Chief Executive Officer, has completed the purchase of the remaining outstanding ownership of the company from its previous investors, resulting in full private ownership by Mueller.
Founded in 1991, Custom Design Benefits is an independent third-party administrator that partners with employers and their broker partners to design, implement, and manage customized benefits strategies. The firm is known for its client first approach, innovative thinking, and long-term relationships built on trust, transparency, and measurable results.

Mueller has led Custom Design Benefits since 2016 and has served as CEO throughout a period of sustained growth, expansion of services, and deepened client impact. The completion of this transaction marks a significant milestone in the company’s evolution and reinforces Mueller’s long-term commitment to the firm’s mission, clients, and employees.

IS Benefits Strengthens Its Marketing Team
Integrated Solutions for Benefits and Insurance Services (IS Benefits), a leading provider of stop-loss marketing and cost containment solutions for self-funded employers, is pleased to announce the appointment of Shale Cooper as Director of Stop-loss Marketing.
In this role, Shale will lead the company's stop-loss marketing initiatives, overseeing the RFP and renewal process while strengthening strategic relationships with brokers, consultants, third-party administrators (TPAs), carriers, and managing general underwriters (MGUs). His expertise will further enhance Integrated Solutions' consultative approach to stop-loss placement, helping partners navigate an increasingly complex and rapidly evolving market.
Julie Mueller Custom Design Benefits
Shale Cooper Integrated Solutions
Custom Solutions > One-Size-Fits-All

We make it easier to deliver forward-thinking self-funded strategies tailored to your evolving workforce needs.
No two employers are alike. So why settle for benefits providers that treat you that way?
We partner with self-funded employers to create smarter, more personalized benefits strategies that integrate service and support into one seamless experience. Because better healthcare solutions start with flexibility, partnership, and a plan built around people—not processes.
Are you ready for benefits planning time? Let’s talk. pinnacletpa.com/excellence
Most recently, Shale served as Director of Stop-loss Sales at a group medical stop-loss captive, where he developed and led sales and go-to-market strategy. Prior to that, he held integral positions at Health Care Service Corporation (HCSC), where he helped strengthen one of the nation's largest direct writers of stop-loss coverage through strategic initiatives, sales enablement, and market development. Earlier in his career, Shale served as a Stop-loss Specialist at Sun Life, cultivating broker and consultant relationships through a consultative approach centered on education and partnership.
"Shale's experience spans nearly every facet of the stop-loss ecosystem—from consulting and carrier relationships to captive strategy and employer advisory work," said Tyler Benware, Chief Executive Officer of Integrated Solutions. "As healthcare costs continue to rise and the stop-loss market becomes increasingly challenging, our partners need more than transactional marketing support. They need a strategic advisor who understands risk, asks the right questions, and helps uncover opportunities to improve outcomes. Shale embodies that approach, and we're thrilled to welcome him to the team."
Clay Kelley Joins QBE Captive Team
QBE North America has appointed Clay Kelley as assistant vice president, captives, where he will work with advisers and employer groups on healthcare cost strategies and solutions.

®


If you can’t see risk, you can’t price it. But the most consequential stop-loss risks rarely announce themselves. Only Curv blends clincial insight with actuarial rigor to expose the catastrophic claims lurking behind group health data—so you can underwrite with confidence.
rxhistories.com/curv/group-health

Kelley brings more than 25 years of experience in self-funded healthcare benefits, with expertise spanning the administration of self-funded plans, stop-loss underwriting, and products including captives and consortiums. He describes himself as a trusted adviser to brokers seeking solutions for clients that are already self-funded or are looking to move to a self-funded platform from fully insured arrangements.
He joins from Blackwell Captive Solutions, where he served as assistant vice president of sales, captives. Before that he held the role of regional vice president at ClearPoint Health, and earlier sales leadership positions at Crescent Health Solutions, Maestro Health and Planned Administrators. His earlier career included stop-loss and client services roles at HM Insurance Group and Key Benefit Administrators.
Brad Feldman Joins C&F Stop-Loss Underwriting Team
Crum & Forster’s (C&F) Accident & Health Division announces that Brett Feldman has joined the company as Vice President of C&F Stop-loss Underwriting within the Division’s Medical Business Unit. In this role, Feldman will shape the growth strategy for C&F’s stop-loss business, with oversight of product development, portfolio management, and strategic initiatives.
Service Matters Under Renewal Pressure
While cost often leads renewal conversations, service can be the difference between a plan that works on paper and a partner that works in practice.
With BRMS, you gain expert guidance focused on:

Building trusted and valued relationships with clients and members
Fully integrated team support across every stage of plan administration
Proactive plan management and comprehensive strategic direction
BRMS is Your Partner in Every Season. Learn more at brmsonline.com
“BRMS is always so helpful…Their professionalism and dedication make working with them a positive experience.”
-BRMS Client
Clay Kelley QBE North America

Brett Feldman Crum & Forster Accident & Health
“Brett brings a rare blend of underwriting discipline, strategic thinking, and team leadership to Crum & Forster,” said David Webb, Senior Vice President, C&F Stop-loss within the A&H Division’s Medical Business Unit at Crum & Forster. “His extensive experience in the stop-loss space will be invaluable as we continue to expand our capabilities and deepen our market presence. We are excited to welcome Brett and look forward to the positive contributions he will bring.”
A seasoned industry veteran, Feldman has spent his career developing high-performing teams and executing growth strategies across the stoploss and captive markets. He joins C&F from Captive Resources, Inc., where he served as Head of MSL Underwriting and led the build-out of the company’s Health Solutions Underwriting function
“I am honored to join the C&F Stop-loss team at such an exciting time for the business,” said Feldman. “Crum & Forster’s commitment to disciplined underwriting, thoughtful growth, and strong client and broker partnerships aligns closely with my own approach. I look forward to working with the team to expand our capabilities, deliver even greater value to our partners, and continue building on the strong foundation already in place.”
Skyward Names New Head of A&H Actuarial
Skyward A&H is pleased to announce the appointment of Harry Gong, FSA, CERA, MAAA, as Senior Vice President, Head of A&H Actuarial.
Harry brings approximately 18 years of distinguished industry experience, having previously held key leadership positions at Aon, RGA, and UnitedHealthcare. His robust credentials and extensive expertise in the reinsurance sector provide the perfect strategic blend to support Skyward’s growing medical stop-loss business.
“Our ability to provide our clients with top-notch service stems from building a leadership team of the industry’s top talent, and Harry exemplifies that standard,” said Mike Remeika, Divisional President of Skyward A&H. “He comes to us with an exceptional reputation, and his actuarial insight is second to none. His broad knowledge and deep expertise will help us further strengthen our market position and deliver even greater value to our clients.”
Harry expressed his enthusiasm for role stating:

“I am thrilled to join the talented team at Skyward. I have long admired the company's dynamic momentum in the market and their unwavering commitment to a client-focused philosophy. I look forward to leveraging my experience to drive innovative solutions and contribute to the continued growth and success of the A&H division.”
Harry Gong Skyward Specialty
Greg Arms to Advise EvolTech
EvolTech is pleased to announce the appointment of Greg Arms as Senior Strategic supporting the company’s continued growth and market expansion.
Greg is a 40-year insurance industry veteran with deep experience in the Life, Health, and Pension insurance sectors, both in the US and internationally. Over the course of his career, he has held senior leadership roles at the industry’s foremost insurance carriers and brokers. In his advisory role, he will work closely with EvolTech’s leadership team to provide strategic insight into market trends, operational challenges, and the evolving needs of organizations within the insurance and healthcare ecosystem.
“We are thrilled to welcome Greg to EvolTech as a Senior Strategic Advisor. His strategic perspective, global experience, and strong relationships across the insurance and healthcare-related sectors will help EvolTech better address the evolving needs of organizations across industries and geographies,” commented Thulasidharan LG, CEO, EvolTech.

MINES and Associates is One to Watch in Colorado
"I’m excited to share that MINES and Associates was recognized as a 2026 Colorado Companies to Watch winner in the Empowering Colorado category," said Dani Kimlinger, PhD, MHA, SPHR, SHRM-SCP, Chief Executive Officer and Partner @ MINES and Associates.
"We had the privilege of accepting this award on behalf of our team. The metrics behind each organization tell an important story, but behind every number are people who care deeply about serving others."
For more than 45 years, MINES has been committed to supporting the wellbeing of individuals, families, workplaces, and communities. As the needs of those we serve continue to evolve, I am especially proud of how our team embraces innovation while staying true to our mission and values.


Dani Kimlinger MINES and Associates
Sarah Novak promoted at zakipoint Health
zakipoint Health announced that Sarah Novak has been promoted to Director of Customer Success.
In her expanded role, Sarah will lead our Customer Success strategy, oversee client retention, drive implementation oversight, and ensure that every customer and partner realizes measurable outcomes from zakipoint Health's platform and services.
Merger of Two MGUs Creates Jencap A&H

International Assurance of Tennessee Inc. and Aran Insurance Underwriters, two highly respected stop-loss managing general underwriters, announced the combination of their operations under a new unified brand—Jencap A&H Insurance Solutions (Jencap A&H). The newly aligned platform brings together deep underwriting expertise, national reach, and expanded capabilities to better serve brokers, carriers, and clients.


Sarah Novak zakipoint Health
“This is a meaningful step forward for our business and our partners,” said the President of Jencap A&H, Scott Eastland. “Jencap A&H will continue to build on the strong reputations of both organizations while delivering a unified, forward-looking platform designed for growth.”
Together, the combined operations will deliver broader market access, enhanced program flexibility, and deeper underwriting resources—all backed by the scale and strength of the Jencap platform. By aligning best-in-class teams and capabilities, Jencap A&H is positioned to accelerate growth while continuing to deliver the service, responsiveness, and expertise brokers rely on.
“Each legacy company brings more than 40 years of experience in the medical stop-loss industry,” said Brandon Baisden, Chief Revenue Officer at Jencap A&H. “This next chapter creates a stronger, more scalable platform for our TPA’s and brokers—expanding geographic reach, enhancing underwriting capabilities, and unlocking new opportunities for partners nationwide.”

2026 SELF-INSURANCE INSTITUTE OF AMERICA
BOARD OF DIRECTORS
CHAIRWOMAN OF THE BOARD*
Amy Gasbarro
President
ELMCRx Solutions
CHAIRPERSON ELECT, TREASURER AND CORPORATE SECRETARY*
Mark Lawrence
President
HM Insurance Group
BOARD MEMBER
Blake Allison
Chief Executive Officer
Employers Health Network
BOARD MEMBER
Christine Cooper
CEO
aequum, LLC
BOARD MEMBER
Orlo “Spike” Dietrich Operating Partner
Ansley Capital Group
BOARD MEMBER
Jeffrey Fitzgerald
General Manager, MHW Benefit Partners
MedImpact
BOARD MEMBER
John Fries
Head Accident & Health NA
Swiss Re Corporate Solutions
BOARD MEMBER
Matthew Smith
Managing Director
Brown & Brown Healthcare
BOARD MEMBER
Beth Turbitt
Managing Director
Aon Re, Inc.
VOLUNTEER COMMITTEE CHAIRS
Captive Insurance Committee
George M. Belokas, FCAS, MAAA
President
Beyond Risk
Future Leaders Committee
Morgan Sandell
Operations Lead, Underwriting Operations
QBE North America
Price Transparency Committee
Traci McGinnis
Founder & Principal
Datavoce Consulting, LLC
Cell and Gene Task Force
Ashley Hume President
Emerging Therapy Solutions®
* Also serves as Director
SIIA NEW MEMBERS
CORPORATE MEMBERS:
Paige Ahern
Senior Account Consultant
PBIRx, Inc. Shelton, CT
Samuel Bojorquez Project Manager Wells Onyx Tallahassee, FL
Debra Buss
Underwriting Manager Geisinger Health Plan Danville, PA
Kristina R. Campbell VP Benefits FP&A Group Management Services Richfield, OH
Nicole Connell VP of Business Development Pharma Strategies Atlanta, GA
Brad Coppens
President & Managing Partner
InTandem Capital Partners New York, NY
Scott Helfrich
Commercial Leader
U.S. Preventive Medicine Jacksonville, FL
Blair Hunnicutt
Account Development Executive
RR DONNELLEY Chicago, IL
Prerana Jakhotia
Lead AI Product Manager Blue Cross Blue Shield Chicago, IL
Matthew Lund CEO/President
Fortune Management Inc Seattle, WA
Verona Macdonell
Marketing Health Data Innovations Beachwood, OH
William R. Mattecheck, CLU RHU CEO
Face Rock Enterprises Portland, OR
Traci McGinnis
Founder & Principal Datavoce Consulting, LLC Charleston, SC
Sarah Peccia
Associate Vice President Fengate Asset Management Toronto, ON
Mario Richter
Head of Alternative Risk
Starkweather & Shepley East Providence, RI
Mark Selna CEO HealthBay Dallas, TX
Jim Sherry VP National Sales
Daffodil Health West Chester, PA
Priscilla L. Strom Chief Growth Officer Metre Nashville, TN
Terra Vennard
Executive Director, Marketing Medcor McHenry, IL
EMPLOYER MEMBERS:
Casey Duininck
Director of Risk Services
Better Health Collective Staples, MN
Dani Kimlinger CEO & Partner
MINES & Associates
Les Boughner Chairman
Advantage Insurance

Liz Midtlien Head of Large Claims Solutions BCS Financial Corporation
Matt Hayward Office President Ryan Specialty
BOARD OF DIRECTORS
Jonathan Socko President East Coast Underwriters, LLC
Nigel Wallbank SIEF Chairman Emeritus
The integrated TPA platform built for self-insured health plans
Care Compass connects enrollment, claims adjudication, and compliance reporting in a single system — so your team stops reconciling across vendors and starts running a tighter operation.
PILLAR 1
Compliance built into daily work
Most self-insured plans run claims, care, and reporting on separate systems. That disconnection creates errors, audit risk, and administrative burden your team absorbs every day.
SELF-INSURED EMPLOYERS See
Audit trails, regulatory reporting, and discrepancy detection embedded in every workflow — not a separate process at audit time.
PILLAR 2
One system, not a stack of vendors
Claims adjudication, provider payments, enrollment, and care management all run on the same platform. No duplicate entry. No data gaps.
PILLAR 3
A foundation that scales with you
Add programs, grow census, or expand services without replatforming. 30 years of complex care experience behind it.
A $51K health bill is enough to stop anyone in their tracks

Zelis Health Bill Assist SM gives members the support they need to understand complicated bills, explore their options and move toward resolution.
Expert guidance can help turn a stressful billing moment into a better member experience.

Scan to see how Zelis helped one member avoid a $51K health bill.

Predictability happens when expertise leads.
Managing uncertainty through a range of insights.
At HM Insurance Group, experts guide every decision. Our experienced minds bring together curated data, clinical analysis and disciplined underwriting to help manage complex risk and deliver the right Stop Loss coverage at the right price. It’s a reliable method our brokers stand behind — in a market that’s anything but predictable.
Experience predictability in practice. Visit hmig.com/predictability.