PREFACE
Thediscoveryoftheruddyglobules(redcells)isattributedtoJan Swammerdam(1637-1680)inAmsterdam;but,itwasAntonjvan Leeuwenhoek(1632-1723)ofDelft,whoasaresultofhisabilitytogrind lenseswithgreatermagnifyingpower(x275),madeamoredetailed descriptionofredcells,delineatingtheirgrossstructure.
Thebiochemistry,physiology,andbiophysicsoftheredcellhave beenstudiedintensivelyoverthreecenturiesand,althoughconsidered a“simple”structure,sinceitisanucleateandafteronedayinthecirculationhasnocytoplasmicorganelles,itsmysterieshavebeenslow tobeunraveled.Theprocessofenucleationoftheerythroblastinthe hematopoieticspaceandthemovementoftheanucleatecellfromthe hematopoieticspacetothemarrowsinusandfromtheretothesystemiccirculation,accomplishedbyacellwithoutanintrinsicapparatus tosupportamoeboidmotility,andthedeterminantsofitsaveragelife spanofapproximately120daysarestillbeingelucidated.Itsstructural andbiophysicalproperties,biochemicalpathways,andtherelationship amongthosefeatureshavebeenofcontinuedinteresttoscientists.Its absenceofinterferinggranules,containingproteolyticenzymes,organelles,andothercomplexitieshaveallowedtheisolationofhighlypurifiedredcellmembranesandtheearlyexplorationofthebiochemical andbiophysicalfeaturesofcellmembranes,applicabletoothercells, includingthecharacteristicsofmembranetransportofvariousmolecules.Thenatureofthestructureandfunctionofhemoglobinandthe explorationoftheglycolyticpathway,thehexosemonophosphateshunt, andtheLuebering-Rapoportpathwaywereotherrewardsreapedfrom thestudyofredcells.
Muchisknown,butasourmentor,friend,andcolleague,Ernest Beutler,cautionedPh.D.graduatesataScrippsInstitutedoctoralgraduation,oneshouldnotassumethatourunderstandingofthebiomedical sciencesissoprofoundthatwhatisleftforusistofillinsomegaps. Hearguedthatmuchfundamentalbiomedicalknowledgewasstill undiscoveredandwaitingtobeilluminated.Amonghismanycontributionstothepathogenesisofdiseaseandapplicationoftherapy,his contributionstounderstandingtheredcellandanemiawerenotable. Theseobservationsincludedaclassicseriesofpapersdescribingthe effectsofoxidantstressonindividualswithredcellglucose-6-phosphate dehydrogenasedeficiencyandalife-longinterestintheenzyme’svariantsandepidemiology.Hismonographonmethodsformeasuringred cellenzymeswasanearlycontributiontoenhancingthespecificityof thediagnosisofhemolyticanemia.Publishedoverfivedecadesago, itremainsanunsurpassedsourceofmethodsfortheassayofredcell enzymes.Beutler,also,usedredcellenzymemeasurementasasurrogate fordiagnosisofsystemic,untilthendifficulttodiagnosediseases,such asgalactosemia,glycogenstoragedisorders,andothers.Hefoundthat redcellglucose-6-phosphatedehydrogenasedeficiencywasinherited asanXchromosome-linkeddisorderanddescribedthemosaicismof normalanddeficientredcellsinheterozygousfemales.Thisfindingof mosaicismprovidedthebasisforanintellectualjumptothehypothesis ofXchromosomeinactivationinhumans,coincidentwithMaryLyon’s descriptionofthephenomenoninmice.He,also,madeseminalcontributionstounderstandingtheeffectsofirondeficiencyinnon-anemic womenandtheexpressionofironoverloadinthosehomozygousfor theHFEmutationandthevalueofadditivesforprolongedstorageof redcells,stillincurrentuse.
WithnoDNAorRNAsynthesis,nomitochondriaandtheir relatedenzymaticbiochemicalenergygeneratingpathways,andwith arelativelyshortlifespan,thisamitoticcellissustainedatanormal
concentrationinthebloodbyarobustdailyproductionofnewcellsin themarrow,theprocessoferythropoiesis.Thisprocessdeliverstwoto threemillionnewredcellstothebloodpersecond.Althoughremarkable,itisalsoavulnerabilityshouldredcellproductionbedampenedby diseaseorsubstrateinsufficiency:thelatter,aprincipalcauseofanemia.
In1929,3yearsafterobtaininghisM.D.degreeattheUniversityof Manitoba,hisfamilyhavingimmigratedtoCanadafromAustria,Maxwell MyerWintrobe,obtainedhisPh.D.atTulaneUniversity,hisdoctoral thesisentitled“TheErythrocyteinMan.”Wintrobeisconsideredthe fatherofclinicalhematologyhavingpublishedthefirstcomprehensive textintheEnglishlanguage,ClinicalHematology,in1942.Heintroducedthetechniqueofthehematocritdevicetomeasurethepacked redcellvolumeatatimewhenhemoglobinandredcellcountmeasurementswereneitheraccuratenorreproducible.Theword“hematocrit”wassoappealingthatitbecameasynonymforthepackedred cellvolumeratherthantheinstrumentofmeasurementasintendedby Wintrobe.Initially,the“Wintrobe”tube,asitbecameknown,wasfilled bypipettewithbloodtothe1mLmarketchedonthetubeandthegradationsonthetubeallowedonetoreadthefractionofbloodthatwas composedofredcellsaftercentrifugation.Later,themicrohematocrit centrifuge,whichreachedG-forcesthatremovedplasmatrappingasa significantconsiderationinthemeasurementincapillarytubesfilled withblood,couldbefoundoneverywardandclinicallaboratoryasthe principalmeanstomeasurethepackedredcellvolumeand,thereby, identifyanemiaorerythrocytosis.Achartallowedthedetermination ofthepackedcellvolumewhenthecapillarytube,regardlessofthe volumeofblooditcontained,wasplacedagainstitsscales.Wintrobe institutionalizedtheredcellindices,meancellvolume(MCV),mean cellhemoglobin(MCH),andmeancellhemoglobinconcentration (MCHC)andshowedintwoclassicpaperin1930and1934thatone couldclassifytheanemiasfordiagnosticpurposesbydistinguishing amongmacrocytic,normocytic,simplemicrocytic,andhypochromic microcyticanemias,amethodofdifferentialdiagnosisstillusedtoday. AftermovingtotheUniversityofUtahfromJohnsHopkinsUniversity, Wintrobeestablishedoneofthemostesteemedhematologyclinicaland researchtrainingprogramsintheworld.Healsodescribedalongwith hiscolleagueGeorgeCartwrightthattheaveragehematocritandhemoglobinconcentrationwashigherinresidentsofSaltLakeCity(elevation4300feet)thanthevalueobservedatJohnsHopkinsinBaltimore (elevation480feet).Hededucedfromthatprescientobservationthat hypoxia,inthatinstancefromhigheraltitude,isaprincipalregulatorof normalerythropoiesis.
In1953,F.WilliamSundermanandcolleaguesenhancedtheaccuracyofbloodhemoglobinmeasurementbyintroducingthecyanmethemoglobinmethod.In1956,WallaceCoulterintroducedhishigh-speed, automaticbloodcellcountermakingbloodcellcountingaccurate, reproducible,andcapableofmeetingthedemandsofabusyclinicand hospitalenvironment.The“CoulterPrinciple”heldthatcellsarepoor conductorsofelectricityinasaltsolution.Thus,whencellsarediluted insalineandaredrawnthroughatinyaperturecarryingacurrent,each cellproducesaslightimpedancetocurrentflowasitpassesthroughthe narrowaperture.Thepulsecreatedbythisimpedancecanbeamplifiedandcounted.Moreover,thesizeofthepulseisproportionaltocell volume.Thus,thenumberandvolumedistributionofredcellsina measuredvolumeofsolutioncanbeconvertedtoredcellcountand volumeelectronically.Theirproduct,redcellcountandredcellvolume, providedthehematocrit,nowaderivedvalue.Thousandsofcellscan
SUMMARY
Collectively,theerythroidprogenitors,terminallydifferentiatingerythroblasts (precursors),andadultredcellsaretermedtheerythrontoreinforcetheidea thattheyfunctionasanorgan.Thewidelydispersedcellscomprisingthis organarisefrompluripotentialhematopoieticstemcells.Followingcommitmenttotheerythroidlineage(unipotentialprogenitor),furthermaturation givesrisetotheerythroidprogenitors,burst-formingunit–erythroid(BFU-E) and,subsequently,colony-formingunit–erythroid(CFU-E),thatcanbeidentifiedbytheirdevelopmentintorepresentativeclonalcoloniesofredcellsin vitro.TheCFU-Ethenundergoesterminaldifferentiation,progressingthrough fourtofivemorphologicstages,eachhavingcharacteristiclightmicroscopic andultrastructuralfeatures.Duringterminalerythroiddifferentiation,there isanincreasingamountofhemoglobinsynthesisaccompaniedbynuclear chromatincondensation,andatthefinalstageofdifferentiation,thereis nuclearextrusiontogenerateananucleatepolychromatophilicmacrocyte (reticulocytewithsupravitalstaining).Thehumanpolychromatophilicmacrocyte(reticulocyte)maturesover2to3days,firstinthemarrowandthen incirculationintothediscoiderythrocyte.Duringreticulocytematuration, cytoplasmicinclusions,includingresidualmitochondriaandribosomes,are degraded,andthereticulocytelosessurfaceareatoachievethemeancell volumeandsurfaceareaofadiscoidalerythrocyte.Matureerythrocytesare approximately7to8μmindiameterandundergoextensivedeformationto passthrough3-μm-diametercapillariesandthe1-μm-wideand0.5-μm-thick endothelialslitsintheredpulpofthespleen.Theabilityoftheredcellto undergoextensivereversibledeformationisessentialforbothitsfunctionand itssurvival.Redcelldeformabilityisafunctionofitsgeometry,theviscosity
ofthecytoplasm,largelydeterminedbytheconcentrationofhemoglobin. Decreaseddeformabilityisafeatureofredcellsinvariouspathologicstates. Theerythrocyteisuniqueamongeukaryoticcellsinthatitsprincipalphysicalstructureisitscellmembrane,whichenclosesaconcentratedhemoglobin solution.Thus,allstructuralpropertiesofthiscellareinsomewaylinkedtothe cellmembrane.Incontrasttoothercells,theerythrocytehasnocytoplasmic structuresororganelles.Amonghumancells,onlyredcellsandplateletsdo nothaveanucleus.
ERYTHRON
Themassofcirculatingerythrocytesconstitutesanorganresponsible forthetransportofoxygentotissuesandtheremovalofcarbondioxidefromtissuesforexhalation.Collectively,theprogenitors,precursors, andadultredcellsmakeupanorgantermedtheerythron,whicharises frompluripotentialhematopoieticstemcells.Followingcommitment totheerythroidlineage,unipotentialprogenitorsmatureintotheerythroidprogenitors,theburst-formingunit–erythroid(BFU-E)and, subsequently,thecolony-formingunit–erythroid(CFU-E),whichthen undergoesfurthermaturationtogenerateanucleatepolychromatophilic macrocytes(reticulocytesonsupravitalstaining).TheBFU-Eand CFU-Eareidentifiedbytheirdevelopmentintomorphologicallyidentifiableclonalcoloniesofredcellsinvitro.Thereticulocytefurther matures,firstinthemarrowfor2to3daysand,subsequently,inthe circulationforapproximately1day,togeneratediscoiderythrocytes.1-5 Theproerythroblast,thefirstmorphologicallyrecognizableerythroid precursorcellinthemarrow,typicallyundergoes5mitoses(range4-6) beforematurationtoanorthochromaticerythroblast,whichthenundergoesnuclearextrusion.Afeatureoferythropoiesisisthataftereachcell division,thedaughtercellsadvanceintheirstateofmaturationwith significantchangesingeneandproteinexpressioncomparedwiththe parentcelland,ultimately,becomefunctionalasmatureerythrocytes.4 Inthisprocess,theyacquirethehumanbloodgroupantigens,transport proteins,andallcomponentsoftheerythrocytemembrane.4,6
Intheadultstageofdevelopment,thetotalnumberofcirculatingerythrocytesisinasteadystate,unlessperturbedbyapathologic orenvironmentalinsult.Thiseffectdoesnotholdduringgrowthof theindividualinutero,particularlyintheearlystagesofembryonic developmentandduringneonataldevelopmentasthetotalbloodvolumeincreasesmarkedly.Consequently,erythrocyteproductioninthe embryoandfetusdiffersmarkedlyfromthatintheadult.
THEEARLIESTERYTHRON
AcronymsandAbbreviations:BFU-E,burst-formingunit–erythroid;CFU-E, colony-formingunit–erythroid;cP,centipoise;DIC,disseminatedintravascular coagulation;EMP,erythroblastmacrophageprotein;ICAM-4,intercellular adhesionmolecule-4;IL,interleukin;MCH,meancellhemoglobincontent;MCHC, meancorpuscularhemoglobinconcentration;MCV,meancellvolume;MDS, myelodysplasticsyndrome;SA:V,surfacearea-to-volumeratio;TTP,thrombotic thrombocytopenicpurpura.
*ThischaptercontainstextwrittenforpreviouseditionsofthisbookbyBrianBull, PaulHerrmann,andErnestBeutler.
Intheveryearlystagesofhumangrowthanddevelopment,thereare twoformsoferythroiddifferentiation:primitiveanddefinitive.7-10 Chapters2and17providedetailedinformationofembryonicand fetalhematopoiesis.Theprimitiveerythronsuppliestheembryowith oxygenduringthephaseofrapidgrowthbeforethedefinitiveformof maturationhashadachancetodevelopandseedanappropriateniche. Thehallmarkofthisprimitiveerythronisthereleaseofnucleatederythroidprecursorscontainingembryonichemoglobin.Althoughprimitiveinthesensethatthecellscontainnucleiwhenreleasedintothe circulation,thisformofmaturationdiffersfromavianandreptilian erythropoiesisinthatthenucleusiseventuallyexpelledfromthemammaliancellsastheycirculate.Thetransientpresenceofanucleusinthe cellsofthecirculatingprimitiveerythroncandecreasetheefficiency ofgasexchangeinthelungsandmicrovasculaturebecausethenucleus

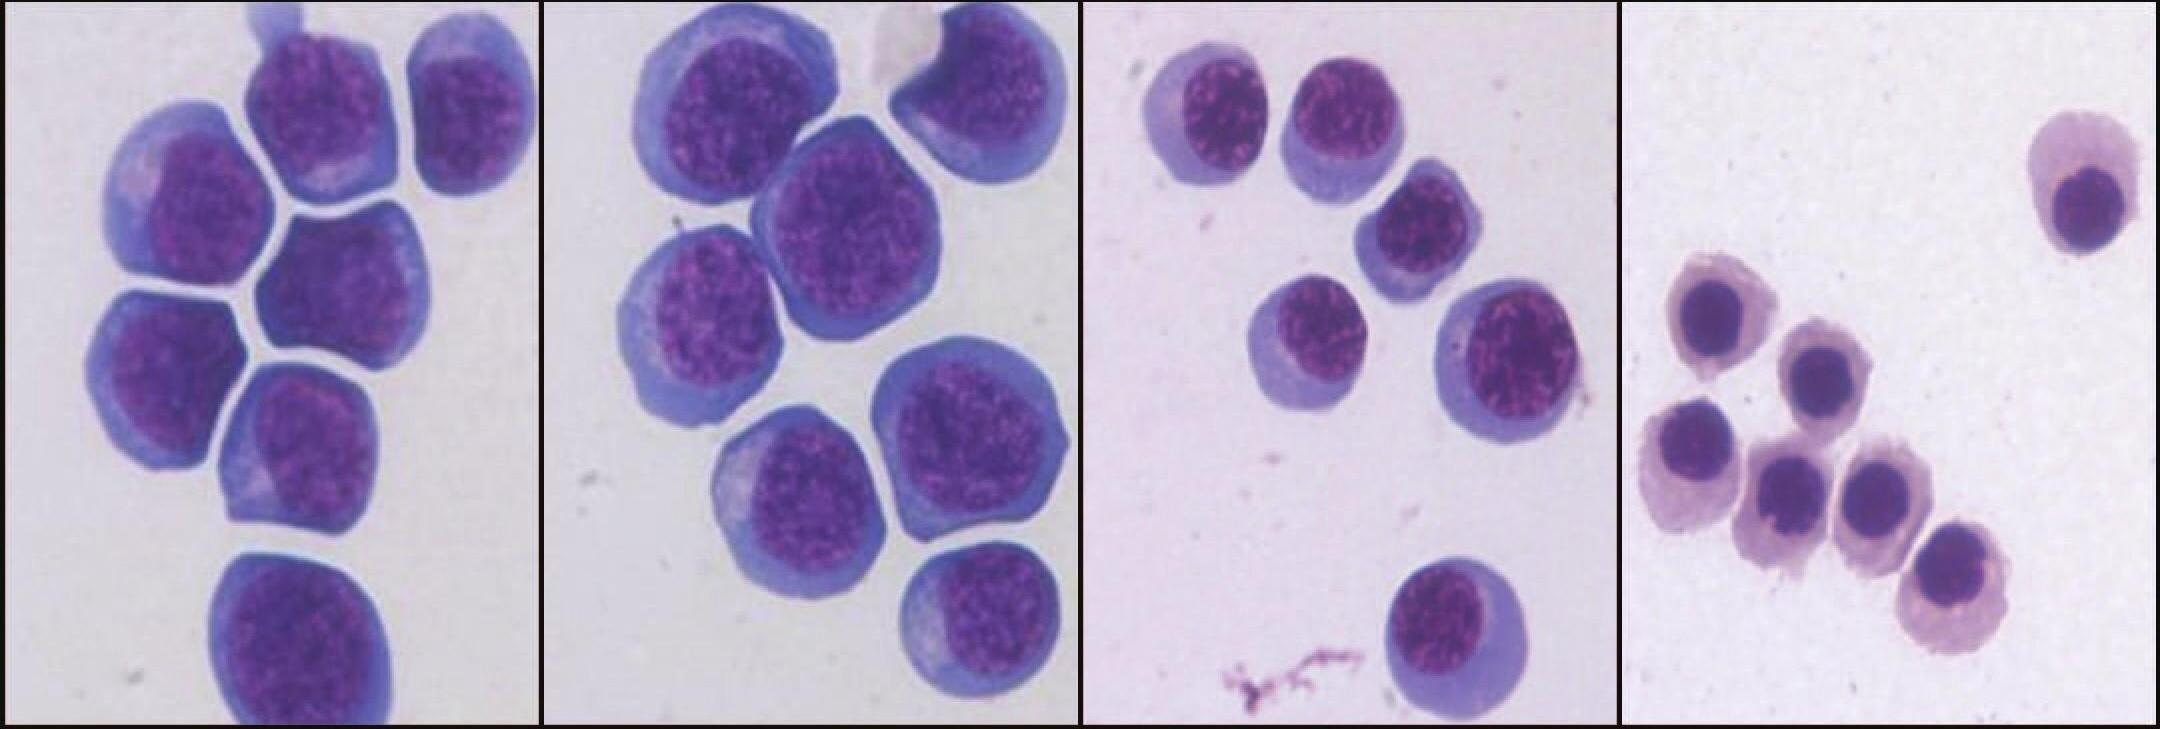
Figure1–3.Humanerythroblastprecursorsasisolatedbycellflowcytometry.Imagesareofpopulationsofhumanerythroblastprecursorsat stagesoferythroidmaturationwhensortedfromhumanmarrowbyflowcytometry.AandB.Proerythroblastsandearlybasophilicerythroblasts;(C)polychromaticerythroblasts;and(D)orthochromaticerythroblasts.
ProerythroblastsOnstainedfims,theproerythrobastappears asaargece,irreguaryroundedorsightyova.13Thenuceusoccupiesapproximatey80%oftheceareaandcontainsfinechromatindeicateydistributedinsmacumps.Oneorseverawe-definednuceoi arepresent.Thehighconcentrationofpoyribosomesgivesthecytopasmofthesecesitscharacteristicintensebasophiia.Atveryhigh magnification,ferritinmoecuesareseendispersedsingythroughout thecytopasmandiningthecathrin-coatedpitsonthecemembrane (Figs.1-2and1-4).Diffusecytopasmicdensityonsectionsstainedfor peroxidaseindicatesthathemogobinisareadypresent.Dispersedgycogenparticesarepresentinthecytopasm.
BasophilicErythroblastsBasophiicerythrobastsaresmaer thanproerythrobasts.Thenuceusoccupiesthree-fourthsofthece areaandiscomposedofcharacteristicdarkvioetheterochromatininterspersedwithpink-stainingcumpsofeuchromatininkedby irreguarstrands.13Thewhoearrangementoftenresembeswhee spokesoracockface.Thecytopasmstainsdeepbue,eavingaperinucearhaothatexpandsintoajuxtanucearcearzonearoundthe Gogiapparatus.Cytopasmicbasophiiaatthisstageresutsfromthe continuedpresenceofpoyribosomes(Figs.1-2and1-5).
PolychromatophilicErythroblastsAfterthemitoticdivision ofthebasophiicerythrobast,thecytopasmchangesfromdeepbue tograyashemogobindiutesthepoyribosomecontent.Cesatthis stagearesmaerthanbasophiicerythrobasts.Thenuceusoccupies essthanhafofthecearea.Theheterochromatinisocatedin we-definedcumpsspacedreguaryaboutthenuceus,producing acheckerboardpattern.Thenuceousisost,buttheperinucear haopersists.13Itisatthispointthaterythrobastsosetheirmitotic potentia.Eectronmicroscopyofthepoychromatophiicerythrobastreveasincreasedaggregationofnucearheterochromatin.13Active ferritintransportacrossthecemembraneisawaysevident,and siderosomesaongwithdispersedferritinmoecuescanbeidentified withinthecytopasm(Figs.1-2and1-6).
Orthochromic(syn.Orthochromatic)ErythroblastsAfterthe finamitoticdivisionoftheerythropoieticseries,theconcentrationof hemogobinincreaseswithintheerythrobast.Undertheightmicroscope,thenuceusappearsamostcompeteydenseandfeatureess. Itismeasurabydecreasedinsize.Thisceisthesmaestoftheerythrobasticseries.13Thenuceusoccupiesapproximateyone-fourthof theceareaandiseccentric.Cemovementcanbeappreciatedunder thephase-contrastmicroscope.Roundprojectionsappearsuddenyin
differentpartsoftheceperipheryandarejustasquickyretracted.13 Themovementsprobabyaremadeinpreparationforejectionofthe nuceus.Theceutrastructureischaracterizedbyirreguarborders, refectingitsmotiestate.Theheterochromatinformsargemasses. Mitochondriaarereducedinnumberandsize(seeFigs.1-2,1-7,and1-8).
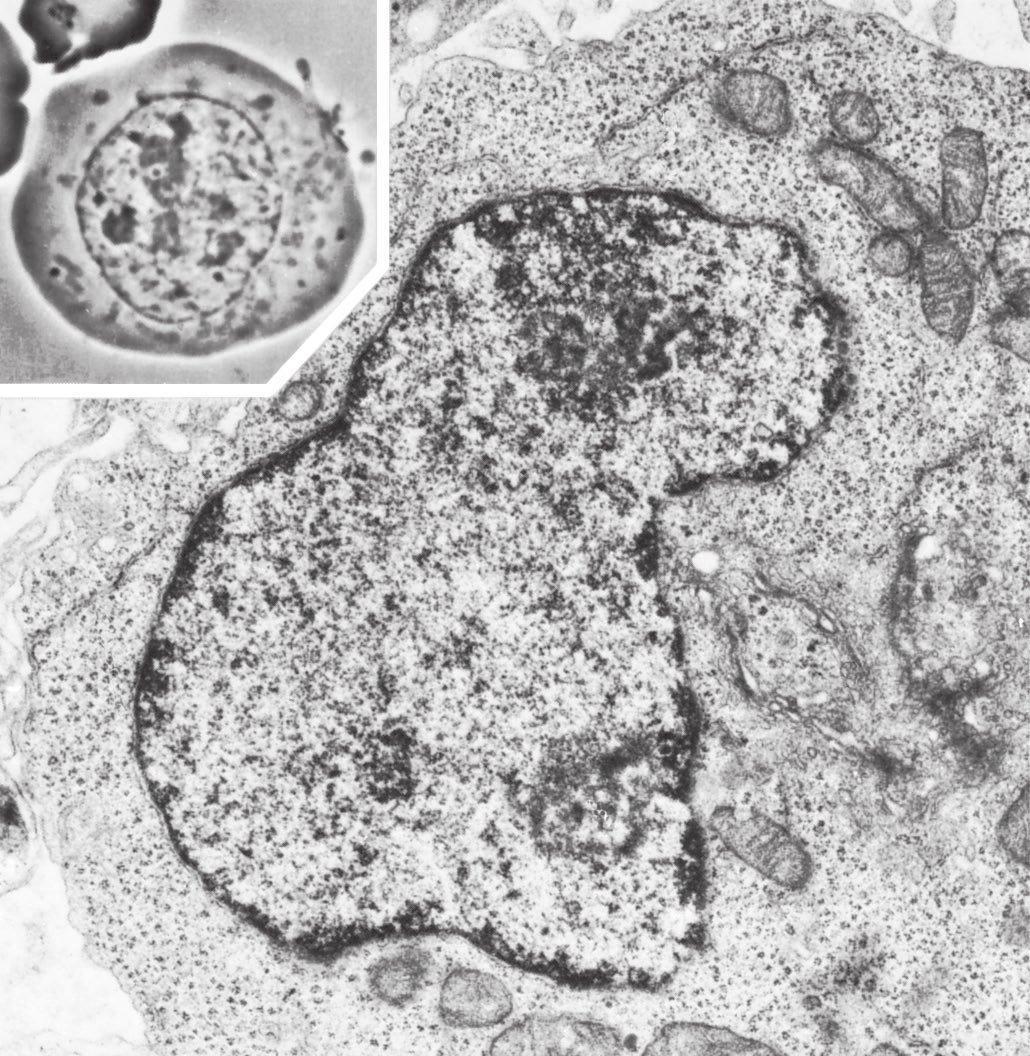
Figure1–4.Proerythroblast.Phase-contrastmicrograph(inset)ofa proerythroblastshowingtheimmaturenucleuswithnucleoliandfinely dispersednuclearchromatin.Thecentrosome(juxtanuclearclearzone) isapparentwithitsdenseaccumulationofmitochondria.Electronmicroscopicsectionoftheproerythroblastshowsnucleoli(n)incontactwith thenuclearmembrane.Chromatinisfinelydispersedandformssmall aggregatesinthefixednuclearmembrane.Theperinuclearcanalisnarrowbutwelldefined.Polyribosomegroups,manyinhelicalconfiguration, aredispersedthroughoutthecytoplasm.TheGolgiapparatus(g)iswell developed,andregionsofendoplasmicreticulum(arrows)areseen.
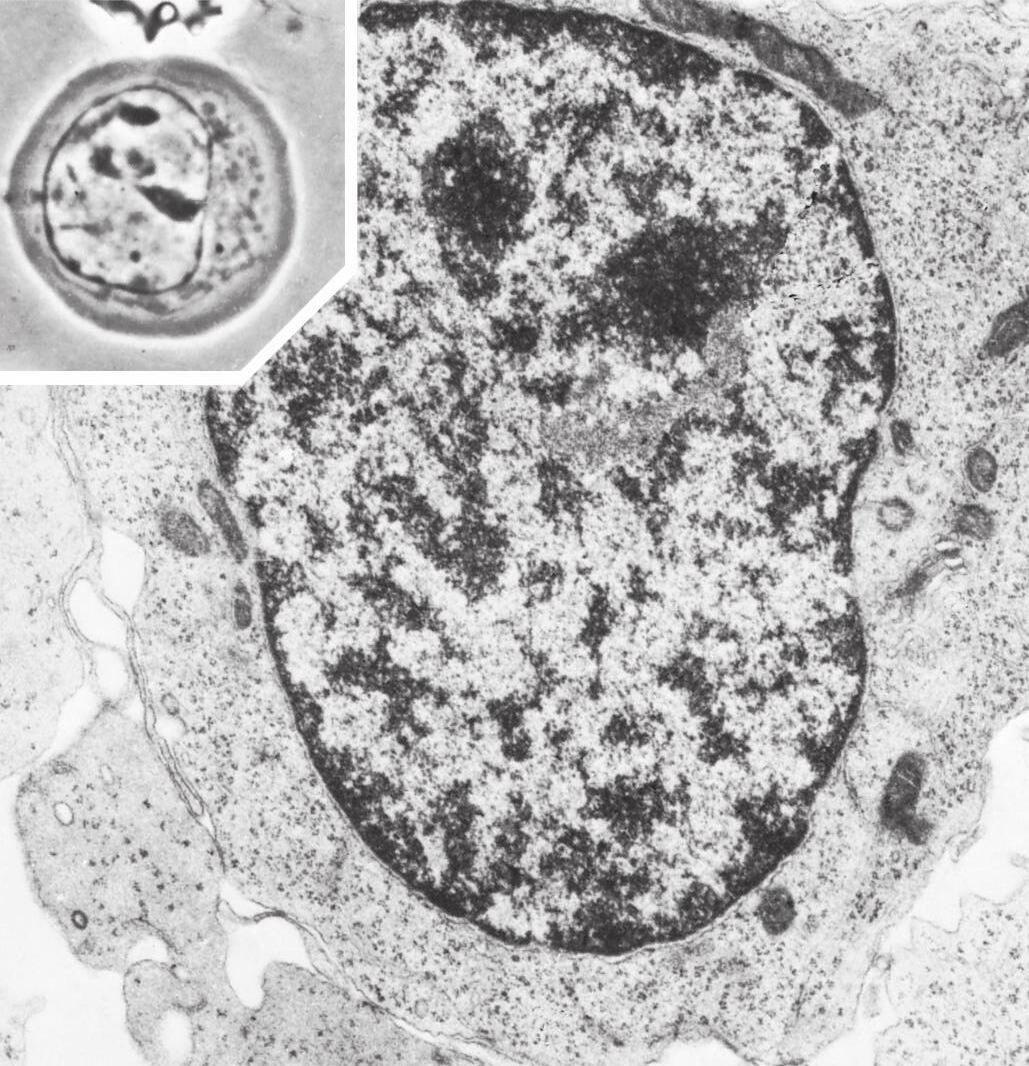
Figure1–5.Basophilicerythroblast.Phase-contrastphotomicrograph (inset)showsincreasedclumpingofthenuclearchromatinandfurther roundingofthecell,withaggregationofthemitochondriaandcentrosomeintotheregionsofnuclearindentation.Theelectronmicroscopicsectionshowsclumpingofthenuclearchromatin,nuclearpores (p),organizationofthenucleoli,increaseddensityofpolyribosomes(pr), well-developedGolgiapparatus(g),andadecreaseinsmoothendoplasmicreticulum.
NormalSideroblastsAnormaerythrobastsaresiderobasts inthattheycontainironinstructurescaedsiderosomes,asevidentby transmissioneectronmicroscopy.Thesestructuresareessentiaforthe transferofironforheme(hemogobin)synthesis.Byightmicroscopy, undertheusuaconditionsofPrussianbuestainingforiron,aminority ofnormaerythrobasts(approximatey15%-20%)canbeidentifiedas containingsiderosomes,andthosethatcanbesoidentifiedhavevery few(1-4)smaPrussianbue–positivegranues.
PathologicSideroblastsAheterogeneousgroupoferythrocytedisordersisaccompaniedbyineffectiveerythropoiesis,abnorma erythrobastmorphoogy,andhyperferremia.Thesedisordersincude acquiredmegaobasticanemia(Chap.9),congenitadyserythropoietic anemias(Chap.14),thaassemias(Chap.17),theinheritedandacquired siderobasticanemias,pyridoxine-responsiveanemia,acoho-induced siderobasticanemia,andeadintoxication(Chaps.20and23).Some oftheseconditionsarecharacterizedbythepresenceofpathoogic siderobasts.Pathoogicsiderobastsareoftwotypes.Thefirstisan erythrobastthathasanincreaseinnumberandsizeofPrussianbue–stainedsideroticgranuesthroughoutthecytopasm.Thesecondisthe erythrobastthatshowsiron-containinggranuesthatarearrangedin anarcoracompeteringaroundthenuceus(Fig.1-8).Thesepathoogicsiderobastsarereferredtoasringorringedsideroblasts. 26,27Eectronmicroscopicstudiesshowthatgranuesinringedsiderobastsare iron-oadedmitochondria.Inceswithiron-oadedmitochondria, manyferritinmoecuesaredepositedbetweenadjacenterythrobast membranes.

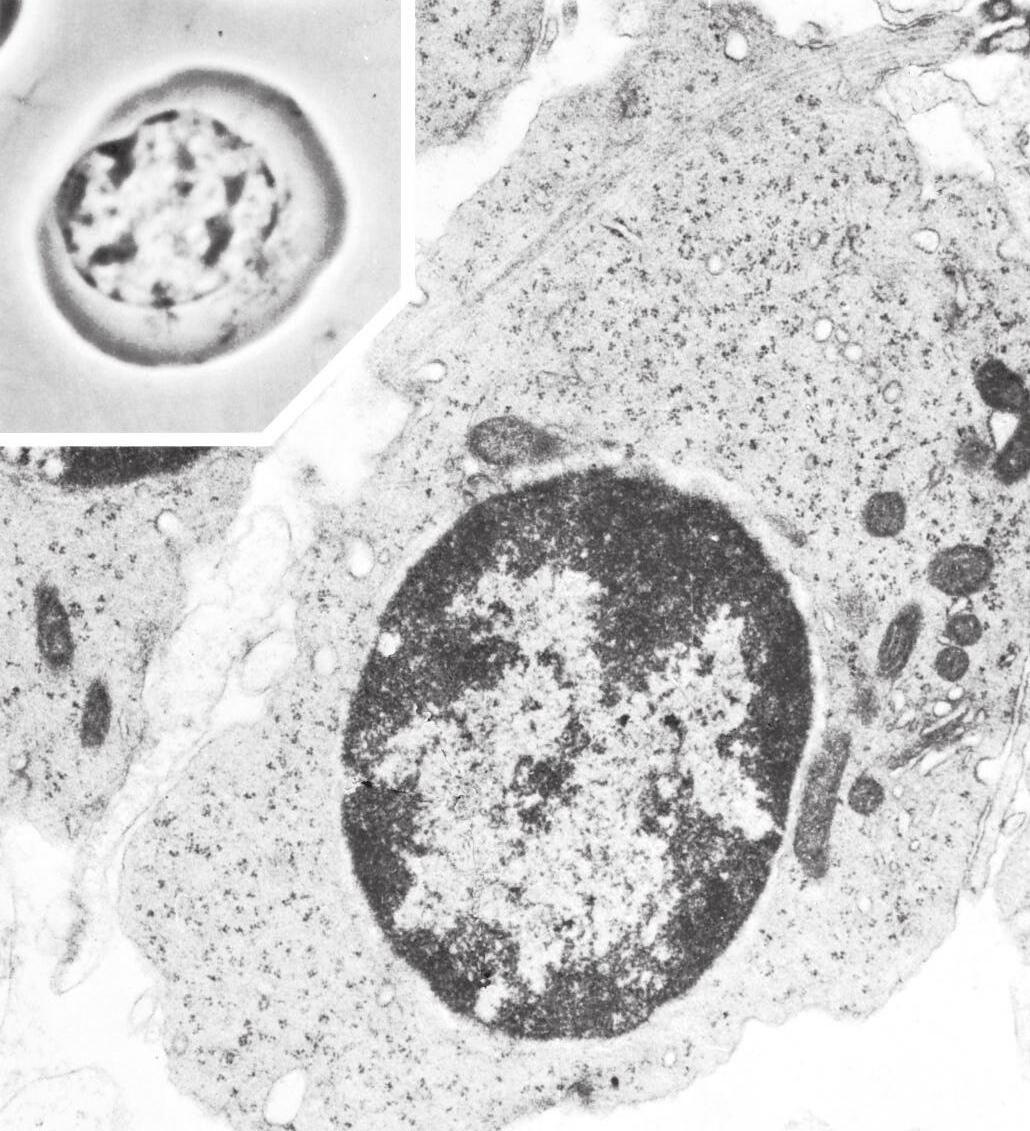
Figure1–6.Polychromatophilicerythroblast.Phase-contrastmicrograph(inset)demonstratesdiminishedsizeofthiscellcomparedwith itsprecursor.Furtherclumpingofnuclearchromatingivesthenucleus acheckerboardappearance.Thecentrosomeiscondensed,andaperinuclearhalohasdeveloped.Theelectronmicroscopicsectiondemonstratesrelativereductionofthedensityofpolyribosomesanddilution bythemoderatelyosmiophilichemoglobininthecytoplasm.Nuclear chromatinshowsamarkedincreaseinclumping,andnuclearpores(P) areenlarged.
RETICULOCYTE
Birth
Beforeenuceationattheateorthochromaticerythrobastsstage,intermediatefiamentsandthemarginabandofmicrotubuesdisappear. Enuceationisahighydynamicprocessthatinvovescoordinatedaction ofmutipemechanisms.28-30Tubuinandactinbecomeconcentratedat thepointwherethenuceuswiexit.Thesechanges,accompaniedby microtubuarrearrangementsandactinpoymerization,payaroein nucearexpusion.Expusionofthenuceusinvitroisnotaninstantaneousphenomenon;itrequiresaperiodof6to8minutes.Theprocess beginswithseveravigorouscontractionsaroundthemidportionofthe ce,foowedbyadivisionoftheceintounequaportions.Thesmaer portionconsistsoftheexpeednuceussurroundedbyathinringof hemogobinandpasmamembrane(Fig.1-9).Invivo,expusionofthe nuceusmayoccurwhietheerythrobastisstipartofanerythrobasticisandandtheoutereafetofthebiaminarmembranesurrounding theexpeednuceusishighinphosphatidyserine,asignaformacrophageingestion(Fig.1-10).22Twohypotheseshavebeenproposedto expainhowthereticuocyteexitsthemarrow.19-21Thereticuocytemay activeytraversethesinusepitheiumtoentertheumen.Moreikey, however,thereticuocytemaybedrivenacrossbyapressuredifferentiabecauseitappearsincapabeofdirectedamoeboidmotion.Invitro experimentaevidencefavorsthehypothesisthatpressuredifferentiais ikeythedriverforreticuocytereease.21
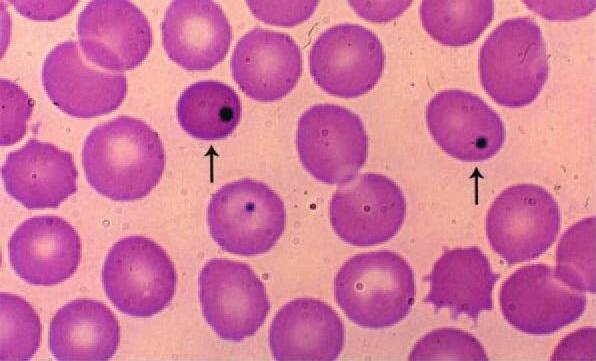
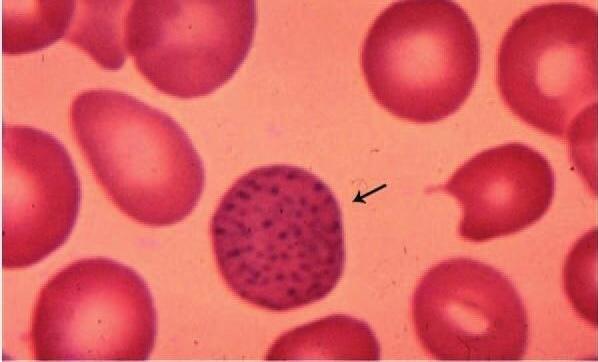
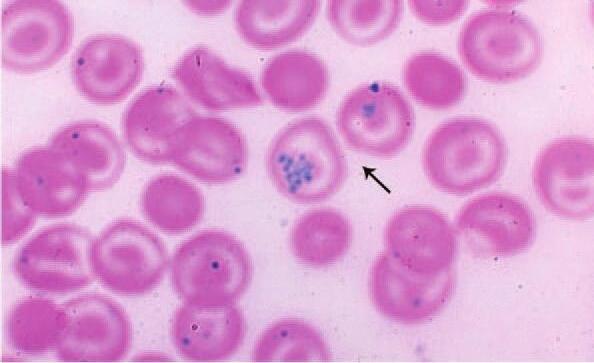
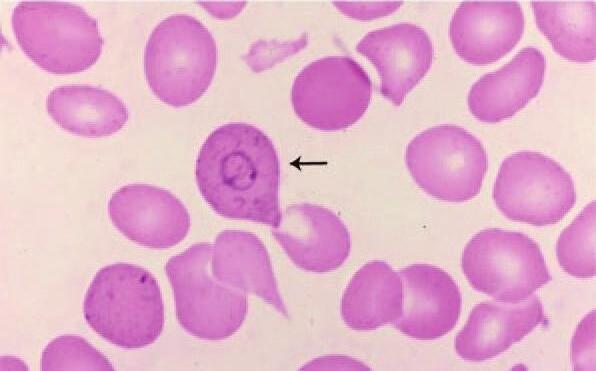
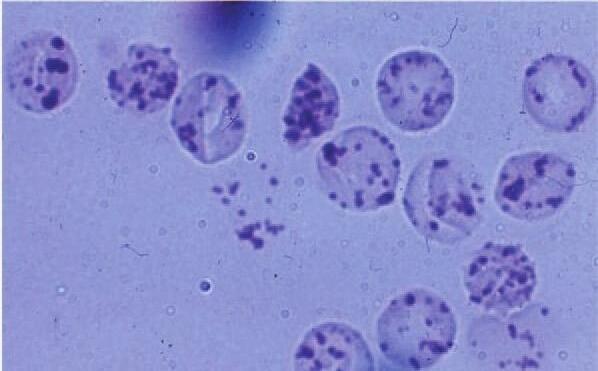
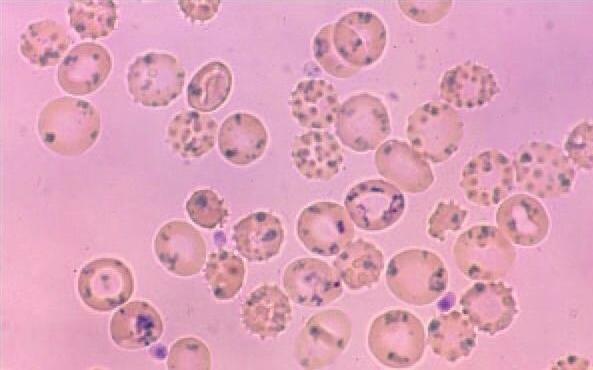
Figure1–11.Redcellinclusions.Bloodfilms.A.RedcellswithHowell-Jollybodies(arrows)postsplenectomy.Thecrispcircularborder,darkblue color,andperipherallocationarecharacteristics.B.Basophilicstippling.Thesebasophilicinclusionsmaybefineorcoarse.Inthiscase,thecellcontains coarsestipplingseeninleadpoisoning(arrow)C.Siderocyte.ThesecellscontainpurplegranuleswhenstainedwithWrightstain(Pappenheimer bodies).Comparedwithbasophilicstippling,sideroticgranulesareusuallyfewerinnumberandsometimesclustered.ThesePrussianblue–stained cellsconfirmthatthegranulescontainiron(bluereactionproduct).Thearrowpointstotwosiderocytes.D.Cabotring.Rareredcellinclusion(arrow) Seetextforfurtherdescription.E.Heinzbodies.Thesecellsfromapatientwithglucose-6-phosphatedehydrogenasedeficiencywereincubatedwith asupravitaldye,whichstainsthedenaturedglobinprecipitates.F.RedcellsfromapatientwithhemoglobinHdisease(α-thalassemia).Thehemoglobinprecipitatesarestainedwithbrilliantcresylblue.(ReproducedwithpermissionfromLichtmanMA,ShaferMS,FelgarRE,etal:Lichtman’sAtlasof Hematology2016.NewYork,NY:McGrawHill;2017.)
BasophilicStippling
BasophiicstippingconsistsofgranuationsofvariabesizeandnumberthatstaindeepbuewithWrightstain.Eectronmicroscopicstudies haveshownthatpunctatebasophiliarepresentsaggregatedribosomes.42 Cumpsformduringthecourseofdryingandpostvitastainingof theces,muchas“reticuum”inreticuocytesprecipitatesfromribosomesduringsupravitastaining.Thecumpedribosomesmayincude degeneratingmitochondriaandsiderosomes.Inconditionssuchasead intoxication(Chap.23),pyrimidine5’-nuceotidasedeficiency(Chap.16), andthaassemia(Chap.17),theateredreticuocyteribosomeshave agreaterpropensitytoaggregate.Asaresut,basophiicgranuation appearsargerandisreferredtoascoarsebasophilicstippling
HeinzBodies
Heinzbodiesarecomposedofdenaturedproteins,primariyhemogobin,thatforminredcesasaresutofchemicainsut;inhereditary defectsofthehexosemonophosphateshunt(Chap.16);inthethaassemias(Chap.17);andinunstabehemogobinsyndromes(Chap.18).43
HeinzbodiesarenotseenonordinaryWright-orGiemsa-stainedbood fims.Heinzbodiesarereadiyvisibeinredcesstainedsupravitay withbriiantcresybueorcrystavioetandareeiminatedasredces traversetheendotheiasitsofthespenicsinus.
HemoglobinHInclusions
HemogobinHiscomposedofβ4tetramers,indicatingthatβchainsare presentinexcessasaresutofimpairedα-chainproduction(Chap.17). Exposuretoredoxdyessuchasbriiantcresybue,methyenebue,or newmethyenebue,resutsindenaturationandprecipitationofabnormahemogobin.44-46Briiantcresybuecausestheformationofaarge numberofsmamembrane-boundincusions,givingtheceacharacteristic“gofba-ike”appearancewhenviewedbyightmicroscopy.
Methyenebueandnewmethyenebuegenerateasmaernumberof variabysizedmembrane-boundandfoatingincusions.Thesechanges areseenmostfrequentyinα-thaassemiabutcanasobefoundin patientswithunstabehemogobin(Chap.18)andinrarepatientswith primarymyeofibrosisinwhomacquiredhemogobinHdiseasehas deveoped.
SiderosomesandPappenheimerBodies
Normaorpathoogicredcesinboodcontainingsiderosomes(“iron bodies”)usuayarereticuocytes.Theirongranuationsareargerand morenumerousinthepathoogicstate.Eectronmicroscopyshowsthat manyofthesebodiesaremitochondria-containingferruginousmicees ratherthantheferritinaggregatescharacterizingnormasiderocytes.47 Siderosomesusuayarefoundintheceperiphery,whereasbasophiic stippingtendstobedistributedhomogeneousythroughoutthece. PappenheimerbodiesaresiderosomesthatstainwithWrightstain. EectronmicroscopyofPappenheimerbodiesshowsthattheironoften iscontainedwithinaysosome,asconfirmedbythepresenceofacid phosphatase.Siderosomesmaycontaindegeneratingmitochondria, ribosomes,andotherceuarremnants.
STRUCTUREANDSHAPEOFERYTHROCYTES
Thenormarestingshapeoftheerythrocyteisabiconcavedisc(Fig.1-12). Variationsintheshapeanddimensionsoftheredceareusefuin thedifferentiadiagnosisofanemias.Normahumanredceshave adiameterof7to8μm,andthediameterdecreasessightywithce age.Thedecreaseinsizeikeyresutsfromossofmembranesurface areaduringtheerythrocyteifespanbyspeen-faciitatedvesicuation. Theceshaveanaveragevoumeofapproximatey90fLandasurface areaofapproximatey140μm2.Themembraneispresentinsufficient excesstoaowthecetoswetoasphereofapproximatey150fLorto
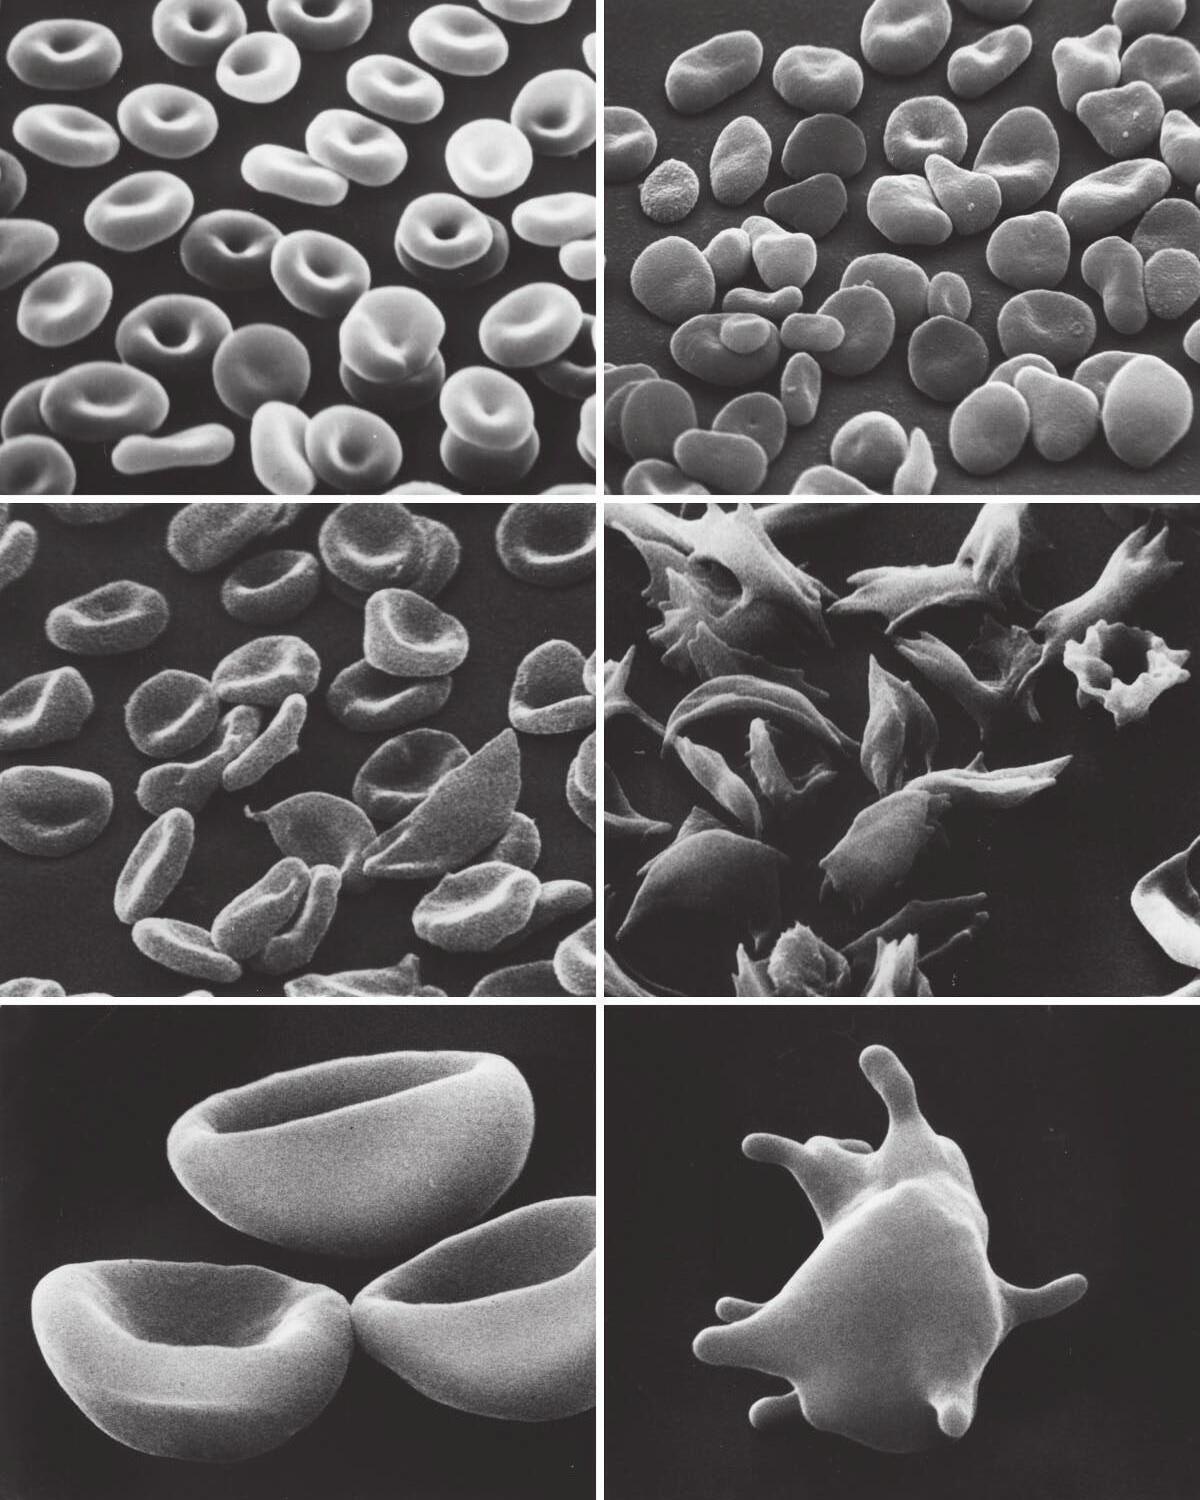
Figure1–12.Scanningelectronmicrographsofdistinctredcellmorphologies.Discoidnormalredcells(topleftpanel).Elliptocytesandfragmentedredcells(toprightpanel).Oxygenatedsickleredcells(middleleft panel)anddeoxygenatedsickleredcells(middlerightpanel).Stomatocyticredcells(bottomleftpanel).Acanthocyte(bottomrightpanel)
deformsoastoenteracapiarywithadiameterof2.8μm.Thenorma erythrocytestainsreddish-brownwithWright-stainedboodfimsand pinkwithGiemsastain.Thecentrathirdoftheceappearsreativey paecomparedwiththeperiphery,refectingitsbiconcaveshape.Many artifactscanbeproducedinthepreparationoftheboodfim.Theymay resutfromcontaminationofthegasssideorcoversipwithtracesof fat,detergent,orotherimpurities.Frictionandsurfacetensioninvoved inthepreparationoftheboodfimproducefragmentation,“doughnutces”oranuocytes,andcrescent-shapedces.Observedunderthe phase-contrastorinterferencemicroscope,theredceshowsacharacteristicinternascintiationknownasredceficker.48Thescintiation resutsfromthermayexcitedunduationsoftheredcemembrane. Frequencyanaysisofthesurfaceunduationshasprovidedanestimateofthemembranecurvatureeasticconstantandofchangesinthis constantresutingfromacoho,choesterooading,andexposureto cross-inkingagents.
REDCELLSHAPEANDSURVIVAL INCIRCULATION
Theredcespendsmostofitscircuatoryifewithinthecapiarychannesofthemicrocircuation.Duringits100-to120-dayifespan,the redcetravesapproximatey250kmandosesapproximatey15%to 20%ofitscesurfacearea.Theongsurvivaoftheredceisateast partiayaresutoftheuniquecapacityofitsmembraneto“tanktread,”
thatis,torotatearoundtheredcecontentsandtherebyfaciitatemore efficientoxygendeivery.Thephysicaarrangementofmembraneskeetaproteinsinauniformsheofhighyfodedhexagonaspectrinattice permitsthisunusuabehavior.49-51Thearrangementasoisresponsibe forthecharacteristicbiconcaveshapeoftherestingce.Redcesmust asobeabetowithstandargeshearforcesandmustbeabetoundergo extensivereversibedeformationduringtransitthroughthemicrovascuatureandintransitingfromthespenicredcepupbackintocircuation.Theresiiencyandfuidityofthemembranetodeformation isreguatedbythespectrin-basedmembraneskeeton.49Adeficiency intheamountofspectrinorthepresenceofmutantspectrininthe submembraneskeetonresutsinabnormayshapedcesinhereditaryspherocytosis,eiptocytosis,andpyropoikiocytosis(Chap.15).49 Inregionsofcircuatorystandstiorverysowfow,redcestrave inaggregatesof2to12ces,formingroueaux.Withinargevesses, increasedshearforcesdisruptthisaggregation.
REDCELLCOMPOSITION
Theerythrocyteisacompexce.Themembraneiscomposedofipids andproteins,andtheinteriorofthececontainsmetaboicmachinery designedtosustainthecethroughits120-dayifespanandmaintain theintegrityofhemogobinfunction.Eachcomponentofredbood cesmaybeexpressedasafunctionofredcevoume,gramsofhemogobin,orsquarecentimetersofcesurface.Theseexpressionsareusuayinterchangeabe,butundercertaincircumstanceseachmayhave specificadvantages.However,becausediseasemayproducechangesin theaverageredcesize,hemogobincontent,orsurfacearea,theuseof anyofthesemeasurementsindividuaymay,attimes,bemiseading. Forconvenienceanduniformity,dataintheaccompanyingtabes (Tabes1-1through1-6)52-125areexpressedintermsofceconstituent permiiiterofredceandpergramofhemogobin.Inmanyinstances, thisprocessrequiredrecacuationofpubisheddata.Theserecacuationsassumeahematocritvaueof45%and33gofhemogobinper deciiterofredces.Toobtainconcentrationpergramofhemogobin, theconcentrationpermiiiterredboodcecanbemutipiedby3.03. Thetabesistonysomeofthemostcommonyreferredtoconstituents oftheerythrocyte.Thereferenceonwhicheachvaueisbasedisthe firstnumberpresentedintheastcoumnofeachtabe.Whereappicabe,additionaconfirmatoryreferencesaregiven.Insomeinstances, onythepercentageofthetotaofthetypeofconstituentpresentis given.Chapter15discussesthedetaiedproteincompositionofthered cemembraneanditsvariousproteinconstituents.
TABLE1–1.HumanErythrocyteProteinand WaterContent
TABLE1–2.HumanErythrocytePhospholipids
Lipid Amount
Totalphospholipids2.98±0.20mg/mLRBC56
Ethanolamine phosphoglyceride 29%oftotal phospholipid
Meanplasmalogen content 67%ofethanolamine phosphoglyceride
Serinephosphoglyceride10%oftotal phospholipid 56
Meanplasmalogen content 8%ofserine phosphoglyceride 56
Lecithin 0.320.03–0.95mg/mL57
Sphingomyelin 0.12–1.13mg/mL57
Lysolecithin 1.82%oftotal phospholipids 58
Abbreviation:RBC,redbloodcell.
Someresultsaregivenasmean±standarddeviation.
ERYTHROCYTEDEFORMABILITY
Duringits120-dayifespan,theerythrocytemustundergoextensive passivedeformationandmustbemechanicaystabetoresistfragmentation;ceuardeformabiityisanimportantdeterminantofred cesurvivainthecircuation.Redcedeformabiityisinfuenced bythreedistinctceuarcomponents:(1)ceshapeorcegeometry, whichdeterminestheratioofcesurfaceareatocevoume(SA:V; highervauesofSA:Vfaciitatedeformation);(2)cytopasmicviscosity,whichisprimariyreguatedbythemeancorpuscuarhemogobin concentration(MCHC)andisthereforeinfuencedbyaterationsin
TABLE1–3.HumanErythrocyteCoenzymeandVitamins
Ascorbicacid
Abbreviation:RBC,redbloodcell. Someresultsaregivenasmean±standarddeviation.
TABLE1–4.Nucleotides
Compound
Adenosinemonophosphate0.021±0.00369-72
Adenosinediphosphate0.216±0.03669-72
Adenosinetriphosphate1.35±0.03571-75
Cyclicadenosine monophosphate 0.015±0.002476
Cyclicguanosine monophosphate 0.013±0.004276
Guanosinediphosphate0.018±0.00571
Guanosinetriphosphate0.052±0.01270,71
Inosinemonophosphate0.031±0.00571-73
Nicotinamideadenine dinucleotide 77,78
Reduced 0.0018±0.00177,78
Oxidized 0.049±0.006
Nicotinamideadeninedinucleotidephosphate 77,78
Reduced 0.032±0.002
Oxidized 0.0014±0.0011
S-adenosylmethionine0.005 79
Totalnucleotide 1.534±0.03380
Uridinediphosphoglucose0.031±0.00571,81
UridinediphosphateN-acetyl glucosamine 0.018 81
Abbreviation:RBC,redbloodcell. Someresultsaregivenasmean±standarddeviation.
cevoume;and(3)membranedeformabiityandmechanicastabiity, whicharereguatedbymutipemembraneproperties,whichincude easticshearmoduus,bendingmoduus,andyiedstress.126-129Either directyorindirecty,membranecomponentsandtheirorganization payanimportantroeinreguatingeachofthefactorsthatinfuence ceuardeformabiity.
ThebiconcavediscshapeofthenormaredcecreatesanadvantageousSA:Vreationship,aowingtheredcetoundergomarkeddeformationwhiemaintainingaconstantsurfacearea.Thenormahuman adutredcehasavoumeof90fLandasurfaceareaof140μm2.If theredcewereasphereofidenticavoume,itwoudhaveasurface areaofony98μm2.Thus,thediscoidshapeprovidesapproximatey 40μm2ofexcesssurfacearea,oranextra43%,whichenabesthered cetoundergoextensivedeformation.Mostdeformationsoccurringin vivoandinvitroinvovenoincreaseinsurfacearea.Thisisimportant becausethenormaredcecanundergoargeinearextensionsofupto 230%ofitsoriginadimensionwhiemaintainingitssurfacearea,but anincreaseofeven3%to4%insurfacearearesutsinceysis.Either membraneoss,eadingtoareductioninsurfacearea,oranincrease incewatercontent,eadingtoanincreaseincevoume,wicreatea moresphericashapewithessredundantsurfacearea.Thisossofsurfacearearedundancyresutsinreducedceuardeformabiity,compromisedredcefunction,anddiminishedsurvivaasaresutofspenic sequestrationofspherocyticredces.A17%reductioninsurfacearea resutsinrapidremovaofredcesbythehumanspeen.130
TABLE1–5.
HumanErythrocyteCarbohydrates,Organic Acids,andMetabolites
Compound μmol/mLRBCReference(s)
Dihydroxyacetonephosphate0.0094±0.002869
2,3-Diphosphoglycerate4.171±0.63669,75
Fructose 0.000354± 0.0000191 82
Fructose6-phosphate0.0093±0.00269,72,75,83
Fructose3-phosphate0.013±0.00184,85
Fructose2,6-diphosphatea 48±1386
Fructose1,6-diphosphate0.0019±0.000669,72,75,83
Glucuronicacid Trace 87
Glucose Inequilibrium withplasma 88,89
Glucose6-phosphate0.0278±0.007569,72,75,83
Glucose1,6-diphosphate0.18–0.3072,90
Glyceraldehyde3-phosphateNotdetectable69
Lacticacid
0.932±0.21153,69,91
Mannose1,6-diphosphate0.150 90
Octulose1,8-diphosphateTrace 92
Pyruvate 0.0533±0.021569
3-Phosphoglycerate 0.0449±0.005169,75
2-Phosphoglycerate 0.0073±0.002569,75
Phosphoenolpyruvate0.0122±0.002269
Ribonucleicacid 1.355mg93
Ribose1,5-diphosphate<0.02 94,95
Ribulose5-phosphateTrace 96
Sedoheptulose7-phosphateTrace 96
SedoheptulosediphosphateTrace 97
Sialicacid 0.825±0.02894
Sorbitol 31.1±5.382,84
Sorbitol3-phosphate0.013±0.00185
Abbreviation:RBC,redbloodcell. aValuesaregiveninpicomoles. Someresultsaregivenasmean±standarddeviation.
Cytopasmicviscosity,anotherreguatorycomponentofredce deformabiity,isargeydeterminedbytheMCHC,whichisdetermined inargepartbycewatercontent.Asthehemogobinconcentration risesfrom27to35g/dL(thenormarangeforredboodces),theviscosityofhemogobinsoutionincreasesfrom5to15centipoise(cP), 5to15timesthatofwater.Attheseeves,thecontributionofcytopasmicviscositytoceuardeformabiityisnegigibe.However,viscosity increasesexponentiayathemogobinconcentrationshigherthan37g/dL, reaching45cPat40g/dL,170cPat45g/dL,and650cPat50g/dL.At theseeves,cytopasmicviscositymaybecometheprimarydeterminantofceuardeformabiity.Thus,ceuardehydration,usuaycaused bythefaiureofnormavoumehomeostasismechanisms,canseverey impairceuardeformabiityandthusdecreaseoptimaoxygendeiverybyimpairingtheabiityofredcestoundergorapiddeformation
TABLE1–6.HumanErythrocyteElectrolytes
Electrolyteμmol/mLRBCReference
protein-bound
98,114
Abbreviation:RBC,redbloodcell.
aObtainedbysubtractingplasmaconcentrationfromwhole-blood concentration.
Someresultsaregivenasmean±standarddeviation.
necessaryforpassagethroughthemicrovascuature.Asexampes,ceuardehydrationreducesredcedeformabiityinhereditaryxerocytosis, sickeceanemia,hemogobinCC,andβ-thaassemia.129,131,132However, changesinceuardehydrationbyitsefappeartohaveitteinfuence onredcesurviva.
Thepropertyofmembranedeformabiitydeterminestheextentof membranedeformationthatcanbeinducedbyadefinedeveofappied force.Themoredeformabethemembrane,theesstheforcerequired forthecetopassthroughthecapiariesandothernarrowopenings, suchasfenestrationsinthespeniccords.Thepropertyofmembrane mechanicastabiityisdefinedasthemaximumextentofdeformation thatamembranecanundergo,beyondwhichitcannotcompetey recoveritsinitiashape.Thisisthepointatwhichthemembranefais. Normamembranestabiityaowshumanredcestocircuatefor100 to120dayswithoutfragmenting,whereasdecreasedstabiityeadsto cefragmentationundernormacircuatorystresses.Bothmembrane
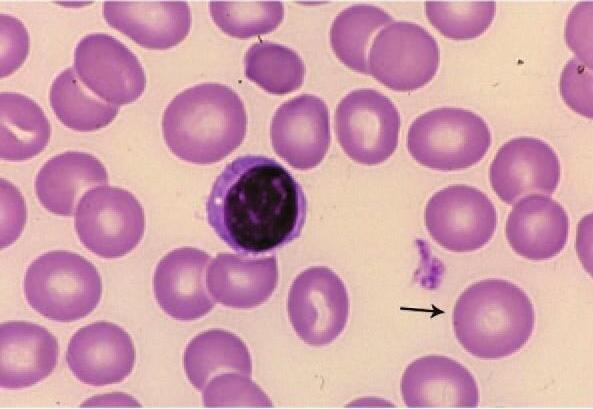
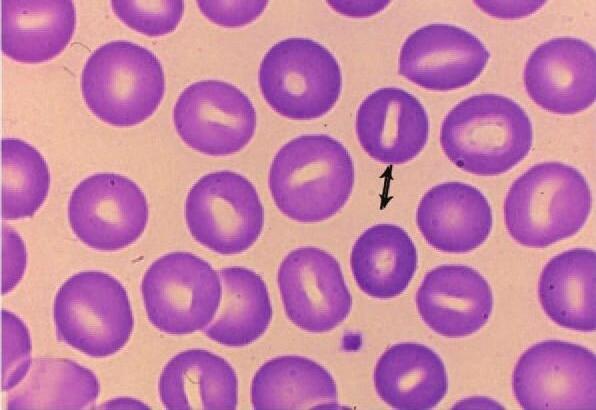
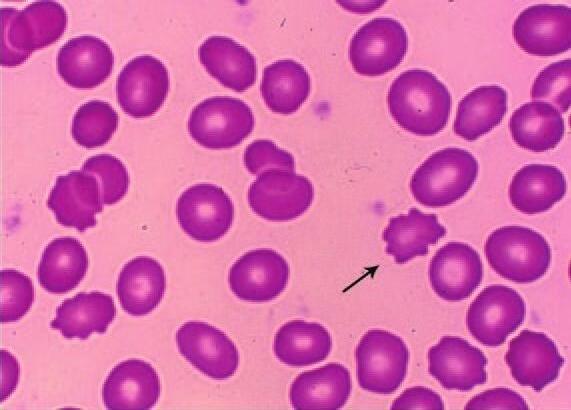
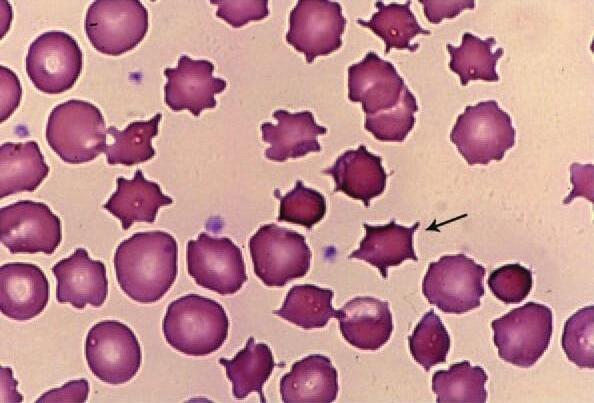
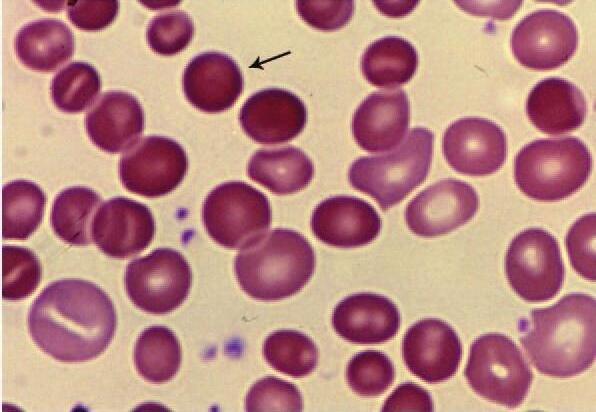
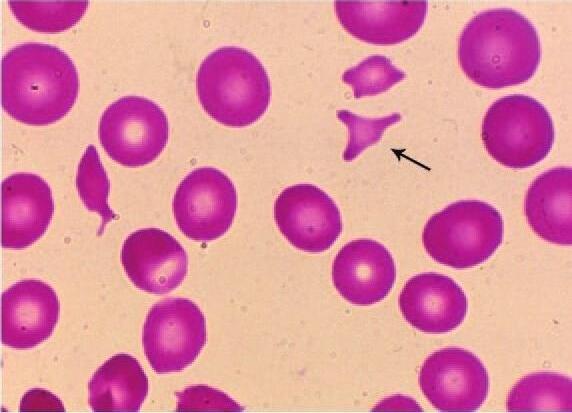
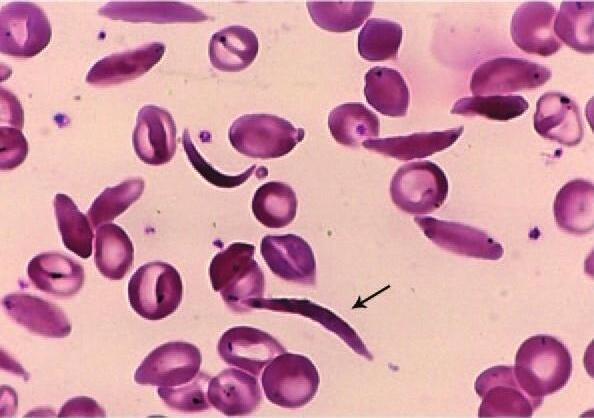
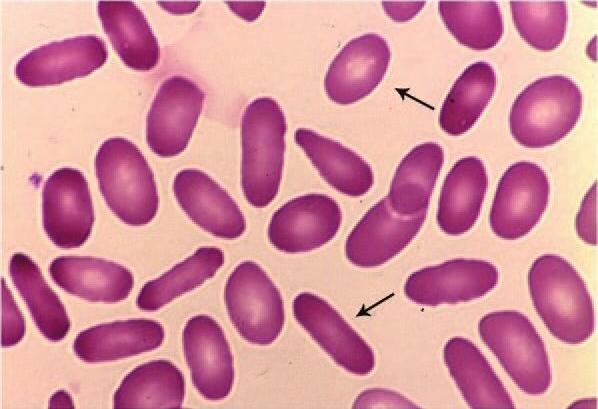
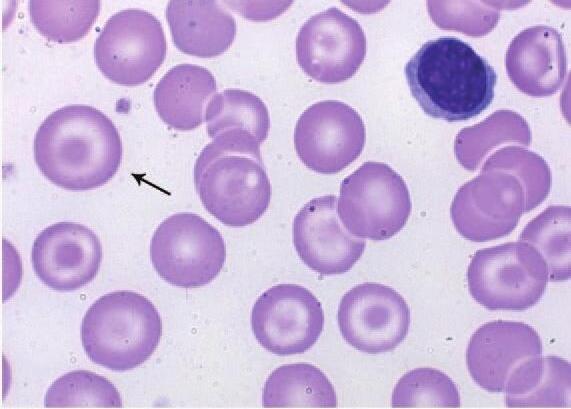
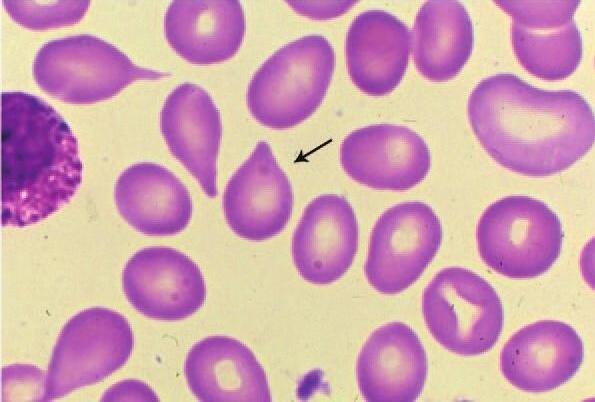
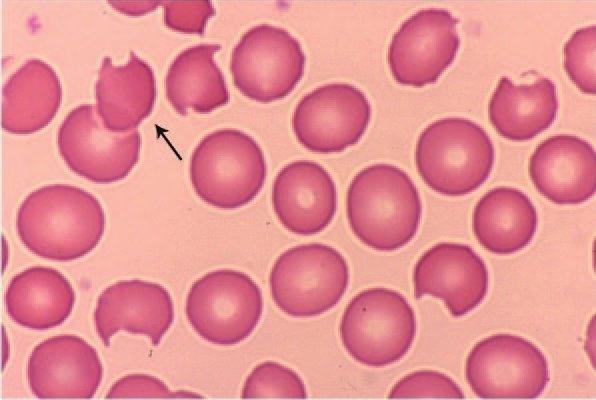
Figure1–13.A.Normalblood.Thearrowpointstoanormochromic-normocyticdiscocyte.B.Stomatocytes.Thedoublearrowpointstothetwo morphologictypesofstomatocyte:uppercellwithaslit-shapedpaleareaandlowercellwithasmallcentralcircularpalearea.C.Echinocytes. Thefieldhasseveralsuchcells.Thearrowpointstooneexamplewithevenlydistributed,blunt,short,circumferentiallypositionedprojections. D.Acanthocytes.Thearrowpointstooneexamplewithafewspike-shapedprojections,unevenlydistributedandofvaryinglengths.E.Spherocytes. Small,circular,densely-staining(hyperchromic)cellsthat,whenfullydeveloped,shownocentralpallor.F.Schizocytes(schistocytes,helmetcells, fragmentedredcells).Thesemicrocyticcellfragmentsmayassumevariedshapes.Thearrowpointstoatriangularshape,buttwoothersofdifferent shapearealsopresentinthefield.Despitebeingdamagedandverysmall,theyfrequentlymaintainabiconcaveappearance,asseenbytheircentral pallor.G.Sicklecells(drepanocytes).Numeroussicklecellsareshown.Twoareintheclassicshapeofthebladeontheagriculturalsickle(arrow).Many redcellsthathaveundergonethetransformationtoa“sickle”celltaketheslightlylessextremeformofellipticalcellswithaverynarrowdiameter withcondensedhemoglobininthecenter(para-crystallization).Abouteightsuchcellsareinthefield.H.Elliptocytesandovalocytes.Thelowerarrow pointstoanelliptocyte(cigar-shaped).Theupperarrowpointstoanovalocyte(football-shaped).Becausebothformsmaybeseentogetherinacase ofinheriteddisease(samegenemutationresultinginbothshapes),asshownhere,ithasbeenproposedthatallsuchshapesbecalledelliptocytes withaRomannumeraltodesignatetheseverityoftheshapechangetowardtheelliptical,thatis,elliptocytesI,II,andIII.I.Targetcells(codocytes). Thearrowpointstoonecharacteristicexampleamongseveralinthefield.Thehemoglobinconcentrationcorralledbymembranerecurvatureinthe centerofthecellgivesittheappearanceofanarcherytarget.J.Tear-drop–shapedcells(dacryocytes).Threedacryocytesareinthisfield.Oneexample isindicatedbythearrowK.Horncell(keratocyte).Severalexamplesareinthefield.Thearrowpointstoatypicalsuchcellwithtwosharpprojections. (ReproducedwithpermissionfromLichtmanMA,ShaferMS,FelgarRE,etal:Lichtman’sAtlasofHematology2016.NewYork,NY:McGrawHill;2017.)
resutofossofmembranesurfaceareaorincreasedcevoume.Stomatocytosisisafeatureofhereditaryhydrocytosiscausedbyincreasedce voumeandconsequentdecreaseinSA:Vratio.Aspectrumofabnorma cesvaryingfromnormadiscocytestostomatocytes,spherostomatocytes,anddensemicrospherocytesisseeninhereditaryspherocytosis.
Elliptocytes
Eiptocytesareseeninhereditaryeiptocytosis(Chap.15)asweas inthaassemia(Chap.17),irondeficiency(Chap.11),andmegaobasticanemia(Chap.9).49Inboodfimsofnormasubjects,eipticaor ovacesusuayconstituteessthan1%oftheerythrocytes.Invarious pathoogicsituations,withorwithoutanemia(thaassemiatrait,foate, andirondeficiency),thenumberofeiptocytescanincreaseto10%. Exceptionay,asindyserythropoiesis,theproportioncanbeashighas 50%.Inhereditaryeiptocytosis,thenumberofeipticaerythrocytes variesgreaty,from1%to98%.Quaitativeandquantitativeanomaies ofspectrinandprotein4.1,themajorproteinsofthemembraneskeeton,areassociatedwithhereditaryeiptocytosis.49,138Severehemoytic anemiaisseenonyinthehomozygousorcompoundheterozygotes formofthedisease(hereditarypyropoikiocytosis),inwhichextensive cefragmentationproducespyropoikilocyteswithmarkeddecreasesin SA:Vratio.
Acanthocytes
Theacanthocyte(Chap.15)isirreguaryshaped,with2to10hemisphericaytippedspicuesofvariabeengthanddiameter.Thebasesof thespicuesontheacanthocyteareofvaryinggirth,unikethespicues onechinocytes,whichhaveremarkabyuniformdimensions.Acanthocytesareseeninneuroacanthocytosisandinabetaipoproteinemia.139 Theackofanemiaintheseconditionssuggeststhattheseceshave nearnormaifespanincircuation.
TargetCells(Codocytes)
Areativeexcessofmembranesurfaceareaordecreasedcevoume eadingtoincreasedSA:Vratioresutsintargetces.140Targetcesmay beseeninobstructiveiverdisease,hemogobinopathies(SandC),thaassemia,irondeficiency,postspenectomy,andecithinchoesteroacetytransferasedeficiency.Inpatientswithobstructiveiverdisease,ecithin choesteroacetytransferaseactivityisdepressed.Thisincreasesthe choestero-to-phosphoipidratioandproducesanabsouteincrease inthesurfaceareaoftheredcemembrane.Incontrast,membrane excessisonyreativeinpatientswithiron-deficiencyanemiaandthaassemiabecauseofthereducedcevoume.Incontrasttospherocytes, whichexhibitincreasedosmoticfragiity,targetredcesareosmoticay resistant.
SickleCells(Drepanocytes)
Thesickecedispaysacharacteristicvariationofformonstained boodfims(Chap.18).Thefusiformceinthecrescentshapewith twopointedextremitiesisencounteredmostcommonyindeoxygenatedboodsampesasaresutofpoymerizationofsickehemogobin. Ifsickeceformationisobservedbyphase-contrastmicroscopy,the eariestchangewithdeoxygenationisossofficker,foowedbysight deformationatthediscocyteborder,withdispacementofthehemogobintooneregionofthece.Thecetheneongatesandbecomes rigidasaresutofpoymerizationofhemogobinS.Uponreoxygenation,thesickeceresumesthediscocyteformand,insodoing,canose membranebymicrospheruationandfragmentationduringretraction ofongspicues.141Evidencesuggeststhatthemoretypicasicke-shaped cesformundersowdeoxygenation.Witheachsicking–unsicking cyce,membranedamageaccumuates,resutingintheformationof irreversibysickedces.142,143Thesecesareincapabeofreversionto
thebiconcavediscshape,evenwhenfuyoxygenated.Theyhavean increasedhemogobinconcentration,increasedcationpermeabiity, decreasedpotassium,andincreasedsodium.
FragmentedCells(Schistocytes)
Schistocytesareseeninmicroangiopathichemoyticanemias(thromboticthrombocytopenicpurpura[TTP],disseminatedintravascuar coaguation[DIC],vascuitis,gomeruonephritis,renagraftrejection), carcinomatosis,heartvavehemoysis(prostheticorpathoogicvaves), severeburns,andmarchhemogobinuria(Chap.22).Fibrinstrandsin damagedboodvessescanbearrayedsothattheysievethepassingred ces.Ifapassingredcefodsoverorotherwiseattachestothestrand, theboodstreampusonthearrestedce,stretchesit,andeventuay fragmentsit.144Thespeenrapidyremovestheschistocyteswithaow reativeSA:Vratio;theremaindermaycircuateformanydays.
REFERENCES
1.AnsteeDJ,GampeA,ToyeAM.Ex-vivogenerationofhumanredcesfortransfusion. CurrOpinHematol.2012;19:163.
2.SatoT,MaekawaT,WatanabeS,eta.Erythroidprogenitorsdifferentiateandmaturein responsetoendogenouserythropoietin.JClinInvest.2000;106:263.
3.GiarratanaMC,KobariL,LapionneHC,eta.Exvivogenerationoffuymature humanredboodcesfromhematopoieticstemces.NatBiotechnol.2005;23:69.
4.HuJ,LiuJ,XueF,eta.Isoationandfunctionacharacterizationofhumanerythrobastsatdistinctstages:impicationsforunderstandingofnormaanddisorderederythropoiesisinvivo.Blood.2013;121:3246.
5.LiJ,HaeJ,BhagiaP,eta.Isoationandtranscriptomeanaysisofhumanerythroid progenitors.Blood.2014;124:3636.
6.SouthcottMJG,TannerMJA,AnsteeDJ.Theexpressionofhumanboodgroupantigensduringerythropoiesisinacecuturesystem.Blood.1999;93:4425.
7.PaisJ.Ontogenyoferythropoiesis.CurrOpinHematol.2008;15:155.
8.PaisJ.Primitiveanddefinitiveerythropoiesisinmammas.FrontPhysiol.2014;5:3.
9.ZambidisET,PeautB,ParkTS,eta.Hematopoieticdifferentiationofhumanembryonicstemcesprogressesthroughsequentiahematoendotheia,primitive,anddefinitivestagesresembinghumanyoksacdeveopment.Blood.2005;106:860.
10.PeredaJ,NiimiG.Embryonicerythropoiesisinhumanyoksac:twodifferentcompartmentsfortwodifferentprocesses.MicroscResTech.2008;71:856.
11.Schmid-SchonbeinH,WesR.Fuiddrop-iketransitionoferythrocytesundershear. Science.1969;165:288.
12.SadahiraY,MoriM.Roeofthemacrophageinerythropoiesis.PatholInt.1999;49:841.
13.BessisM.LivingBloodCellsandTheirUltrastructure.Springer-Verag;1973.
14.GregoryCJ,EavesAC.Threestagesoferythropoieticprogenitorcedifferentiation distinguishedbyanumberofphysicaandbioogicproperties.Blood.1978;51:527.
15.McLeodDL,ShreeveMM,AxeradAA.Improvedpasmacuturesystemforproductionoferythrocyticcooniesinvitro:quantitativeassaymethodforCFU-E.Blood. 1974;44:517.
16.ChasisJA,MohandasN.Erythrobasticisands:nichesforerythropoiesis.Blood. 2008;112:470.
17.ManwaniD,BiekerJJ.Theerythrobasticisand.CurrTopDevBiol.2008;82:23.
18.YokoyamaT,EtohT,KitagawaH,eta.Migrationoferythrobasticisandstoward thesinusoidaserythroidmaturationproceedsinratbonemarrow.JVetMedSci. 2003;65:449.
19.LichtmanMA,SantioP.Redceegressfromthemarrow—Vis-à-tergo.BloodCells. 1986;12:11.
20.ChamberainJK,LichtmanMA.Marrowceegress:specificityofthesiteofpenetration intothesinus.Blood.1978;52:959.
21.WaughRE,SassiM.Aninvitromodeoferythroidegressinbonemarrow.Blood. 1986;68:250.
22.YoshidaH,KawaneK,KoikeM,eta.Phosphatidyserine-dependentengufmentby macrophagesofnuceifromerythroidprecursorces.Nature.2005;437:754.
23.JacobsenRN,ForristaCE,RaggattLJ,eta.MobiizationwithgranuocytecoonystimuatingfactorbocksmeduarerythropoiesisbydepetingF4/80(+)VCAM1(+) CD169(+)ER-HR3(+)Ly6G(+)erythroidisandmacrophagesinthemouse.ExpHematol.2014;42:547.
24.RhodesMM,KopsombutP,BondurantMC,eta.Adherencetomacrophagesinerythrobasticisandsenhanceserythrobastproiferationandincreaseserythrocyteproductionbyadifferentmechanismthanerythropoietin.Blood.2008;111:1700.
25.KawaneK,FukuyamaH,KondohG,eta.RequirementofDNaseIIfordefinitiveerythropoiesisinthemousefetaiver.Science.2001;292:1546.
26.BowmanWDJr.Abnorma(“ringed”)siderobastsinvarioushematoogicandnonhematoogicdisorders.Blood.1961;18:662.
27.HinesJD,GrassoJA.Thesiderobasticanemias.SeminHematol.1970;7:86.
28.KonstantinidisDG,PushkaranS,JohnsonJF,eta.Signaingandcytoskeetarequirementsinerythrobastenuceation.Blood.2012;119:6118.
Thispageintentionallyleftblank
kinasethatinteractswitherythropoietinreceptor;KAP1,KRAB-associatedprotein-1 isatranscriptionalcofactor;KRAB-ZFP,1ofthe400humanzincfingerprotein-based transcriptionfactors;MCV,meancellvolume;mRNA,messengerRNA;mDia2,a proteinthatregulatesactinandfocaladhesiondynamics;miRs,microRNAsaresmall non-codingRNAmolecules;15N,nitrogen;Nix,aproteinthatisexpressedduring erythropoiesisandregulatesmitochondrialapoptosis(autophagy);PHD,proline hydroxylase;PK,pyruvatekinase;PU.1,transcriptionfactor;RACK1,receptorof activatedproteinkinaseC;RAS,therenin–angiotensinsystem;Rb,tumorsuppressor retinoblastoma(protein);RCM,redcellmass;SCL/TAL1,stemcellleukemia/t-cell acutelymphoblasticleukemia1factor;SCL/tal-1,basichelix-loop-helixtranscription factor;SNPs,single-nucleotidepolymorphisms;SOCS3,asignaltransductionprotein (alsoknownasCIS3)thatdownregulatesactivityoferythropoietinreceptor;99mTc, technetium-99;VHL,vonHippel-Lindauprotein.
erythrocytestoreplacethe2×1011redcells(approximately1%ofthetotal redcellmass[RCM])removedfromthecirculationeachday.Redcellproductionincreasesseveral-foldafterbloodlossorhemolysis.WhenoneoftheprogenyofanHSCbecomescommittedtotheerythroidlineage,thisearlyerythroid progenitorundergoesaseriesofdivisionsandconcurrentmaturationthat eventuallyresultinmorphologicallyrecognizableerythroblasts.Afterexpulsionofthenucleus,amacrocyte(polychromatophilicwhenWright-stained,or areticulocyteifnewmethyleneblue–stained)leavesthemarrow.Duringthefirst24to48hoursinthecirculation,reticulocyteslosetheirresidualorganelles(mitochondriaandribosomes)throughanautophagicprocess (Chap.1)andundergoreconditioningofthemembranetobecomematurered cellswithabiconcavediscshape.Erythropoiesisiscontrolledbytranscription factorsandcytokines,theprincipalonesbeingGATA1anderythropoietin (EPO),respectively,whichinfluencelineagecommitment,proliferation,apoptosis,differentiation,andnumberofdivisions,fromtheearliestprogenitor tolateerythroblasts.Thenumberofredcellsproducedvariesinresponseto tissueoxygenation,whichdeterminesthelevelofthetranscriptionfactors, hypoxia-induciblefactors(HIFs)—HIF-1andHIF-2—theprincipalregulators oftheresponsetohypoxia.HIFsmodulateerythropoiesisbyregulationofEPO productionbydirectEPO-independentmechanism(s)andbyfacilitatingiron availability.
Thesurvivalofredcellsinthecirculationcanbemeasuredinavarietyof ways:(1)bylabelingwithradioactiveisotopes,particularly51Cr,andassessing thedisappearanceoftheradioactivetagfromthecirculationovertime; (2)bylabelingtheerythrocyteswithbiotinorafluorescentdyeandmeasuringthismarkerovertime;(3)bydeterminingthedisappearanceoftransfused antigen-matchedallogeneicerythrocytesusingimmunologicmarkers;and (4)bymeasuringtheexcretionofcarbonmonoxide(CO),aproductofheme catabolism.
Suchstudiesshowthatnormalhumanredcellshaveafinitelifespan averaging120days,withsomecomponentofrandomdestruction.Themitochondrialandribosomalremovalhighlightingmaturationofthereticulocyte isaccompaniedbyincreasingcelldensity,butafterafewdaysofintravascular lifespan,thereislittlefurtherincreaseindensityorotherchangesinthephysicalpropertyoftheredcells.Thus,celldensityisnotagoodmarkerforaged redcells.Thishasmadestudyofthesenescentchangesintheredcellthat markitfordestructiondifficult.Candidatesforsuchchangesincludechanges inmembraneAE-1(anionexchanger-1;alsoknownasband3)andexposure ofphosphatidylserineonthemembrane,whichmaybeofmajorimportance.
HISTORY
Erythrocytesevolvedlargelyforthepurposeoftransportingoxygento tissuesandcarbondioxidefromtissues.Thus,thesizeoftheredcell mass(RCM)andtherateofredcellproductionmustbecloselyrelated tosupplyanddemandforoxygeninthetissues.Frenchmountaineers andphysiologistsattheendofthe19thcenturyestablishedthatalow tissuetensionofoxygenstimulatesredcellproduction.1In1906,Paul Carnot,aprofessorattheSorbonne,andMademoiselleDeFlandre,his associate,suggestedthathypoxiageneratesahumoralfactorcapableof stimulatingredcellproduction.2In1950,KurtReissmann3provided evidencefortheexistenceofanindirecthumoralmechanismusing parabioticrats.TheworkofErslevandcolleagues,4,5demonstratedthat theplasmafromanemicrabbitsandprimatescontainsanerythrocyte stimulatingfactor,appropriatelynamederythropoietin(EPO).Then,EPO