The General Dental Council (GDC) has published its annual Registration Statistical Report for 2025, showing a 4.7% increase in the number of registered dental professionals in the UK over the past year.
As of December 2025, 131,680 dental professionals were registered with the GDC. The number of dentists increased by 3.4% to 47,916, and dental care professionals (DCP) by 5.5% to 83,764. The report includes comparison data from previous years to show trends and changes. For the first time, internationally qualified dentists now outnumber UK-qualified dentists joining the register, 53% compared to 47%.
The number of dental nurses increased by 6,473 (5.4%) to 68,472. Dental nurses now make up over 50% of all
those registered with the GDC, with 96% of those who joined the register in 2025 being female.
The number of registered dental therapists grew by 21% to 8,661, while the number of dental hygienists increased by 11% to 11,292; and 71% (1,044) of new dental therapist registrations and 55% (591) of dental hygienist registrations were from internationally qualified dentists who joined the register with DCP titles, a route that has now closed.
Despite overall growth, the number of dental technicians dropped for the sixth consecutive year, falling below 5,000 for the first time. Only 143 dental technicians joined the register in 2025. In total, there were 9,332 additions to the register in 2025, down from 9,888 in 2024.
NHS Modernisation Bill’s
Theresa Thorp, Executive Director of Regulation at the GDC, said: “This report provides important insights into the dental workforce, the people who make up our register, and dental professions that are growing and changing.
“Supporting a diverse and growing dental workforce is one of the core commitments in our strategy, Trusted and Effective, for 2026 to 2028, and we’re committed to ensuring our registration processes are as straightforward as possible for those joining our register.”
Registration timeliness and performance
• For the first time, the report includes a dedicated section on registration timeliness.
• The Registration team assessed 12,654 applications across all routes in 2025, compared to 12,978 in 2024.
positive impact for dentistry
The Government’s NHS Modernisation Bill, announced in the recent King’s Speech, has been welcomed for the most part by the dental professions.
The Association of Dental Groups (ADG) in particular believes these reforms present a significant opportunity to strengthen dentistry’s integration within the wider health system.
The ADG is particularly encouraged by three measures of direct relevance to dentistry:
• The creation of a Single Patient Record, which could finally allow dentistry to link properly with the rest of the health system, improving diagnosis, prevention and continuity of care.
• The transfer of NHS England’s functions into the Department of Health and Social Care, a move that aligns with the ADG’s ongoing work on governance reform and the foundations already laid for an upcoming ADG report on this issue.
• Strengthened accountability for Integrated Care Boards (ICBs), which the ADG views as essential to improving local commissioning, reducing unwarranted variation and ensuring dental access is prioritised consistently across England.
Neil Carmichael, Executive Chair of the Association of Dental Groups, said:
“The NHS Modernisation Bill marks an important moment for dentistry
and outlines three key points that the ADG has been urging stakeholders to grasp. Firstly, the creation of a Single Patient Record is a breakthrough we have been urging for years. This is the missing link that will finally allow dentistry to connect with the rest of the health system, improving diagnosis, prevention and long term outcomes for patients.
“Secondly, the decision to bring NHS England’s functions into the Department of Health and Social Care also has the potential to streamline decision making and strengthen democratic accountability. We have already prepared the foundations for an
• The GDC met, and in several areas exceeded, its timeliness targets across all UK and specialist registration routes in 2025.
Diversity and demographics
• The dental register is predominantly female, with 78% of all dental professionals identifying as female, including 54% of dentists and 92% of DCPs.
• 31% of dentists are of Asian or Asian British ethnic origin (2024: 30%), which is three times higher than the proportion in the total UK population.
• 46% of dentists identified as being of white ethnic grouping (2024: 47%), compared to 74% of DCPs (2024: 75%).
The full report is available at https://tinyurl.com/gdcreg25 ■
ADG report on this issue, and we look forward to contributing constructively as the detail emerges.
“Then, thirdly, strengthening the accountability of Integrated Care Boards is vital. We have been clear that ICBs must take their responsibilities for dental access seriously, and this announcement is a welcome step toward ensuring consistent, transparent and effective commissioning across the country.
“Dentistry must be fully embedded in these reforms. The ADG stands ready to work with Government to ensure that modernisation delivers meaningful improvements for patients and the dental workforce alike.”
Summer decided to make an early appearance, encroaching on Spring’s territory in May. While many of us root for Summer to arrive, I’d argue that perhaps the sun-drenched season went a tad overboard, baking us in temperatures of up to 35°C with no warm up to prepare us.
For those of you working in practice, I hope you either had suitable air conditioning or cooling available, or that your clinic remains comfortable while you provide care. As the climate continues to be evermore unpredictable, temperature management is certainly something to take into consideration when designing a new practice.
Speaking of practice design, we have a terrific look at One Dental Kensington, where clinical directors Deep Patel and Lumini Gamage have been sweating not from the heat but the details that go into the design of the place. You can read all about it on page 10. Before that, we have an imagined conversation in the style of classic sitcom Yes, Minister, penned by former CDO England Sara Hurley. Read the hilarious script for The Dental Reform Brief on page 8.
And last but not least, on page 52 you can find the first half of this year’s Dental Awards winners and finalists. Read the full list and watch this year’s presentation at https://the-probe.co.uk/awards/the-dental-awards-2026/ or scan the QR code. Congratulations to everyone who was shortlisted, a finalist, commended, or won! The standard was incredible this year and you’ve all done so well!
The Probe is published by Purple Media Solutions.
Registered in England.
Registered number 5949065
Managing Editor: James Cooke
Commercial Director: Gary Henson
Divisional Administrator: Francesca Smith
Production Designer 1 : Lorna Reekie
Production Designer 2: Rob Tremain
Digital Content Manager: Stephen Wadey
Circulation Manager: Andy Kirk
Managing Director: Ed Hunt
Regular Contributors: Lisa Bainham, Alun Rees, Dhiraj Arora, Ollie Jupes and Pam Swain
E-mail news, stories or opinion to james.cooke@purplems.com
Media Solutions Ltd, 2014. All rights reserved. ISSN 0032-9185. The publisher’s written consent must be obtained before any part of this publication may be reproduced in any form whatsoever, including photocopies, and information retrieval systems. While every effort has been made to ensure that the information in this publication is correct and accurate, the publisher cannot accept
liability for any consequential loss or damage, however caused, arising as a result of using information printed in this magazine. The views expressed in The Probe are not necessarily the views of the magazine, nor of Purple Media Solutions
Editorial Advisory Board: Dr Barry Oulton, B.Ch.D. DPDS MNLP; Dr Graham Barnby, BDS, DGDP RCS; Dr Ewa Rozwadowska, BDS; Dr Yogi Savania BChD, MFGDP; Dr Ashok Sethi, BDS, DGDP (UK), MGDS RCS; Dr Paroo Mistry BDS MFDS MSc MOrth FDS (orth); Dr Tim Sunnucks, BDS DRDP; Dr Jason Burns, BDS, LDS, DGDP (UK), DFO, MSc; Prof Phillip Dowell, BDS, MScD, DGDP RCS, FICD; Dr Nigel Taylor MDSc, BDS, FDS RCS(Eng), M’Orth RCS(Eng), D’Orth RCS(Eng); Mark Wright BDS(Lon), DGDP RCS(UK), Dip Imp Dent.RCS (Eng) Adv. Cert, FICD; Dr Yasminder Virdee BDS.
Scan to explore The Probe’s back catalogue online or visit the-probe.co.uk/issues
Deep Patel Partner One Dental
Lumini Gamage Partner One Dental
Tom Orchard Head of Practice Sales Lily Head Dental Practice Sales
Rafina O’Brien Dental hygienist, presenter, and speaker
Dr Ravinder Jhutie Prosthetic Dentist TopLabs dental laboratory
Simon Cosgrove Dental Regional Manager Wesleyan Financial Services
Sara Hurley Former Chief Dental Officer, England
Dr Rebecca Williams Associate Dentist Cox and Hitchcock
Aesthetics with a system –composites from TOKUYAMA
Specialists & all-round performers: The ESTELITE family is a unique system for modern restorative dentistry based on spherical fillers.
Individual application options thanks to the wide range of viscosities
Excellent polishability & handling repeatedly honoured by The Dental Advisor
High load-bearing capacity thanks to optimally engineered spherical fillers
Rapid depth curing thanks to controlled refractive indices and RAP technology
The Dental Reform Brief – An entirely imagined exchange
This piece is written in affectionate tribute to the satirical tradition of Yes Minister and Yes, Prime Minister, whose genius lay in exposing the gap between political intent, administrative process and public service delivery. Any resemblance to actual departmental conversations is, of course, entirely coincidental
Scene
The Department of Health and Social Care. A new Secretary of State for Health, recently arrived from the Treasury, is being briefed on NHS dentistry. His Permanent Secretary, Sir Humphrey, enters carrying a large, dog-eared departmental folder, its corners softened by use and its contents thickened by history.
On the cover, in fading ink, it reads:
NHS Dental Reform — England
• 2006 Contract
• 2009 Steele Review
• 2011 Pilots
• 2016 Prototypes
• 2026 Reset
Inside are Select Committee reports, the Steele Review, pilot evaluations, prototype reports, a National Audit Office investigation and a yellow sticky note reading: “Urgent — update lines to take.”
Since the 2006 dental contract was introduced, a dozen Secretaries of State have held the Health brief. The folder, unlike most of them, has remained in post.
Minister: Humphrey, why does this folder say 2006, 2009, 2011, 2016 and 2026?
Sir Humphrey: Continuity, Minister.
Minister: Four of the dates are crossed out.
Sir Humphrey: Also continuity, Minister.
Minister: It looks as though the same problem has been passed from one Secretary of State to the next for twenty years.
Sir Humphrey: I would not say passed, Minister.
Minister: What would you say?
Sir Humphrey: Sequentially retained within the Department’s strategic reform horizon.
Minister: Kicked down the road, then.
Sir Humphrey: Only in the sense that the road has been subject to ongoing review.
Minister: How many Health Secretaries have had this file since the 2006 contract?
Sir Humphrey: That depends whether Minister wishes to count individuals, tenures, or opportunities for decisive reform.
Minister: Individuals.
Sir Humphrey: Twelve, Minister. Thirteen, if one counts Mr Barclay twice, which some officials do, depending on the spreadsheet.
Minister: And the problem is still here?
Sir Humphrey: Very much so, Minister. That is how one recognises a truly durable policy issue.
Minister: There are Select Committee reports in here.
Sir Humphrey: Several, Minister. They add weight to the file.
Minister: Alongside the early warnings after the 2006 contract, the Steele Review, the pilots, the prototypes and the 2023 Health and Social Care Committee report?
Sir Humphrey: A comprehensive record of concern, Minister.
Minister: And implementation?
Sir Humphrey: A more selective record, Minister.
Minister: The 2006 reforms were supposed to improve access.
Sir Humphrey: That was certainly the aspiration.
Minister: But they did not?
Sir Humphrey: Not universally, Minister.
Minister: It says here that Steele pointed towards clearer patient pathways and a better-designed system, less dependent on treatment volume alone. Then came pilots on registration, capitation and quality. So, this is not a new conversation.
Sir Humphrey: No, Minister. It is a mature conversation.
Minister: Seventeen years mature?
Sir Humphrey: Maturity takes time.
Minister: And in 2023, Parliament was still calling for urgent and fundamental reform.
Sir Humphrey: Parliamentary memory can be inconveniently long.
Minister: It also noted frustration that recommendations made fifteen years earlier had still not been implemented.
Sir Humphrey: Minister, consistency is important in public administration.
Minister: Not when it is consistency of failure.
Sir Humphrey: We would normally call that an enduring delivery challenge.
Minister: So nothing good happened in all that time?
Sir Humphrey: On the contrary, Minister. A great deal of good happened. That is what makes the absence of reform so difficult to explain.
Minister: Go on.
Sir Humphrey: Prevention became increasingly prominent: Dental Check by One, phased courses of treatment, early intervention and an impressive accumulation of commissioning standards. All the ingredients of modern oral health system, Minister. Admirably assembled, if not entirely embedded.
Minister: But not the contract.
Sir Humphrey: Not entirely.
Minister: So prevention was recognised, but not built in. Surely it should sit at the heart of the contract, not as an adjunct. Remunerated, measured, expected and supported.
Sir Humphrey: That would require changing incentives.
Minister: Yes.
Sir Humphrey: And changing incentives changes behaviour.
Minister: That is the point.
Sir Humphrey: It is also the risk.
Minister: So we admired the direction of travel without necessarily travelling in that direction.
Sir Humphrey: A fair summary, Minister. Though perhaps a little direct.
Minister: And the prototypes?
Sir Humphrey: The prototype programme tested changes to activitybased dental contracts, including clinical and remuneration models. A veritable garden of reform.
Minister: And then?
Sir Humphrey: The garden was returned to lawn.
Minister: Meaning?
Sir Humphrey: The contract reform programme was recalibrated into the Department’s longer-term reform trajectory, Minister. The participating practices returned to the existing activity system.
Minister: So, after more than a decade testing how to move beyond UDAs, the system returned to them?
Sir Humphrey: With the benefit of learning, Minister.
Minister: Learning what?
Sir Humphrey: That reform is safest when it remains under evaluation.
Minister: And the Dental Recovery Plan?
Sir Humphrey: A most encouraging title.
Minister: The National Audit Office said it was not on course to deliver more than 1.5 million additional courses of treatment. And even if it had, activity would still be millions of courses below pre-pandemic levels.
Sir Humphrey: Context is important, Minister.
Minister: Meaning?
Sir Humphrey: One must judge a recovery plan not only by recovery, but by the seriousness with which recovery is intended.
Minister: So it did not recover the service.
Sir Humphrey: It recovered the appearance of a plan.
Minister: But patients still cannot access care. Children are still presenting with preventable disease. We have dental deserts. The manifesto promised urgent appointments, supervised toothbrushing, recruitment to underserved areas and contract reform. What is the actual plan?
Sir Humphrey: The plan, Minister, is to deliver the commitments. Minister: Yes, but how?
Sir Humphrey: Through implementation.
Minister: Implementation of what?
Sir Humphrey: The delivery programme.
Minister: And what does the delivery programme deliver?
Sir Humphrey: The plan, Minister.
Minister: Humphrey, this sounds circular.
Sir Humphrey: Not circular, Minister. Iterative.
Minister: And where is the patient in this iteration?
Sir Humphrey: At the centre, Minister.
Minister: In what sense?
Sir Humphrey: In the sense that all documents say so.
Minister: I came from the Treasury, Humphrey. I understand money. The BBC recently reported that around £900 million in NHS dental funding was returned through clawback over two years. That’s roughly £1 for every £7 commissioned. That does not sound like a simple story of “no money.”
Sir Humphrey: No, Minister. It is a story of resource allocation, contractual performance, delivery variance and local system utilisation.
Minister: A commissioned pound returned through clawback has not bought access, prevention or trust.
Sir Humphrey: True, Minister. Although it has bought a commissioning intention.
Minister: Patients cannot chew with a commissioning intention.
Sir Humphrey: No, Minister. Though one should not underestimate the value of intention in public administration.
Minister: Let us talk about urgent appointments. They matter.
Sir Humphrey: Absolutely, Minister. Urgent access is central to restoring public confidence.
Minister: But urgent access is not recovery. An extraction, a temporary dressing, no onward pathway, no stabilisation, no prevention, no recall, that is not a functioning service.
Sir Humphrey: It is a responsive intervention, Minister.
Minister: It is a pressure valve.
Sir Humphrey: Precisely. And pressure valves are very important in a system under pressure.
Minister: The aim is to reduce the pressure, Humphrey.
Sir Humphrey: In the medium term, naturally.
Minister: And in the short term?
Sir Humphrey: We announce the pressure valve.
Minister: Urgent access may reduce headlines. It does not reduce incidence.
Sir Humphrey: A stark formulation, Minister.
Minister: Is it wrong?
Sir Humphrey: Not wrong, exactly. Merely insufficiently reassuring.
Minister: Reassuring to whom?
Sir Humphrey: Those announcing the pressure valve, Minister.
Minister: Let us talk about the contract. The Unit of Dental Activity counts activity, but it does not capture prevention, complexity, stabilisation, continuity, patient experience or long-term health gain.
Sir Humphrey: It has the great virtue of being countable.
Minister: So does failure.
Sir Humphrey: Yes, Minister, but failure is harder to include in an annual report.
Minister: Can the number of UDAs tell me whether disease has been prevented? Whether a child avoided hospital extraction? Whether a cancer patient received timely oral health support before treatment?
Sir Humphrey: Not as a standard contract metric.
Minister: Then what does it tell me?
Sir Humphrey: Activity, Minister.
Minister: And what does activity tell me?
Sir Humphrey: That something has happened.
Minister: Not whether the right thing happened.
Sir Humphrey: That would be an outcome, Minister.
Minister: Do we measure outcomes?
Sir Humphrey: We aspire to.
Minister: But we pay and performance-manage through UDAs.
Sir Humphrey: Principally, yes.
Minister: So the system talks outcomes but counts activity.
Sir Humphrey: A concise summary, Minister.
Minister: And then we are surprised when activity drives behaviour.
Sir Humphrey: Surprise is often an important stage in policy development.
Minister: If we want prevention, stabilisation and health gain, we need data that can show them. The NHS already has much of it: general practice, hospitals, community services and pharmacy. But dentistry is disconnected from all of it.
Sir Humphrey: Dentistry has its own systems, Minister.
Minister: That is the problem, not the answer. A patient with diabetes, frailty, cancer or pregnancy does not become less relevant to
dentistry because the data sits somewhere else. And their oral health does not become less relevant to the rest of the NHS because it sits in a dental record. If we are building a Single Patient Record, the mouth is part of the body.
Sir Humphrey: Anatomically correct. Administratively complex.
Minister: Then the administration needs to catch up with the anatomy.
Sir Humphrey: Again with the anatomy, Minister.
Minister: And ICBs. Do they have the tools to commission differently?
Sir Humphrey: They have responsibility, Minister.
Minister: I asked about tools.
Sir Humphrey: Responsibility is a powerful tool.
Minister: Not if they inherit fragile markets, constrained flexibilities, limited data and national expectations still shaped by activity rather than health gain.
Sir Humphrey: Local flexibility must be exercised within a clear national framework.
Minister: Which means?
Sir Humphrey: They may innovate, provided they do not do anything too different.
Minister: Some areas need new forms of provision: multidisciplinary clinics, sessional models, urgent-to-stabilisation pathways, and services connected to children’s health, care homes and wider primary care.
Sir Humphrey: Innovation is welcome, Minister, once it has been piloted, evaluated, assured, risk-assessed, aligned, re-scoped and rendered sufficiently familiar.
Minister: Humphrey, that sounds like innovation being processed until it is no longer innovative.
Sir Humphrey: We prefer to call it responsible transformation.
Minister: Announcements, roundtables, dashboards, action plans, stakeholder events, carefully crafted ambition, none of it is progress unless patients experience care, dental teams can deliver, and commissioners can commission differently.
Sir Humphrey: A demanding definition of progress, Minister. Minister: It is the only useful one. So what do you recommend?
Sir Humphrey: A phased programme of engagement to develop a shared vision for sustainable NHS dental transformation.
Minister: NHS dentistry has spent too long strapped into the policy rollercoaster: big promises, sharp turns, no clear destination. It needs direction.
Sir Humphrey: An unfortunate metaphor, Minister.
Annual Service Contracts
Minister: Is it inaccurate?
Sir Humphrey: Not necessarily inaccurate. Merely unhelpfully vivid.
Minister: Patients want care, not metaphors.
Sir Humphrey: Quite. Though metaphors are considerably easier to procure.
Minister: Then let us be precise. I want to avoid four mistakes: mistaking allocated funding for delivered care; activity for access; access for continuity; and continuity for health gain.
Sir Humphrey: Philosophically elegant, Minister. Operationally troublesome.
Minister: And let us be clear about the ambition. NHS dentistry cannot be repeatedly relegated to the margins of universal healthcare. Oral health is not optional, and access to care is not a favour to be rationed when the system finds it convenient.
Sir Humphrey: A powerful phrase, Minister. Shall I ask communications to incorporate it into the stakeholder pack?
Minister: No, Humphrey. Put it in the operating model.
Sir Humphrey: Ah.
Minister: Are you going to help me fix this?
Sir Humphrey: Minister, I shall ensure the Department gives the matter the fullest and most urgent consideration.
Minister: That is what I was afraid of.
Sir Humphrey closes the folder marked NHS Dental Reform, taking care not to disturb the Select Committee reports, the Steele Review, the National Audit Office investigation or the yellow sticky note marked “Urgent — update lines to take.”
He places it carefully on top of another pile labelled Future Options. Minister: Humphrey, why is that pile so large?
Sir Humphrey: Because, Minister, the future has always been the safest place for dental reform.
About the author
Sara Hurley CBE served as Chief Dental Officer for England from 2015 to 2023. This piece draws on her experience of the policy landscape she inherited and the endeavours to drive forward change. She wishes the new Secretary of State well in delivering on his party’s manifesto pledges
‘This is a practice that sweats the details’
How One Dental became two – and why its meticulous, patient-first approach continues to attract acclaim
One Dental Kensington is a natural evolution of a vision rooted in care, precision and unwavering attention to detail. Still in its early days, its foundation was laid by the success of its sister clinic, One Dental Camberwell, which opened in March 2024 and quickly established itself as an award-winning destination for exceptional dentistry.
It was One Dental Camberwell that proudly won them the title of Best New Practice London – a recognition of the team’s commitment to putting patients first.
But such plaudits were never seen as a finish line; rather, as confirmation that clinical directors Deep Patel and Lumini Gamage’s approach was making a meaningful difference. With patient demand growing and their philosophy resonating strongly, expanding their care to a second location became the natural next step. That next chapter was Kensington.
Deep and Lumini share not only a partnership in leadership but also a shared educational foundation, having both studied dentistry at the University of Plymouth. Since qualifying, they have remained committed to continuous development, refining their clinical skills and elevating the patient experience at every opportunity.
From the very beginning, their vision has been aligned.
‘Our goal has always been to deliver dentistry at the highest possible standard while ensuring every patient feels genuinely cared for,’ they explain. ‘Clinical excellence is essential, but equally important is how patients feel throughout their journey – comfortable, listened to, and confident in the care they are receiving.’
This philosophy is evident across both practices, where the focus extends beyond treatment itself to the environment, communication and personalised care.
Both Deep and Lumini have developed expertise in aesthetic and restorative dentistry. They are passionate about the transformative impact dentistry can have, not just functionally but also emotionally.
‘We are highly focused individuals who take great pride in planning and transforming our patients’ smiles. Helping someone regain their confidence is incredibly rewarding. Equally important is the setting in which that care is delivered. The environment must feel calm, safe and reassuring. Patients deserve to feel completely at ease.’
While Camberwell was always destined to be the first location, deeply connected to Deep’s upbringing, Kensington held its own powerful significance. He spent his school years in Kensington, and it was there that his ambition to become a dentist first took shape. Walking those streets as a student, he imagined a future in which he could open his own practice and serve a community that had played such an important role in his early life.
So, while Camberwell represented home, Kensington symbolised aspiration.
Deep says: ‘Kensington holds so many important memories for me. I went to school there, and even at a young age, I knew I wanted to become a dentist.
Opening a practice in Camberwell was incredibly special because it’s where I grew up. But Kensington was equally meaningful as it represents where my ambitions began.’
Together, Deep and Lumini recognised that Kensington High Street was the perfect location for their second clinic – strategically and emotionally.
‘It felt right,’ they explain. ‘This wasn’t simply about opening another practice. It was about bringing our care to a place that shaped who we are.’
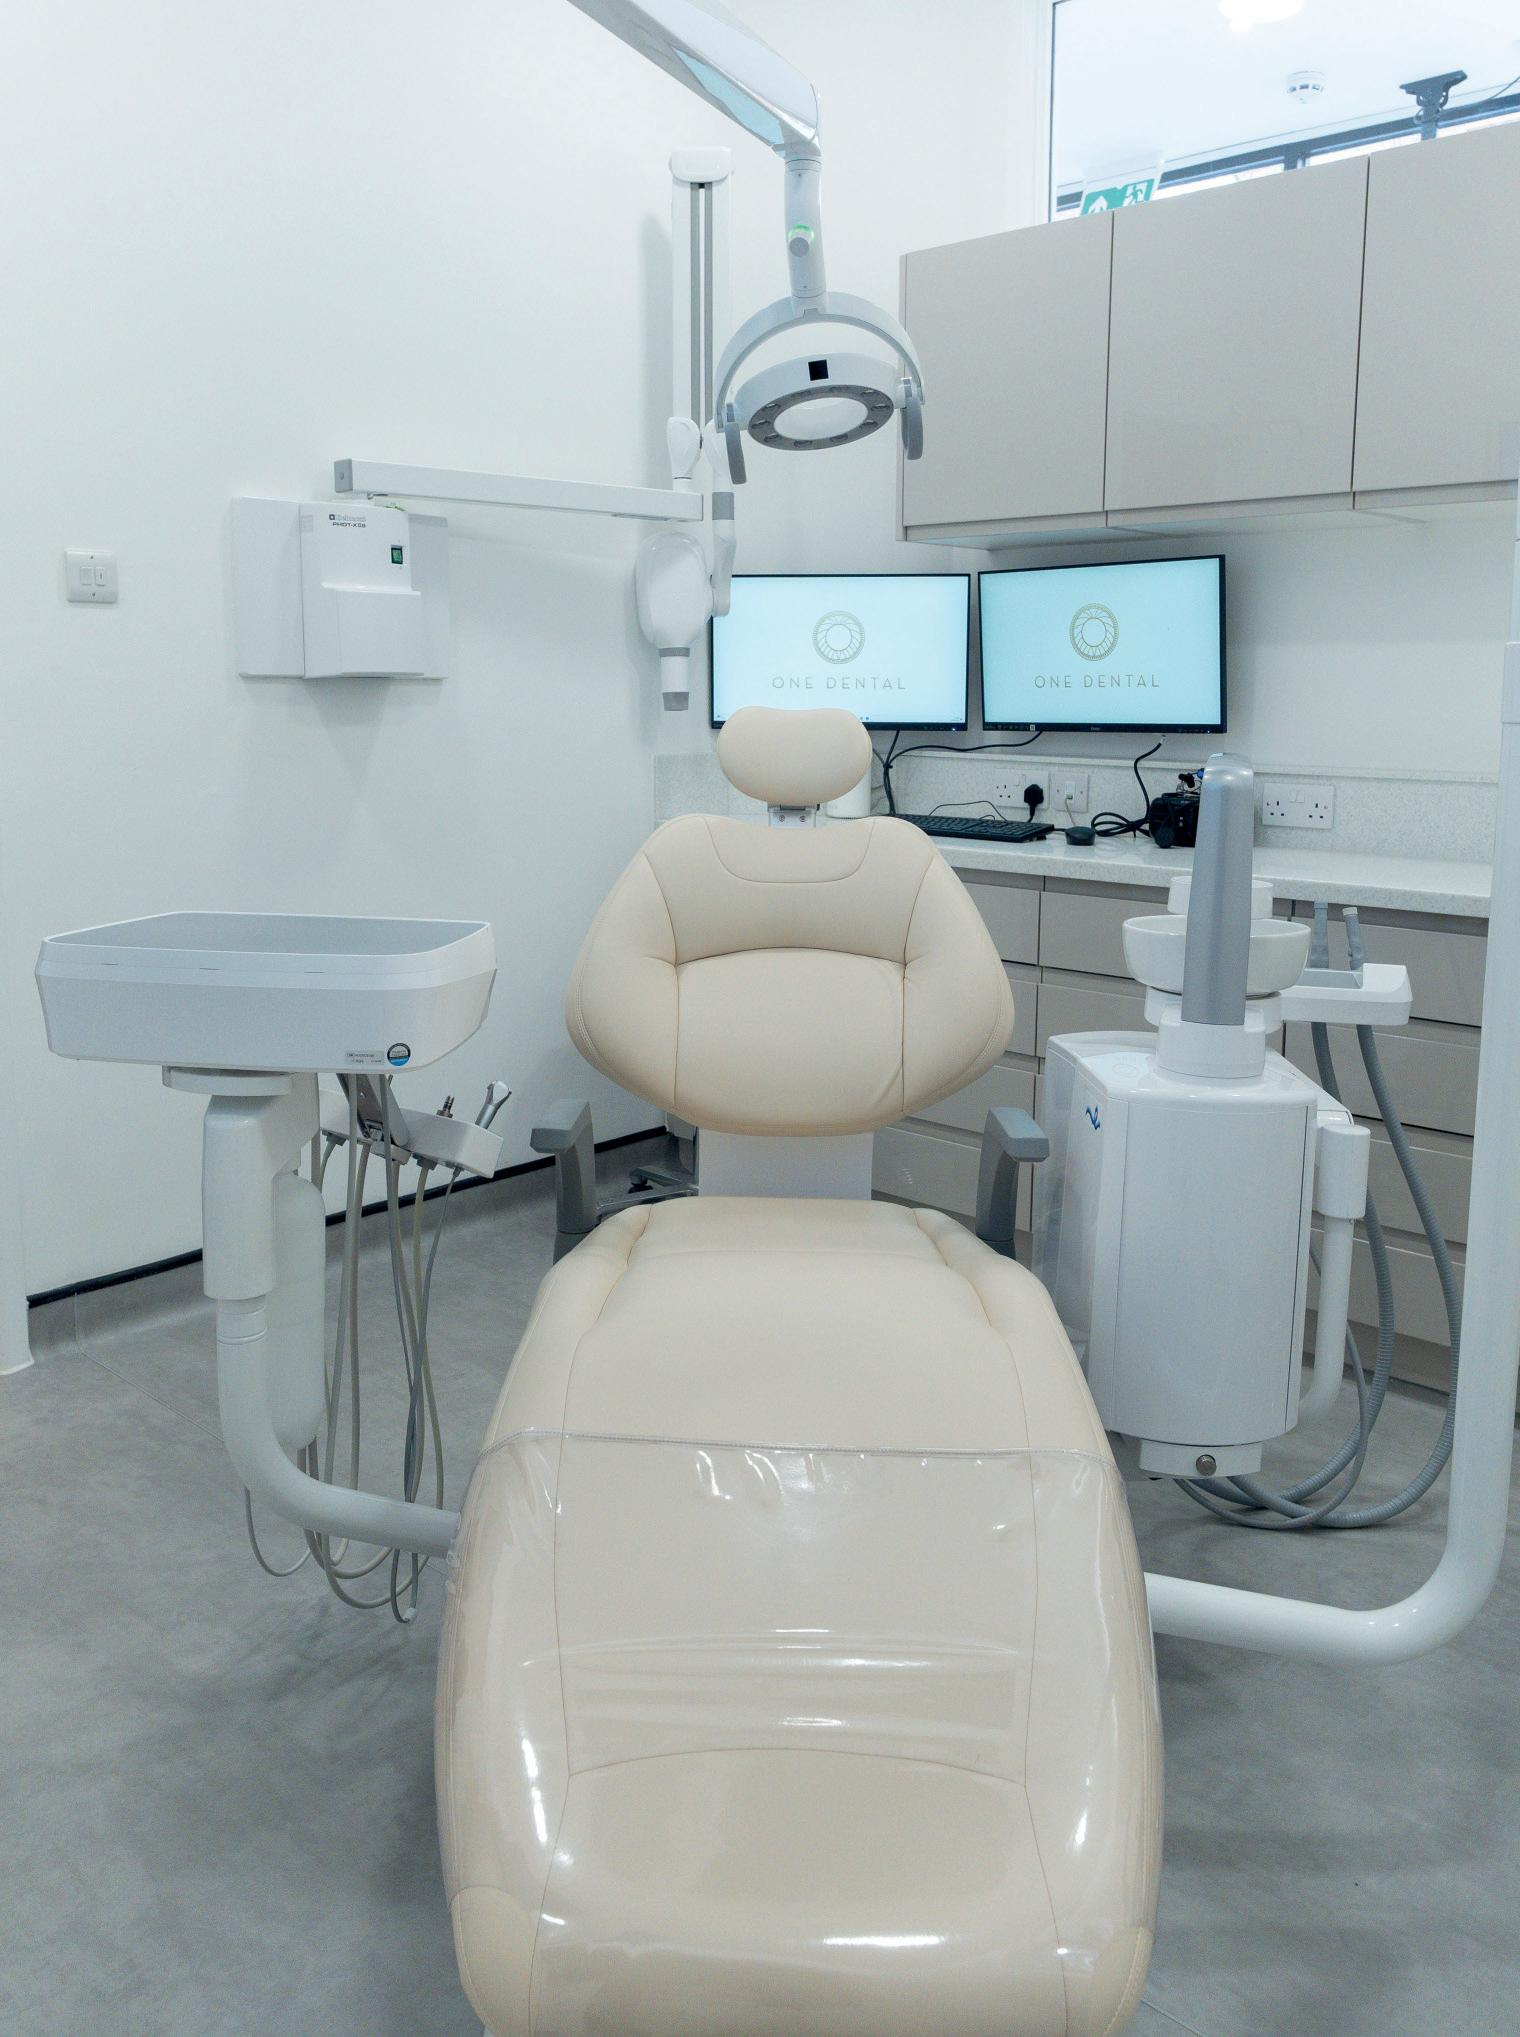
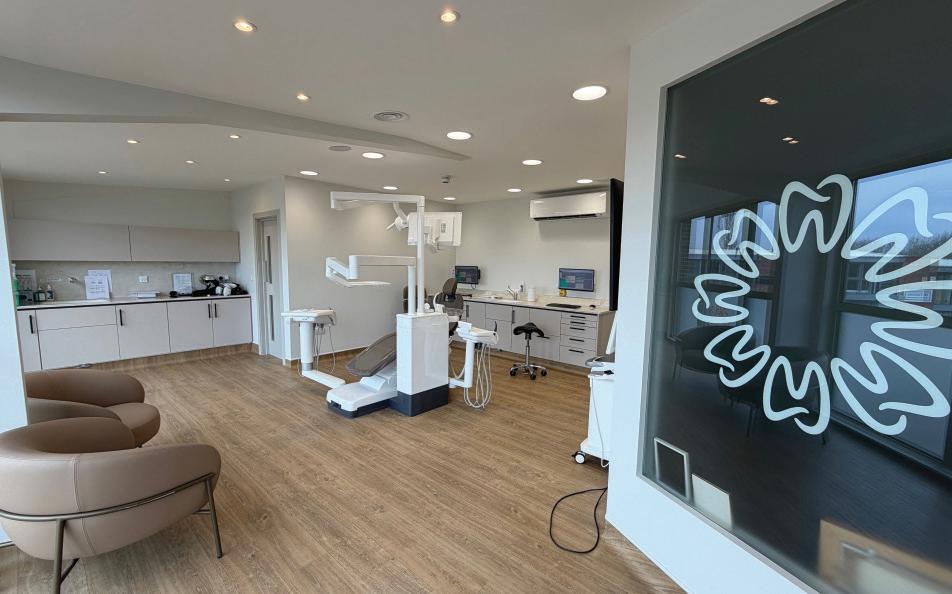
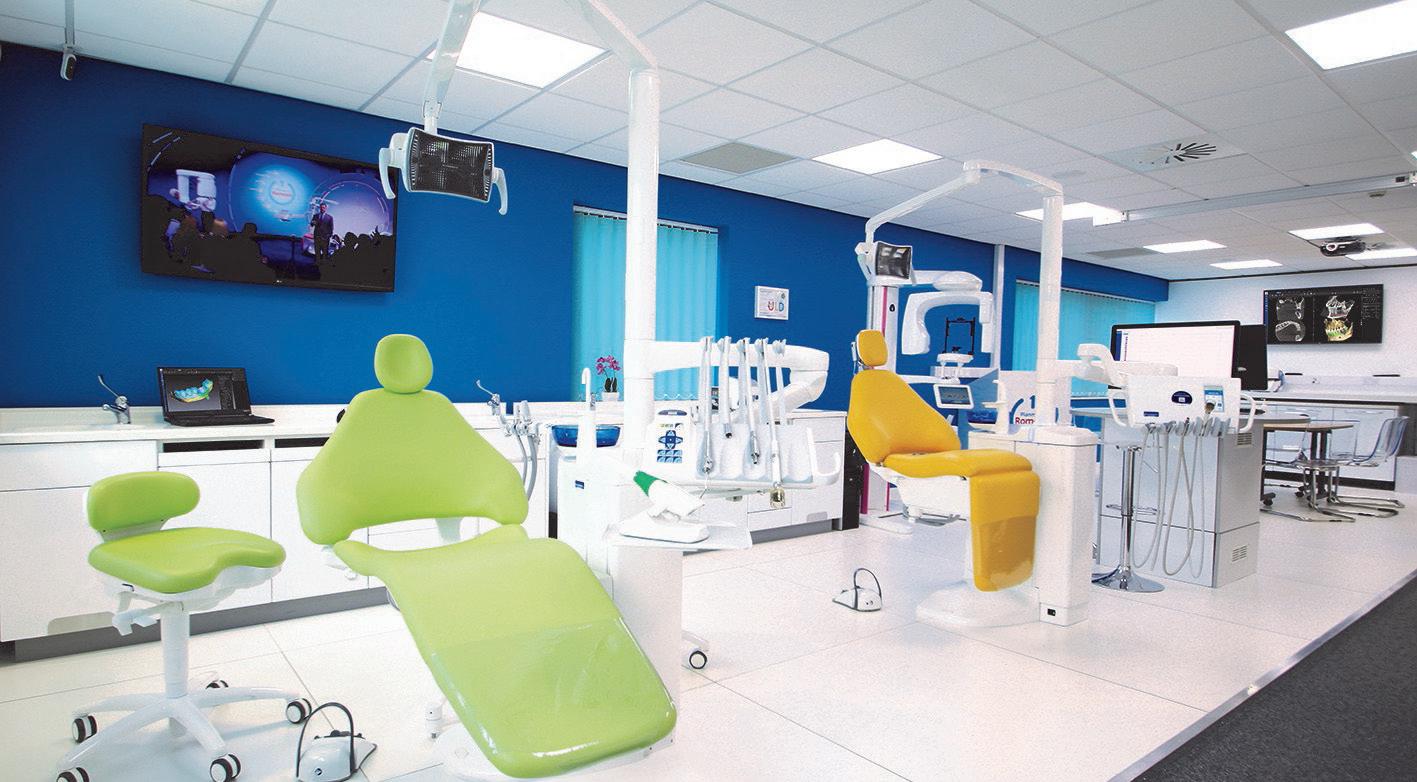
The Kensington clinic features three modern surgeries, designed with the same meticulous attention to detail that defines One Dental. Every element of the space was carefully considered to create an atmosphere that feels luxurious and calming.
The practice concept itself was developed from the ground up by the pair, working closely with designers and contractors to bring their vision to life. When challenges arose, they remained hands-on, ensuring the result reflected exactly what they had imagined.
Their design priorities were clear: create a space that reflects clinical excellence while helping patients feel completely relaxed.
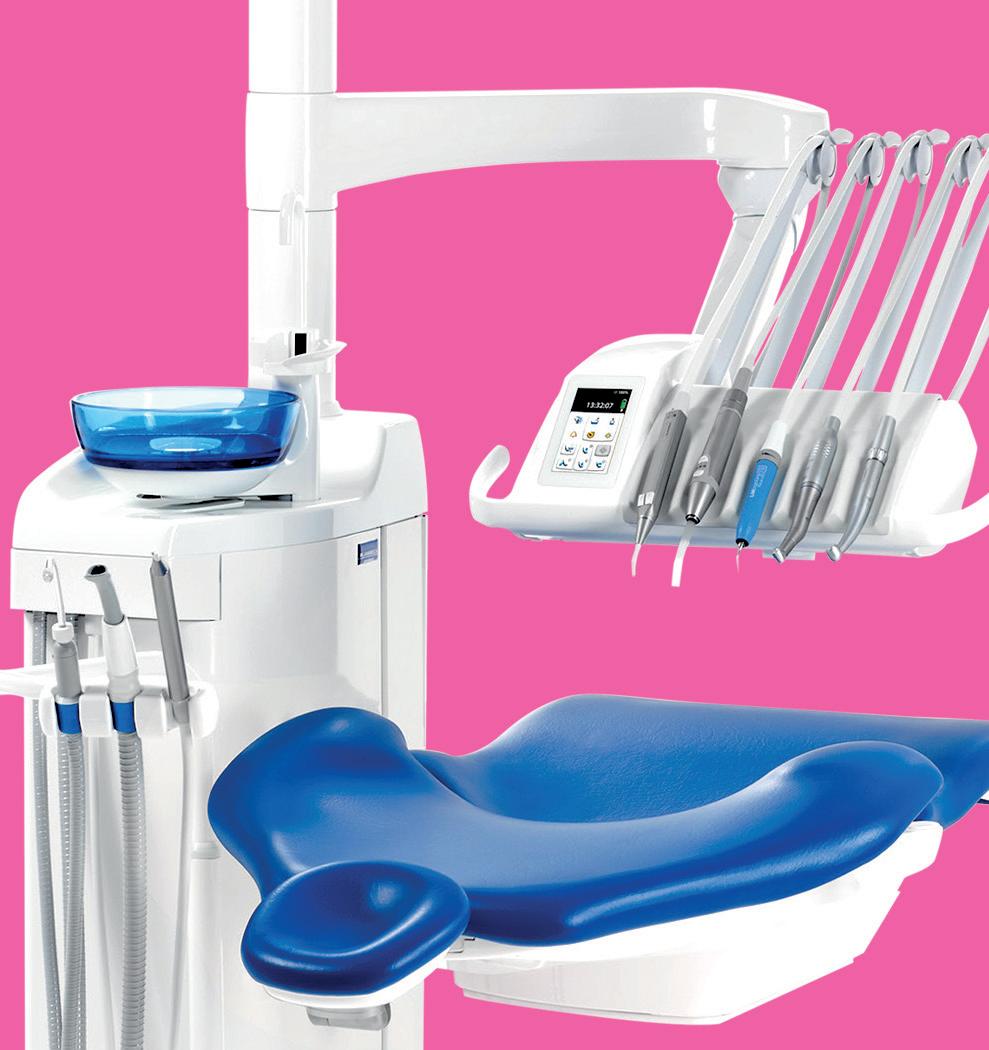
This attention to detail extends to the technology used throughout the clinic. Belmont Eurus S8 treatment centres were chosen for their ergonomic design, exceptional comfort and sleek aesthetic.
‘It combines comfort, functionality, and elegance. ‘Patients often comment on how relaxed they feel –we’ve even had patients fall asleep during treatment, which is always a good sign!’ Patient feedback across both locations consistently reflects the team’s efforts.
Reviews frequently highlight the calm environment, attention to detail, and the sense that patient care is genuinely prioritised. Words such as ‘exceptional’, ‘precise’, and ‘reassuring’ appear time and again, reinforcing the ethos upon which One Dental was built.
The Google reviews are consistently positive.
‘The standard of care was exceptional,’ writes one. ‘Thorough, precise, and clearly rooted in real expertise. You can tell this is a practice that sweats the details. The clinic itself is spotless, modern, and reassuringly well organised. Appointments run on time, communication is excellent, and there’s a real sense that patient experience actually matters here (a rare thing).’
For Deep and Lumini, these responses validate their core philosophy. And they have worked hard to capture this so-called ‘rare thing’. For them, perfection lies in the footnotes and is something they value and nurture.
‘We go into the clinic every day to perform treatments that can truly change lives. We believe in listening carefully, understanding each patient’s concerns and goals, and creating tailored treatment plans that reflect their individual needs. No two patients are the same, and their care should reflect that.’
Opening a second practice brought opportunity, but with this came inevitable challenges. Expanding so soon required resilience, trust in their team and absolute clarity in their vision.
‘It was a significant step, but we are incredibly grateful to our teams, whose dedication makes everything possible. Their commitment to our patients and to our shared values is what allows One Dental to grow while maintaining the standards we believe in.’
Expanding with a second practice is ‘more than just a new business chapter’. Deep says: ‘It’s a deep dive into broadening our trusted and considered, patient-centred care.’ n
Lumini Gamage and Deep patel
How two practices became one
newly designed, multi-surgery
For 15 years, I have delivered treatments from my private dental practice based in Buckingham. Before this year, I owned two practices: Meadow Walk Dental Practice and The Gallery Dental and Implant Centre.
Despite being only a few minutes’ walk away, the inconvenience of separate buildings and having to send patients to and from each practice demanded a smoother, more long-term solution. This was the motivation for combining the two practices into one space – superior patient service, built on comfort, advanced technology and the ability to deliver excellent dental treatments. It would also improve the daily workflow for my clinical and non-clinical colleagues.
Starting from scratch
The new practice was built on space that I had purchased in 2020. As the lease on the previous two practices was due to run out in April 2026, I was ready to begin the project so that it would be completed before this deadline, allowing a seamless changeover with minimal financial cost.
I had a blank canvas to work with; the new building comprised two empty floors so I searched for a team to help. Finding an experienced architect in the dental field and getting planning permission was the initial hurdle – I ended up needing two architects to get the plan we wanted without any uncertainty, and received the necessary planning permission. Once achieved, it became a matter of identifying what I wanted and what I needed in the practice, and what would be achievable. The process was very collaborative, with many team discussions to ensure every box was being ticked as we went.
A bank loan helped get the project moving, and they provided great support – no financial adviser was needed. Looking back, I would have liked a project manager from the beginning to marshal the process, but I had ruled it out due to the additional cost. Some members of the dental team decided that they wouldn’t continue working with us as we transitioned into a new space, leading to some staff turnover. Whilst this was unfortunate, it was important that we made this move for the sake of an improved patient journey. The décor and furnishings we selected reflect a state-of-theart dental practice, where patients enter the space and feel that they are in trustworthy hands. This meant creating a comforting aesthetic which incorporated advanced technologies, demonstrating that the practice was cutting-edge.
essential support
I used Clark Dental to help with installing and servicing our new equipment. This included an Axano treatment centre, which I use in my treatment room. It is a beautiful chair that optimises patient comfort. The implant functions and further attachments are top of the range.
For the other treatment rooms, Clark Dental were a massive help and provided three Intego treatment centres too. These integrate seamlessly with the dental treatment rooms and are remarkably effective and of a high quality. From a patient’s perspective, they are slim and stylish, therefore further reflecting the practice’s modern image.
For the X-rays, I favoured the Dentsply Sirona Heliodent as it offers the most accurate and clear images possible to enhance diagnostics. Clark Dental also supplied a Cocoon X-ray which is a fantastic addition because it is portable and user-friendly. Patients love it too; there is no need to leave them alone for a scan and it impresses them that it acts like a camera – it is very simple but very sophisticated and undoubtedly streamlines the workflow.
The practice also features a CBCT X-ray machine. This has been used for some time because we focus on dental implants and it simplifies our workflow – the Clark Dental team were a great help in moving this across. Finally, the CEREC Primescan was also brought over as this was a practice staple and facilitates a fully digital treatment service. There were a few issues with moving dates – it had to be done here and there over the course of 5 days – but the Clark Dental team was very approachable and the servicing of the products in the new practice was reliably excellent. Matt Rowlingson and the Clark Dental engineering team were invaluable for the completion of the project.
Open for business
To announce the new practice, we started with a couple of Open Days. Originally, we had 200 people apply to visit, but we limited it to 50 to keep things steady and not take on more than we were ready for. There was a word-of-mouth element to begin with as we did not embark on a major marketing push outside of social media and are instead concentrating on getting up and running and tackling small issues for a seamless daily operation.
Since opening, the impact of the new practice has transformed the workflow. The discontinuity in patient care
from having split practices is gone and communication is far more effective and streamlined. The addition of the car park, including a disabled car park with disabled access, has also addressed patient challenges and they, and the staff, have been happy with the improved accessibility.
So far, I have been delighted with the reactions to the new practice. The higher levels of patient satisfaction have reinforced the original motivation for changing practices and it already feels like a massive positive difference has been made.
The consistent support Clark Dental provided to my colleagues and patients throughout this journey has been unrivalled. With first-class dental equipment in place, I look forward to delivering even better patient experiences at The Gallery Dental & Implant Centre.
For more information call Clark Dental on 01268 733 146, email info@clarkdental.co.uk or visit www.clarkdental.co.uk n
about the author
Dr Selvaraj Balaji worked in Maxillofacial units in the UK for many years and gained substantial experience in surgical dentistry. He is the principal dentist of the Gallery Dental & implant centre. Dr Balaji is also the founder of the academy of Soft and Hard tissue augmentation (aSHa) and runs courses, lectures and study clubs in the UK and around europe for aspiring implantologists.
Dr Selvaraj Balaji details the consolidation of his two practices into one
practice: The Gallery Dental & Implant Centre in Buckingham
Discover how we’ve made a 30 year best-seller even better
Find out more - make an appointment to view in our London or Manchester showrooms
Perfecting the art of dentistry
Calm, comfort and care – managing dental anxiety
It is estimated that more than half of the UK population suffer from dental fear or anxiety. The latest Adult Oral Health Survey found that approximately 42% of participants had moderate dental anxiety, while a further 12% reported an extreme fear or phobia. More serious concerns were more likely among younger individuals (under 55), females, and those from lower-income households.
All of this means that every dental professional will regularly encounter patients who are hesitant to enter the surgery, sit in the chair, or undergo treatment. As such, it is important to recognise the issue and provide the support patients may need to manage their feelings and encourage access to care.
Understanding where it comes from Several potential causes of dental anxiety have been identified in the literature. With a complex and multifactorial aetiology, dental fear is often developed in childhood and carried through to adulthood. This may be a learned behaviour from anxious parents, or the result of personal experiences in the practice. Previous traumatic experiences with a dentist, regardless of age, are a significant indicator of dental phobia. In addition, personality traits like neuroticism and low extraversion are associated with an increased likelihood of dental fear, as affected people are usually prone to general anxiety and self-consciousness. Finally, cognitive ability plays a role too. Children with higher intelligence quotients exhibit less anxiety during their first dental visit than those with lower cognitive ability.
creating a safe space
For dental professionals, the first step in supporting anxious patients is acknowledging their fear. While it may be an obvious barrier for some people, others may take steps to hide their feelings out of fear of embarrassment or judgement. Even worse, many truly phobic patients may avoid dental care altogether, which will have a detrimental impact on their oral and systemic health in the long-term.
It is the role of the entire dental team to create a space where patients feel safe enough to share their concerns and ask for the additional support they need to seek dental care. This might begin with a simple questionnaire for new patients to complete before even setting foot in the practice. A small yet powerful addition to the new patient consultation documents, this could immediately identify individuals who have additional needs and show them that you take their anxiety seriously from the outset. It is also important to regularly communicate about services available specifically to help anxious patients in newsletters, on the website, and on social media.
Management techniques
Once dental anxiety or fear has been identified, pre-determined measures should be implemented to support that patient. Simple ideas like offering the first appointment of the day to minimise waiting can make a big difference. Some individuals might appreciate being greeted at the door by the dentist or dental nurse. It could also prove useful to make sure fearful individuals always see the same clinical team to avoid exacerbating anxieties by constantly introducing new professional team members.
Dentists also have access to an array of tools to aid the delivery of dental care. One systematic review found merit in distraction therapies that used music, virtual reality technologies, or hypnosis. These help to mask stimuli often associated with negative emotions; hiding the sounds of the dental drill, for instance. Aromatherapy may also be useful in encouraging relaxation and creating a more pleasant dental environment. Another adjunctive therapy that has shown initial promise in the research for reducing anxiety is acupuncture. A useful technique for any anxiety disorders, it offers a safe and cheap solution to help patients relax in the dental chair. There is also initial evidence suggesting that dog-assisted therapy can be effective for anxious children visiting the dental practice. Though a little more difficult to implement for most modern dental providers, it is food for thought for the future of dental care.
a smooth experience for all
Aside from specific techniques to identify and help manage patient anxieties, it is important to deliver an efficient overall patient experience. All visitors to the practice will appreciate – and expect – a warm greeting from the team, appointment punctuality, and high-quality dental treatment. For nervous patients, a smooth, well-coordinated workflow that promotes comfort and minimises unexpected disruptions or lastminute changes will be especially important. To ensure you can provide the most predictable outcomes in comfortable facilities, your practice design is key. For expert help in assessing your current setup, finding new equipment to elevate your
patient care, and ongoing technical support, look no further than Dental Directory. We offer thousands of cutting-edge innovations and industry-leading products that enable exceptional dental care and superior productivity, complemented by comprehensive equipment installation and maintenance services.
Quality care comes first
Dental anxiety and fear are common across the globe, with dental professionals likely to encounter affected patients in the UK on a daily basis. A complex issue, it requires a multifactorial approach to help individuals manage their symptoms. With proven adjunctive therapies, an empathetic professional team, high-quality dental procedures, and a smooth treatment experience, nervous patients can be effectively supported to better oral and general health. For more information on the products and maintenance services available from Dental Directory, please visit ddgroup.com or call 0800 585 586 n
about the author Dean Hallows, Managing Director of Dental Directory.
Protecting antimicrobial efficacy
Antimicrobial resistance can affect a wide range of organisms, including bacteria, viruses, fungi, and parasites, which are usually treated with antibiotics, antivirals, antifungals, and antiparasitics respectively. There are a number of factors thought to accelerate antimicrobial resistance, including the inappropriate use of antimicrobial drugs and poor infection prevention and control practices.
Dental practitioners must remain abreast of the latest news regarding antimicrobial resistance in order to minimise the risks for their patients, and the wider public.
antimicrobials in dentistry
Antimicrobial resistance is a growing global issue, including within dentistry, which accounts for around 10% of all antibiotic prescriptions in UK primary care. As mentioned, inappropriate use of antibiotics is a significant contributor to resistance, and there has been evidence of this in dentistry. Irresponsible use encompasses a variety of instances:
• Prescribing without infection or where local measures would be sufficient
• Prescribing prophylactically without indication
• Using incorrect dose or treatment duration
• Use of wrong antimicrobial for the type of infection
• Not adjusting treatment when culture data made available
• Administering with IV when oral not appropriate
• Choosing incorrect medicine for patients with an allergy
In situations where they’re generally accepted to be indicated – as an adjunct to manage infections, where final treatment must be delayed, or to prevent infections associated with specific dental treatments – safe and effective use of antimicrobials is paramount. This means prescribing the right medicine for the right clinical indication at the right time, dose, and route with minimal risk of resistance for the patient and future patients.
What are the risks?
Antimicrobial resistance puts public health at risk as it undermines the efficacy of commonly used medicine – not just for individuals, but for the population in general. The UK government commissioned a review that found antimicrobial resistance may kill 10 million people per year by 2050 –stressing the important role that individuals and the wider profession can play now to prevent further instances of this. If resistance keeps rising, and infections become more difficult to treat, more people will be sicker for longer. Ultimately, this results in longer hospital stays, routine surgery becoming more dangerous, and death rates rising as predicted. Therefore, the impact of antimicrobial resistance is large and wide
reaching – having a detrimental effect on dentistry and healthcare as we know it.
enhanced infection control protocols for improved safety
When addressing antimicrobial resistance, infection control is critical. Preventing infection transmission reduces the need for antibiotics, in turn preventing the development and spread of resistant bacteria.
By implementing effective infection control in the practice, dental professionals, their teams, and their patients can help to break the chain of infection. The chain of infection has multiple stages: infectious agent, reservoir, portal of exit, mode of transmission, portal of entry, and susceptible host. There are a number of points in this cycle at which the chain of transmission could be interrupted – stopping or slowing the spread of infection. These include hand hygiene, wearing appropriate PPE, decontamination of instruments and equipment in between patients, cleaning the environment, isolating infected patients, and safe handling of food, water, linens, and sharps. If at least one of these actions are taken to break the chain, the infection will be prevented from spreading further. For the best outcomes, these actions should be targeted depending on the specific organism or environment.
In order to stop the spread of infection between patients in the dental practice, high quality
instrument sterilisation is vital. Eschmann has been designing and manufacturing autoclaves for more than 60 years. The modern range includes the Little Sister SES 3020B vacuum autoclave, which offers a 23-litre capacity, and a choice of both ‘B’ and ‘N’ type cycles to accommodate every type of instrument and load. It also has multiple microprocessors that independently control and verify each cycle, giving you peace of mind that your instruments are being sterilised effectively.
Antimicrobial resistance presents a unique risk, which makes correct prescribing and effective infection control absolutely essential. By preventing the spread of infection within dental settings, fewer patients will require antibiotics to treat them, and resistant bacteria will be less likely develop and spread. By breaking the chain of infection, dental professionals and their wider team can play their role in keeping their patients, the public, and themselves safer.
For more information on the highly effective range of infection control products from Eschmann, please visit eschmann.co.uk or call 01903 753322 n
about the author
Nicky Varney, Head of Marketing at eschmann.
WHEN SIMPLICITY MEETS POWER
CHIROPRO PLUS
defines the CHIROPRO implantology systems, they are undoubtedly two of the most powerful systems on the market. In other words, it means that you get the best of Bien-Air: their user-friendly design, combined with Bien-Air technology ensures uncompromising power with unmatched simplicity, making it an ideal choice for implantologists.
There’s something in the water
Snaking in and around dental chairs, dental unit waterlines (DUWLs) are the arteries of every practice, delivering essential water to handpieces and scalers and enabling a consistent number of patients to be treated every day. Because of their importance, diligent maintenance is required to keep them functional – and safe.
Waterborne pathogens can be acquired through unclean drinking water, from contact with animals or their environment, or through person-to-person transmission. In the dental practice, contaminated DUWLs can release pathogens directly to patients through inhalation or wounds, increasing the risk of infection. But research has also found a potential association between DUWL contamination, respiratory illness and the perceived risk for dental professionals. A deeper understanding is needed to better protect members of the dental team.
perilous pathogens
Most of the organisms isolated from DUWL are of low pathogenicity. However, a few of the most common waterborne microorganisms that can cause illness include:
• Legionella
• E.coli
• Campylobacter
• Salmonella
• Pseudomonas aerugunosa
• Giardia
• Cryptosporidium
With a reported prevalence between 0-68%, legionella is notable and varies wildly in DUWLs. It grows at temperatures of 25-50 degrees Celsius, especially in stagnant water, and can cause the form of pneumonia known as Legionnaire’s disease – it has been frequently evaluated for its role in infecting dental professionals.
identifying the source
Microbial contamination in DUWLs may originate from both waterborne pathogens but also germs from a patient’s oral cavity due to the suck-back of saliva. In cases of the latter, microbes like Porphyromonas gingivalis, which increases the build-up of bacterial plaque, can enter the water supply. Similarly, dental turbines operate with fast rotations; when slowing down the tip of the instrument draws organic material from the oral cavity inside, creating back-contamination. Whilst handpieces may feature anti-retraction valves, there can on occasion be failure, and these fluids may be sprayed onto the next patient’s oral mucosae, even if the handpiece has been replaced.
Even with comprehensive sterilisation of the handpieces, the dental unit will still be a source of pathogens if connected to a contaminated water supply. The undisturbed existence of pathogens in a DUWL leads to the formation of biofilm on the interior surface of the pipes. This is a universal problem; bacteria adhere to the surface of a substrate and are able to
maintain a stable synergy among different species of microorganisms, whilst also becoming resistant to biocidal agents that is 2-3 orders of magnitude greater than that of non-adherent microbial cells – this demands tough decontamination action.
The dominant species isolated from DUWLs are Gram-negative bacteria; these are among the world’s most significant public health problems because of their ability to resist antibiotics, leading to a heightened risk of morbidity and mortality. Respiratory complications, such as asthma and Legionnaire’s disease, can be triggered or exacerbated by the production of cell wall endotoxins, of which Gram-negative bacteria is a potent source. This is the occupational risk that dental professionals face if DUWLs are not regularly decontaminated, as the resulting bacteria can spread through the air –patients are at a much lower risk. It has been further reported that higher rates of Legionella antibodies have been found among dental personnel than among the general public.
prevention first
More than 81 million people in Europe are affected by chronic respiratory diseases, the sixth leading cause of death. It is therefore paramount that correct decontamination protocols are followed to reduce the risk of respiratory diseases, protecting both patients and the dental professionals who are more consistently exposed to pathogenic transmissions.
Among the recommended practices are anti-stagnation practices to keep water circulation constant, manually flushing through all devices and instruments connected to a waterline before use, and disinfecting the water through both continuous and discontinuous treatments. The combined effect of these protocols prevents biofilm formation and the subsequent risk of infection transmission.
ready for action
A reliable solution for water maintenance is Bioclear Daily from Dentisan. Reducing the planktonic bacteria count in water flowing through the dental unit, it is designed for daily use to disrupt biofilm formation and maintain water quality to the HTM 01-05 standard. Able to be diluted and readied in advance, prepared solutions can keep for up to 10 days in suitable plastic containers for ease of use. Ensure compliance and prevent the risk of infection with the help of Dentisan.
The association between contaminated DUWLs and the risk of respiratory illness is an alarming occupational hazard for dental professionals. An effective decontamination workflow that regularly prevents pathogen build-up keeps the dental team safe from infectious diseases for a consistent, uninterrupted working environment.
For more information about Dentisan, please visit https://dentisan.co.uk/ n
about the author
Jenny Nixon, Business Development, Dentisan.
One of the many challenges faced throughout healthcare today is the management of antimicrobial resistance (AMR). The term refers to the emergence of pathogens that no longer respond to antibiotics, antifungals, antivirals, and antiparasitics, creating genuine concerns about the efficacy of treatment across a broad spectrum of health conditions. The problem requires a collective response from professionals in dental, medical, agricultural, food, and many other industries, as well as the general public.
a growing problem
AMR occurs naturally, as pathogens evolve to overcome the effects of antibiotics over time, rendering medications useless against various illnesses. However, the issue is being accelerated by a number of human behaviours, like misuse of antibiotics. Improper use or overconsumption of related medications in human and animal sectors is providing an opportunity for pathogens to adapt more quickly than they otherwise would. This, combined with environmental, social, medicinal, health, climatic, and economic factors, is driving the emergence of new resistant pathogens. Consequently, AMR has become a major threat to public health around the globe, contributing to an estimated 35,200 deaths every year in the UK alone. In 2023, approximately 66,720 serious antibiotic resistant infections were recorded across the nation, representing a 7% increase from 62,300 in 2019.
The same government report found that one of the main causes of antibiotic resistant bloodstream infections was E. coli; responsible for around 65% of related infections in 2018-23.
Worryingly, the research also identified a widening gap between those living in the most and least deprived areas of society with regards to the risk of acquiring an antibiotic resistant infection. In fact, people living in the former regions in 2023 were more than 42% more likely to experience an antibiotic resistant infection – which represented a significant rise from 30% in 2019. This adds to the already stark data showing that those living in the 20% most deprived areas of England are twice as likely to be admitted to hospital than those from the least deprived locations.
a nationwide mandate
A growing threat to modern medicine about
The big concern about AMR is that infections which have been easily treatable for decades will become incurable, putting millions of people worldwide at significant health risks. In 2019, the UK government published “The UK’s 20-year vision for antimicrobial resistance”, which aims to guide a collaborative effort across the nation to effectively contain, control, and mitigate the development of further AMR. It lays out a plan to reduce the burden of infection on the NHS, to encourage optimal use of antimicrobials, and to support new diagnostics, therapies, and vaccines to facilitate infection prevention across the board. It suggests that at least 20% of all antibiotic prescriptions in primary
care are inappropriate, which highlights a key area that we as healthcare professionals should take note of.
To make change more manageable, the government created four 5-year action plans to guide the two-decade mandate. “Confronting antimicrobial resistance 2024 to 2029” is focused on four key themes: reducing the need for, and unintentional exposure to, antimicrobials; optimising the use of antimicrobials; investing in innovation, supply, and access; and being a good global partner. Of relevance to dental professionals is the spotlight on antimicrobial stewardship and disposal, promoting appropriate prescription and use of medications.
the dental contribution
These are crucial aspects of the dental professional’s role today. We should all carefully consider when and why we prescribe antimicrobials to our patients. They remain an important adjunctive therapy to prevent or treat oral infection, but we have a responsibility to use them only when clinically indicated. The Faculty of General Dental Practice and Faculty of Dental Surgery have produced a useful document that outlines current research in the field and offers authoritative guidance to aid clinicians’ decision-making. It summarises the evidence for antimicrobial use in various situations, from endodontics to periodontology, chronic infections, dry socket, prophylaxis, and more.
Also within our remit is patient education on the topic. Research suggests that some confusion remains among the general public with regards to the morality of antimicrobial consumption when not required. There is also a lack of understanding about how personal actions contribute to the broader AMR challenge. The complex nature of the issue means that educating patients can be difficult in itself, but it is important that we try. Building rapport with patients is beneficial, as is the use of specially designed toolkits, such as those provided by the UK government.
time for action
Ultimately, it is for everyone to take action against antimicrobial resistance if we are to successfully protect the future health of the global population. It begins with small steps taken by individuals, which centre around appropriate use of the drugs.
For further information about the endodontic referral services available from EndoCare, please call 020 7224 0999 or visit the NEW website endocare.co.uk n
the author
Dr Michael Sultan, endocare clinical Director.
OPTIONAL EXTRA
Sound reducing cover
Reduces noise levels from 64-71dB(A) to 63-68.5dB(A)
Annual Service Contracts from as little
In today’s fast-paced dental environment, reliability is everything. From chair packages and decontamination equipment to compressors and X-ray systems, every aspect of a practice depends on equipment operating safely, efficiently, and without interruption.
Annual Service Contracts provide dental practices with a proactive, structured approach to equipment maintenance, helping to minimise downtime, control costs, and protect both patient experience and regulatory compliance.
Rather than reacting to equipment failures as they arise, preventative maintenance focuses on identifying and resolving issues before they become costly problems. Dental equipment is subject to constant daily use, and even the highest-quality systems naturally experience wear over time. Without routine servicing, minor faults can quickly escalate into significant breakdowns, resulting in cancelled appointments, operational disruption, and reputational damage.
An Annual Service Contract (ASC) offers a practical and cost-effective solution by spreading servicing costs into manageable monthly payments while ensuring equipment receives scheduled maintenance in accordance with manufacturer recommendations and industry standards. In addition, practices may choose to upgrade to an Annual Service and Repair Contract (ASRC), which combines preventative maintenance with reactive repair support for even greater peace of mind.
Beyond planned servicing, contract customers benefit from a range of additional advantages, including:
• Priority response for reactive call-outs
• Dedicated account management support
• 10% discount on additional call-out and labour charges
• 10% discount on parts for ASRC customers
• Maintenance and operational guidance for practice teams
single surgery plans – from £56.00 + Vat per month
Sign up for a typical single surgery ASC from as little as £ 56.00 + VAT per month, covering a chair package, intraoral X-ray, and suction pump, including comprehensive servicing tailored to the specific maintenance requirements of each item of equipment.
Practices seeking additional protection can upgrade to an Annual Service and Repair Contract (ASRC) from as little as £87.00 + VAT per month. In addition to all ASC benefits, the ASRC includes up to three reactive visits per annum, inclusive of call-out, parking, tolls, and up to two hours’ labour per visit.
dental Chair package
Our chair package servicing goes beyond a standard mechanical and electrical inspection. Using genuine manufacturer service kits, preventative maintenance includes the replacement of high-wear consumable components such as seals, filters, diaphragms, valves, and O-rings within the delivery unit, foot control, and air/water syringe assemblies. Replacing these components at scheduled intervals helps reduce the risk of leaks, maintain reliable functionality, and prolong the operational lifespan of the chair.
intra-Oral X-ray systems
Wall-mounted intra-oral X-ray systems are mechanically and electrically serviced during years one and two, with all operational functions checked and certified as safe and effective. During year three, a routine survey (commonly referred to as a critical examination) is completed. Critical examinations are also required following installation, relocation, or major repair work. Handheld X-ray units require an annual critical examination.
suction pumps
Selected suction pump manufacturers also allow for remote monitoring support.
Routine servicing typically includes the use of genuine manufacturer service kits, replacement of seals, filters, and O-rings, leak and flow testing, and amalgam separator replacement where applicable (amalgam must legally be segregated from general or clinical waste streams and processed through specialised recovery systems).
autoclave service plans – from £50.00 + Vat per month
All decontamination equipment should be validated, tested, maintained, and serviced in accordance with manufacturer guidance, HTM 01-05 recommendations, Care Quality Commission (CQC) expectations, and PUWER regulations.
A standard autoclave annual service typically includes replacement of key wear-and-tear components exposed to repeated heat and pressure cycles, such as door gaskets, bacteriological filters,
dust filters. Services also include vacuum and leak testing, chamber cleaning, and completion of the annual PVI (Pressure Vessel Inspection), supported by certification documentation.
Where required, validation services and benchmark cycle servicing can also be incorporated into the plan, such as 4,000-cycle servicing for selected W&H autoclaves.
Compressor service plans –from £45.00 + Vat per month
It’s a legal requirement for dental air compressors to be serviced annually and undergo a PSI inspection in accordance with manufacturer recommendations to maintain performance, reliability, and longevity.
Our compressor servicing includes the use of genuine manufacturer service kits, replacement of intake filters and piston head gaskets, vessel draining, and inspection of the water bottle.
Dryer stack replacement can also be added in accordance with manufacturer schedules. Each service concludes with a PSI pressure test and inspection to confirm that the compressor can consistently maintain the required operating pressure and that no air leaks are present.
protecting Your practice
Ultimately, an annual service and maintenance contract is about far more than equipment servicing. It is an investment in operational continuity, regulatory compliance, financial predictability, and patient confidence. By combining preventative maintenance with expert technical support, dental practices can significantly reduce the likelihood of unexpected failures while ensuring equipment continues to perform at its best.
Work with hague dental
Hague Dental’s Specialist Engineering Division supports practices throughout the UK with manufacturer-trained engineers and a dedicated Customer Relations Hub, providing:
• Rapid servicing and repair support
• Automated service reminders and digital certification
• Expert preventative maintenance programmes
• Technical guidance aligned with HTM 01-05 requirements
Whether preparing for a CQC inspection, improving equipment reliability, or seeking a more cost-effective maintenance strategy, Hague Dental’s tailored service plans are designed to support modern dental practices with confidence. n
*Prices shown are illustrative and based on a single compressor including annual service and PSI inspection.
to arrange a complimentary service plan review or discuss your practice requirements, contact our Customer Relations hub today.
Clinically proven to get to work in under , relieving acute dental pain.4
TARGETED RELIEF
Benzocaine provides effective relief right at the source of dental pain.1-3
TRUSTED TOLERANCE
Orajel’s non-systemic formula is well-tolerated with minimal risk of side effects.1,2,4
The aesthetics expansion
Managing waste as your practice diversifies
Nearly one in four practitioners administering cosmetic injectables in the UK are dentists. 40–50% of private dental practices now offer facial aesthetic treatments. The reasons seem clear: declining NHS income, established patient relationships, existing facial anatomy expertise, and a market predicted to reach over £11 billion this year.
For practices making this transition, the clinical opportunities are substantial. However, expanding into facial aesthetics fundamentally changes your waste management needs, particularly when it comes to the disposal of sharps. Understanding these changes and implementing compliant workflows from the outset will help prevent any accidental regulatory breaches during a time of change.
Why are dental practices moving into facial aesthetics?
The move into facial aesthetics is a natural extension of a dental practice, as dentists have pre-existing, in-depth knowledge of facial anatomy and physiology, as well as experience in clinical workflows and patient care, with decontamination protocols already in place.
Financial pressures are also likely a factor. Mixed NHS-private practices face UDA constraints, and fully private practices may seek reliable, additional income streams. Aesthetic treatments offer high-margin procedures with repeat business, as patients require regular top-ups every 3–6 months, creating predictable income. Infrastructure is a big part of it: the physical clinical space, CQC registration, and many workflows and protocols already exist. Training courses can enable practitioners to build aesthetic services part-time while continuing to provide high-quality dental care.
transforming the waste profile
Dental sharps waste is straightforward once the appropriate workflows are established. Local anaesthetic cartridges, suture needles, disposable scalpels and blades can be managed routinely, with different coloured waste containers on hand to manage different hazards.
Aesthetic treatments, as could be expected, create an entirely different waste profile. Every dermal filler, collagen stimulator or skin booster syringe contains pharmaceutical residue. These sharps are contaminated with medicinal products and must therefore be segregated into yellow-lidded containers destined for incineration. Whilst botulinum toxin (Botox®, etc.) needles complicate things further, as these are known to be cytotoxic and must be segregated into a purple-lidded sharps container.
The volume of waste generated changes dramatically. A single aesthetic appointment may involve 20–40 injection points for botulinum toxin, or multiple syringes for dermal fillers. Compare this to occasional local anaesthetic injections during dental procedures.
Additionally, aesthetic procedures generate new waste streams: empty pharmaceutical vials, preparation syringes, and potentially cytotoxic waste if handling specialised treatments. Each requires appropriate segregation according to Health Technical Memorandum 07-01 (HTM 07-01) guidelines.
Understanding the colour code HTM 07-01 establishes the UK colourcoding system for the segregation of healthcare waste. For practices offering aesthetic treatments, understanding these distinctions prevents costly compliance failures and keeps clinicians, visitors and waste handlers safe. Commonly produced waste should be segregated as follows:
Yellow-lidded: All sharps containing, or contaminated with, medicinal products and chemicals, including dermal filler syringes, and any pharmaceutical injections. An infection risk may also be present. Yellow-stream waste requires incineration or alternative treatment at an authorised facility.
Orange-lidded: These containers remain appropriate for sharps waste without chemical or pharmaceutical contamination. Phlebotomy needles for blood tests, non-medicinal sharps, and some dental procedure waste. Orange stream waste can undergo alternative treatment, with incineration as a secondary option.
Purple-lidded: This stream applies exclusively to cytotoxic or cytostatic medicine contamination. While uncommon in standard dental aesthetics, when botulinum toxin (Botox®, etc.) is used, this becomes a must-have addition.
The colour code for clinical waste must be followed in both dental and aesthetic care. Every item entering an incorrect container creates waste stream contamination, potentially resulting in rejected collections, regulatory investigation, and re-classification costs.
Setting up your new sharps waste system
Deliberate waste management planning is key to successfully integrating aesthetics into the practice.
Separate treatment spaces and pointof-use containers: Position colour-coded sharps containers in treatment rooms at arm’s reach of the point of use. Separate spaces for treatments and their subsequent colour codes reduce cross contamination risks and remind staff of their different waste requirements.
Staff training: Every team member must understand the colour-coding system and pharmaceutical waste requirements. Ensure individuals are up to date with regular training.
Documentation protocols: Hazardous waste requires consignment notes tracking waste from the producer through collection to disposal. Maintain records for the mandatory three-year period.
Storage and audits: Segregate waste types safely in a secure storage space. Implement monthly checks ensuring containers are used correctly and documentation remains current, alongside regular audits depending on the volume of clinical waste produced, especially when the work completed in the practice changes significantly.
professional sharps waste management solutions
Practices expanding into facial aesthetics must find specialist waste management support that understands the specific requirements of clinical sharps disposal. Initial Medical provides comprehensive sharps waste solutions designed for healthcare settings, including UN-approved Eco Sharps Bins in multiple sizes and colours suitable for aesthetic treatment rooms, regular collection services with complete hazardous waste documentation support, and expert guidance on compliance for practices adding aesthetics to their services. Their containers are manufactured with at least 40% recycled plastic, providing sustainable disposal. Facial aesthetics could be a fantastic opportunity for dental practices to grow. However, clinical expansion must be matched by an evolution in waste management. With good systems in place, dental practices can confidently offer aesthetic treatments while protecting patients, staff, and practice reputation. To find out more, get in touch at 0808 304 7411 or visit the website today www.initial.co.uk/medical n
about the author rebecca Waters, Head of Marketing at rentokil initial.
INNOVATIVE, NOT COMPLICATED.
The heart of the A-dec® 300 Pro delivery is the new Dynamic Screen 5 (DS5), an interactive touchscreen that feels so intuitive, it’s almost like having your smart phone in the surgery.
Easy to navigate and view, the responsive 5” screen displays only the information you need in the moment, including procedural timers, chair positions, and on-screen messaging. It’s a smarter, simpler way to bring new confidence—and control—to your practice.
>> GET CONNECTED at
Prevention-first dentistry
Fighting oral disease is an ongoing battle. After cardiovascular disease and diabetes, oral diseases are the third most expensive conditions to treat and affect more than 3.5 billion people worldwide. The World Health Organization (WHO) began the Global Oral Health Action Plan in 2023, with 2030 as a target to provide universal oral health coverage for all people. Now halfway through the action plan, the need to reduce the prevalence of caries, periodontitis, oral cancers and edentulism is still urgent. Fortunately, there is a silver lining to managing oral diseases – most are preventable. This means patients can maintain healthier smiles for a long-lasting quality of life, but getting to this stage relies on three things: education, compliance, and the right oral hygiene solutions.
Reframe the patient’s perspective
Highlighting the power of prevention reframes a patient’s perspective, especially those who think oral health isn’t fully their own responsibility and dental practitioners will take care of all the problems in their mouth. Clear patient communication is therefore essential to achieve optimal hygiene outcomes, with particular focus on regular dental appointments, brushing twice a day and why it is important for the rest of the body. A useful analogy to help patients rethink oral hygiene is of buying a new car: if the car is not annually serviced then hidden problems will
exacerbate, leading to potential breakdown and a hefty repair job. This is why it is worth having a service, allowing professionals to spot potential risks and prevent further damage – a small payment that reduces the likelihood of a much larger bill down the line. Like a car, the teeth and gingivae need close attention to maintain aesthetic and functional outcomes and prevent invasive treatments such as tooth extraction.
Reduce treatment times
An important area to spotlight is posttreatment oral hygiene. Generally, patients do not want to return for timely and costly fixes and repairs and instead prefer a treatment that is long-lasting. But without a proper oral hygiene understanding, there is no long-lasting effect for any treatment; from inflamed gingivae to alveolar bone resorption, inadequate daily dental care leads to compromised tooth structures, edentulism, and then a returning trip to the dental practice. Preserving their recent dental treatment through diligent oral care can be a powerful motivator for patients. Emotion is an integral part of effective communication; logic justifies our actions but it is usually only applied after an emotional decision has been made. Finding an approach that emotionally resonates with each patient can lead to compliant preventive action. For instance, ask a patient to think about what their mouth is used for: eating, speaking, smiling, kissing,
humming, whistling – if they enjoy these actions, then looking after the mouth twice a day is a very small price to pay.
Another educational strategy that practitioners can empower their patients through is by detailing the knock-on effect of oral disease. Whilst a study found that 84% of patients know that oral health influences general wellbeing, the scientific explanations may be lesser understood. It is worth identifying that what is bad for the teeth is usually bad for the body, with a high consumption of sugary foods and acidic drinks increasing the risk of caries but also behavioural patterns, mental health disorders and systemic health conditions like obesity. If poor oral health influences general health, than it can have a larger impact on quality of life, family and, ultimately, society when the issues mount up. Far from a fearmongering technique, demonstrating this knock-on impact as a worst-case scenario for poor oral health contextualises the important role that toothbrushing and interdental cleaning play, beyond just keeping the teeth and gingivae stable.
Learn from the best
The iTOP programme from Curaden delivers a systemic approach to oral prophylaxis. More than just theory, iTOP is a practical journey designed to teach dental professionals worldwide how to transform oral hygiene practices and effectively coach patients toward
lifelong healthy habits. You’ll gain valuable insights into new tools and techniques that will not only improve your patients’ oral heath but also enhance their overall well-being. Prevention-first dentistry is the future, representing a proactive and logical way of reducing oral disease prevalence. Not only is prevention a more cost-effective solution to a restoration, it also encourages patients to think about the broader implications of their oral health and overall health. This maintains compliance and pushes us closer to achieving the target of universal oral health coverage.
For more information about iTOP courses and to book your place on one, please visit The Curaden Academy website: http://www.curadenacademy.com/
To arrange a Practice Educational Meeting with your Curaden Development Manager please email us on sales@curaden.co.uk
About the author
Andrew Turner, Curaden Head of Marketing, UK & Ireland.
The importance of conviction in communicating dental treatment plans
On a recent Ethical Sales & Communication Programme, we were talking about the importance of presenting treatment with conviction, especially when it was treatment that the patient requires for health purposes.
In the realm of dentistry, communication is as crucial as clinical expertise. I have spent 28 years training and coaching dental professionals to improve their communication skills, which results in an increase in case acceptance. Dentists and other clinicians are not only healthcare providers but also educators and advocates for their patients’ oral health. One of the most significant aspects of this role is explaining treatment plans to patients, particularly when these treatments are necessary for their health. Expressing these plans with conviction is essential for several reasons, as it directly impacts patient understanding, trust, and compliance. Here are three other advantages:
1. It builds trust and confidence
When you communicate with conviction, it instils confidence in your patients. Confidence is a cornerstone of trust, and trust is fundamental in the patient-dentist relationship. Patients are more likely to believe in the necessity of a treatment plan when their clinician speaks with assurance. Without doubt, this will lead to greater patient satisfaction and more loyal patients.
2. Enhancing patient understanding
Clear and confident communication helps ensure that patients fully understand their treatment options, the reasons behind them, and the expected outcomes. When a dentist explains a treatment plan with conviction, it reduces confusion. Patients are more likely to understand the importance of the treatment and how it will benefit their oral and overall health. This understanding is crucial for informed consent.
3. Encouraging patient compliance
When you present with conviction, you will significantly improve patient compliance. When patients perceive that a dental professional is knowledgeable and certain about the recommended course of action, they are more likely to follow through with the treatment and attend future appointments. This compliance is essential for achieving desired health outcomes and preventing further complications. It is a win-win. You get to deliver the dentistry that you want to do and the patients wins because they have better oral health. This also means that your patients require less treatment later in their lives.
My belief is that it is crucial that, if patient requires treatment that is going to benefit their lives, for example a visit to the dental hygienist if they have gum disease, it is crucial that you communicate this with conviction so that the patient can see the importance. Showing pictures and scans can obviously help.
I always remember my financial advisor once saying to me that he invests in the same funds that he was recommending. That gave me confidence in my decision. Saying something like, ‘If you were my mother, I would be advising you to get this treatment now,’ can have a huge effect. If you do not and the patient does not take your advice, not only do you lose, but the patient loses. However, the patient loses more, because down the line this treatment is going to get worse as it might mean more treatment at more expense.
It’s not just what you say that counts. It is also how you say it.
About the author
Over the last 28 years, Ashley Latter has delivered over 34,000 hours of Business Coaching to the Dental Industry all over the world.
Six NHS sites sold in four months.
Strategy beat exclusivity.
When John Gatus of PB Robinson brought Lily Head in to support the sale of a six-site NHS dental group, we opened the opportunity to the wider marketincreasing buyer reach, encouraging competition, and securing the right purchaser.
Lily Head understood both the business and us as individuals, and opened the opportunity up to the wider market, which ultimately difference.
John Gatus - P B Robinson
Lily
The evolution of crown materials in modern dentistry
Crown restorations have long held a pivotal role in restorative dentistry, with their ability to balance long-term function and aesthetics remarkably. Whilst their purpose has remained broadly the same over the years, the materials and technique have each evolved to match the changing patient expectations, gradually digitalising workflows, and advances in material science. Understanding the history and evolution behind these materials supports better treatment and understanding of the current landscape dental professionals now work within – continuously adapting to the new and ever-changing demands.
Early restorative approaches
Around 180AD, the American Dental Association states that the Etruscans were practicing dental prosthetics with the use of gold crowns and fixed bridgework – specifically for the aesthetic purpose of demonstrating wealth. However, over the years they have been repurposed to deliver results that offer functionality as well as aesthetic that matches that of more natural dentition rather than for ostentatious purposes.
Much of the 20th century saw crown material selection navigated almost solely by durability and marginal integrity. Metalbased crowns – particularly those designed with gold alloys – were notably understood as the representation of long-term success. This was particularly due to their ability to withstand occlusal force and resist fracture – making them reliable restorations, especially in posterior regions.
Clinically speaking, the materials used in this era offered exceptional performance – with survival rates exceeding anything seen before from other restorative materials proposed or used at the time. However, as dentistry and both patient awareness and expectations evolved, the aesthetic limitations of full-metal crowns proved an issue – with patient preference requiring restorations that integrated more seamlessly with natural dentition.
The aesthetic compromise
The late 1800s saw a major improvement in dental crowns as Dr. Charles H. Land patented the porcelain ‘jacket’ crown – allowing a visibly broken tooth to appear whole and fixed. However, it became apparent that it was vulnerable to microscopic cracking – impacting the tooth and surrounding gingiva. By the late 1960s and into the 1970s, porcelainfused-to-metal (PFM) crowns emerged, offering a solution to both the functional and aesthetic requirements of crowns. Despite the advancement, limitations were still rife, presenting issues such as opaque margins, limited light transmission, and the risk of porcelain chipping. Over time, gingival recession exposes underlying metal margins – compromising the aesthetic intention entirely.
The
expansion of all-ceramic solutions
Approaching the early 2000s, developments supported the wider use of all-ceramic crown materials. Improved processing techniques and the introduction of materials such as zirconia – which afforded excellent durability, aesthetic appeal, and long-term stability – expanded clinical indications, allowing clinicians to more closely replicate the translucency and depth of natural enamel restoratively. Although these materials offered clear aesthetic advantages – improving patient satisfaction – they introduced further dependencies. Due to the intense fabrication, they relied more heavily on laboratory workflows which limited flexibility within practice and increased turnaround times. The compromise of more improved clinical outcomes was workflow efficiency – particularly in cases where same-day solutions were desirable.
Digital dentistry
Over the past decade, digital dentistry has augmented the reshaping of crown fabrication further. With AI design and intraoral scanning, clinicians are now able to produce crowns in-house – minimising turnaround time and enhancing patient satisfaction insurmountably.
Though chairside restorations excel efficiency and convenience, an increased demand for the right materials became apparent. Not only did the crown materials need to offer the same level of aesthetics and durability that patients expected, but they now needed to perform predictably well, under time constraints.
Persistent limitations and compromise
Despite significant progress in every era of crown advancements, each stage has involved compromise. Clinicians have constantly been required to balance strength against aesthetics, speed against durability, or efficiency against predictability – each of which should ideally not be compromised at all. Material choice has often led this decision, dictating workflows rather than being designed to support them.
Recent years prove that material development can meet the competitive demands more easily – establishing high translucency materials that both look like and perform like natural dentition – whilst offering compatibility with efficient workflows.
Next-level crown materials and workflows
Leading the way in innovative crown material is SprintRay. Their Crown HT is a high-translucency resin with >60%
ceramic – delivering remarkable aesthetics. Offering lifelike light diffusion that replicates natural teeth, the Crown HT is ideal for fabricating definitive crowns and minimally invasive restorations including inlays, onlays, and veneers. Mirroring the functional performance of surrounding dentition, the Crown HT guarantees durable restorations –without compromising aesthetics.
The future of crown restorations
The evolution of dental crown materials represents the field’s continuous endeavour for balance – between durability, functionality, and aesthetics. Digital technologies, clinical understanding, and revolutionising materials each play a role in uncompromised developments – allowing clinicians to deliver excellent restorations that adhere to the modern expectations of patients, without hidden complexities. For more information on the SprintRay 3D printing solutions changing the game in dentistry, please visit sprintray.com/en-uk/
About the author Ross Phillips, SprintRay Area Manager, UK & Nordics.
Why isolation performance matters in restorative dentistry
Effective isolation is crucial for successful restorative dentistry. Properly controlling moisture and microbes helps to establish a dry working field to ensure reliable and high-quality treatment results. Dental dams offer an engineered solution for this, preventing patients from aspiring or ingesting foreign objects, protecting soft tissue, and even reducing risk of infection. It is integral that the material offers dependability once tension is applied. Elasticity and tear resistance are both important factors that can significantly impact whether isolation is maintained throughout a procedure, or whether it is compromised. Therefore, choosing the right dental dam is a big decision.
advances in engineering
By excluding moisture and saliva from the tooth being restored, the bond between the restorative material and tooth is improved, whilst also minimising infection risk. Poor bonding can compromise the restoration, both in terms of success and longevity compared to other isolation materials.
Other methods of isolation include the use of cotton rolls combined with aspiration by saliva ejectors. However, although this method is relatively low-cost and widely available, cotton rolls are clinically inefficient due to the frequent requirement of replacing sodden ones throughout treatment to ensure a dry operating field.
Research indicates that restorations might be more likely to remain in place and be in good condition after six months when using
a rubber dam instead. Dental dams also offer reassurance to dental professionals regarding the spread of pathogens too as it has been reported that up to 70% of airborne particles could be reduced around a 3-ft diameter of the operational field when a dam is used.
Having been introduced to the dental profession by Dr Sanford C Barnum on 15 March 1864, the application of dental dams has been significantly improved and is now used frequently as a more practical approach to isolation.
Key to efficient workflows
Restorative cases are often time consuming and demand uninhibited, broad access to the oral cavity. This requires the dental dam material to demonstrate excellent, long-term elasticity and stability under tension. Elasticity allows the dental dam to stretch over clamps and tooth contours without compromising soft tissue or access, meaning its elasticity must be controlled and adaptable to avoid thinning or loss of tension. Additionally, tension is linked to tear resistance, whereby tears commonly occur at specific points of stress. Materials that offer consistent thickness and controlled elasticity allow the forces to be distributed more evenly, which reduces the risk of failure. As even the
most minor tears can interrupt the continuum at any point during the procedure, strong resistance is integral. This could otherwise compromise the isolation of the tooth and subsequently impact the time-frame and potential success of the treatment.
Recent advances in non-latex, synthetic dental dams have introduced greater benefits beyond a solution to latex allergies. Unlike natural latex designs, the synthetic approach can be engineered to deliver greater elasticity and tear resistance. This level of consistency and reliability is highly valuable in restorative dentistry as predictable handling is crucial for efficient workflows and continuous aesthetic quality.
material predictability for the best results
Using dental dams – with this predictable material behaviour – significantly reduces interruptions during treatment. Dental dams that uphold tension maintain greater consistency during treatment for many different patients. When clinicians are less likely to pause due to tears or overstretched isolation tools, focus and workflows are less frequently interrupted. Though these disruptions might be minor in moment, their consequences can greatly compromise results – increasing cognitive load and chair time whilst diminishing patient satisfaction.
Selecting the best isolation materials
When selecting a dental dam product for use in your practice, considering these factors is important for continuous success in treatments.
The new HySolate SyntX Dam from COLTENE is the most advanced latex free dental dam for faster isolation and confident retraction. With exceptional tear resistance, the HySolate SyntX Dam is engineered with polyisoprene – combining incomparable elasticity and tear resistance without allergy risks. The dam also comes with a preprinted template, making them easy to learn and use, whilst also streamlining workflows further by minimising preparation time. COLTENE supports stable isolation throughout treatment with its revolutionary HySolate SyntX Dam.
Restorative success is impacted not only by clinician technique and skill, but by the materials used throughout the process. Dental dams that maintain elasticity and tension – and that provide excellent tear resistance – allow procedures to flow more smoothly and predictably. By working with controlled materials, workflow predictability and efficiency is enhanced significantly. For more information, visit https://products. coltene.com/EN/CH/products/treatmentauxiliaries/dental-dam/standard-non-latexdental-dam/hysolate-syntx-dam email info. uk@coltene.com or call 0800 254 5115. n
about the author Vik Sharma, Sales Director, Coltene Group.
The home stretch
Apatient returns four months after splint delivery, displaying only modest improvement. Pain has reduced, but maximum mouth opening is still too restricted for comfortable eating or yawning. They want to know how much longer until function returns. The honest answer: splint therapy alone can take 12 months or more to achieve maximum improvement in restricted opening. But recent evidence suggests a faster pathway exists. Combination therapy – pairing occlusal splints with evidencebased home management – delivers earlier results and accelerated function recovery. For GDPs managing temporomandibular joint disorders (TMD) conservatively, understanding when and how to recommend this multimodal approach may significantly improve patient outcomes.
three pathways
If a patient’s self-management of TMD fails to provide meaningful results, several options remain.
Splint therapy alone is standard, as occlusal splints reduce muscle hyperactivity, protect the dentition, and gradually improve mouth opening. The evidence is robust; for pain reduction and functional gain, splints work. However, development is slow – often slower than a patient would prefer.
Manual physiotherapy with splint therapy represents the gold standard in terms of fast and effective TMD recovery. Specialist physiotherapists combining manual techniques and progressive exercises with splint use achieve superior outcomes for pain and mouth opening than splint use alone. The limitation is access: TMD-trained physiotherapists remain scarce, NHS waiting lists can be long, and private treatment is costly.
Splint therapy combined with structured home stretching bridges this gap, as adding home-based exercise programmes produces earlier results than splint use alone. Patients are, therefore, able to achieve measurable gains in function without specialist physiotherapy access. Structure and routine with progressive resistance tend to deliver quantifiable results.
Why combination therapy?
Restricted mouth opening often involves a mechanical limitation that passive splint wear doesn’t directly address – stretching is often needed to restore the full range of motion. Studies comparing splint-only versus splint-plus-exercise consistently favour combination approaches. The implications for quality of life are significant. Patients with maximum opening below 35mm report substantial difficulties, and so each millimetre gained translates to meaningful functional improvement. Device-assisted stretching has been proven to aid in patients achieving 1–2mm increases per week, which is substantially higher than splint therapy alone.
Challenges of home stretching
The traditional advice, to stretch the jaw at home several times daily with fingers, tends to suffer from poor patient compliance and inconsistent completion. Patients lack professional feedback at home, force application varies unpredictably, and motivation naturally wanes. As such, successful home stretching depends on clear patient education, ongoing professional support, and regular measurement of progress.
Evidence-based home stretching requires progressive resistance, quantifiable measurement, controlled force application, and structured routines – manual finger stretching lacks these components. Deviceassisted stretching addresses these limitations by providing consistent, measurable resistance with built-in progression.
Implementing combination therapy
An initial assessment establishes baseline maximum opening, identifies the TMD subtype, and rules out red flags. For muscle-based TMD, or disc displacement with reduction, combination therapy is appropriate first-line management.
Four weeks post introduction of both splint and home stretching, measurement of maximum opening will indicate to the practitioner the level of patient compliance. Patients responding to combination therapy typically show around 5mm of improvement by this point,vi and those plateauing may require treatment modification, or possibly specialist referral.
This approach changes conservative management from passive to active, and offers predictable and objective milestones.
Structure at home
The challenge for general dental practitioners has long been recommending specific, evidencebased home stretches without access to quality physiotherapy. Device-assisted stretches address this gap by providing the structure and progression that manual stretching lacks.
Flowable composite
Dental professionals want to give their patients the best restorations possible. This means enhanced aesthetics that not only look natural within the dentition, but also make a person feel confident in their smile. Function is also a priority – a restoration should stand both the test of time and the test of everyday life, standing up to masticatory forces as well as some expected parafunctional habits.
To achieve these goals, a clinician will look for well-regarded, effective materials, and wonder how to make the most of them. In the world of composites, flowable solutions have increasingly gained popularity, now making up a core part of everyday restorative care.
Clinicians should understand what a flowable solution could contribute to their workflow, which elements to look out for when identifying additions to their arsenal, and how they can use them to their greatest potential.
Behind the flow
Flowable composites offer improved ease of use, handling, and wetting properties compared to conventional composite resins. Their reduced viscosity also allows good adaptability to cavity walls, whilst a considerable filler content – often around 61% to 71% of its weight – ensures high occlusal loads can be managed. An increased wetness aids conformity to every irregularity in the tooth structure, minimising gaps that may be a target for further problems.
A cost comparison favours home devices substantially: a one-time device investment versus six sessions with a specialist physiotherapist. For patients facing NHS physiotherapy waiting lists or unable to afford private treatment, device-assisted home stretching offers accessibility while also delivering evidence-based, appropriate care. The OraStretch® Press Rehab System from Total TMJ exemplifies this approach. The device delivers controlled, progressive passive stretching with quantifiable resistance measurement. Patients perform structured protocols, tracking maximum opening improvement. As a complement to splint therapy rather than replacement, the OraStretch® enables practitioners to offer therapies without specialist physiotherapists.
Conservative TMD management has evolved in more recent years to combination approaches. Splints remain foundational, but adding structured home stretching delivers faster functional gains without requiring specialist referral. Device assistance provides the steady progression and objective measurement that manual stretching lacks. For patients and practitioners alike, this is a practical advancement: utilising active, measurable treatment while maintaining the accessibility and affordability of minimally invasive care. For more details about Total TMJ and the products available, please email info@totaltmj.co.uk n
about the author
Karen Harnott, total tmJ Operations Director.
Preheating increases the fluidity of composite resins. An increased adaptability to the cavity wall and better edge closure means clinicians can expect reduced microleakage. Studies also show an increased monomer conversion when a composite resin is warmed prior to light curing.
The final aesthetic result may also benefit from composite warming as a method of material preparation. The literature notes that prewarming dental composites not only enhances the mechanical properties of a solution, but decreases its susceptibility to colour change. The higher degree of conversion reduces the risk of discolouration as a result of environmental exposure and ageing, ensuring restorations look better for longer – and flowable composites appear to benefit the most.
See it to believe it
Amongst their many indications, the literature has shown they are an especially preferred material for pit and fissure sealants, with increased retention when compared to conventional resin-based sealants.
Some professionals may implement them in the bonding of orthodontic brackets and lingual orthodontic retainers, denture repairs, and for repairing ditched amalgam margins, crown margins, and composite restoration margins. Each solution’s potential impact will differ, and looking at the recommended indications is key.
As for the elements to look out for, an increased depth of cure is pivotal for bulk fill solutions. High-quality aesthetics will ensure patients leave their appointment happier, and this can either be achieved through a wider range of shades being available or, more simply, an adaptive system that can cover the VITA shade guide in as few as three options. To simplify the restorative process, it may also be useful to find solutions that do not even need a blocker in order to achieve the desired aesthetic results; this creates a smaller inventory, with less waste produced, and more straightforward care.
What can a warmed composite do for you?
Composite warming can have a fantastic effect on the application of some flowable composite restoratives. First, it’s vital to ensure that the solution is manufacturerapproved for this process, with the relevant testing for its safety and efficacy. Choose clinically-proven solutions from reliable material providers, and be sure to also select compatible composite warmers that allow for direct control over the temperature of the restorative material – maximising safety and predictability. With this in place, it’s possible to begin to get much more from your materials.
With their improved adaption to the walls of a restoration site, and the potential for improved outcomes with composite warming, it’s no surprise that many clinicians use flowable solutions frequently in their care.
One of the more complex challenges facing composite use is always high-quality aesthetics. Clinicians will want to match the surrounding dentition colour whilst replicating the aesthetic of dentine underneath enamel that dissipates near the bevel and incisal edge. This can, with some composite systems, be particularly difficult. The change in shades may require multiple composites layered to create a natural appearance. This isn’t the case with the new Solventum™ Filtek™ Easy Match Flowable Restorative, which uses just 3 shades –Natural, Bright, and Warm – to match the entire VITA classical shade guide. A naturallyadaptive opacity ensures clinicians can replicate the visual anatomy of the natural dentition, whilst its flowable properties allow for a wide range of treatment applications. The solution is also able to be pre-warmed for enhanced outcomes, up to one hour at a time, and up to 25 times overall. Clinicians can use the new Solventum™ Filtek™ Composite Warmer for speed, simplicity, and reliability. The solution has been rigorously tested to ensure you can maximise results without compromising on composite physical properties.
Flowable composite materials are an effective addition to the modern dental inventory. Choosing a solution that optimises aesthetics, application and longevity ensures patients have the best experience in the dental chair, and for many years after.
To learn more about Solventum, please visit solventum.com/en-gb/home/oral-care/ For more updates on trends, information and events follow us on Instagram at @solventumdentalUK and @solventumorthodonticsemea n
Suction Simplified
All your suction needs met from a single supplier
UK based technical support
The Complete Package
Monitor the performance of your suction unit – faults and maintenance messages are immediately displayed
Devices, materials and accessories to ensure the safety and longevity of your equipment
Reassurance of German manufacturing standards
After the implant
For many patients, the final day in the chair may feel like the final day of their long implant journey. Plenty of challenges are now in the rearview mirror, but plenty still remain ahead. Namely, oral hygiene and restorative upkeep. It is, of course, vital to protect the investment of dental implants, but is post-implant care likely at the forefront of every patient’s mind at this stage?
Dental implants have an impressive survival rate: over 95% at 10 years, yet peri-implantitis affects approximately 20% of all implant patients. This inflammatory condition, characterised by progressive bone loss around osseointegrated implants, is the primary threat to their long-term survival.
Patients can potentially spend thousands on implant treatment, and yet surgical success is really only the beginning. Long-term survival depends on effective daily oral hygiene, yet for many with fixed implant bridges and overdentures, achieving adequate cleaning using traditional methods proves remarkably difficult.
Why implants fail
Peri-implantitis mirrors periodontal disease in some ways, but typically progresses more rapidly. Inflammatory lesions around failing implants are often larger than comparable periodontal sites, while bone loss follows a circumferential pattern. What begins as reversible periimplant mucositis – soft tissue inflammation without bone loss – converts to destructive periimplantitis if biofilm accumulation continues. Strong evidence identifies controllable risk factors: history of chronic periodontitis, poor plaque control, and absence of regular maintenance care.
the oral hygiene gap
When it comes to patients with single-unit implants in accessible positions, traditional string floss might suffice. However, many face more complex scenarios: multipleunit bridges or implant-supported overdentures creating physical barriers to conventional cleaning.
Consider the patient with a fixed implant bridge. The prosthetic sits against tissue, creating an interface where biofilm accumulates. String floss cannot access the underside of fixed prosthetics, and interdental brushes cannot navigate the complex structures of implant abutments and pontics. Patients with implantsupported overdentures may find accessing the junction between implant, abutment, and tissue –where plaque threatens peri-implant health the most – close to impossible with traditional tools. This accessibility issue can be a fairly serious one for health and implant survival, as it is bacterial biofilm in these locations that drive peri-implant disease. If patients cannot effectively remove it daily, the conditions for peri-implantitis development are present regardless of how well the treatment has gone up until this point.
When cleaning is inadequate
When biofilm removal fails, the inflammatory cascade begins. Initially, patients develop perimplant mucositis: bleeding on probing, tissue redness, swelling. At this stage, the condition remains reversible with improved hygiene. However, continued presence of biofilm converts peri-implant mucositis to peri-implantitis. Probing depths increase, bone loss becomes evident radiographically, and inflammatory lesions extend deeper. Once established, peri-implantitis
about the author anne Symons, Waterpik ambassador Dental hygienist, currently working in a Specialist Periodontal/Implant practice. Dealing
cannot be reversed through oral hygiene alone, and surgical intervention becomes necessary. Clinical implications aside, patients can experience anxiety about their costly investment failing, embarrassment from visible dental issues, and the stress of potentially having to undergo treatment all over again. Managing failing implants, for practitioners, is a crucial and sometimes difficult process.
What do implant patients need?
The secret to effective peri-implant hygiene is taking the time and care to reach those areas traditional tools may find it hard to access. A soft-bristled toothbrush to avoid scratching the implant, low-abrasion toothpaste, and an antiseptic mouthwash for the management of bacteria could all contribute to the new hygiene routine, but these hard-to-reach areas demand more specialised cleaning methods. Research demonstrates that water flossers address this accessibility challenge well. Studies comparing water flossing to string floss around implants show that they are more than twice as effective, indicating a 145% greater reduction in bleeding on probing. The mechanism is straightforward: pulses of water reach beneath prosthetics, around abutments, and into areas string floss physically cannot access. The irrigation effect removes loosely attached biofilm while creating a flushing action at the same time, which non-water flossing techniques cannot replicate.
Setting patients up for success
Water flossing’s advantage in accessibility can change the game for patients with implants. Arguably, when it comes to risking periimplantitis, using a water flosser goes beyond convenient to necessary.
Establishing water flossing as part of the immediate post-treatment protocol, rather than waiting for signs of a problem, will help set patients up for
long-term success. During the healing period, gentle flushing out can support tissue recovery, and as patients transition to long-term maintenance, this already established routine will continue to protect their investment.
The Waterpik™ Ultra Professional water flosser addresses the specific challenges implant patients face through a range of specialised tips designed for different restoration types. For patients with implants, crowns, and bridges, dedicated tips access stubborn biofilm in areas traditional tools cannot reach. Those with implant-supported overdentures or fixed implant bridges will benefit from specific tips designed to target areas beneath and around prosthetics, enabling patients to maintain that implant-tissue interface.
Practitioners placing or restoring implants should recognise that traditional oral hygiene recommendations may prove inadequate. Patients invest substantially in implant treatment, and expect long-term success. Providing them with tools capable of maintaining that solution is an essential part of the treatment. Evidence increasingly supports water flossing as a primary recommendation for implant patients, particularly those with fixed bridges or overdentures – protecting implant investments requires appropriately sophisticated post-surgical prosthodontic care.
For more information on Waterpik water flosser products visit www.waterpik.co.uk. Waterpik products are available from Amazon, Costco UK, Argos, Boots and Tesco online and in stores across the UK and Ireland. n
Strong. Aesthetic. Flexible.
Class I-V restorations, including occlusal surfaces
Two viscosities: F00 (build-up) & F03 (filling)
Self-levelling for easy placement
Superior polishability and durable gloss thanks to its submicron S-PRG particles
Chameleon effect for natural aesthetics
Fluoride release and recharge
Hay fever and oral health
Allergic rhinitis, also known as hay fever, is triggered by rising pollen counts as seasons change and is unavoidable for a vast number of people. In the UK alone, approximately 16 million people are affected, with symptoms varying from sneezing and itchy eyes to nasal congestion, respiratory issues, and more. However, despite the widespread awareness and experience of hay fever, it is rarely discussed in a dental context. Unlike the common cold or flu, hay fever is often prolonged, with symptoms persisting and sometimes compounding –particularly throughout spring and summer. Such a prolonged period of symptoms like nasal congestion and medication use can influence an abundance of oral health factors. Most of these are overlooked, but dental professionals are in the unique position to support patients with allergic rhinitis, by encouraging healthy habits and offering tailored advice.
Mouth breathing and saliva composition
One of the most recognised and common symptoms of hay fever is nasal congestion, which leads to patients instinctively relying on mouth breathing. While this might not seem significant, the consequences for the oral cavity – particularly long-term – can be substantial. Inevitably, an increase in mouth breathing dries out the oral cavity, leading to reduced moisture in the mouth. The protective purpose of saliva – removing debris and plaque from dentition, buffering acids, and supporting remineralisation through calcium and phosphate exchange – is diminished, increasing a patient’s vulnerability to oral disease.
the effects of antihistamines
Medication is another contributing factor, as many antihistamines declare xerostomia as a side effect. The intersection between mouth breathing-induced dryness and medication-related dryness causes a compound effect on oral health. In not knowing that the xerostomia they are experiencing is linked to medication, patients often attempt to combat it with any means possible, responding to the symptoms rather than the source. For example, patients might take throat lozenges or sip on sweetened beverages to increase salivation, without understanding the complications their actions are contributing to, such as an acid or sugar increase.
Though there are sugar-free options available for aids like lozenges, without knowing the consequences of the sugary options, patients might not actively seek a reduced sugar alternative. This makes professional dental guidance absolutely essential.
Vulnerable interdental space
The health of interdental spaces between dentition is heavily dependent on thorough mechanical cleaning – especially when saliva production is compromised and other habits are altered. Though toothbrushing is non-negotiable, alone it is insufficient for the adequate cleaning in between teeth, which combined with reduced saliva levels, accelerates the development and accumulation of plaque in interdental spaces. This makes consistent and in-depth interdental plaque removal exceptionally important during allergy season.
Clinical guidance
The best approach to supporting patients through the oral health risks associated with hay fever is preventive – which doesn’t need to be complex. Awareness of the intersection between hay fever and oral health is important for patients, as very few will recognise the connection between the two.
Other minor adjustments can alleviate the oral consequences of nasal congestion and medication use. Dental professionals should:
• Encourage sufficient hydration
• Recommend sugar-free lozenges where required
• Emphasise toothbrushing twice a day with fluoride toothpaste
• Reinforce further layers of oral care like interdental plaque removal and alcoholfree mouth washes
Furthermore, when patients are already managing persistent allergy symptoms, overcomplicated or time-consuming oral hygiene routines are unlikely to be wellsustained. As such, tool recommendations should encourage simplicity without compromising efficiency.
tools that truly support
Interdental brushes, designed for purpose, are a fantastic addition to oral hygiene routines. Flexible ones can offer a thorough and controlled clean without adding excessive pressure – reaching all the spots at risk of suffering from reduced saliva levels.
One such product is the range of TANDEX FLEXI interdental brushes, designed to take oral hygiene to the next level. Designed with a plastic-coated wire, the risk of abrasive damage and sensitivity is avoided, whilst ensuring a thorough clean. The vast range offers eleven sizes, guaranteeing a bespoke clean for every user. When used in parallel with the TANDEX PREVENT Gel – which combines fluoride (900 ppm) and chlorhexidine (0.12%) – plaque is mitigated further due to the antibacterial effect.
Preventive care and the supportive guidance
Dental professionals have the power and duty to support patients suffering from hay fever with advice, guidance on preventive care, and the right tools. Allergic rhinitis is greatly inconvenient in so many areas of day-to-day life – oral health doesn’t need to contribute to this – informed assistance can ensure that.
TANDEX is giving dental professionals the opportunity to win a FREE FLEXI Educator Kit by answering just a few questions! Enter the quiz by scanning the code or following this link https://form1.tandex.de/ For more information on Tandex’s range of products, visit https://tandex.dk/ n
about the author Jacob Watwood, on behalf of tandex, rodericks Dental Partners associate at Fieldside Dental Practice.
The real cost of dental pain
Dental pain is a common issue experienced by people across the nation. It can be caused by various factors and, therefore, requires professional assessment to determine appropriate treatment. However, this can take time – either while diagnostic testing is completed or during the wait for an available appointment. Considering the impact that this pain can have on an individual’s everyday life, it is important that the dental team can offer support to alleviate symptoms as quickly as possible.
Individual wellbeing
Crucially, toothache can have a detrimental impact on a patient’s quality of life. Oral pain – alongside tooth loss and impaired dental functionality – is associated with an increased risk of mental health conditions like depression. The literature has also established a link between dental pain and anxiety, with chronic dental pain associated with an overall poorer quality of life.
Mental health and wellbeing are further affected by the physical implications of chronic toothache. A bidirectional relationship exists between chronic pain and sleep, with higher pain levels leading to lower quality and quantity of sleep, and vice versa. Dental pain can also influence nutrition, as chewing problems can cause individuals to avoid certain foods, increasing the chance of malnutrition.
Clearly, toothache can have a significant effect on those who experience it. However, the impact of dental pain spreads far beyond the afflicted individual.
economic burden
Oral health problems are estimated to account for 9-27% of work absences due to sickness, with toothache being a leading cause. It has been reported that almost three in 10 British people (28%) miss work due to tooth pain, which equates to 11.7 million individuals. Approximately 7% of working-age adults have taken an entire week off for dental pain, adding up to 23 million sick days. This costs the UK economy millions of pounds in lost production each year.
However, this may not accurately reflect the number of people who suffer from dental pain. It is thought that oral discomfort is often not enough – or perceived to be enough – to take the day off, meaning that a high proportion of affected workers will still attend. In the aforementioned study, 9% of respondents found toothache to negatively affect the quality of their work and reduce their productivity.
Just as worryingly, research has suggested that many individuals – up to 73% – will delay dental treatment specifically because they don’t want to take time off work.
treatment costs
While this maintains work presenteeism, it ends up costing the population in other ways. Firstly, reduced productivity across UK industries is hindering economic growth. The UK is ranked in the lowest third of the 38 countries listed by the Organisation for Economic Co-operation and Development (OECD), having experienced slower growth compared to many other nations. Sluggish productivity, particularly in low-wage sectors,
alongside low growth rates are preventing the UK economy from flourishing as others are. Dental pain is only the tip of the iceberg when it comes to improving workplace productivity, but it is important nonetheless. Delayed dental treatment also has financial implications. When oral health problems are allowed to develop and advance, they often require more drastic intervention when the professional team is eventually consulted. Dental caries alone is estimated to cost the UK £18,000 per person – a sum that could easily be reduced with more timely treatment and effective prevention strategies. Other estimations suggest that missing a £60 dental appointment could cost someone up to £4,000 in the following three years, demonstrating how quickly seemingly small problems can grow if left untreated.
accessible dental care
Sadly, there is no quick fix. Dental professionals must make their services accessible to as many people as possible, tailoring what they offer to suit their local demographics. Core messages should be centred around prevention, encouraging patients to take responsibility for their oral health, maintain effective at-home dental hygiene routines, and attend regular appointments. When patients are in pain, they should understand the importance of seeking timely professional support. They will also need an immediate solution that will help to alleviate their symptoms while they await their appointment. In these situations, consider Orajel® Dental Gel – it contains 10% benzocaine to deliver rapid pain relief in just 2 minutes. Alternatively, the Orajel® Extra Strength solution contains 20% benzocaine for a greater local anaesthetic effect when needed.
Dental pain has wide-reaching consequences on individuals, with untreated dental health problems increasing treatment costs and affecting the nationwide economy. Professionals can help to address the issues by prioritising prevention strategies and helping patients to avoid the development of oral disease in the first place. When issues do occur, being able to recommend fast and trusted pain relief will be just as vital for a positive patient experience.
For essential information, and to see the full range of Orajel products, please visit https://www.orajelhcp.co.uk/ n
about the author Sumera Bashir, Medical affairs & Scientific engagement lead, orajel.
Dr Ian Dunn Dr Ra Louisa Clarke
The new electric flosser that fills a decade-long gap
Flossing has always been the weak link when it comes to oral hygiene. Clinicians know it works; patients know they should do it. Yet the evidence consistently shows that most people floss infrequently, inadequately, or not at all – particularly those with tight contacts, fixed orthodontic appliances, or limited manual dexterity. For many people, traditional string floss is the dental equivalent of a cold shower: they know it is good for them, and they find any excuse to avoid it.
The tools available should make routines simpler, more thorough, and more effective – kickstarting an oral hygiene practice that will protect a patient’s smile for life.
Tahir Oral Care, a British oral care company founded by Stefan White, set out to address this challenge with a straightforward premise: the reason people do not floss is that the tools are not always right. The Tahir Electric Flosser is his answer.
Designed around the patients who need it most
Dr Dhiru Patel, Specialist Orthodontist, has noted the value of the device for patients in active orthodontic treatment, where interdental cleaning around brackets and wires is both critical and notoriously difficult to achieve.
As he puts it: “The Tahir electric flosser is a very useful and practical device – it is nothing short of inexplicable that a product of this kind has been absent from the market for so long.”
The evidence supporting powered flossing devices for patients is wellestablished – generally considered to be between 29% to over 50% more effective than string flossing. What has been glaringly missing is a well-designed, evidence-backed product for clinicians to recommend.
The Tahir Electric Flosser is a rechargeable, handheld device built for one-handed use. It delivers 12,000 sonic vibrations per minute across four cleaning modes, and uses disposable floss heads that are replaced every three to four days. The result is a device that mimics the motion and efficacy of traditional flossing while removing the dexterity demands that cause so many patients to abandon the habit.
The Tahir Electric Flosser is designed with exactly these patients in mind.
The floss heads are recyclable, available in cool mint, and included in quantity in the starter kit – enough to cover the first two to three months of use. Sensitivity-safe technology makes the device appropriate even for patients with gingival sensitivity who might find other powered options too aggressive.
Built to be believed Tahir Oral Care has secured £200,000 in grant funding to conduct a randomised controlled trial with Barts and the London School of Medicine and Dentistry across 1,000 patients in London – generating the kind of peer-reviewed, productspecific evidence that is still rare in the consumer oral care space.
Results are forthcoming. The intent is clear. This is a brand that wants to truly earn its place on the recommendation list – not just the shelf.
The Tahir Electric Flosser is available for patients through their website, Amazon, and Harrods. For practice enquiries and professional ordering, visit tahiroralcare.com
Extra insights into your care
Digital imaging software has revolutionised everyday routines, transforming the opportunities for care that can be provided to patients. With the right solutions on hand, practice teams can perform radiographic exams quickly and simply, providing optimal comfort to their patients, whilst gaining thorough insights.
Carestream Dental has pioneered a range of versatile and effective CBCT systems, and partnering imaging software, that helps to transform everyday care. Whether practices wish to advance the care they can provide to patients already at the practice, or if they want to explore the potential to receive referrals and expand this aspect of the business, Carestream Dental is the ideal port of call for all things imaging.
see more with Cs 9600
At the height of the Carestream Dental offering is the CS 9600 CBCT Scanner, a versatile 5-in-1 solution that blends 2D panoramic and cephalometric imaging, CBCT imaging, 3D facial scanning and 3D model scanning into one unit. Such a range ensures professionals can develop insights tailored to a wide array of needs. This includes everything from endodontic care, to dental implant simulations.
One example of this is the innovative Scan Ceph module. The add-on produces high-quality cephalometric exams in just seconds. An 18 x 24 cm lateral image with the Fast Scan mode can take as little as 3 seconds, with a minimal risk of motion blur, and obtain fully automated tracings in 10 seconds. This means patients have faster treatments, and don’t have to keep still in one spot for long – see improved images and happier visitors as a result.
The CS 9600 also offers up to 14 unique fields of view, ranging from 4 cm x 4 cm to 16 cm x 17 cm, supporting a range of diagnostic needs. With applications in a range of maxillofacial treatments, selecting the most appropriate field of view ensures you have access to the aspects of the dentition that require most attention. You can then reduce excess radiation, and better patients throughout care.
Confident first steps
For clinicians looking to simply enter the world of dental radiography with an
effective, intuitive solution, the CS 8200 3D Access CBCT Scanner from Carestream Dental offers great value.
The easy-to-use imaging system features a modern interface that helps to quickly establish routine examinations, within a streamlined workflow. In addition to six selectable fields of view, the CS 8200 3D Access operates with four imaging settings. This way, the ideal entry into this form of care can meet your needs as the practice and patient base grows; choose from panoramic technology, CBCT imaging, 3D model scanning and cephalometric imaging to meet your needs.
An ultra-compact and smart design means the CS 8200 3D can fit into many practice spaces, whilst being adjustable to patients who can stand or need to sit throughout the examination. This way, your Carestream solution moulds to your needs.
It isn’t the only way Carestream Dental products can be designed around your practice. Digital imaging systems are designed to enhance your existing workflows, including with the new CS 3D Imaging Premium.
Plan with ease
The CS 3D Imaging Premium software utilises AI-powered tools to plan implants faster, and with fewer clicks. Clinicians can automate tasks for virtual crown and implant placement, calculated on the presented clinical situation. Changes can be made within the software for complete confidence in the treatment plan, and simply shared amongst professionals for improved communication.
Data can then be exported to create surgical guides for predictable outcomes, and exported to laboratories and partners. Carestream Dental creates digital solutions designed to adapt to, and revolutionise your workflows. To find out more, contact the team today.
For more information on Carestream Dental visit www.carestreamdental.co.uk
For the latest news and updates, follow us on Facebook and Instagram @carestreamdental.uk n
Practice independence
What do you do when it starts costing more than it’s worth?
For many dentists, owning a practice has long represented professional freedom. It offers the ability to shape patient care, build a team around shared values, and guide the direction of the business.
For some, that independence remains deeply rewarding.
However, the environment in which practices operate has evolved considerably. Administrative, regulatory, and financial pressures have increased, and the responsibilities associated with running a practice have become more complex. As a result, a growing number of principals are finding it harder to ignore the true cost of going it alone.
the hidden price of staying solo
Running a practice has never been simple, but in recent years, complexity has intensified.
Regulatory requirements from the Care Quality Commission (CQC), NHS contractual obligations, and evolving compliance frameworks – from infection control to data protection and clinical governance – now demand significant time and resource. In many independent practices, much of this responsibility ultimately sits with the principal.
Administrative workload is now widely recognised as a leading contributor to dentist burnout and dissatisfaction. Time spent on compliance, HR, and business management is time not spent with patients – or on the parts of dentistry that drew many practitioners to the profession in the first place.
Buying power and the economies of scale
Independent practices also face structural challenges when it comes to procurement.
Larger groups are often able to negotiate more favourable terms on materials, equipment, and laboratory fees. By contrast, a solo principal typically has far less negotiating leverage. Over time, these differences compound.
The same dynamic applies to associate recruitment. Candidates increasingly look beyond salary, considering the wider proposition: CPD support, clinical mentoring, access to modern equipment, and clear professional development pathways.
Competing in these areas can be difficult when margins are already under pressure.
isolation and the limits of going it alone
There is also a less visible – but equally important – cost.
Solo practice ownership can be professionally isolating. Decisions around clinical governance, complex cases, or business strategy are often made without the benefit of peer input.
Access to best-practice sharing, clinical networks, and operational expertise –resources that larger organisations typically embed into their infrastructure – is often limited for independent principals.
Over time, this isolation can affect both clinical confidence and business resilience. Challenges that might be quickly addressed within a broader network can take longer to resolve when faced alone.
Weighing the options
For principals experiencing these pressures, the choice is often framed as binary: remain independent, or sell and step away.
In reality, the range of options is evolving.
A full sale to a traditional corporate group may provide capital and operational relief, but it can also involve relinquishing a degree of clinical autonomy and adapting to a different cultural and operational model. For principals who value independence, that trade-off can feel significant.
Shared ownership models offer a third path. Rather than treating ownership as an allor-nothing decision, they are designed to combine the benefits of scale and support with the ability to retain meaningful influence over how a practice operates day to day.
a different kind of partnership
DeNovo Dental Partners has developed its model with this balance in mind.
Principals who join DeNovo can realise the full value of their practice upfront – through a combination of cash and equity – while continuing to lead their practice with autonomy over clinical and operational decisions.
As significant shareholders in the wider group, Partners also benefit from ongoing wealth creation linked to both practice and group growth, ensuring their financial interest continues beyond completion. Day to day, Partners gain access to central support services and a network of peers where knowledge, experience, and best practices are actively shared. There is no single right answer for every practice owner.
The decision about whether – and how –to seek external support will always depend on individual circumstances, career stage, and what you want from the next chapter of your professional life.
But understanding the full range of options available – including models that enable principals to retain autonomy while gaining support – is an important first step towards making a confident, well-informed decision.
Our exclusive TrueFit® Technology analyses your unique facial features and working posture to deliver comfort, perfect visual alignment, and lasting ergonomic support.
CUSTOM MEASURED • CUSTOM FITTED • CUSTOM MADE
loupes bring your
Managing patient expectations through communication
Managing expectations is one of the more challenging aspects of dentistry. The more realistic a patient’s expectations, and the more aligned they are with the eventual outcome, the less likely they will be unhappy with treatment, and make a complaint. Identifying and addressing patient expectations is therefore important in managing your risk. This is especially true when patients are considering elective treatment for cosmetic reasons, compared with clinically necessary interventions to treat disease or maintain dental function.
Causes of unrealistic expectations
• Lack of information: Opening hours/ access to dental care, wait times, treatment availability or complications of treatment.
• Too much information: Patients might attend the practice with a preconception of how they want to be treated, basing their expectations on internet searches, past dental care experiences or those of friends and family whose situation may have been different.
• Not checking understanding: It is important to allow enough time to check a patient fully understand the issues involved in their care, the potential complications of their treatment or alternative treatment options.
• Time pressures: Allocating insufficient appointment time undermines the ability to establish a good rapport and a professional relationship with patients which is important to gaining patients’ trust.
• Anxiety: If a patient is anxious this can compound their ability to absorb/ process information and make misunderstandings more likely.
Managing patient expectations
1. Make information about the practice easy to access
Clear and consistent information from all members of the team, on the website,
social media, answer phone and posters in the waiting room can help patients know what to expect. Let them know how long appointments should last, the procedure when arriving at the practice, opening times, treatment fees etc. Principle two of the GDC’s Standards for the dental team directs you must treat patients as individuals1. You should take their specific communication needs and preferences into account where possible and respect any cultural values and differences. This includes making reasonable adjustments for patients for whom there are barriers to communication. It is a registrant’s professional responsibility to ensure any advertising, promotional material and website is accurate and not misleading about their skills and qualifications.
2. Ensure you communicate in ways the patient can understand Patients want clear explanations about their dental condition, treatment options, and post-treatment care. Avoid using dental jargon, technical terms, or abbreviations to prevent confusion. Remember that each patient is different and will have different needs and levels of understanding. Use visual aids, models, or digital images. Providing patient information leaflets to read at home may be a helpful addition to the information provided in surgery. In accordance with the Equality Act 20102 consider large print, braille, audio, or electronic formats. Development in digital technology has helped to provide new tools to support communication both in-surgery and remotely, for example, the ability to annotate images / videos, interactive educational tools and the ability for patients to re-access information and provide confirmation of understanding.
3. Encourage two-way communication
Have an open and honest conversation with the patient. Patients have a fundamental need to be heard and understood but this
will also give the treating dental clinician a clearer understanding of the patient’s expectations. Encourage active listening by the whole dental team. Establishing a good rapport and professional relationship with the patient goes a long way to gaining their trust – and consequently, improving their experience of their care.
4. Check understanding
Anxiety, physical disabilities, cognitive impairment and other circumstances can make it harder for patients to absorb the information you give them during appointments. Do not make assumptions about what the patient will or will not understand. Patients will have varying degrees of knowledge and experience regarding dental treatment. Check that the patient has truly understood all the information provided.
5. Set realistic timeframes
Effective time management skills increase your focus and productivity. Educate patients about the limitations of time during appointments and emphasise the importance of prioritising their concerns. Setting realistic timeframes helps manage patient expectations and ensures that each concern receives proper attention. Providing patients with sufficient time positively changes their perception of the level of care provided.
6. Address unrealistic expectations
When a patient requests a very particular form of treatment, be especially mindful of the patient’s expected outcome. If an unrealistic expectation is expressed, respectfully correct it. Pay particular attention to the patient who resists having their unrealistic expectation corrected. Increasing expectations may equate to increased risk.
7. Manage your own expectations
You need to be clear about what can be delivered. It is extremely important to only work within your level of confidence
and competence. When bad news is not effectively communicated, the dental professional may unwittingly create false hope for the patient3. Clinicians will sometimes find themselves attempting to manage failing dentitions with “herodontics”. In most of these cases, it is only a matter of time before failure inevitably results. When it does, not only can the situation be harder to manage, but the false hope and increased expectations created can lead to negative consequences for an increasingly disappointed patient. This in turn can have dentolegal or regulatory repercussions for the dental professional who may well feel genuinely aggrieved, believing that they have gone above and beyond the call of duty for the patient4
8. Avoid misrepresentation
It is important that we do not mis-represent our own abilities or skills. Care should be taken to ensure any communication with patients, or in the public domain, does not imply specialist skills or qualification unless the dentist is registered as a specialist in that field.
References
1. GDC Standards for the dental team. General Dental Council - Communicate effectively with patients
2. Equality Act 2010. Equality Act 2010
3. Waylen A. The importance of communication in dentistry. Dent Update. 2017; 44:744-780
4. Andrew James Paterson. Avoiding disasters in restorative dentistry by effective communication. Dental Update 2024 48:3, 707-709.
About the authors Dr Elaine Cook and Dr Noel Kavanagh are Dentolegal Consultants at Dental Protection.
YES. THIS WAS DIGITALLY PRESSED.
Patented Digital Press Stereolithography™ powers an all-in-one resin capsule system, printing ultra-viscous, ceramic-filled resins with unmatched precision. Midas is your new partner for creating definitive crowns, inlays, onlays, and veneers in just 10 minutes.
THE WORLD’S FIRST DIGITAL RESTORATION PRESS
Learn more Scan to meet Midas
What show is your reception team putting on?
One thing I say a lot when working with dental practices is this: “Your waiting room has an audience – and reception are on stage, whether they realise it or not.”
Now, before anyone imagines I want front-of-house teams sitting in silence like they’re in detention, that’s not the point at all. Patients want warmth. They want personality, smiles, humour and friendly conversation. Nobody enjoys walking into a dental practice that feels cold and awkward.
But there’s a fine line between friendly and forgetting there are patients sitting three feet away, listening to absolutely everything. And honestly? They hear far more than teams think they do. Scrolling through their phone does not mean they aren’t listening.
This is one of the most common things I see in practices. Reception teams become comfortable with each other – which is lovely in many ways but, over time, the desk can start sounding less like a professional front of house and more like a kitchen table chat during dinner.
Patients may not understand dentistry, compliance or treatment planning, but they are incredibly good at picking up atmosphere. They notice the dramatic sigh after
somebody hangs up the phone. They notice the eye roll when a patient asks another question. They hear comments about “difficult” patients. They hear frustrations about clinicians, diaries, staffing problems and business worries. And yes, they absolutely hear that Sarah’s boyfriend slept on the sofa after an argument about whose turn it was to empty the dishwasher.
I once walked into a practice where a patient sat quietly in reception while two team members debated whether one of them should dump her boyfriend because he “still shares a Netflix account with his ex.” Meanwhile the patient was sat there wondering whether this was the right place to trust with her implant treatment.
Another practice had a full-volume discussion about whose husband had booked a lads’ holiday to Ibiza “at his age.” There were a couple of gents of a similar age in the wating room, who I’m sure I saw flinch.
Now, some patients probably do find this entertaining. There’s always someone who enjoys a bit of live daytime drama while waiting for the hygienist. But plenty of patients don’t. Some are anxious, embarrassed, worried about treatment costs or simply wanting a calm environment.
Best in show?
BADN recently attended the Dentistry Show at the NEC in Birmingham – a welcome return (almost!) to the shows of past years, with a large number of both exhibitors and punters, and not too many non-dental stands!
The Dentistry Show also has the advantage of a Dental Nurse Forum, which on the Friday was chaired by BADN. Many thanks to Janet Pickles of R A Medical, Rachel England of the Oral Health Foundation, DeCon Pete, Faiza Arshad and Hannah Lambourn, as well as BADN’s Rebecca Silver and Preetee Hylton, for their presentations.
And the bigger issue is this: Patients don’t separate reception from the clinical side of the practice. To them, it’s all one experience. If the reception area feels chaotic, negative, unprofessional or tense, patients often assume that same energy exists behind the surgery door too. That’s the bit teams sometimes forget.
A patient sitting quietly on their phone may actually be listening to every word while building an opinion about your professionalism, your culture and whether they trust the practice. And trust matters massively in dentistry.
Front of house is so much more than answering phones and booking appointments. Reception sets the tone. It creates the atmosphere patients walk into and remember afterwards. The good news is this is usually easy to improve once teams become aware of it.
Most people aren’t trying to behave unprofessionally. It’s normally habit, familiarity, stress or simply forgetting how open reception spaces really are.
Small changes make a huge difference:
• Keeping conversations appropriate for the environment
• Avoiding visible frustration
• Being mindful of tone and body language
• Supporting each other professionally in front of patients
• Remembering that “private conversations” in reception are rarely private
And leaders do need to address it – not aggressively, but clearly. Because culture at reception doesn’t happen by accident. Teams take their lead from what is accepted, ignored and repeated every day. The practices that get this right create an atmosphere where patients feel welcome, calm and reassured before they’ve even sat in the chair. And in an industry where reputation spreads quickly, those little moments at reception matter far more than people realise.
So, next time you walk through your waiting room, ask yourself: If your reception team are putting on a show… what’s the audience going home thinking about? n
About the author Lisa Bainham is president at ADAM and practice management coach at practice Management Matters.
There was also the Dental Nurse Lounge – a sad, unloved, empty space with a few tables and chairs… A million miles away from the Lounge which we hosted back in 2022 when it had coffee, cakes and goodie bags. If any companies are interested in sponsoring the Lounge next year, please contact me on pam@badn.org.uk!
Following their success at Showcase, the BADN trio of ducks made a further appearance at this show – Richard Duck (aka Dick Duck) who, since his debut at ExCel has received a PhD so is now known as Doc Dick Duck, and his two brothers, Robin Banks and Justin Case, hid themselves on various stands. Any dental nurses spotting them and reporting back to the BADN stand received either £10 or £20 off their membership, or a free year’s BADN membership – according to which duck they spotted.
BADN (and the ducks!) will also be exhibiting at the Scottish Dental Show in Braehead on 12-13 June; Presidentelect Carolyn Roberts will be speaking on both days. Come and visit us!
And shortly after that, the “cooling off” period ends and – if all goes according to plan – BADN should merge with Community, the Union, allowing us to continue supporting and promoting dental nurses and the dental nursing profession. Watch this space! n
the
About
author pam swain MBe is Chief executive of BADn
•
• Optic
• Power 20w
• Micro head: Ø 9 x 10.8 mm
MODEL Z micro (ultra-mini head) CODE PA2357001 RRP £1,256
Also available in fittings for KaVo®, Dentsply Sirona®, W&H® Scan for full info on handpiece models/order codes
For regular or short shank burs
Perio & oral hygiene
Varios Combi Pro2
iPiezo engine®
AN EVOLUTION IN ULTRASONIC AND POWDER THERAPY
Gentle yet powerful, reliable and exceptionally durable, Varios Combi Pro2 has a host of advanced features designed to improve efficiency, control and enhance patient comfort. Engineered with meticulous attention to detail, Varios Combi Pro2 is an investment in clinical excellence and in the health of your patients.
• Superbly comfortable water temperature, for both ultrasonic & powder
• Durable titanium ultrasonic handpiece
• Jet Nozzle for Perio Handpiece
• Auto Cleaning
• Removable Powder Chambers*
• Multi-functional wireless foot control
Elevate your practice and patient care with the Varios Combi Pro2 - the future of
Heated Water
Both ultrasonic and powder handpieces inject water that is heated to the approximate temperature of the oral cavity, ensuring greater comfort, even for those patients with sensitivity.
Jet Nozzle for Perio Handpiece
Executes precise, targeted treatment to areas with staining or thick biofilm on roots or restorations.
Titanium Ultrasonic handpiece
• Durable & lightweight, with unrivaled ergonomics
• Non-slip & scratch-resistant Duragrip coating
• Slim LED handpiece enhances visibility
Perio & oral hygiene
Powder Therapy
pearl
Supragingival powder for tough stains. Used with ProphyMate or the Varios Combi Pro (Prophy Chamber).
• Calcium carbonate powder (54
Supragingival powder for moderate stains. Used with Prophy-Mate or the Varios Combi Pro (Prophy Chamber).
powder (65
Perio Mate Powder
For subgingival biofilm removal or mild supragingival stains. Used with PerioMate or the Varios Combi Pro (Perio Chamber).
• Glycine based powder (25 µm)
BUY ANY 2 PACKS OF FLASH OR SOFT pearl GET A FREE nozzle for Varios Combi Pro or Prophy-Mate
POWDER THERAPY PATIENT LITERATURE
Available on request with Prophy-Mate neo, Perio-Mate and Varios Combi Pro purchases.
Including reciprocating and rotary Endo features
NEW compact portable electric micromotor, for general & endodontic applications with contra angles (ie speed increasing/red band, 1:1 direct drive/blue band or speed reducing/ green band).
• Lighter motor with enhanced power/torque
• Ideal for general (restorative, prophy etc) and endo applications (rotary & reciprocating** modes)
• Enhanced patient safety function indicates when the handpiece needs repair to minimise it overheating
• Versatile installation options – portable or semi built-in
Implantology & Oral Surgery
Surgic Pro2 & VarioSurg 4
Pre-course
07900 246529 N. Ireland &
Asnain Sadiq asadiq@nsk-uk.com 07435 840097
Derbys/Notts/Yorkshire/Lincs
Tomlinson jtomlinson@nsk-uk.com 07545 786619 National
Muirhead nmuirhead@nsk-uk.com 07353 969563 South Wales Robert Musgrove rmusgrove@nsk-uk.com 07798 918741
Hargreaves ahargreaves@nsk-uk.com 07872 824175
South West Ben Guest bguest@nsk-uk.com 07350 361543
Excellence is not accidental
We live in an era of constant chasing – bigger, better, faster everything. Innovation and disruption dominate, and within dentistry it is no different. We’re, quite rightly, moving forward digitally, clinically and operationally but underneath these advancements some principles remain constant (and are really important to hold on to). We shouldn’t go at such a speed that we miss them: building safe and reliable foundations; and communicating effectively.
I’m going to explain what I mean using two international brands: Toyota and The Ritz-Carlton. Where Toyota is known for operational refinement, The Ritz-Carlton is recognised for next-level customer experience and consistency. Both organisations understand that excellence is not accidental.
Toyota became globally respected through its relentless focus on training, consistency and incremental improvement (my love of Kaizen – development through a series of continuous small steps – is well documented). Employees are encouraged to master fundamentals, contribute ideas and constantly refine whatever they can. Taking a ‘no waste approach’ they apply it to everything from managing physical waste, to time, movement, inefficiency and unnecessary complexity. They also take a ‘crawl, walk, run’ training approach where the ‘crawl’ part is revisited thoroughly so the basics are never overlooked.
I love these ideas – Toyota’s business practices can be applied to so many parts of our lives, not just at work. Clinical confidence is rarely built overnight. It develops gradually through education, repetition, mentorship and reflection.
Strong foundations allow clinicians to grow safely and sustainably, particularly in endodontics where precision, judgement and consistency are essential. Mentoring plays an important role within that process. I find that one of the most valuable aspects of teaching and training younger clinicians is seeing confidence develop through understanding. What counts are the fundamentals, communication and attention to detail. These are the building blocks that allow more advanced skills to flourish later. And in revisiting some of the basics, we can all continue to learn something new, every time.
Another organisation recognised for operational excellence is The RitzCarlton hotel group. Their reputation is not built purely on luxury, but on the consistency of experience and investment in people. Staff training, communication and attention to detail are embedded into the culture at every level. They have a morning ‘line up’ ritual where staff go through service principles, standards, concerns, and talk openly. They are empowered to resolve customer issues independently creating a culture of accountability and immediacy instead of relying on the more traditional, rigid hierarchy.
Thoughts from Birmingham
In November 2012, the late Nigel Hawkes, writing in the British Medical Journal, said, “There is little in UK Medicine that the General Medical Council cannot make worse.” My brother introduced me to the quotation and shared the original, pay-walled article with me.
At the recent British Dental Conference & Dentistry Show, I had a couple of things that I wanted to discuss with the GDC representatives. Early on Day 1, I found their stand, explained the background of Hawkes’ statement and asked for their response to my version that, “There is little in UK Dentistry that the General Dental Council cannot make worse.”
One thing I noticed early on in both my visits was the tag-team nature of the representatives. Whilst one of them was engaging with me, the other was preparing to come back at a slightly different angle with another argument to fudge or divert from my original question. To be fair, on Day 1 they were polite, assuring me that “things had changed” and “they were listening”. They trotted out the usual platitudes, stuck to the party line and I am sure that I will have had much the same effect as a tick on the hide of a rhinoceros. We parted on reasonable terms.
My visit on Day 2 was quite different. I was less amiable. I did have an axe to grind and wanted the answer to a simple question: Are dental registrants who own practices treated less favourably than corporate bodies?
Here is the case: my brother (him again), a retired professor of medicine and no mug, was a patient of a practice whose owners sold their business to a well-known corporate. All was well. After three years, the owners retired and his care was continued by a couple of different associates and hygienists. Again, all was well and he had no issues with his continuing care, nor with
Again, there are parallels within dentistry. Patients may not always understand the technical complexity behind treatment, but they recognise professionalism, organisation and reassurance immediately. Calm environments, clear communication and well-structured systems all contribute significantly to patient confidence. Often, it is the small details that shape the overall experience. There are clear parallels here with successful practice management and team culture.
I believe that long-term success in dentistry isn’t about chasing dramatic transformation. It comes from building well, refining consistently, and remaining committed to high standards over time. Technology will continue to evolve. Techniques will continue to advance. But the principles that underpin excellent patient care will remain as relevant as ever:
• Strong, regular training
• Thoughtful, empathetic mentorship
• Clear layers of communication
• Continual refinement and improvements. Ultimately excellence is created, not stumbled upon. n
About the author Dr Dhiraj Arora BDs MJDf rCs (eng) Msc (endo) pG Cert Ce owner of evo endo, with three practices (limited to endodontics) in Twickenham, Gerrard’s Cross and slough. Dhiraj is a passionate teacher and ambassador for all things endo. follow him on instagram: @drdij_evoendo
the referral practice that he visited for provision of implant care.
Then, after another two or three years, I heard a rumour that the practice was to close. I asked my brother what was happening and was told that, as far as he was concerned, all was the same and that he had a routine hygiene appointment in a fortnight. He contacted the practice and was told that the practice was indeed closing and that he “should have been informed”. His choices were to visit another of the chain’s practices either in another part of the city or to drive 30 odd miles to another branch. That can be summed up as “take it or leave it”. No continuity of care.
I told Day 2’s GDC tag-team the story without mentioning the fact that the practice was a corporate and they agreed that leaving a patient “in the lurch” (my words) was not acceptable. When I revealed that the owner of the practice was a corporate body they told me that “nothing could be done” because they only had authority to “go after” individual registrants. At one point they told me that a complaint could possibly be made against the associate and the hygienist, a suggestion that I
refused to consider as they were both casualties of the closure and had done nothing wrong.
During our “heated” discussion I was asked to calm down, I assured them I was just getting warmed up. However, they did seem disappointed when I revealed that I was no longer a registrant, nor was I a British resident or citizen.
The 2006 GDC guidance, issued during the “Dentistry enters a new era” launch, established that commercial interests must not override patient care or clinical judgment, emphasising director accountability. It specifically warned that attempting to influence clinical decisions for financial gain would be treated with maximum gravity, upholding professional autonomy under commercial ownership…. In this case, either the guidance has changed, is being interpreted differently or is misunderstood. Whatever, with regard to an individual patient, “The Spreadsheet Will Decide”.
I repeat, “There is little in UK Dentistry that the General Dental Council cannot make worse.” Nobody seems to care, except the “poor bloody infantry” and nobody listens to them. n
Introducing the ADI Team Congress 2027
The ADI Team Congress 2027 will be a celebration of the organisation’s 40 year anniversary. Attendees will review all that has been achieved in implant dentistry so far, as well as exploring both what’s current and what’s coming next, with compelling inspiration from notorious international experts in the field.
An array of exceptional speakers has been assembled specifically to showcase some of the best clinicians and genuine leaders in dental implantology. The majority will be travelling from abroad to discuss innovations, trends, and techniques from their countries. A selection of renowned UK practitioners will also share perspectives from closer to home for truly comprehensive insights. As such, there will be some brand new faces never seen before at ADI events, as well as a couple of previous favourites returning to update us on game-changing clinical advancements or research projects.
In addition, I’m delighted to be welcoming some sensational headline speakers to the stage with ideas and perspectives from beyond dentistry – watch this space for some really exciting announcements!
The programme will, therefore, cover a broad range of topics, from bone and soft tissue grafting to full-arch rehabilitation. A spotlight will also be placed on when not to place implants. This is another new feature for this event, but I feel it is important to understand the treatment options available when implants are not appropriate – for younger patients or those with a contraindicative medical history, for example. There will be content for professionals who are just starting out in implantology, all the way to those of us who work at the most complex clinical level.
A combination of hands-on workshops and lectures will be available, in addition to an extensive implant-focused exhibition supported by key members of the industry. This gives attendees a platform to discover more about the products or systems discussed in lectures, to see solutions first-hand and engage with developers or manufacturers to better understand technological capabilities and potential to support business growth.
This interaction is just the start of what the ADI community offers. The 2027 Team Congress social programme will include many opportunities to enjoy time with friends, to make new connections, and let your hair down a little with your team. We’re hosting a massive party on Friday night and everyone is invited – dust off your best
Quentin Tarantino themed outfit to join us for delicious food and a glass of something bubbly, before we hit the dancefloor to throw shapes like Mia and Vincent.
Among the festivities, we also look forward to honouring the first of our colleagues to become Fellows as part of the newly launched ADI Fellowship Pathway. This was recently implemented in order to complement the skill development necessary for success in implantology and better support individuals in each stage of their career.
This will be an event for the entire dental implant team, putting education and connection front and centre. We’re heading to Liverpool so it will be a pleasure to welcome you all to my home town. Easily accessible from all areas of the UK, this is an iconic city of culture, history, and music – and I know all the best spots for anyone wanting to make the most of their visit!
The ADI Team Congress 2027 – “The Future in Focus. Four Decades of Implant Excellence.” – will be hosted on 15–17 April at the ACC in Liverpool. It will be an opportunity to look back at our progress in the last four decades and to push the boundaries even further. We share a goal to constantly enhance the implant treatment available to our patients. By sharing best practices, inspiring each other, and collaborating to develop new approaches to complex clinical situations, we can change the lives of even more individuals around the world. I invite you all to save the dates in your diary and make sure you don’t miss the ADI Team Congress 2027 – “I think this just might be my masterpiece…”
The future in focus. four Decades of implant excellence.
ADi Team Congress 2027
ACC Liverpool 15-17 April
Liverpool energy. ADi expertise.
Book today at www.adi.org.uk ADI members have access to discounted tickets n
About the author
Dr pynadath George, GDC-registered specialist oral surgeon and president of the ADi (Association of Dental implantology).
Go digital with Dr Diana Tadros
Digital dentistry continues to level-up all elements for patients and practitioners: improved diagnostics, greater patient comfort, faster treatments, superior precision and less chair time.
Incorporating digital products and services, especially cutting-edge solutions, is an inevitability to enhance your treatments and grow your practice. But discovering these solutions and identifying which ones will most benefit your daily workflow can be difficult, with extra considerations for cost and having enough space in the practice to house larger products. This is where hearing from leading dentists can help.
Digital demonstrations
Dr Diana Tadros delivers masterful cosmetic dental treatments from her boutique private practice in Fort Lauderdale, Florida. A Fellow of the American Academy of Cosmetic Dentistry (AACD), Diana also teaches courses on in-house digital design at the eminent Kois Center, and is the founder of Exocad Elite, a training continuum that simplifies 3D printing and digital workflows for long-lasting reliability and a more streamlined workflow.
Dr Tadros will be delivering both a handson workshop and a lecture at the BACD 22nd Annual Conference. The workshop, “Dive into Digital Wax-ups”, will position cosmetic dentists at the cutting-edge of technological development.
Dr Tadros expands: “The course will take you through the unparalleled power of digitally designing your own cosmetic waxups in the 3D realm, and being able to do so during a consultation appointment by utilising Exocad. From smile design concepts in the digital world, patient and lab communication, to tips and tricks on setting up your cases for optimal results, learn about the power of functional mock-ups and logically driven treatment plans to drive patients to a more solid understanding of their treatment and occlusion, while designing aesthetic cases that are built to last.
“Delegates who attend will gain a better understanding of the anatomy of a digital wax-up, learn how Exocad can be utilised to enhance communication channels between patient and lab, and master the basic functions of Exocad design software.”
Talk of the town
Dr Tadros’ lecture will highlight the power of the digital workflow and how it can optimise multiple aspects of your workflow. Titled “The Digital Road to Treatment Success”, it will bring the future to the present; a session on the innovative products and
services that can enhance your cosmetic dental treatments. Dr Tadros divulges:
“This interactive, content-packed lecture guides participants through the full digital workflow – from designing cases with precision and bringing them to life with 3D printing, to presenting them in a way that truly connects with patients. We’ll cover how to maximise digital tools in everyday practice, simplify your workflow, and boost case acceptance through more engaging and confident treatment presentations for varying case types. Further, we’ll dive into how to translate your treatment plans and strengthen communication with your specialists and labs to achieve optimal results. Whether you’re just starting with digital dentistry or looking to sharpen your skills, this session is packed with practical tips, real cases, and ideas you can use right away.
“For attendees of the talk, there are five learning objectives:
• Understand the key principles of digital dental design and how to translate them into clinical practice
• Navigate in-office 3D printing, from choosing the right printer to optimising print workflows for various case types
• Present treatment plans more clearly and confidently using digital visuals and tools
• Build a seamless digital workflow that connects diagnostics, design, fabrication, and communication
• Identify common challenges in digital adoption and learn how to overcome them in a general or specialty practice
This is a comprehensive presentation on the limitless possibilities of digital dental design, and the superb outcomes it leads to – for both your patients and your practice.”
The BACD 22nd Annual Conference takes place in London on 13-14 November 2026. Held at the Royal College of Physicians, this year features a 2-day programme jam-packed with excellent speakers, intriguing workshop topics and a range of networking opportunities that make the event a calendar highpoint for all those with a passion for cosmetic dentistry.
Dr Tadros’ focus on digital dentistry supports the conference’s theme of “Future Frontiers in Cosmetic Dentistry”. Designed to guide dental professionals towards new ideas and prepare them for the technologies and potential challenges on the horizon, the theme is a reflection on the BACD’s commitment to leading by example; empowering dental professionals with the knowledge and skills needed to deliver ethical cosmetic dental treatments that last.
Don’t miss out on game-changing insights from international speakers – book your place at the BACD 22nd Annual Conference.
BACD 22nd Annual Conference 13- 14 november 2026 royal College of physicians
For further information and enquiries about the British Academy of Cosmetic Dentistry, visit www.bacd.com n
Smile Month at 50
A moment to reflect, and a call to lead
Each year, Smile Month (formerly National Smie Month) offers us an opportunity to refocus on prevention, patient education and the fundamentals of good oral health. But this year feels different.
As the campaign reaches its 50th anniversary, I had the opportunity to attend an event that invited not just celebration, but honest reflection about how far we have come, and more importantly, where we need to go next.
Reading the Oral Health Foundation’s latest report, Oral Health: From Treatment to Prevention, I found myself feeling both proud of our profession and challenged by the report’s findings. Because while the story of the last 50 years is one of real progress, the next chapter will require something more of us, not just as clinicians and supporting teams, but as leaders.
There is no question that dentistry has transformed lives over the past half-century.
Prevention, an area I am deeply passionate about, is moving beyond an ambition and we are making tangible headway in bringing it into the core of our practice. Through national campaigns, fluoride toothpaste, empowered teams and consistent patient messaging, we are beginning to see a shift in the focus from reactive care to proactive health. We are starting to see this in our patients, in healthier mouths, retained dentition and improved awareness. Nationally, oral health outcomes have improved significantly, reflecting decades of commitment across the profession.
However, that is only part of the picture. What struck me most in this year’s findings is not the progress, it is the persistence of preventable disease:
• Nearly one in three adults still has tooth decay
• Two in five do not attend regularly
• One in four are not brushing twice daily with fluoride toothpaste
To me these are systemic issues. When we look beyond the numbers, this is about people: patients living with avoidable pain, reduced confidence, and compromised wellbeing. It’s about families who don’t access care until they have no choice, and communities where oral health simply isn’t prioritised because other pressures take precedence. Many of us are experiencing this within our own services: later presentations, more complex needs, and patients who have already fallen through the cracks.
If there is one message that stands out from both the report and wider research, it is this: inequality is no longer a side conversation, it is the central challenge for oral health. We know that those in more deprived areas experience higher levels of disease, more pain, and reduced access to care. We also know that access itself has become a barrier, with patients travelling long distances or disengaging from services altogether.
From a leadership perspective, this is where the conversation must shift. Because this is not simply about individual behaviour, it is about systems, access, and how care is designed and delivered. This means the solution cannot sit solely with the patient. It sits with all of us.
National Smile Month has always been exceptional at raising awareness. The messaging is clear, consistent, and evidence-based, but awareness alone is not enough anymore. As a profession, we have a responsibility to translate that awareness into action, into tangible change within the environments we influence.
For me, that starts with a fundamental question: are we truly designed around prevention, or are we still structured around treatment? I ask this because despite everything we know, the system often pulls us back towards reactive care. Targets, access pressures, and patient demand can all shift focus away from prevention, even when it remains our stated priority.
One of the most important shifts highlighted in the report is the role of the wider dental team, and I believe this is one of our greatest opportunities. Prevention does not sit with one clinician; it is a collective responsibility. Hygienists, therapists, and nurses all have a critical role to play in influencing behaviour, delivering education, and building patient trust.
As leaders, our role is to remove barriers, create clarity, and empower our teams to work at the top of their scope. By giving our teams the time and structure to deliver meaningful preventive conversations, embedding consistency in messaging across all patient touchpoints, and supporting confidence in delivering behaviour change, not just clinical care. If you caught my
session at the Dentistry Show you would have heard me say that when teams feel empowered, the opportunities can be significant and that includes prevention becoming a culture.
On reflection I often come back to the fact that prevention rarely happens with grand gestures. It happens in the small, consistent moments. A conversation at the chairside. A nurse reinforcing advice. A hygienist building trust over time. These moments matter. When they are delivered consistently, across every interaction, they have the power to shift behaviours - not instantly, but sustainably. The challenge for our profession is ensuring that these moments are not lost within busy clinical environments.
For me, this year’s Smile Month is less about promoting key messages – we already know them – and more about asking how effectively we are bringing them to life. Are we reaching the patients who need us most? Are we designing services that reduce, rather than reinforce, inequality? Are we consistently prioritising prevention, even under pressure? These are not easy questions, but they are necessary ones.
If the last 50 years have been about building awareness, the next 50 must be about embedding change, which will not happen by default. It will require leadership at every level of dentistry, from my roles such as mine that focus on clinical services, strategy and policy, to my fellow colleagues in the practice. As a profession, we have already proven what we can achieve, now we are faced with the challenge to ensure that this progress is shared, so no patient, no matter their circumstances is left behind. Improving oral health isn’t just about someone’s smile, it’s about the kind of system we choose to lead, and who that system ultimately serves. n
About the author
Lianne scott-Munden, Clinical services Lead at Denplan.
EasyFit
Helps patients make interdental brushing a routine that sticks.
The innovative conical brush head glides smoothly between a range of interdental spaces to remove plaque effectively – making it easy and comfortable for patients who are just starting out.
Available in sizes S/M and M/L.
TePe
Endurance in dentistry
What ultra marathons have taught me about being a dental hygienist
Most people do not immediately connect ultra marathons with dentistry. One involves mountains, exhaustion, mud, sleep deprivation and running distances most people avoid driving. The other involves clinical precision, prevention, patient communication and working in confined surgery spaces for hours at a time.
Yet for me, the two are deeply connected. Alongside working as a dental hygienist, I run ultra marathons and regularly train for endurance events. Over time, I have realised that many of the qualities required to complete an ultra are the exact same qualities needed to sustain a long-term career in dentistry: discipline, consistency, resilience, preparation and the ability to remain calm under pressure.
The parallels are surprisingly strong.
Dentistry is an endurance profession
Dentistry is often viewed as a clinical profession built around technical skill, but physically and mentally it is also an endurance profession.
As hygienists and therapists, we spend hours maintaining concentration while working in static postures, often with limited breaks and high clinical demand. The profession requires fine motor skills, communication, emotional intelligence and physical stamina simultaneously.
Patients may only see a 30- or 60-minute appointment. What they do not see is the cumulative effect of maintaining that level of focus all day, every day.
Running ultra marathons changed how I approached this.
Ultra running is not about sprinting. It is about pacing, energy management and consistency over long periods of time. That mindset translates directly into clinical practice. Dentistry is not won in one perfect day. It is built through sustainable habits repeated over years.
Mental resilience and pressure
One of the biggest lessons endurance sports teach is how to manage discomfort.
During an ultra marathon, there will almost always be moments where you want to stop. Your legs hurt, your energy drops and your brain starts negotiating with you. The challenge becomes less physical and more psychological. Dentistry can feel similar at times.
Clinicians manage demanding workloads, anxious patients, time pressures, regulatory standards and increasing expectations. Burnout within dentistry is discussed far more openly now than it was previously, and rightly so. Many dental professionals spend years prioritising patient care while neglecting their own physical and mental wellbeing.
Running became an outlet that helped me manage that pressure.
Training provides structure outside work. It clears mental fatigue and creates space away from clinical environments. More importantly, it reinforces confidence in your ability to tolerate difficult situations and continue moving forward even when things become uncomfortable. That resilience transfers back into practice.
The importance of physical health in clinical careers
Musculoskeletal strain remains one of the biggest occupational challenges within dentistry. Neck pain, back pain and shoulder problems are incredibly common across the profession.
Fitness has helped me significantly with this aspect of clinical work.
Strength training, mobility work and endurance conditioning improved not only my general health but also my posture, stamina and recovery between clinics.
Spending hours leaning over patients places enormous strain on the body, and I became much more aware that if I wanted longevity within dentistry, I needed to treat physical health as part of my professional responsibility.
There is sometimes a misconception that fitness needs to be extreme to be beneficial. It does not.
You do not need to run ultra marathons to improve resilience or wellbeing. Walking regularly, strength training a few times per week, improving mobility or simply building better recovery habits can make a substantial difference to energy levels and career sustainability.
The reality is that dentistry can be physically unforgiving if clinicians do not actively look after themselves.
prevention: in sport and dentistry
Another strong overlap between ultra running and dentistry is prevention.
In endurance sport, success is rarely determined by one exceptional training session. It is usually determined by the small things done consistently over time: hydration, nutrition, recovery, sleep, pacing and injury prevention.
Dentistry operates exactly the same way.
As hygienists, much of our role revolves around preventing disease progression before patients experience significant problems. Daily habits matter far more than occasional dramatic interventions.
One thing I have found particularly interesting is how athletes often understand the concept of prevention extremely well in sport while overlooking it in healthcare.
Runners will invest heavily in trainers, recovery tools and nutrition plans to avoid injury, yet sometimes neglect routine dental care until pain develops.
There is also growing awareness around the relationship between oral health and overall systemic health, particularly regarding inflammation, cardiovascular health and performance. Athletes increasingly recognise that health cannot really be compartmentalised. Oral health forms part of the wider picture.
running and patient communication
Ultra running has unexpectedly improved how I communicate with patients too.
Endurance events expose you to people from every background imaginable. You spend hours talking to strangers at aid stations, on trails and during events. You learn quickly how important encouragement, reassurance and mindset can be when someone is struggling.
Patients are often similar. Many arrive anxious, embarrassed or overwhelmed about their oral health. Some have avoided dental care for years. Others feel frustrated by repeated setbacks.
As clinicians, technical skill matters enormously, but communication often determines whether patients feel capable of making long-term changes.
Running taught me patience. Progress rarely happens instantly, whether in endurance sport or oral health behaviour change.
Discipline over motivation
People often ask what motivates someone to run ultra marathons. The truth is that motivation is unreliable.
Some mornings you do not want to train. Some days you do not feel energetic or inspired. The same can apply professionally. Not every clinic day feels exciting. Not every task feels rewarding.
What matters is discipline and routine.
Both dentistry and endurance sport reward consistency far more than intensity. Small efforts repeated consistently over time produce results. That applies equally to fitness, patient care, periodontal treatment outcomes and career progression.
finding identity outside dentistry
One thing I believe is increasingly important within healthcare professions is maintaining identity outside work.
Dentistry can become consuming very easily. The profession demands precision and responsibility, and many clinicians tie their self-worth closely to performance at work. Having something completely separate from dentistry helps create balance.
For me, running provides that separation. It removes me from surgery environments, screens and clinical pressures. It also reminds me that discomfort, setbacks and difficult periods are temporary. In ultra marathons, things can change dramatically within an hour. Bad moments pass. That perspective is useful professionally as well.
Looking forward
The culture around wellbeing within dentistry is slowly changing for the better. There is more openness around burnout, stress management and career sustainability than there once was. I believe physical fitness should form part of that conversation.
Not because every dental professional needs to become an endurance athlete, but because healthcare professionals often spend so much time looking after others that they neglect themselves in the process. Ultra marathons have taught me lessons far beyond running. They have improved my resilience, physical health, discipline and mindset as a clinician. They have also reinforced something I regularly discuss with patients: long-term health is rarely built through dramatic short-term actions. It is built through consistent habits maintained over time. Whether in dentistry or endurance sport, prevention and preparation will always outperform crisis management. n
About the author
rafina o’Brien is a dental hygienist, presenter, and speaker with experience across community, nHs, and private dentistry. Alongside her clinical career, she has served across the British Army and royal navy, shaping her approach to leadership, resilience, and patient care.
she is also involved in charitable healthcare initiatives supporting vulnerable communities and is passionate about empowering women to step forward with confidence in healthcare and leadership spaces. outside dentistry, rafina takes part in endurance challenges to raise awareness and support charitable causes, combining her passion for fitness, resilience, and community impact.
Six ways to avoid frown lines on facial aesthetics
The DDU’s Una Man explores the dento-legal aspects of cosmetic practice and plans for tougher regulation
The desire to look good and awareness of non-surgical ‘tweakments’ has driven a boom in facial aesthetics.
According to researchers at UCL, there were 19,701 practitioners working in 2025, compared with 3,667 who were identified in a 2023 national study.
As experts in facial anatomy and giving injections, entrepreneurial dental professionals have a head start in cosmetic practice. But it’s important to uphold professional standards as the GDC could still investigate fitness to practise concerns that might damage confidence in dentistry.
Practitioners should also be aware of the changing legal picture, with both the Scottish and UK Governments planning to impose tougher regulation on cosmetic providers.
Here are six dento-legal areas that need particular attention:
1. Training
The GDC expects you to be “sure that you have undertaken training which is appropriate for you and equips you with the appropriate knowledge and skills to perform a task safely.”
Choose an accredited training programme with clearly defined
learning outcomes, like the ones approved by the Joint Council for Cosmetic Practitioners (JCCP). Ensure the programme is at the right level as some aren’t suitable for firstline training.
Look out for new training requirements from the Scottish and UK Governments, in case you need further training. Regular CPD will help maintain your knowledge and skills.
2. patient assessment and consent
Explore what the patient expects at the outset as part of an open and honest conversation. You must be sure the treatment is reasonable, in line with accepted practice and in the patient’s best interest, taking into account their psychological state. Don’t be afraid to say no if you don’t judge treatment to be appropriate. Ensure the patient is fully informed about what the treatment involves and consents. This includes the costs, risks, benefits and the alternatives, including not proceeding with treatment. The GDC’s guidance on consent states that it is a continuous process, and not a one-off event. Encourage them to ask questions and make a complete, clear and contemporaneous record of consent discussions.
3. prescribing
Prescription only medicines (POMs) can only be prescribed by a dentist who should properly assess the patient first.
The prescribing dentist is responsible for the decision to delegate administration and needs to ensure the person concerned is appropriately trained, competent and that appropriate standards are being upheld. The GDC’s guidance on prescribing medicines also says dentists must not remote prescribe for non-surgical cosmetic procedures.
The Botulinum Toxin and Cosmetic Fillers (Children) Act and the new Non-surgical Procedures and Functions of Medical Reviewers (Scotland) Bill make it illegal to administer botulinum toxin and cosmetic fillers to under-18s.
4. premises
The GDC says you “must treat patients in a hygienic and safe environment” which includes protocols for medical emergencies and reporting patient safety incidents to the appropriate national body (such as the Yellow Card scheme).
More stringent regulation is planned under the new Scottish legislation which will restrict nonsurgical cosmetic procedures to premises which are registered with Healthcare Improvement Scotland. The UK Government is expected to introduce standards on hygiene, infection control and premises as part of its planned licensing and regulation scheme.
5. promotion
Marketing must be factual, verifiable and avoid unjustifiable claims. Whether it’s for a website, social media or print, ensure content complies with the GDC’s guidance on advertising your services and the Committee of Advertising Practice (CAP) Code. CAP guidance on the marketing of cosmetic interventions covers photographs and testimonials. Remember that POMs such as botulinum toxin cannot legally be advertised directly to the public. The MHRA’s Blue Guide sets out the law surrounding advertising medicines.
6. indemnity
The GDC expects you to be appropriately indemnified for all work so ask your dental defence organisation or provider about this. n
Founded in 1987, by Robert Hughes, Triple O Dental Laboratories has become one of the UK and Europe’s leading orthodontic and orthopaedic laboratories, trusted by clinicians for innovation, precision, and clinical support. From advanced orthodontic appliances and aesthetic aligner systems to full orthodontic solutions, TMD support, and cutting-edge digital workflows, Triple O combines decades of expertise with modern technology to help practices deliver exceptional patient outcomes with confidence.
Our Aligners are made out of
ZENDURA FLX ENDURA
The world leading aligner material
Reduced Treatment Times
Increased Comfort
Highly Stain Resistant
The elastometric middle layer of Ze with the hard outer shell, delivers th and recover from mechanical defo up to 150%, plus better tooth movem competing materials over a 7-10 da
Self-Ligating Brackets elf-Ligating
fast’s renowned self-ligating are desi
Cfast s renowned self ligating brackets are designed to deliver efficient, comfortable, and highly aesthetic tooth movement with reduced friction and improved control throughout treatment
Trusted by clinicians for their simplicity and predictable results, the system allows for faster arch development, smoother alignment, and excellent patient comfort.
Fixed Bracket & Ali ner Course g ixed Aligner
osted
Hosted by Dr Miguel Polonia BDS, MSc Orth.
The Cfast 2 Day Course is designed to help dentists confidently introduce simple, profitable orthodontics into practice using a combination of our advanced Zendura FLX aligner system and our renowned self-ligating bracket system
Across two hands-on days, delegates learn how to diagnose, treatment plan, and manage a wide range of cosmetic orthodontic cases using both fixed and aligner techniques, giving clinicians the flexibility to choose the best solution for each patient while achieving efficient, predictable smile transformations
On-going support after course with our Cfast portal
14 4 hrs CPD rs receive £660 A free Cfast ca c se s or a treatment st s arter kit* case treatment starter er e
Course Dates & Locations ourse &
THE
AWARDS 2026
‘And the winners are’ - Part One
The Probe and Smile proudly present The 2026 Dental Awards
The 2026 Dental Awards marks the 28th edition of this prestigious event that, for more than quarter of a century, has sought to recognise the outstanding individuals and teams whose dedication and drive continues to raise standards throughout the UK dentistry profession.
Winning or becoming a finalist in the Dental Awards is a tremendous accolade that provides a significant boost to the profile of a practice. Not only is the event an opportunity to share in the happiness and success of those who win an award, but it offers the chance to see what fellow dental professionals are doing across the United Kingdom.
Dentist of the Year
Winner: Dr Chloe Harrington-Taylor
Dr Chloe Harrington-Taylor is a truly remarkable denstist, whose passion has shone through during The Dental Awards for several years. Chloe was highly commended last year in this category, and the year before that won the accolade of Young Dentist of the Year. We surely haven’t seen the last of Chloe yet… Many congratulations once again to Dr Chloe HarringtonTaylor, The Dental Awards’ Dentist of the Year 2026.
Highly Commended: Dr Sulaman Anwar
Finalists: Nida Kamal
Dr Wajiha Basir
Young Dentist of the Year
Winner: Awaz Sharief
Many congratulations to Awaz. The judges were impressed by the consistency Awaz has shown in working to improve within the dentistry profession.
Highly Commended: Bethan Elvins
Simran Bains
Commended: Paul Midha
Dr Riaz Sharif
The Dental Awards presentation, which streamed on the-probe.co.uk, as well as on The Probe’s Youtube channel, is available to watch on-demand now. Scan the QR code below to see the winners of The Dental Awards 2026 react to their victories, as well as to discover who was named a finalist in each of the 13 hotly contested categories.
The Dental Awards is sponsored by B.A. International, Colosseum Dental, Dental Elite, Tempdent, and Waterpik, and is presented in association with the Oral Health Foundation, ADAM, BACDT, BADN, BADT, BSDHT, and CDTA.
For more, scan the QR code below to visit the-probe.co.uk/awards/the-dental-awards-2026/
To see the full list of our winners, highly commended, and finalists, and to watch the 2026 Dental Awards Presentation, scan the QR code or visit:
Dental Therapist of the Year – in association with BADT
Winner: Imogen Johnson
Congratulations to Imogen, who impressed judge Debbie Hemington with an excellent entry, demonstrating drive and ambition and breaking barriers. Rhiannon Jones meanwhile was complimentary of the variety of evidence presented and an obvious passion for the role, citing an appreciation for Imogen’s comments about advocacy via the professional organisations and her understanding of how dental therapists can progress together.
Highly Commended: Gulab Singh
Commended: Gemma Cowen
Finalists: Sandy Kaur Khaira
Dental Hygienist of the Year – in association wiht BSDHT
Winner: Rhianna Clarke
Rhianna impressed the judges with an excellent case study in which she took on a challenging patient with multiple considerations to be taken into account. Overall, Rhianna won over some comprehensive submissions and engaging presentation styles.
Highly Commended: Gemma O’Callaghan
Commended: Rafina O’Brien
Finalists: Sandy Kaur Khaira
Lauren Chipman
Dental Nurse of the Year – in association with BADN
Winner: Adrien Chabaud
Judges Preetee Hylton and Rebecca Silver explained that Adrien showed a true passion and desire for dental nursing, going above and beyond what is expected. His commitment to bettering himself and being proactive in the world of dentistry are key to why he won the award for dental nurse of the year.
Highly Commended: Kelly Hunter
Elizabeth Brumby
Commended: Anjali Kale
Keischa Gonzales
Imogen Johnson
Rhianna Clarke
Adrien Chabaud
Immediate loading of an anterior maxillary implant using a guided protocol
d r Ravinder Jhutie describes a case in which immediate dental implant treatment was carried out to restore an upper anterior incisor
TFig. 1 Pre-op maxilla
Fig. 2 Pre-op mandible
Fig. 3 Pre-op temporary restoration
Fig. 4a Digital design of guide 1
Fig. 4b Digital design of guide 2
Fig. 4c Digital design of guide 3
Fig. 5 Surgical guide for implant placement
Fig. 6a Restorative guide with crown
Fig. 6b Restorative guide with crown
Fig. 7a UL1 tooth root pre-extraction
he immediate placement and loading of dental implants in the provision of single maxillary anterior restorations is considered a predictable and safe treatment option, resulting in adequate survival rates and favourable aesthetic outcomes for five years post-surgery. Further contributing to high survival rates is the use of guided implant placement and implant planning software, with research suggesting that a guided approach is less invasive than a standard protocol, requiring less time and causing minimal discomfort. The use of digital planning software is also advantageous, making it possible to plan the position of implants prior to surgery to a high degree of accuracy. This also allows clinicians to anticipate the potential changes or complications that might occur and mitigate these ahead of time.ii
Patient background
Fig. 7b Pre-op radiograph
Fig. 8 Extracted UL1 tooth root
Fig. 9 UL1 site post extraction
Fig. 10a Surgical guide placed
Fig. 10b Surgical guide placed
Fig. 11 CONELOG Progressive-Line Promote plus implant
Fig. 12a Dental implant placement
Fig. 12b Dental implant placement
Fig. 12c Dental implant placement radiograph
A 68-year-old male patient attended the practice with failure of the UL1. He had a temporary restoration provided by his regular dentist, who then referred him for a permanent solution. Overall, the patient’s oral health was good, with a number of existing restorations in the mouth, including an implant at the UR1 (present for 10+ years), and considerable tooth wear present throughout the dentition. The patient was not interested in full-mouth rehabilitation –his primary goal was to restore the function and aesthetics in the anterior region, with a fixed replacement for the UL1.
A range of treatment options were discussed with the patient, including dentures, bridges, and dental implants, ensuring he understood the risks and benefits of each. Ultimately, the patient chose a dental implant as he preferred
Fig. 13 Free gingival graft harvest site
Fig. 14 Connective tissue graft
Fig. 15a Connective tissue graft placed
Fig. 15b Connective tissue graft placed
Fig. 16 Bone grafting
Fig. 17 Dental unit and abutment radiograph
Fig. 18a Crown
Fig. 18b Crown with composite build up
Fig. 19 Crown loaded onto implant
Fig. 20 Healing 4 days post-op
Fig. 21 Healing 14 days post-op
to have a fixed, gold-standard solution.
A comprehensive assessment was then carried out to ensure the patient was a suitable candidate for dental implant treatment, including a 3D scan to assess the bone and the patient’s anatomy, and intraoral scans to facilitate digital planning.
treatment planning
In this case, a guided surgery was preferred in order to facilitate a prostheticallydriven approach. This would ensure that the positioning and angle of the implant was correct, and would create the ideal aesthetic and functional outcome required in the anterior zone.
Additionally, an immediate placement and loading approach was selected for this case. Particular care was required with the mesial and distal soft tissue during removal
of the temporary restoration and extraction of the root – with the aim to keep the surrounding soft tissue intact.
A CBCT and intraoral scans were taken and uploaded to SMOP as well as Smilecloud software for digital planning alongside the dental technician (Sohaib Abouelela at Zenith Dental Labs). This planning stage included designing the surgical guide as well as a digitallyproduced crown. This software allows dental professionals to change the shape of the tooth, enabling the crown to be designed in such a way that the soft tissue graft could grow and expand in an ideal way. The surgical guide was fabricated prior to the appointment in the dental lab, as was the crown, which was then attached to the temporary abutments with composite to create the ideal emergence profile, as well as aid with pink aesthetics.
treatment provision
On the day of surgery, the temporary restoration was removed, and the UL1 root was extracted as atraumatically as possible, with the mesial and distal soft tissue kept intact according to the clinical plan. This ensured that there was a good blood supply between the palatal and buccal area, preserving the health of the bone and soft tissue.
The surgical guide was placed in the mouth, and the site was drilled in accordance with the surgical plan. One screw-mounted 3.8mm x 11mm CONELOG ® Progressive-Line Promote plus implant (Camlog) was placed through the guide, following the treatment plan with precision.
To ensure sufficient soft tissue volume could be achieved at the UL1 site, a free gingival graft was harvested from the palate and de-epithelialised to obtain connective tissue. The soft tissue graft was placed, and stabilised with three sutures (Glycolon 5.0).
A temporary cylinder abutment was then placed, and bone grafting was carried out using MinerOss ® Blend (BioHorizons) – consisting of 70% cortical and 30% cancellous allograft chips. This aimed to fill the jump gap between bone and implant; this was carefully placed in the bone corridor to aid with reliable revascularisation to improve bone volume at the site, and aid stable healing. Following this, the restorative guide was used to place the crown into the mouth. This is done to ensure that the resulting prosthesis will be seated in the correct 3D position, mesially, distally, buccally, and palatally, as was planned on the digital smile design. Once this was confirmed to be correct, the implant was restored out of occlusion with the provisional restoration, and a post-operative radiograph was taken to ensure that the implant and crown were seated correctly.
Outcome and case appraisal
The case went extremely well. The patient and I were very happy with the outcome. The patient was not in pain, and at four days post-op, the site was healing really well.
This was my first time using the CONELOG ® Progressive-Line Promote plus implant, and I was very impressed with its performance. It is a system which
my mentor, Dr Imran Nasser uses, and recommended to me. It is a versatile option for immediate placement and loading, especially as it offered excellent torque values.
Utilising a digital planning system made it really easy to liaise with the dental technician in this case, meaning that we were able to really effectively plan the whole case, including finalising implant diameter and length, ensuring that as much possible has been planned for prior to the day of surgery.
My advice for clinicians who are planning to undertake a similar case would be to take your time – for example, allocating more time than you think you’ll need, booking four hours for what could be a one-hour surgery, removing time pressure and allowing you to give your full focus to the patient in your chair. I personally also find it helpful to write out the treatment steps, so that I feel confident that the treatment plan is being followed with complete accuracy. This systematic approach, along with tools such as digital planning and guided surgery, has had a big impact for me, and has made the results I can achieve consistent and repeatable.
For product information from BioHorizons and Camlog, please visit https:// theimplanthub.com/
Quality Great Price Made in Great Britain
References available upon request about the author Dr Ravinder Jhutie graduated from the University of Birmingham in 2017, and provides a range of treatments, including dental implants. Dr Jhutie has a passion for creating lifechanging smiles for his patients and, in 2022, acquired TopLabs dental laboratory to ensure the quality and precision of the dental prosthetics he provides matches that of his surgical capabilities. He has now sold Toplabs prosthetics and ventured into other industries including The Haulage Family. Dr Jhutie has a wide collection of interests and, as part of his self-development, believes there is value in being uncomfortable to achieve progress
OPTIM Interdental brushes are precision made in the UK, using high tensile strength, plastic-coated, stainless-steel wire at the core, which helps to prevent the brushes from buckling, even on the smallest sizes. They are the same colour coded sizes that practices/ patients are already familiar with and are very competitively priced.
For more information or to request a sample, simply speak to your dealer, scan the QR code or visit https://optim-idb.uk/survey/
Extract and align
d r Rebecca Williams presents an orthodontic treatment for crowding following the extraction of a supernumerary tooth, including the use of power chains and elastics
Awoman in her early 30s presented to the practice with concerns regarding crowding throughout the dentition. She was seeking a solution that would optimise aesthetics, and give her confidence in her smile.
A brief assessment highlighted a supernumerary tooth in her lower lateral dentition, which was exacerbating the crowding. Her oral hygiene was good with no restorative concerns. To understand more, a thorough assessment of the dentition was enacted.
The patient had a Class I skeletal relationship and average FMPA, with average lower face height and no asymmetry. She had a Class I incisal relationship, with a 1mm overjet and an overbite of 3mm. The central line was Class I, and she similarly had a Class I relationship throughout both the left and right molars.
On the left, her canines exhibited a Class I relationship, and the right side had a Class II relationship by half of a unit. The lower arch had crowding throughout the lower 6-10 teeth. Standard radiographs, including an OPG X-ray and bitewings, were taken with no abnormal findings.
The patient was deemed appropriate for orthodontic care and a dedicated treatment plan was devised.
treatment options
Successful treatment would reduce crowding throughout the lower incisors, where it was most prominent, whilst correcting the overjet and overbite that was present. A minimally invasive approach is always preferred. In this case, extraction of the supernumerary incisor was recommended, as this would create space and, therefore, reduce the need for interproximal reduction (IPR).
Clear aligners are a popular orthodontic treatment approach for many individuals due to improved aesthetics and comfort when compared to fixed solutions. However, the patient was advised that traditional fixed braces would provide enhanced control over tooth movement, and aid the movement of the lower anterior teeth after extraction of the supernumerary incisor (LR2).
Other treatments were discussed, including the option of no orthodontic treatment and the continued monitoring of oral hygiene,
but the patient was interested in resolving the crowding. With all relevant information presented, and informed consent attained, the patient elected to undergo fixed orthodontic care with a tooth extraction.
As this was one of my first orthodontic cases utilising the extraction of a tooth, I consulted each step with Dr Pinkoo Bose, a mentor at IAS Academy. Following the completion of many of IAS Academy’s engaging orthodontic courses, I had the skills to carry out such a case, but the guidance of an experienced and knowledgeable professional provides further confidence in the treatment plan; the patient was informed that I would be supported by a mentor throughout the case, and she expressed that she was happy with this approach.
A Spacewize+ assessment was completed to assess the necessary space creation for the desired orthodontic tooth movements, and an Archwize assessment informed the IPR recommendation. This was shared with Dr Bose, and due to the helpful visuals, was shown to the patient to further inform her of the planned care. The use of IPR in the upper dentition was expected to create black triangles, which could be corrected with cosmetic composite restorations alongside tooth whitening after the completion of the orthodontic regimen.
With an appropriate plan in place, and complete patient consent, care could proceed.
First steps
The extraction of the supernumerary LR2 was completed by the oral surgery team within the practice, ensuring the patient had the best available care. She experienced no complications with this, and healing progressed as planned.
IPR was carried out throughout the upper dentition, creating a total of 2.3mm of space, as indicated by the Spacewize+ and Archwize assessments. This equated to 0.3mm IPR canine to canine and 0.4mm at the distal of the canines. Once again, the space created in the lower dentition eliminated the need for further IPR, maximising the conservation of the existing enamel.
Clarity fixed brackets from Solventum were placed using the Clarity Digital Bonding system. This enabled optimal
placement to be planned digitally, and then replicated accurately with full-arch bracket placement, ensuring predictable tooth movement. 0.12 NiTi wires were implemented across the dentition; both brackets and wires were tooth-coloured to maximise aesthetics.
The patient was provided with oral hygiene instruction and advice to optimise the healing of the extraction site.
Progression of care
After a review at six weeks, the wires were replaced in accordance with the pre-planned sequence. Images were regularly shared with Dr Bose, who could provide feedback and recommended amends for the next stages of care, and also confirm when the correct steps were taken; this helped to instil confidence throughout the workflow and ensured the patient received effective care.
As expected, interproximal spaces were created throughout the dentition as treatment progressed. A single power chain is conventionally used to eliminate these; Dr Bose recommended that the use of a power chain both above and below the NiTi wire would work for closing these, accelerating treatment whilst also ensuring accuracy.
During this phase of treatment, it was important to try and match the centre lines as best as possible. Elastics enabled this movement to be controlled, and as it was my first time implementing them, each planned step was shared with Dr Bose for review. A unilateral class 2 traction was implemented on the right side, and a class 3 was implemented on the left. This action of push and pull would ensure optimal movement. Dr Bose provided an annotated image of where to place crimp hooks, and which elastics to use, ensuring these could be provided to the patient without misinterpretation.
Throughout care, the patient experienced build-ups of tartar in the newly created interproximal spaces, which were removed with the help of professional oral hygiene treatment. This ensured periodontal health was maintained throughout care, and is especially necessary in fixed orthodontic treatment when many patients may struggle with thorough plaque removal.
Fig 1. Patient presentation with malocclusion, smile view
Fig 2. Crowding in the upper and lower dentition, anterior view
Fig 3. Lower dentition features a supernumerary incisor (LR2), anterior view
Fig 4. Crowded upper arch, anterior view
Fig 5. Final result, anterior view
Fig 6. Final result in the lower arch with a lingual retainer, occlusal view
Fig 7. Final result in the upper arch, occlusal view
Fig 8. Extraction of the supernumerary LR2 allowed for optimal occlusion, right lateral view
Fig 9. Final result in the lower arch following LR2 extraction, anterior view
Fig 10. Final result in upper arch, anterior view
Fig 11. A successful result, anterior view
Fig 12. Initial presentation and final result, smile view
Final Result
At the end of treatment, the patient’s overjet and overbite were eliminated, with optimal occlusion achieved. The brackets and wires were debonded, and fixed retainers were applied to the lingual surfaces of the upper and lower dentition. Clear removable retainers were also provided for maximum support. Tooth whitening was performed, and any minor spaces left due to IPR were treated with the placement of composite.
The patient, like myself, was happy with the outcome, and delighted with the aesthetic result. I shared the outcome with Dr Bose, who also noted the treatment as a success. If I attempted the case again, I would focus further on the movement of the LR3 into the space created by the extracted supernumerary tooth, as well as wire bending in the final stages of treatment.
Support from an IAS Academy mentor on this case was extremely beneficial, with the ability to see new approaches to the case, and receive confirmation on prospective treatment elements. This ensured that, as my first case with a tooth extraction and the use of elastics, each step was taken with confidence and with the patient’s needs immediately in mind.
The outcome was a success, with a natural-appearing result that treated the present crowding effectively and maximised aesthetic and function. n
about the author
Dr Rebecca Williams is an Associate Dentist with the Cox and Hitchcock Dental Group in Cardiff, Wales. Since attaining her BDS from the University of Wales in 2007, Dr Williams has fueled her passion for aesthetic dentistry and orthodontics with a number of courses from the IAS Academy. She would like to thank Professor Ross Hobson and Dr Pinkoo “Pinks” Bose for all of their support and mentorship, her Principals, David Cox and Robert Hitchcock, for their amazing support, and her Dental Nurse, Robyn Hurley. Dr Williams’ work can be found on Instagram at @ rebecca_dentist_hyrox.
“
I chose Eschmann, as amongst my peers, it was repeatedly recommended as being the best company for quality & reliability
”
Chris Pritchard, Principal Dentist
Call in the experts. Contact us for your FREE Care & Cover package quotation.
With no hidden fees, Care & Cover offers:
• Annual Validation and PSSR certification
• Annual service & software upgrade
• On-site support from our team of over 50 specifically trained engineers
• Unlimited breakdown cover
• Unlimited Eschmann parts & labour
• Technical telephone support
• Enhanced CPD User training
Experience Eschmann excellence at www.eschmann.co.uk, or call us on 01903 753322.
Dentistry Show London
Gain more, grow faster, get ahead
Following the success of the British Dental Conference & Dentistry Show (BDCDS) 2026 in Birmingham this May, attention is already turning towards the capital as Dentistry Show London (DSL) prepares to return to Excel London on Friday 9 and Saturday 10 October 2026.
BDCDS welcomed more than 10,300 delegates across two busy days and reinforced the continuing demand for events that combine practical education, networking and innovation. Alongside world-class speaker sessions and handson learning opportunities, delegates explored the latest technologies and products from over 400 suppliers and manufacturers, while new theatres and show features such as DentalPod and the Rising Stars Student Competition, helped create a more interactive and engaging experience across the show floor. That momentum now continues at Dentistry Show London, where many of the same themes shaping dentistry today, including business growth, workforce pressures, artificial intelligence and digital innovation, will take centre stage once again.
Practical conversations for modern dentistry
For many dental professionals, the value of attending in-person events increasingly comes down to practicality. Delegates are looking for ideas they can take back into practice immediately, alongside honest conversations about the realities of working in modern dentistry.
DSL’s 2026 programme reflects that shift. Alongside clinical education, the event will focus heavily on the operational and business challenges affecting practices across the UK. Confirmed sessions will explore topics such as standing out in a competitive market, introducing medical aesthetics into practice, attracting and retaining the future workforce, and understanding the impact of NHS contract reform six months on. The aim is not simply to discuss trends, but to provide practical insight into how practices can adapt, grow and remain resilient in a changing profession.
Technology and innovation will also feature strongly throughout the two-day programme, particularly around artificial intelligence and digital dentistry. Following the strong interest in AI discussions at BDCDS Birmingham, DSL is expected to continue those conversations with a strong emphasis on practical application. The event will explore how AI and digital systems may support more efficient workflows, improve communication, reduce administrative burden and enhance the patient experience within everyday practice.
As dentistry continues to evolve, clinicians are becoming increasingly selective about where they spend their time. Events that combine education with genuine relevance, practical takeaways and opportunities for meaningful discussion are likely to offer the greatest value.
More than lectures and lanyards
The appeal of Dentistry Show London extends well beyond traditional lecture-based learning. Delegates
This year’s Show will feature seven CPD-accredited theatres, more than 100 speakers and an extensive exhibition floor showcasing over 180 leading suppliers, manufacturers and service providers. Over 4,000 visitors are expected to attend over the two days with over 100 content hours available.
Panel discussions are expected to play a larger role in the 2026 programme, alongside live demonstrations and interactive sessions designed to encourage practical learning and open debate. For many delegates, hearing how others are approaching similar challenges can be just as valuable as the formal CPD itself.
Networking also continues to be one of the biggest draws for attendees. Reflecting on previous events, many delegates have highlighted the opportunity to reconnect with colleagues, meet new partners and exchange ideas with professionals facing similar pressures within practice.
DSL will once again bring together practice owners, associates, practice managers, dental hygienists, dental therapists, dental nurses and dental technicians under one roof, reflecting how interconnected the modern dental team has become.
Whether delegates are looking to strengthen clinical knowledge, explore new technologies, build confidence in their next career step or identify fresh ideas to support business growth, DSL aims to provide relevant insight for every member of the practice team.
the value of coming together
The combination of education, innovation and connection is unparalleled at DSL. Previous visitors have commented on the impact of having a mixture of hands-on experience and education in one place. Eddie Crouch, Chair of the BDA Board, praised the atmosphere of previous events, calling the Show ‘a brilliant mix of CPD, innovation and networking.’ There are numerous opportunities for collaboration and conversation across the profession, helping to build a sense of connection which has become increasingly important across dentistry. While experiences across the profession may differ, many of the conversations currently happening within practices are remarkably similar. Recruitment pressures, financial challenges, patient expectations, technological change and workforce wellbeing continue to affect practices of all sizes.
By bringing those conversations together under one roof, Dentistry Show London creates an opportunity for delegates to gain fresh perspective, exchange ideas and return to practice with renewed confidence.
Whether attendees are looking to streamline workflows, improve patient communication, strengthen team culture or better understand the future role of AI within dentistry, DSL 2026 is designed to help dental professionals gain more, grow faster and get ahead. n
Dentistry s how London 2026 takes place at e xcel on 9 and 10 October.
For more information and to register interest, visit
@dentistryshowCS
Dentistry Shows
The Dentistry Show
@dentistryshowCS
Dentistry Shows
The Dentistry Show
@dentistryshowCS
Dentistry Shows
The Dentistry Show
Gain more, grow faster, get ahead.
Dentistry Show London stands at the centre of a profession in transformation. As AI reshapes diagnostics, private dentistry grows, workforce dynamics evolve, and NHS reform shapes care, DSL unites the sector to navigate what’s next. With 100+ leading speakers, 100+ hours of Enhanced CPD education, and 180+ exhibitors, it delivers practical insights, new connections, and real opportunities, helping practices and teams thrive in a rapidly changing UK dental landscape.
london.dentistryshow.co.uk
Planmeca UK celebrates 10 years of innovation in British dentistry
As it marks its 10th anniversary as a subsidiary of Planmeca Oy, Planmeca UK reflects on a decade of development with a direct connection to a global innovator and one of the industry’s most respected manufacturers. Recognised worldwide for pioneering dental units, exceptional 2D and 3D imaging devices and comprehensive software solutions, Planmeca has been delivering Scandinavian engineering to forward-thinking customers for more than 50 years. Over the past ten years, Planmeca UK has become a widely known member of the British dental landscape supporting practices with advanced equipment, dependable service, and a hands on approach to customer engagement.
From launching a mobile showroom to strengthening its dealer network, expanding its engineering team to establishing dedicated Territory Manager support, Planmeca UK has spent its first decade building a foundation of trust and innovation.
Dealer network and dedicated territory managers
Planmeca UK’s success has its roots in a dedicated dealer network, who display technical competence, quality service, and long term commitment
to the industry. Combining worldwide innovation with local expertise, resulting in stress-free installations and onboarding, as well as ongoing support wherever it’s needed.
Another key strength of Planmeca UK’s service model is its team of designated Territory Managers, each responsible for supporting both dealers and end users within their region. Their role is central to ensuring that every practice receives consistent, knowledgeable, and personalised support when they need it.
Offering guidance on product selection, hands-on demonstrations, and support on workflow planning, our representatives provide support for customers at a local-level. This dual support structure strengthens relationships across the entire supply chain and ensures that every customer, both dealers and clinicians, benefits from Planmeca’s expertise.
Dedicated support and skilled engineers
Complementing its dealer network and Territory Managers, Planmeca UK employs a team of factory trained engineers who provide both on site and remote technical support. Their expertise spans the entire Planmeca portfolio, including dental units, imaging systems, and software platforms. Support services include remote diagnostics and troubleshooting, preventive maintenance guidance and assistance with digital workflow integration and upgrades. A support model that ensures fast, efficient solutions - often resolving issues without the need for a visit.
Dedicated in-house customer support is also available for both end users and dealers alike, with common spare parts available locally to help minimize any kind of downtime to the
dentist. And for parts despatched from the Planmeca factory in Helsinki, you can expect next day delivery on orders received by noon.
Plandemo: Bringing the showroom to the practice
One of Planmeca UK’s standout achievements is the launch of Plandemo, the company’s very own mobile showroom. Designed to bring the full Planmeca product experience directly to the entire dental team, Plandemo has brought a new approach to how clinicians explore and trial new equipment.
Removing the inconvenience of taking time out of the day to travel to a showroom, clinicians are able to try out dental units, take live patient scans, discover digital workflow solutions – all on the doorstep of their dental practice. This innovative hands-on approach has made it easier than ever for practices to evaluate technology in a real world context, at a time that suits them!
A decade of progress, with more ahead
The next decade promises even more innovation to come, and Planmeca UK is poised to continue leading the way.
As dentistry continues to evolvewith AI enhanced imaging, and smarter treatment environments - Planmeca UK remains committed to supporting clinicians with all the technology and expertise they need.
For more information
• Phone: 02476 994160
• Email: ukmarketing@planmeca.com
• Web: www.planmeca.com
A decade of progress
Making sense of the new employment rights changes in dentistry
Beth Honey explores what the latest employment rights reforms mean for dental practices, offering practical insight into the changes already in force and the further developments practices should be preparing for later this year and into 2027
Aims
The aim of this article is to explore the latest employment rights reforms affecting dental practices, focusing on the practical implications of the changes already in force and the further developments practices should be preparing for through 2026 and into 2027.
Learning objectives:
On completing this Enhanced CPD session, the reader will be able to:
• Understand the key employment rights reforms already affecting dental practices following the implementation of the Employment Rights Act 2025
• Recognise where changes to Statutory Sick Pay, parental leave, whistleblowing protections and holiday pay records are most likely to affect day-to-day practice management
• Identify the practical steps practices can take to support compliance, documentation and consistent people management processes
• Understand the further employment law developments due through late 2026 and 2027, including the implications for harassment prevention and unfair dismissal processes
Learning Outcome: A,B,D
The Employment Rights Act 2025 represents one of the biggest shifts in UK employment law for many years and, while some of the most widely discussed reforms are still to come, several important changes are already affecting dental practices.
For practice owners and managers, that can understandably feel like a lot to absorb alongside the everyday realities of running a busy practice. Recruitment pressures remain high across dentistry, teams are already balancing increasing patient demand with compliance responsibilities, and many employers are trying to interpret what these reforms will mean day-today rather than simply in legal terms.
The good news is that a substantial number of practices may already have the right foundations in place. In many cases, these reforms formalise processes that responsible employers will already be familiar with, but they also reinforce the need for consistency, documentation and ensuring managers understand how policies should be applied in practice.
With that in mind, understanding where the immediate operational impact is most likely to appear can help practices focus their attention where it matters most.
Where practices should focus first
One of the most immediate changes for dental practices is the reform to Statutory Sick Pay (SSP), which came into force on 6 April 2026. SSP is now payable from the first full day of
sickness absence, with the previous three-day waiting period removed, while the lower earnings threshold has also been abolished.
Employees whose earnings previously fell below the qualifying threshold may now receive SSP at 80% of their average weekly earnings, or the standard SSP flat rate, whichever is lower. For many practices, this will involve reviewing payroll and absence management processes to ensure they reflect the updated requirements, particularly for part-time and lower-paid employees.
Alongside SSP, practices also need to review their approach to paternity leave and unpaid parental leave, both of which are now day one rights. Until recently, employees needed 26 weeks of service to be eligible for paternity leave and one year’s service to take unpaid parental leave, but those qualifying periods have now been removed.
In practical terms, this means a new starter could request parental leave during a probationary period, something many practices may not previously have encountered. While situations like this are unlikely to become common occurrences, they do reinforce the importance of making sure onboarding processes, staffing plans and management approaches reflect the updated position.
Practices should also be aware of the Bereaved Partner’s Paternity Leave Regulations 2026, which came into force on 6 April. Where a child’s primary carer dies within the first year following birth or adoption, the surviving partner now has a day one right to take up to 52 weeks of unpaid leave.
Getting records and processes in order
The reforms also increase expectations around accurate and accessible record keeping. Many dental practices will already have systems in place to manage annual leave and payroll, but employers are now legally required to maintain formal holiday pay records, including details of leave taken, payments made in lieu of untaken leave and how holiday pay has been calculated, with records retained for six years.
Failure to comply is a criminal offence, and the Fair Work Agency, which launched in April 2026, has enforcement powers in this area. This is particularly important for practices with
part-time employees, irregular working patterns or variable-hours contracts, where holiday pay calculations can often become more complex.
While changes like this inevitably involve some administrative review, many practices find that clearer and more consistent record keeping ultimately makes employment processes much easier to manage dayto-day. When records are centralised and well-organised, it becomes far simpler to respond confidently to queries from employees, regulators or external bodies if they arise later.
This focus on clear and consistent processes has become even more relevant as the Fair Work Agency brings together several existing enforcement
Six practical steps to prioritise now
While some of the wider reforms are still to come, several important changes are already in force and worth reviewing across the practice now. If you have not yet revisited your processes following the recent reforms, these are some of the key areas to focus on first:
1. Ensure payroll systems are set up to pay SSP from the first day of absence, with no lower earnings threshold
2. Review paternity and parental leave policies to remove previous qualifying service requirements
3. Make sure managers understand the extended whistleblowing protections relating to sexual harassment concerns
4. Check that holiday pay records are being stored in a compliant format and retained for the required six-year period
5. Revisit redundancy procedures if any restructuring or staffing changes may be on the horizon
6. Start preparing now for October 2026’s strengthened duty around preventing sexual harassment, including third-party harassment involving patients.
functions, including National Minimum Wage enforcement, within a single body. While employment issues have traditionally been associated mainly with tribunal claims after a dispute has arisen, there is now far greater emphasis on employers being able to demonstrate that systems, procedures and records are compliant from the outset.
There have also been important changes relating to collective redundancy consultation. While many individual dental practices may never reach the threshold where collective consultation applies, triggered when 20 or more employees at a single establishment are proposed for redundancy within a 90-day period, the potential consequences of getting the process wrong have increased significantly.
If an employer fails to comply with its collective redundancy consultation obligations, the maximum protective award a tribunal can make has doubled from 90 days’ pay to 180 days’ pay per affected employee.
Sexual harassment and whistleblowing changes
Some of the most important changes introduced this year relate to whistleblowing protections and sexual harassment. Disclosures relating to sexual harassment are now explicitly recognised as protected disclosures under whistleblowing law.
This means employees who raise concerns about sexual harassment have formal protection from detriment or dismissal linked to making that disclosure, on top of any existing discrimination or harassment protections. Within dentistry, concerns have the potential to relate to interactions involving either colleagues or patients, reinforcing the need for clear processes so team members feel supported and concerns can be managed correctly, where needed.
Most practices will already be supporting team members appropriately in these situations, with the reforms simply reinforcing the importance of clear processes, consistent handling of concerns and appropriate documentation.
This area will become even more significant in October 2026, when the duty on employers strengthens further from taking ‘reasonable steps’ to taking ‘all reasonable steps’ to prevent sexual harassment, including harassment involving third parties such as patients. Tribunal time limits for bringing claims are also due to increase from three months to six months.
In practical terms, this places greater responsibility on employers to demonstrate that preventive measures are active, understood by the team and consistently applied in day-to-day practice life, rather than existing only within written policies.
For many practices, now is therefore a sensible time to review harassment policies, manager training and reporting procedures before the next phase of reform comes into force in the autumn.
Preparing now for the next wave of reform
While the 2026 changes are significant in themselves, many practices are already thinking ahead to the reforms due in 2027, particularly around unfair dismissal rights.
From January 2027, the qualifying period for unfair dismissal protection is due to reduce from two years to six months, while the compensation cap for unfair dismissal awards is also being removed. For practices, this is likely to place greater emphasis on recruitment processes, probationary reviews, performance management and documentation from a much earlier stage of employment. That does not mean practices should become hesitant about recruitment or anxious about managing teams. However, it does reinforce the importance of having clear expectations, regular review processes and well-documented
To
CPD Questions
1.What change has been made to Statutory Sick Pay (SSP) from 6 April 2026?
a) SSP can only be claimed for absences longer than three days
b) SSP is now payable from the first full day of sickness absence
c) SSP is no longer available to part-time employees
d) SSP is only available after one week of absence
2.Why are the new holiday pay record requirements particularly important for practices with part-time or variable-hours staff?
a) Practices must calculate holiday entitlement monthly
b) Variable-hours staff no longer qualify for paid annual leave
c) Holiday pay calculations can often become more complex
d) These employees are excluded from statutory holiday entitlement
3.Under the updated whistleblowing protections, what are employees protected from if they raise concerns about sexual harassment?
a) Detriment or dismissal linked to making that disclosure
b) Mandatory mediation meetings
c) Changes to their working hours
d) Having concerns investigated formally
4.What will the strengthened duty on employers from October 2026 require practices to demonstrate?
a) That all policies are reviewed every month
b) That preventive measures are active, understood by the team and consistently applied in day-to-day practice life
c) That all staff have completed annual HR appraisals
d) That complaints are resolved within seven working days
5.How may practices using compliant HR systems such as iComply find employment reforms easier to manage?
a) Policy updates may already be incorporated automatically as legislation changes
b) Employment contracts no longer need to be reviewed internally
c) Staff grievances can be managed without documentation
d) Payroll changes are automatically approved by regulators
conversations in place from the outset. There is also still time to prepare, and many of the most effective steps are relatively straightforward once broken down into manageable stages, particularly when practices review policies systematically (see boxed text) rather than trying to respond reactively once issues arise.
For practices using compliant HR systems such as iComply, some policy updates may already be incorporated automatically as legislation changes. Practices managing policies internally should ensure employment documents and procedures are reviewed regularly as further reforms are introduced over the coming months.
Ultimately, while the pace of employment reform may feel challenging at times, many of these changes become far more manageable when approached early and systematically. For dental practices, the focus should be on creating clear, consistent processes that support both the long-term stability of the practice and the people working within it. n
About the author Beth Honey is the HR Services Team Leader within the iTeam department, bringing over seven years of experience in the HR field. She is passionate about supporting effective people management and is driven by a commitment to enhancing workplace culture and improving the overall employee experience. Outside of work, Beth enjoys exploring the South West Coast Path, spending quality time with friends and family, and walking her energetic Labrador.
The caries comeback – why glass ionomers matter more than ever
Aim:
To enhance the knowledge and clinical decision‑making of oral healthcare teams on dental caries and the evolving NHS dental landscape, along with the role of glass ionomer and glass‑hybrid restorative materials in delivering effective, prevention‑focused and minimally invasive patient care.
Learning objectives:
• To describe the current trends in adult dental caries prevalence
• To explore recent NHS dental contract reforms and how they influence caries management
• To evaluate the clinical indications and advantages of glass ionomer and glass‑hybrid restorative materials
GDC anticipated learning outcomes: B,C
Dental caries remains a major public health issue in the UK.1 This means oral healthcare teams should consider sustainable improvements to enhance patient care.
The good news is that an increasing number of adults are retaining more natural teeth into later life.2 However, the latest adult oral health survey (AOHS,2023), published in 2025 showed:
• 41% of adults had obvious caries affecting the pulp and/or the dentine layer. This represents a 13% increase in caries prevalence Vs. the 2009 survey, almost reversing the previous decrease, bringing the 2023 estimate closer to the one of 1998 rather than 2009. This increase was also more pronounced in middle-aged and older adults with the largest proportion being primary disease on teeth not previously restored2
• 64% of adults had clinical caries in one or more teeth on the crown or roots when using enamel caries as a sensitive measure2
This increase in caries levels coincides with a shift in the dental landscape with an increasing acceptance of the benefits of the minimum intervention oral care (MIOC) framework providing a personfocused, prevention-based, susceptibility/ needs-related, team-delivered approach to help ensure effective access to primary oral and dental care.3
Restorative material choice is also shifting, not only to align with the MIOC framework, but also as a direct result of guidance around the use of dental amalgam. For many, dental amalgam has been the material of choice for high need patients due to its practical benefits in clinical dentistry. However, its use has been challenged due to the environmental and health impacts attributed to the 50% elemental mercury it contains. The demise of dental amalgam was hastened by the United Nations Minamata Convention in 2013 which led to a phase out for use in children 15 years and under, and this phase out was subsequently extended to cover pregnant/nursing women in July 2018. This, along with an imposed ban on the export by the European Union in January 2025 and a ban on
the manufacturing and import of dental amalgam in the EU from July 2026, increasingly challenges the ongoing use and availability of dental amalgam in the UK. These changes leave oral healthcare teams from all practice settings looking for alternative restorative materials.4
Additionally, delivery of NHS dentistry is also changing. Dental contract reforms introduced in England from 2022 to 202657 provide oral dental contract changes healthcare teams new ways of managing higher need caries patients. This includes best clinical practice supporting MIOC’s efficiency in managing oral diseases and enabling oral healthcare teams to deliver long-term, high-quality and patient-centered oral healthcare. These reforms mark a significant step in improving both access to NHS dentistry and the care people receive. They also respond to concerns raised by dental professionals about aspects of
previous contractual arrangements they felt limited their ability to provide optimal care. These reforms, as they apply to the treatment of dental caries, include:
• Band 2 treatments from December 2022 were subdivided into additional bands two of which include the placement of permanent fillings5,6
• Band 2a awards 3 UDAs: Includes up to 2 teeth requiring permanent fillings
• Band 2b awards 5 UDAs: For a combined total of three or more teeth requiring permanent fillings or extractions
• As part of 2022/2023 NHS dental reform, dental therapists and dental hygienists can now also open and close NHS courses of treatment to provide direct access to NHS care within their GDC scope of practice5-6, if they are competent and indemnified to do so. This allows dental therapists to carry
out direct restorations on primary and secondary teeth as part of an NHS course of treatment. Guidance on
‘Building dental teams: Supporting the use of skill mix in NHS general dental practice’7, suggests that maximising the potential of the wider dental team has the potential to:
• reduce patient wait times by increasing flexibility in care provision
• contribute to efficient contract performance
• enhance working conditions through workload distribution
• improve recruitment and retention in dental teams
• boost workforce wellbeing through team working
• support professional development This guidance document opens with a quote from a dentist who uses skill mix in practice:
Brought to you by
“It’s tough being a dentist… you’re on your own; the more we can do, working with therapists… it’s life changing. It makes things so much easier. I think the more we can get people working in this way, the better we’ll all be”. Dentist, practice owner and NHS contract holder.
• April 2026 saw the introduction of a new Urgent Care safety net, helping people get rapid access to NHS care when they need it most. This reform requires practices to allocate a minimum of 8.2% of their contract value to urgent and unscheduled care. The primary benefits include significantly higher, fairer remuneration for complex treatments, dedicated financial support to maintain open capacity, and expanded access to care for the local community8
• During this 2026/2027 NHS year there will also be the introduction of new clinical pathways to improve care for patients with unmanaged progressive disease (complex care needs).8 These new pathways will be paid at a set fee per pathway. For patients with dental caries, the criteria includes:
• Care Pathway 1: Patients with 5 or more teeth with caries (into dentine with no periodontal disease) paid at set fee of £272. Anticipated treatment period 6 months
• Care Pathway 2. Patients with 5 or more teeth with caries into dentine with currently unstable periodontal disease paid at set fee of £680. Anticipated treatment period 12 months
These new care pathways, underpinned by the minimum intervention oral care (MIOC) framework, will provide risk assessment and increased support for preventive care and oral health stabilisation, including the application of clinically appropriate restorative materials by dentists and dental therapists. Considering the increased caries levels, changing landscape/workflows and the need for amalgam replacements, oral healthcare teams will need to explore suitable restorative materials.
Although resin composite restorations are increasingly popular, their use in cases where there are high levels of unmanaged disease may not be appropriate,
particularly where oral health stabilisation is required in conjunction with supportive preventive advice and care. This is where glass ionomers become a more viable option for restorative dental treatment. GC, a leader in restorative materials, transformed glass ionomer from an emerging material into a mainstream restorative material. For generations of clinicians, the GC Fuji brand has become synonymous with dependable glass ionomer dentistry. The GC Fuji range therefore represents decades of innovation in glass ionomer technology, delivering fluoride-releasing, chemically adhesive, restorative solutions that support minimally invasive and preventionfocused dentistry. In many respects, the dental profession, through its adoption of MIOC, has now moved closer to the role Fuji was designed to meet and has fulfilled for decades.
The GC Fuji range remains an indispensable partner with its wide range of indications supporting today’s oral healthcare teams in delivering enhanced patient care within the MIOC framework:
• Fuji IX GP – A high viscosity glass ionomer and the proven gold standard for posterior cavities. Resin-free, condensable, easy to apply and contour. Available as Fuji IX GP FAST for shorter procedure time and Fuji IX GP EXTRA for higher translucency
• Fuji II LC – A resin-modified glass ionomer providing the easy light cure option with controlled placement with a light induced setting. Fuji II LC can also be reduced to a base for use under a posterior composite restoration
• Fuji Triage – A low-viscosity glass ionomer providing fluid protection. The first-line solution for MIH, provides instant relief and acts as a tooth plaster and is available in pink or white Fuji remains one of GC’s core restorative brands, representing decades of leadership in glass ionomer technologies, in addition to the clinically proven and successful EQUIA family.
EQUIA Forte™ HT has taken glassionomer technology with advanced glass hybrid technology further still, offering a long-term, cost-effective restorative alternative. It is a strong, biocompatible bulk fill restorative system (Fil and Coat) with an excellent long-term success rate, even in posterior load-bearing cavities. Benefits include:
CPD Questions
1. The prevalence of adults with obvious caries in the AOHS in 2023 was more pronounced in:
a. Edentate adults
b. All adults
c. Younger adults
d. Middle-aged and older adults
2. In England, Band 2a awards 3 UDAs for how many teeth requiring a permanent filling?
a. 5 teeth
b. 3 teeth
c. 2 teeth
d. 4 teeth
3. The GC Glass Ionomer Fuji IX GP is the gold standard for posterior cavities because it is:
a. Resin free
b. Condensable
c. Easy to apply and contour
d. All off the above
4. Advanced glass hybrid technology found in GC’s EQUIA Forte™ HT provides:
a. No requirement for a bonding agent
b. A requirement for a bonding agent
c. No resistance to micro-leakage
d. No chemical bond directly to dentine, enamel and cementum
• Moisture tolerance
Glass hybrids are hydrophilic to withstand the humidity of the oral environment or the dentine-pulp fluid flow in tubules. Glass hybrids are ideal for use when isolation is difficult to achieve as their moisture tolerance enables quicker and more efficient placement of restorations while often making the use of rubber dam optional
• No bonding agents
While resin composite requires a specific bonding process, glass hybrids have no need for a bonding agent as they chemically bond directly to dentine, enamel and cementum to create a strong, stable and chemically fused seal for longterm resistance to micro-leakage
• Surface coating
Glass-ionomer cements undergo a rapid initial hardening reaction but continue to undergo a setting reaction for some time after this hardening is complete. Applying a protective resin coating, such as EQUIA Forte Coat, to the material during the initial setting phase can improve surface hardness and wear resistance during the initial setting period, when it is most susceptible to water uptake or dehydration
The overall clinical survival rates for GC Equia Forte HT (and its direct predecessor Equia Forte) range between 93% and 100% at 2 to 3 years, and maintain an impressive 81% to 94.5% survival rate up to 5 to 6 years for Class I and Class II restorations.
In a recent article published in Dental Update ‘After dental amalgam: the battle
of the bulk fills’10, Professor Trevor Burke states “The clinical studies cited... indicate that the recently introduced glass hybrid material, Equia Forte (HT), shows promising results in Class I restorations and in small/ medium Class II restorations ... with better cost-effectiveness than equivalent resin composite restorations because it is quick and easy to use.”
Consider using Equia Forte™ HT when clinically relevant including as an amalgam alternative, a restorative for teeth affected by MIH and as a treatment for root caries. GC’s glass ionomer and glass hybrid products are the intelligent solution for meeting the challenge of increased caries levels, changing landscape/ workflows and offer a real alternative to dental amalgam. n
References available upon request
About the author
Debby Ward, Sales Manager Operatory, GC UK Ltd.
Equia Forte™ HT Fil and Coat
Missed us at dentistry show Birmingham? A date for the implant diary
No problem! Our product specialists can bring the world of digital dentistry right to your door with the Plandemo mobile showroom. Packed with the latest in cutting-edge technology, you can try out the innovative Compact Classic dental unit kitted out in sumptuous Metallic Gold Ultra Relax upholstery, and see just how easy it is to use the Viso G1 CBCT imaging unit first hand, along with the high-quality clinical images it produces.
Experience the rich selection of tools and features available in our AI-powered Romexis dental software, and find out how same-day dentistry can be incorporated into your surgery with the PlanMill 35 milling unit.
So what are you waiting for? It’s the perfect opportunity to explore our full product range at a time and location that suits you - book your appointment today at www.planmeca.com/plandemo or call us on 02476 994160!
Enhance practice aesthetics
The Edarredo range of dental cabinets from Clark Dental is available in a variety of colours, ensuring a seamless integration into your dental practice and enhancing the aesthetic of your brand.
The range includes the mobile Tender cabinet, a dynamic workstation that can be moved around the treatment room with ease. The compact size of the Tender makes it a flexible addition to the daily workflow, able to fit into small spaces to best optimise the area.
Best used for intraoral scanners, laptops and monitors, with room for a tower PC in the cupboard below, the Tender is an easy way to scan and analyse clinical images without leaving the room. It can also be quickly wheeled around the treatment
The HySolate SyntX Dam from COLTENE offers next-level isolation for all your endodontic and restorative requirements. The polyisoprene formulation permits the predictable and consistent stretching of the dam over clamps and contact points, without the risk of tearing or thinning. The material is also non-latex – supporting use with an extended patient base – for those with sensitivities.
The distinctive blue colour optimises visual focus, providing great contrast which is particularly useful for clinical photography. Furthermore, the HySolate SyntX Dam comes with a pre-printed template on one side, facilitating faster and more accurate punching, whilst minimising decision0making throughout treatment.
Everyone in the field has heard it – “the future of dentistry is digital” – which is exactly why it’s integral to ensure your practice doesn’t fall behind.
Dental Directory encourages practices through this transition, delivering more than merely a supply of new technology, but everything supporting it. With a huge digital collection – offering everything from state-of-the-art 3D CBCT imaging and efficient X-ray sensors to highly precise intraoral scanners and effortless milling machines – Dental Directory has all the digital innovations your practice needs to continue excellent patient care. Better yet, Dental Directory guarantees the continued health of your investments, with advice, warranty, and servicing options all
centre to discuss a diagnosis with the patient if required.
Simple yet reliable, the Tender reflects the practicality of the Edarredo range – sleek dental cabinets that match your treatment room and deliver a tidier, more streamlined workflow.
Supplied and installed by Clark Dental, get in touch today to find out more about the Edarredo range.
For more information call Clark Dental on 01268 733 146, e: info@clarkdental.co.uk or visit www.clarkdental.co.uk.
With exceptional elasticity, high tear resistance and retention, and remarkable ease-of-use, the HySolate SyntX Dam is the only choice for isolation. Find out more about the most advanced latex-free dental dam for faster isolation and confident retraction. Contact the team today!
For more information, visit https:// products.coltene.com/EN/CH/products/ treatment-auxiliaries/dental-dam/standardnon-latex-dental-dam/hysolate-syntx-dam email info.uk@coltene.com or call 0800 254 5115.
The dental implantology event you don’t want to miss is back for 2027!
The ADI Team Congress 2027 is titled “The Future in Focus. Four Decades of Implant Excellence” and it will celebrate achievements in the field so far while exploring what might come next.
It will offer a comprehensive programme packed with world-class clinical education, networking, connection, innovation, and more. The entire dental implant team is invited, from dentists to dental hygienists/ therapists, dental nurses, practice managers, and treatment coordinators, ensuring a well-rounded learning experience for all.
There will also be an opportunity to
engage with industry, discovering the latest products and technologies designed to elevate clinical outcomes and streamline the professional workflow.
Get the dates in your diary to make sure you don’t miss out!
ADI Team Congress 2027 15-17 April 2027, ACC Liverpool
For more information about the ADI, visit www.adi.org.uk
Join today!
Boost patient engagement
When you implement Sensei Cloud, the cloud-based practice management solution from Carestream Dental, you gain access to simpler, more convenient, and more seamless workflows.
The Patient Bridge feature facilitates highly efficient patient communication and engagement every step of the way. Not only does this enhance the patient experience, it also helps to build rapport with each individual, encouraging their ongoing loyalty to the practice for long-term sustainability.
Ensuring smooth integration with existing workflows, the software can be used by practices offering NHS, private, or mixed services with ease. It’s even beneficial for multi-site businesses, and can be designed to scale as you grow.
When design meets dentistry, exceptional results follow. The Black Is White Hydrosonic Pro from Curaprox brings together striking aesthetics and advanced biofilm control in one sophisticated device. Matt black, beautiful and Swiss engineered for performance.
Delivering up to 84,000 rotations per minute across three power levels, the sonic toothbrush harnesses hydrodynamic forces to clean deep into interdental spaces while remaining ultra-soft on teeth and gingivae. Its carbon-coated Curen® filaments absorb discoloured particles gently, helping to lift stains without damaging enamel.
Thoughtful Curacurve® ergonomics and a tear-drop filament arrangement ensure
Find out more from Carestream Dental today. To learn more about how Sensei Cloud can help your practice thrive, visit gosensei.co.uk. For the latest updates, follow us on Facebook and Instagram @carestreamdental.uk.
available to complement your digital dentistry journey. Don’t fall behind in the new generation of dentistry, continue to lead with innovation, maintaining patient satisfaction. Contact the team to find out more today!
Dental Elite provides expert support at every stage of your dental practice sale.
Recently, the team assisted Michael Fahami when he decided to sell his practice, finding a suitable buyer, and taking care of the paperwork. Michael commented:
access to hardto-reach areas, making it ideal for patients with braces, implants and restorations.
A powerful battery delivers up to two weeks of brushing, supported by intuitive one-button operation and a compact travel charger.
Developed by Prof. Ulrich P. Saxer, Black Is White Hydrosonic Pro pairs whitening innovation with clinical credibility – beautifully. Visit www.curaprox.co.uk and www.curaden.co.uk.
Dental Directory – more reasons to smile. For more information on the products and maintenance services available from Dental Directory, please visit ddgroup.com or call 0800 585 586.
“I had previously worked with Dental Elite when purchasing a practice, so it made sense to use them again when selling my business. The experience was excellent - support was always available, they introduced the right buyer, and supported with the CQC application.
“The team are knowledgeable, responsive, and genuinely understand the process of buying and selling dental practices. Special thanks to Anil, Lottie and Sophie, who were all brilliant throughout.”
No matter what your reason may be for selling your practice, contact the helpful team at Dental Elite to ensure the best possible experience.
For more information on Dental Elite visit www.dentalelite.co.uk, email info@ dentalelite.co.uk or call 01788 545 900.
TANDEX FLEXI and TANDEX PREVENT Gel
TANDEX FLEXI gives an e cient and gentle treatment for both teeth and gums. It includes 11 di erent sizes so there are brushes to suit small interdental spaces or more complex bridge and implant spaces. Your dentist or dental hygienist will help you find a size that is right for you.
TANDEX PREVENT Gel is a specially developed gel with 900 ppm fluoride and 0.12% chlorhexidine. Strengthens enamel and protects against plaque and cavities. It provides e ective cleaning between the teeth. An antibacterial gel designed especially for use with interdental/gum brushes.
TANDEX FLEXI is a specially designed interdental brush with an ergonomic grip. The flexible grip makes it easy to reach for all patients even interdental spaces in the back of the mouth. For more information visit https://tandex.dk/ To request samples and place orders, please visit DHB Oral Healthcare at https://dhb. co.uk/ SCAN.ENTER.WIN.
A Prime way to scan
Take digital impressions to a new level of quality with the Dentsply Sirona Primescan®II, supplied and installed by Clark Dental.
Powered by a DS core, the wireless Primescan® II improves access to the hard-to-reach areas of the oral cavity with its slim head design, enabling clinicians to scan the posterior teeth for enhanced diagnostics. This flexibility extends to the angle possibilities: each tooth can be scanned anywhere between 5 and 85 degrees.
Capturing highly accurate scans using fluorescence and near-infrared technologies, it is an ergonomic practice essential that scans straight to the cloud. The Primescan®can also scan materials
such as glass and metal, with intelligent processing in the sensor ensuring a fast prosthetic design workflow too.
With considerable experience supporting dental practices, Clark Dental supplies cutting-edge imaging solutions such as the Primescan® II, as well as innovative extraoral systems, treatment centres and 3D printing solutions – discover the full range today.
For more information call Clark Dental on 01268 733 146, e: info@clarkdental.co.uk or visit www.clarkdental.co.uk
clarity with the cs 8200 3d Access
Metal artefacts can compromise the care your patients receive. The CS 8200 3D Access CBCT scanner from Carestream Dental puts the power in your hands to reduce interference, and inform high-quality treatments.
With CS MAR (metal artefact reduction) technology, clinicians can devise confident diagnoses and reduce the risk of misinterpretation. There is even the ability to automatically have live comparisons between the standard radiographic image, and the final result with CS MAR in place.
The CS 8200 3D Access presents panoramic technology, CBCT imaging, 3D model scanning and cephalometric imaging in one system, but makes care simple with a user-friendly interface. Clinicians with limited experience in radiography can choose the system to support patients with
greater confidence, whilst still attaining high-quality results.
Patient safety is prioritised through a low-dose imaging mode, which helps to develop leading 3D images at the same or lower dose as a standard panoramic exam.
Find out more about how the CS 8200 3D Access can make a difference in your practice by contacting the Carestream Dental team today. More information visit www.carestreamdental.co.uk.
For the latest news and updates, follow us on Facebook and Instagram @carestreamdental.uk
“I only refer to places I would go myself” Waste responsibilities made simple with Initial Medical
At EndoCare, we are so grateful to all our referring clinicians for their continued support.
Many thanks to the referring dentist who very kindly provided the following review:
“I say to patients that as a rule I only refer to places I would go myself.
“EndoCare is the go-to place for my endodontic referrals. Not only are they outstanding and ethical clinicians that I trust 100%, they are supported by an excellent team that ensures a smooth patient journey. They always act in the best interests of the patient with honest advice. Referrals are always followed up, usually the same day, and once the patient has been seen I receive a letter/
radiograph with the outcome advising me and the patient of the next steps.
“I really appreciate that I can pick up the phone if I have a query or a patient needs an urgent appointment and 99% of the time the phone is answered and dealt with usually by Fiona who is quite simply, amazing.”
For further information, please call 020 7224 0999 or visit the NEW website www.endocare.co.uk
IAs Academy offers recognised diplomas in orthodontics
IAS Academy is known for its comprehensive and ethical training in orthodontics and restorative dentistry. The globally respected training team is offering various programmes in 2026, including two diplomas that result in recognised qualifications.
Clear Aligners Diploma – this is an authoritative year-long course that will take your aligner skills to expert-level, exploring treatment concepts, digital workflows, treatment planning, and in-house aligner production.
Next start date: 02 July 2026
Advanced Diploma – the two-year programme trains clinicians to manage
TANDEX is thrilled to invite you to participate in the latest TANDEX Quiz –keeps you smiling!
The quiz offers dental professionals – from hygienists and dental nurses to clinicians and more – the opportunity to win a FREE TANDEX FLEXI Educator Kit! The kit itself includes a plethora of FLEXI Interdental brush sizes; colour coordinated for ease-of-use. It is a fantastic education bridge between patients and practitioners, supporting the correct guidance and building on healthy, repeatable habits. Entering is simple, with participants being asked to complete a short form and clinical questionnaire. A monthly draw will take place on the last Friday of each month – one entry each!
complex malocclusions with a range of appliances and is recognised by the College of General Dentistry as a preferred training provider.
Next start date: 04 June 2026
Don’t miss this opportunity to gain the qualification and experience you need to excel in your career. Find out more today.
For more information or to book the course, visit https://courses.iasortho.com/ courses or call 01932 336470 (Press 1)
Keeping on top of clinical waste workflows is made simple with guidance and solutions from Initial Medical, including the eco-friendly Griff Pac waste container range. It offers a 25% reduction in CO2 emissions during production, and a 64% reduction in CO2 emissions from raw materials. Importantly, Griff Pac solutions are colourcoded in line with current regulations, ensuring each waste item can be appropriately segregated. These containers are made from corrugated polypropylene with an integral HDPE liner, which ensures they are suitable for storing both dry and wet waste. The Initial Medical team have vital expertise
in creating clearly defined waste workflows, and they are always on hand for queries.
Whether you need advice on implementing regulations safely or are interested in learning about our waste collection service, contact us today to step up your clinical waste workflows.
To find out more, get in touch at 0808 304 7411 or visit the website today www.initial.co.uk/medical.
targeted pain relief in just 2 minutes
Orajel® makes pain relief simple for patients awaiting a dental appointment for a broken tooth or any tooth that needs a filling.
The topical gel is simply:
• Squeezed onto a clean finger or swab as a pea-sized amount
• Applied to the area of pain
• Job done
Orajel® gets to work in just 2 minutes, providing reliable relief from discomfort. This is significantly faster than alternative pain management options at home, which can typically take much longer to take effect.
Orajel® Dental Gel contains 10% benzocaine to afford powerful local anaesthetic exactly where it’s needed. Find
out more today.
For essential information, and to see the full range of Orajel products, please visit https://www.orajelhcp.co.uk/
Find out more about this exciting opportunity –contact the team today!
Enter the quiz by scanning the code or following this link https:// form1.tandex.de/ For more information on Tandex’s range of products, visit https://tandex.dk/
Our products are also available from DHB Oral Healthcare https://dhb.co.uk/
Garrison Dental Solutions launches the Advanced Band & Wedge Instrument, expanding its precision instrument line with a new option engineered to elevate control, grip, and confidence in clinical procedures.
With the addition of the Advanced Band & Wedge Instrument, Garrison now offers three distinct forceps options, each designed to enhance grip, precision, and control—so clinicians can work with confidence across a range of restorative needs. Whether placing a wedge or maneuvering a sectional band into position, there is a Garrison instrument tailored to the task.
A Versatile New Option for Everyday Excellence
The Advanced Band & Wedge Instrument features:
• 45-degree angled tips for improved posterior access
• Specially engineered gripping teeth for secure band and wedge placement
• Approximately 16X the grip* of standard cotton pliers
This makes it the ideal solution for clinicians who need precise handling and ergonomic reach without the intensity of the Ultimate Band Instrument.
CS 8200 3D Advance Edition
Looking for more possibilities?
Every patient is different, so your CBCT imaging system has to adapt. The CS 8200 3D’s Advance Edition enhances your diagnosis with a powerful 4-in-1 system for all your needs. It boasts more and extended fields of view and Al-automated implant planning1 for faster workflow.
Scan to learn more
Extended fields of view up to 16 x 10 cm
AI-automated implant planning1 Three upgradeable FOV configurations
Compact, awardwinning design
Intuitive interface and software
75-micron resolution
Most events in peoples’ lives take planning. Some, like weddings, can take a year or two to organise. Others, like a holiday, may take a few days or weeks.
Retirement, however, is the one event that most of us think about over a period of 30 to 40 years. Whether we truly plan for it is another matter. We often talk vaguely about exotic holidays, playing more golf or taking up pottery. But beyond contributing to the NHS Pension Scheme and/or a private pension, many simply hope for the best.
From paycheque to pension
It can be easy to underestimate the ‘feel’ of retirement income compared to earned income from dental work. After decades of predictable monthly pay, retirement can feel uncertain, like relying on various pots of money that may one day run out.
For this reason, retirement income needs to be carefully constructed, considering available sources, taxefficiency and, most importantly, the level of income required to maintain your desired standard of living.
The longevity challenge
One complication is that retirement income must last for an unknown length of time. Based on current life expectancy, some people retiring in their 50s could spend as many years in retirement as they did working. This can be a daunting prospect, particularly if pension funds aren’t managed carefully.
Other risks to consider include market volatility, inflation eroding the real value of income and potential long-term care costs.
Guaranteed income
Many dentists will have at least part of their retirement provision in the NHS Pension Scheme. This is an excellent foundation, providing a guaranteed, inflation-linked income for life.
Another reliable source is the state pension. However, both come with limitations – primarily the age at which they can be accessed. The state pension is increasing from 66 to 67 between April 2026 and March 2028, with a further rise to 68 planned for the mid-2040s.
NHS pension ages vary depending on the section of the scheme you’re in, and early access typically results in an actuarial reduction in your pension.
Flexibility vs certainty
Because of these restrictions, those wishing to retire early must plan more carefully.
Private pensions offer greater flexibility. They can be used to secure guaranteed income for life, removing the risk of funds running out. However, this approach isn’t suitable for everyone. It may lead to excess income later in life, increasing inheritance tax liabilities. Additionally, in the event of early death, annuities generally do not return the remaining fund.
The role of drawdown
Alternatively, a drawdown strategy allows income to vary over time. This can be structured around when NHS and state pensions begin, reducing reliance on private pensions later and allowing more funds to remain invested for growth throughout retirement.
Other income sources
Retirement income often comes from multiple sources. ISAs, investment portfolios and rental properties can all contribute, depending on individual needs and tax circumstances.
Principal dentists may also have proceeds from the sale of their practice, which require careful investment planning to generate sustainable income.
The
last 10 years
The final decade before retirement is critical for refining your plans. This is the time to make sure debts, such as mortgages and practice loans, are repaid. You should also look to maximise pension contributions during what are likely your highestearning years.
Why strategy matters
A clear strategy is essential. Without one, it’s easy to fall into the habit of dipping into savings each month, potentially depleting funds sooner than expected.
Creating a predictable, sustainable income stream is key. Working with a financial expert can help ensure retirement is about enjoying the wealth you’ve built, rather than worrying about whether it will last.
To speak to a Specialist Financial Adviser from Wesleyan Financial Services, visit wesleyan.co.uk/dental or call 0808 149 9416. Charges may apply. You will not be charged until you have agreed to the services you require and the associated costs. Learn more at wesleyan.co.uk/charges.
Remember, the value of investments may go down as well as up and you might get back less than you invest.
Wesleyan Financial Services Ltd (Registered in England and Wales No. 1651212) is authorised and regulated by the Financial Conduct Authority. Registered Office: Colmore Circus, Birmingham B4 6AR. Telephone: 0345 351 2352. Calls may be recorded to help us provide, monitor and improve our services to you.
About the author
Having vast experience as a dental Specialist Financial Adviser (SFA) over the years, Simon Cosgrove is now a Dental Regional Manager at Wesleyan Financial Services, guiding a team of dental SFAs to support dentists, their families, and their practices with financial planning to secure their financial future.
Sorting out your retirement income
Growth routes
How can you successfully grow your business? There are many answers: increased prices for customers, reduced costs, more marketing, and investing in technology, to name a few. But it is crucial that any growth plan maintains your brand image and your own ethos is not compromised by the actions you take.
For dental practice owners, growth is always the goal to stay ahead of the competition and abreast of the constant changes in technology and patient tastes. But in a challenging landscape, finding the right path for your practice’s future can be a tricky endeavour.
First steps to success
If you are looking to grow your business, the crucial first step is to make an honest assessment of where you are now. This includes looking at:
• Income – how much revenue is being made on a monthly/annual basis?
• Patient feedback – regularly checking online reviews is essential to improving performance and patient satisfaction. Replying to these reviews also reflects how open you are to feedback and helps you understand which areas can be improved.
• Staff feedback – whilst some staff members may be more open with their feedback, others may be quieter. Checking in on the dental practice team and finding out what is and isn’t working for them can guide you towards the appropriate solution; sometimes anonymous feedback can lead to more honest responses about how to optimise the daily workflow.
Please the patients
The easy option for practice growth is to raise the prices of treatments, but this is not sustainable. Hiked prices rarely appeal to patients, especially during extended periods of economic uncertainty. Having established and consistent treatment costs, or offering payment plans, provides a level of financial security for patients, ensuring regular appointments and boosting the practice image as a place that puts its patients, rather than revenue, first. By doing so, revenue can still increase due to positive word of mouth.
Promote value
Rather than overcharging patients to generate more revenue, instead offer more valuable services. Along with reviews, numbers paint a picture of how well the practice is doing with the treatments it is providing. One way to determine which services are most financially beneficial is to analyse the competition and also the average daily yield of each dentist, done by checking the income over a month / year and dividing by the number of days worked. Like patients, each dentist is different, from the treatment types to the length of each appointment.
For instance, Dentist A may generate £1,000 a year and Dentist B may average £1,200. The superior performance of Dentist B may be because they deliver a higher number of cosmetic dental treatments, for example, whereas Dentist A focuses more on routine check-ups; this may encourage you to focus on providing more cosmetic dental treatments as it is clearly more lucrative. Alternative suggestions could be specialist pathways like periodontal care and orthodontic services. If following this route, adjusting the practice marketing
and hiring / training more dentists who can deliver these treatments would therefore be a reliable way of ensuring growth.
coach support
An effective way of growing your practice is through the support of a dental business coach; someone who can give a second opinion on your decisions and guide you towards a successful and sustainable growth plan. Acting as a mentor figure, business coaches can improve practice profitability without impacting your relationship to the patients, providing ongoing support and advice with every decision.
The Clyde Munro Linchpin Programme is an excellent training opportunity that allows you to achieve more for your practice, with guaranteed revenue increases that don’t come at the cost of compromising your values. Led by Dr Barry Oulton, the course is no risk and all reward, with Clyde Munro there to refund the full fee of the programme once you increase your hourly revenue. The
fantastic 12-week course will reduce stress and boost your professional and personal life for a truly unmissable opportunity.
Highway to success
There are many roads to growing your practice, making it essential to take the one that best aligns with the interests of your business. Whether offering new treatment services, focusing on patient experience or using a financial mentor, be confident in your business growth plan. To sign up for the Clyde Munro Linchpin Programme visit barryoulton.com/my-dentist-academy n
about the author
Jo Hood. Head of clinical Recruitment & Development at clydeMunro Dental Group.
Why authentic content matters more than ever in the age of AI
The rapid growth of artificial intelligence has completely changed how content is created. From social media captions to blog posts, generative AI tools can now deliver content in just seconds. For busy dental practices, this can feel like a huge opportunity to save time and scale output. However, when it comes to social media, there’s an important difference to remember – although AI can support content creation, it can’t replace it. As generative AI becomes more widely used across various platforms, followers are becoming more aware and more selective about what they trust online. So now is the perfect time for dental practices to double down on genuine, human-led content. AI is everywhere, but not everyone trusts the process. Research shows that consumer confidence in AI-generated content remains fairly low, with only a small percentage of people feeling fully comfortable with content created entirely by AI. More than half of people worldwide are still hesitant to fully trust AI, highlighting a
clear gap between efficiency and credibility.
This trust gap creates a massive opportunity for dental practices. While it may be tempting to rely on AI for social media posts, the practices that stand out will be the ones that prioritise original and authentic communication.
This is because people don’t just want information – they want connection. Content that feels real and relatable will always perform better than content that feels generic or overly polished. Usergenerated content, such as patient testimonials or behind-the-scenes stories, is a great example. Audiences are far more likely to trust and engage with content that reflects real-life experiences.
So, a simple video of a patient sharing their smile transformation or a team member explaining a procedure or treatment in their own words can carry far more weight than a perfectly structured AI-generated photo. There’s also growing awareness around the limitations of generative AI in social media. Many people are becoming concerned about misinformation, a lack of transparency, and
impersonal content. Your audience isn’t just consuming content anymore; they’re evaluating it. And when something feels inauthentic, it will often be dismissed.
So, what does this mean for your practice?
Dental practices don’t need to avoid AI altogether. It can be incredibly useful for brainstorming ideas, structuring captions, or improving efficiency. But when it comes to social media, it shouldn’t be doing all the talking.
The most effective approach is to use it as a support tool, not a substitute. The content itself still needs a human voice – whether that’s from your team or your patients.
Think about highlighting real patient stories, team introductions, day-in-the-life clips, and honest conversations about treatments. These types of posts not only build trust and credibility but also create an emotional connection – something AI can’t replicate.
This corresponds with a wider shift happening in digital behaviour. As social feeds become saturated with AI-generated content, audiences are now beginning to look for something different. Authenticity,
personality, and transparency are becoming more important than ever.
In other words, the more generative AI is used to fill social media, the more impactful genuine content actually becomes.
Dental practices should lean into this! And those who show their individual personality, highlight their team, and showcase real patient stories will inevitably build stronger relationships with their patients.
At the end of the day, social media isn’t just about posting more – it’s about connecting better.
And that still comes down to people. n
References
• Reuters Institute for the Study of Journalism (2025). Generative AI and News Report 2025: How people think about AI’s role in journalism and society.
• KPMG (2025). Trust in AI remains a critical challenge.
about the author abby Leach, content creation Manager at connect My Marketing.
Sell smart, sell strong
For many dental practice owners, the decision to sell does not begin with a valuation. It begins with a question: have I built something that someone else will truly understand, value and want to carry forward?
A practice is rarely just a business on paper. It can represent years of clinical care, team development, patient relationships, financial risk and personal sacrifice. When the time comes to consider a sale, owners are not only asking, “What is my practice worth?” They are also asking, “Will buyers recognise the value I have built?” and “How do I protect the outcome I deserve?”
At Lily Head Dental Practice Sales, we advise dental practice owners across the UK on valuations, sales and exit strategies. In my experience, one of the most common mistakes owners make is waiting until they are ready to sell before thinking seriously about sale readiness.
A successful sale is often built long before the practice reaches the market.
Preparation gives sellers clarity. It helps them understand value, reduce buyer concerns and approach the market from a position of confidence. While market conditions may shift, buyer logic remains remarkably consistent.
Whether the buyer is an independent dentist, an associate, a group, a corporate or an investor, they are usually asking three questions: is this practice worth the money, is it worth the risk, and is it worth the effort?
The strongest outcomes rarely come from simply finding a buyer. They come from preparing properly, pricing realistically and giving credible buyers the confidence to move forward.
a valuation is not just a number When owners think about valuation, they often focus on the headline figure. What multiple might I achieve? How much will someone pay? How long will the process take?
These are very important questions, but a valuation is not just a number. It is a judgement on risk, return and transferability.
Most dental practice valuations start with maintainable EBITDA. The multiple applied to that EBITDA is where confidence and demand come in. If buyers believe the profit is sustainable, transferable and capable of growth, confidence increases. If they believe the profit is fragile, dependent on one person or difficult to evidence, confidence falls.
In simple terms, valuation is driven by EBITDA, confidence and demand. A buyer does not just buy historic figures. They buy confidence in what happens next.
What buyers are really looking for
Buyers do not pay a premium for turnover alone. They pay for profit they believe will still be there after completion.
A full diary, strong revenue and a good reputation all matter, but buyers will look closely at maintainable profit. They will want to understand whether EBITDA is realistic, whether adjustments are reasonable and whether the practice has absorbed rising staff, lab, material, compliance and associate costs.
Buyers will also consider how dependent the practice is on one individual. That person might be the principal, a high-performing associate or a hygienist who holds the plan base together.
From the seller’s perspective, this may feel like a strength. From the buyer’s perspective, the question is simple: what happens if they leave?
Patient demand is another key area. Patient numbers matter, but a large database is not the same as a loyal, active patient base. Buyers want to understand whether patients attend regularly, whether recall is working, whether the plan base is stable and whether new patients are still coming in.
The key point is simple: sustainable profit needs sustainable patients.
evidence beats optimism
Most sellers can identify growth potential in their practice. However, buyers will only pay attention to a growth story if it is realistic, practical and deliverable.
General statements about “huge potential” are rarely enough. They can sometimes weaken the conversation, because the natural buyer question is: if the potential is so clear, why has it not already been realised?
Stronger opportunities are supported by evidence, such as available chair time, spare surgery space, unused sessions, hygiene capacity, treatment demand, plan opportunity or expansion potential.
Team stability also matters. Dental practices are people businesses, and a stable, engaged and well-led team reduces buyer risk. Buyers want confidence that associates, hygienists, nurses and support staff are likely to stay, and that the practice can function without the seller solving every problem. This is where culture becomes commercial. A strong team does not just make the practice a better place to work. It helps protect value in a sale.
a clear exit strategy creates confidence
Buyers are not just buying past performance. They are buying their future.
They will ask what happens on day one after completion. Will the seller stay? For how long? Will patients accept the transition? Will the team remain? Can the business grow? Is the return worth the money, stress and responsibility?
The earlier an owner understands their preferred exit, the easier it becomes to build the right strategy. Do they want to sell and leave completely? Stay clinically but step away from ownership? Reduce days gradually? Prioritise price, certainty, continuity, speed or a particular buyer type?
Different motivations require different strategies. A seller looking for maximum value may need a different approach from one prioritising speed, buyer type or continuity for the team.
start before you need to sell
Selling well is not just about finding a buyer. It is about building a practice that buyers understand, value and trust.
Whether an owner is thinking about selling soon or several years from now, preparation can protect value, reduce risk and create options. That may include understanding true maintainable
EBITDA, reviewing reliance on key individuals, assessing patient activity and retention, identifying realistic growth headroom, considering team stability and reviewing the property position.
An early valuation and exit review can help an owner understand what their practice may be worth today, where value is protected, where risk exists and what could be improved before going to market.
For practice owners considering a sale now, in the next few years, or simply looking to understand their options, a confidential valuation or conversation with an experienced dental practice broker at Lily Head can provide clarity on value, timing, risk and the practical steps that may help maximise sale value.
Sell smart. Sell strong. And make sure your exit reflects the value of the business you have spent years building. n
about the author
Tom Orchard, Head of Practice sales, Lily Head Dental Practice sales. tom.orchard@lilyhead.co.uk
Compatible with all obturation techniques (single-cone, warm, cold).
The high radiopacity allows for immediate quality control and ensures adequate documentation.
Creates an antimicrobial environment during early setting.
Fast, clean dispensing with preloaded 2g syringe.
Supports periapical healing with alkaline biocompatibility.
Streamlined work ow with direct intracanal placement.
Easy access in narrow or curved canals thanks to bendable tip.
Minimised waste through controlled material usage.
Why CanalPro Calciseal?
Selling to an associate... a thing of the past?
When I started in the service of selling dental practices more than 20 years ago, there was a reasonable proportion of practices that were passed down from principal to associates, with no real consideration from the principal to go to the open market. However, we are now seeing a smaller proportion of practices sell this way.
The market has changed substantially since this time with multiple buyers and offers being received for each practice being sold, as well as higher prices being paid. So, are people who sell to their associates short-changing themselves, or is there a way to have the best of both worlds?
One of the major benefits of going to market is to have an agent by your side for the whole of the transaction; providing a valuation and guidance on how to enhance the value of your dental practice, confirming the things that need to be in place prior to marketing, undertaking the negotiations, sourcing proof of finance from the buyer or assisting the buyer to arrange finance, preparing the heads of terms for the solicitors, and resolving any issues or queries throughout the process. The service that an agent provides should not be underestimated and is likely to ensure that the deal does not fall through and is undertaken in a timelier manner. However, you can have the same level of service if you want to sell to your associate with the aid of an agent.
Valuation
For any practice sale, it is important to have a valuation of your practice by someone who fully
understands the market. This is not a simple calculation using your turnover or profit from the accounts. The valuer will need to ‘get under the hood’ to understand the income sources, how the associates are paid, whether there are any hygiene recharges in place, the current staff structure, and the personal costs that are running through the business that can be added back. Having an accurate valuation will save issues down the line.
Sales brochure
Whilst the associate may work in the practice five days per week, they are unlikely to understand the intricacies of the financials and how the practice works. It is important that they fully understand so that they have the confidence to move forward with the purchase. Following a valuation, any costs removed can be shown transparently, again providing the associate with the confidence that they can follow the changes made and can see that these are accurate.
Advice
I believe one of the key benefits is having someone that they can talk through financials with and help them understand the market. When we are dealing with associate sales, it is always nice to see when you can build a good conversation about the associate’s needs, and give them the reassurance of the market, the sale process, and external advisors that they can contact where needed. Having that one person that they can speak to is often the reason for a successful sale. If an issue arises then it can be spoken about and resolved.
Offers and negotiation
If the associate appreciates that the valuation is accurate and understands the figures, they are more than likely to put in a stronger offer. In most circumstances, when we market the practice to an associate, we would confirm that they have first refusal, but this does not mean that they are the only option. Once they understand this, offers are generally where we would expect them to be. As an agent, understanding deal structures and what can or cannot work is important to make sure that the sale will get to completion. It is also important to ensure that they have finance in place or, if not, the agent can help put this in place.
Heads of terms and legals
Providing clear instructions to the solicitor and working with them through the process to make sure that everything is completed on time. Any issues or changes to the practice are resolved as they happen.
Selling your dental practice to an associate may be the preferred route, but it does not mean that you must accept any less with the sale. Most clients tell us that they like the fact that they can stay out of the negotiations and maintain their day-to-day relationship with the associate, whilst we, as an agent, handle the discussions.
About the author
Martyn Bradshaw is a Director of PFM Dental and heads up the dental practice sales agency.
Dentists’ Provident, always by your side.
None of us know what the future holds.
Having to take time off work because of an illness or injury can have a serious effect on your finances. This is where we come in – our income protection plans can help take away the worry by replacing the income you lose, until life gets back to normal.
For over a hundred years, our members have trusted us to give them peace of mind when they need it most. Isn’t it time you did the same?
To get a quote for an income protection plan please visit www.dentistsprovident.co.uk
To discuss a new plan just for you or review your current plan please contact our member services consultants on 020 7400 5710 or memberservices@dentistsprovident.co.uk
Understanding the current market for NHS practices
For groups and individuals alike, understanding of the current in the UK dental market, across private, mixed, and NHS practices remains essential when making informed decisions. With interest rates now slightly lower than they were a couple of years ago, market confidence has begun to improve.
Taking into account the experiences of practice owners over the past year, alongside projections for the year ahead, we explore what these changes may mean for buyers and sellers across the sector.
The landscape over the last year
In 2025, we saw some hesitation by sellers of NHS practices considering bringing their practices to market. This was driven by several factors, including negative press coverage, wider economic uncertainty and anticipated changes of capital gains tax. As a result, some vendors questioned whether they would be able to maximise value on exit.
More recently, however, owners of NHS practices have now seen a number of positive changes – including the softening of recruitment pressures and greater stabilisation of UDA rates.
Compared to the 12–18 months prior, operating an NHS practice has become more manageable. As such, we anticipate increased activity within the NHS practice market over the coming year. Combined with improved lending conditions and continued demand from individual dentists, transaction levels are likely
to rise, particularly in areas where recruitment is less of a challenge, such as London, Manchester, Birmingham, and Liverpool.
The impact of nHs contract changes
When assessing NHS contracts in dentistry, it’s helpful to consider both the percentage uplifts they’ve had and recent contractual changes. These changes have made it easier for practices to achieve UDA targets compared to previous years.
In practical terms, this allows practices to generate improved income outcomes for a similar, or in some cases reduced, level of clinical activity. Many practices are now being awarded more UDAs relative to workload than at the same point last year.
Practices brought to market previously while underperforming against UDA targets often faced valuation challenges. Buyers and lenders were understandably cautious due to the risk of breach notices or potential contract loss. By contrast, NHS practices entering the market today are typically operating with greater confidence in meeting contractual obligations. As a result, NHS and mixed practices are likely to be received more positively by buyers, supporting stronger pricing across the sector.
Groups, nHs, and private: who’s coming out on top?
Overall, in the group market – with Earnings Before Interest, Taxes, Depreciation, and Amortisation
above £200,000 – private and mixed practices are still king.
However, the independent market is going from strength to strength – especially for NHS dental practices. NHS contracts offer predictable income security, which lenders often view favourably when compared with purely private goodwill that may rely heavily on an individual principal.
While private practices may achieve higher EBITDA multiples, this does not automatically translate into stronger profitability. Associate remuneration in private dentistry typically sits between 45 and 50 percent of income, alongside increased laboratory and material costs.
Consequently, some of the most profitable opportunities remain high-performing NHS practices with strong UDA rates, where associate costs may sit closer to 30 to 32 percent. Practices operating with around 10,000 UDAs and limited private income continue to attract strong buyer interest, as purchasers recognise the opportunity to introduce private revenue and create additional value post-acquisition.
support when you need it
In a highly competitive and evolving marketplace, having experts on your side who have an in depth understanding of the nuances of dentistry can make a significant difference. With a team of experienced advisors across sales, acquisitions, recruitment, and finance, Dental
Elite combines market insight with transactional experience support clients in achieving the best possible deals for their circumstances.
support when you need it
In a competitive and evolving marketplace, having experienced advisers with a detailed understanding of the dental sector can make a significant difference. With specialist teams across practice sales, acquisitions, recruitment and finance, Dental Elite combines market insight with transactional experience to support clients in achieving the best possible outcome for their circumstances.
Market outlook
Looking ahead to 2026, we expect larger groups to re-enter the market more actively, although competition from independent buyers seeking value opportunities may limit rapid expansion.
At the same time, NHS practices are expected to continue growing in popularity, supported by improved target achievement and increased operational stability.
For more information on Dental Elite visit www.dentalelite.co.uk, email info@dentalelite.co.uk or call 01788 545 900 n
about the author
Luke Moore, founder and Director of Dental
elite.
(EBITDA)
What’s Your Dental Practice Really Worth in Today’s Market?
Get your copy of the 2025/26 Goodwill Report
Built on real valuations from across the UK market, so whether you’re buying, selling or planning ahead, you can act with confidence.