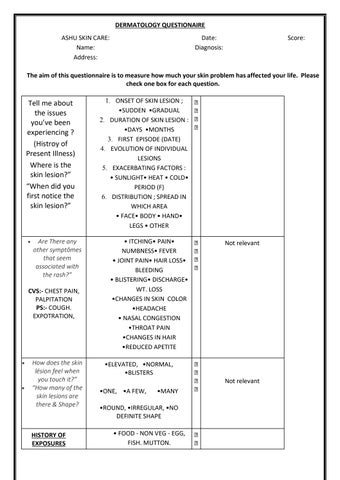
DERMATOLOGY QUESTIONAIRE ASHU SKIN CARE: Name: Address:
Date: Diagnosis:
Score:
The aim of this questionnaire is to measure how much your skin problem has affected your life. Please check one box for each question.
Tell me about the issues you’ve been experiencing ? (Histroy of Present Illness) Where is the skin lesion?” “When did you first notice the skin lesion?”
Are There any other symptômes that seem associated with the rash?”
CVS:- CHEST PAIN, PALPITATION PS:- COUGH. EXPOTRATION,
How does the skin lésion feel when you touch it?” “How many of the skin lesions are there & Shape?
HISTORY OF EXPOSURES
1. ONSET OF SKIN LESION ; •SUDDEN •GRADUAL 2. DURATION OF SKIN LESION : •DAYS •MONTHS 3. FIRST EPISODE (DATE) 4. EVOLUTION OF INDIVIDUAL LESIONS 5. EXACERBATING FACTORS : • SUNLIGHT• HEAT • COLD• PERIOD (F) 6. DISTRIBUTION ; SPREAD IN WHICH AREA • FACE• BODY • HAND• LEGS • OTHER • ITCHING• PAIN• NUMBNESS• FEVER • JOINT PAIN• HAIR LOSS• BLEEDING • BLISTERING• DISCHARGE• WT. LOSS •CHANGES IN SKIN COLOR •HEADACHE • NASAL CONGESTION •THROAT PAIN •CHANGES IN HAIR •REDUCED APETITE
Not relevant
•ELEVATED, •NORMAL, •BLISTERS Not relevant •ONE, •A FEW,
•MANY
•ROUND, •IRREGULAR, •NO DEFINITE SHAPE • FOOD - NON VEG - EGG, FISH. MUTTON.
HISTORY OF ALLERGIES DRUGS FOOD SEASONAL
HISTORY OF PAST ILLNESS •DIABETES. •HYPERTENSION • TUBERCULOSIS
•VEG – MUSHROOM, BRINJAL. • PETS & INSECTS. • CONTACT HISTORY: SOAP, ROOM CLEAN • H/O TO ANY MEDICATION DRUGS, IMMUNIZATION •PAST HISTORY OF SKIN DISORDER •GENERAL MEDICAL HISTORY •ALLERGY DESEASES./ TO DRUGS. •ANY OTHER CHRONIC MEDICATION:WHEN , WHAT MEDICATIONS COMPLIANCE , CONTROLLED
Not relevant
Not relevant
“Have you tried •Very much •A lot • A little •Not any treatments for at alL your rash?” OINTMENTS “Did they make TOPICAL STEROIDS any difference? ANTIBIOTICS IMMUNO SUPPRESSANTS
“Have you been in contact with anyone recently who had an infectious disease or skin problems like yours?”
YES
Do you have any medical conditions?” “Are you currently seeing a doctor or specialist regularly?”
Very much A lot A little Not at all
OBGYN HISTORY FOR FEMALE PATIENTS PERIODS
Not relevant
Not relevant NO
•REGULARITY•FLOW•PADS PER DAY •CRAMPS•PREGNANCY•AB ORTION
Not relevant
Not relevant
•ABNORMAL VAGINAL DISCHARGE SOCIAL HISTORY
ANY SPECIFIC DIET HISTORY
HISTORY OF PREVIOUS HOSPITALISATION FAMILY HISTORY
SMOKING :•DURATION •NO. OF CIGARETTES PER DAY INTERESTED TO QUIT ALCOHOL:•DURATION•AMOUNT•INTERESTED TO QUIT •FOR DIABETES •FOR HYPERTENSION •FOR HIGH CHOLESTEROL•FOR WEIGHT LOSS •FOR MUSCLE GAIN COVID ANY TRAUMA
DISEASES RUNNING IN FAMILY
Not relevant
Not relevant
Not relevant
ANY ALL CONTACTS RECENTLY
Pelasse check You have answered EVERY question. Tank You.