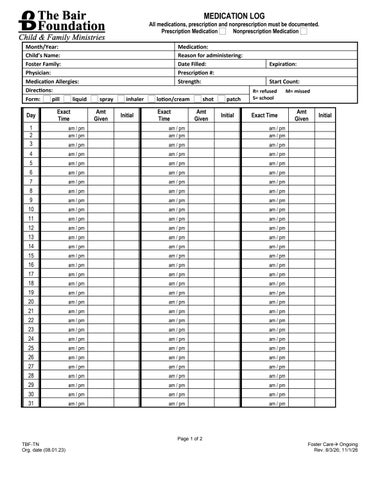
MEDICATION LOG
All medications, prescription and nonprescription must be documented. Prescription Medication Nonprescription Medication Month/Year: Child’s Name: Foster Family: Physician: Medication Allergies: Directions: Form: pill liquid Day
Exact Time
Medication: Reason for administering: Date Filled: Prescription #: Strength: spray Amt Given
inhaler Initial
lotion/cream Exact Time
shot Amt Given
patch Initial
Expiration: Start Count: R= refused S= school
Exact Time
1 2 3
am / pm am / pm
am / pm am / pm
am / pm am / pm
am / pm
am / pm
am / pm
4
am / pm
am / pm
am / pm
5
am / pm
am / pm
am / pm
6
am / pm
am / pm
am / pm
7
am / pm
am / pm
am / pm
8
am / pm
am / pm
am / pm
9
am / pm
am / pm
am / pm
10
am / pm
am / pm
am / pm
11
am / pm
am / pm
am / pm
12
am / pm
am / pm
am / pm
13
am / pm
am / pm
am / pm
14
am / pm
am / pm
am / pm
15
am / pm
am / pm
am / pm
16
am / pm
am / pm
am / pm
17
am / pm
am / pm
am / pm
18
am / pm
am / pm
am / pm
19
am / pm
am / pm
am / pm
20
am / pm
am / pm
am / pm
21
am / pm
am / pm
am / pm
22
am / pm
am / pm
am / pm
23
am / pm
am / pm
am / pm
24
am / pm
am / pm
am / pm
25
am / pm
am / pm
am / pm
26
am / pm
am / pm
am / pm
27
am / pm
am / pm
am / pm
28
am / pm
am / pm
am / pm
29
am / pm
am / pm
am / pm
30
am / pm
am / pm
am / pm
31
am / pm
am / pm
am / pm
TBF-TN Org. date (08.01.23)
Page 1 of 2
M= missed
Amt Given
Initial
Foster Care Ongoing Rev. 8/3/26; 11/1/26
Child’s Name: ______________________________
Month/Year: _______________
Medication: _______________________________
Signature and Initials of anyone who is authorized to administer medication, including respite providers: Signature Initials Signature
Initials
Document the following incidents below: 1. Any missed medications and the reason, including if the child refused to accept medication 2. Any other medication incidents such as adverse reaction or change in behavior. 3. School or Respite (Document amount of medication given to school/respite provider) 4. Medication discontinued? If YES, who approved and date discontinued. Also document how discontinued medication was discarded in accordance with The Bair Foundation Policy. 5. Medication changed? If Yes, who approved and date changed 6. *CHILDREN SHOULD NOT MISS ANY DOSES OF MEDICATION – If a dose is missed, contact your Care Coordinator or director immediately and document your conversation below. Date Medication Related Incident, New Medication, or Discontinued Medications Initial
If a caregiver finds a medication error, the caregiver must contact a healthcare professional immediately and follow the healthcare professional’s recommendations. Medication Error Documentation: Initial Document conversation along with whom has been notified -
Document Child’s Response to Medication:
Positive
Negative
Initial
If Negative, Why?
Document all scheduled and unscheduled appointments for medication monitoring below. If a visit is cancelled, explain why. Date
Scheduled and Unscheduled Medication Monitoring Appointments
For Bair Care Coordinator Use Only:
Correct dosage was given each time Actual times are written for each dosage, including a.m./p.m. Each entry is initialed No ditto marks on the form No blanks on form
Initial
Any changes in prescriptions given exactly according to written directions from physician
Page 2 completed with all necessary signatures and initials Page 2 completed for all changes, respite doses, school doses Page 2 completed for all psychiatric med check appointments
My signature below verifies this Medication Log has been reviewed for accuracy and found to be correct. Monthly pill count: _________
Bair Care Coordinator Signature: ______________________________
TBF-TN Org. date (08.01.23)
Page 2 of 2
Foster Care Ongoing Rev. 8/3/26; 11/1/26